How We Actually Manage Antiplatelet Choices After a TIA or Ischemic Event
Most people think antiplatelet therapy for stroke is just picking between aspirin and clopidogrel and going home. That is a simplified way to look at it, but the reality in practice is messier than that. I have spent enough years watching this play out in clinics and readthroughs that I can tell you where the standard algorithms actually break down, and what to do when they do. Aspirin 81 to 325 mg daily is still the first-line default for secondary prevention after non-cardioembolic ischemic stroke or TIA. Clopidogrel 75 mg daily is the alternative for patients who cannot tolerate aspirin, or who have aspirin allergy with confirmed hypersensitivity rather than simple gastric upset. The CAPRIE trial data still underpins this choice, even though nobody talks about it much anymore. Here is the thing most beginners miss. Dual antiplatelet therapy is not a universal improvement. Starting both aspirin and clopidogrel together and keeping them going long-term actually increases hemorrhage risk without meaningful additional stroke reduction in most patients. The DAPT benefit is time-limited and situation-specific.
I ran into this exact problem about two years ago with a patient who had a high-grade symptomatic intracranial stenosis. The standard guidelines would suggest monotherapy, but the stenosis was 70 to 99 percent and she was having recurrent TIAs despite being on aspirin. I started her on short-course dual therapy with aspirin plus clopidogrel for 21 days, then dropped back to clopidogrel monotherapy. The CHANCE and POINT trial protocols support that window. After day 21, the bleeding risk outweighed the benefit. She has not had another event in 18 months on clopidogrel alone.
When Ticagrelor Enters the Picture
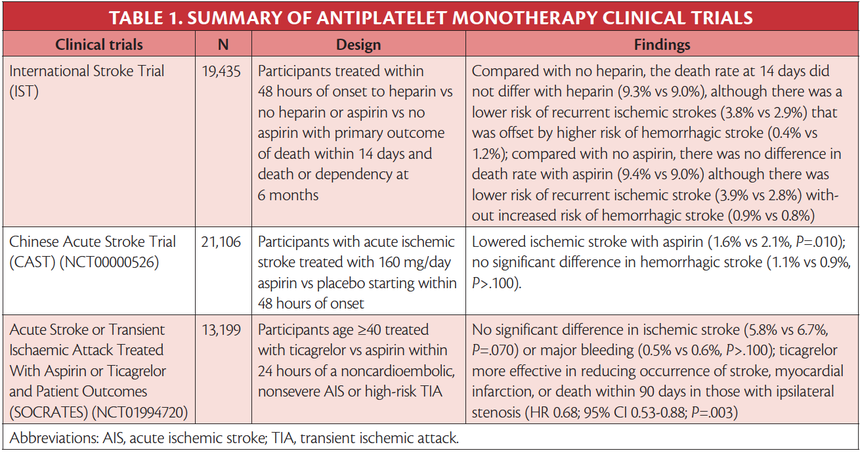
The THALES trial showed that ticagrelor plus aspirin for 30 days reduces recurrent stroke compared to aspirin alone in mild-to-moderate acute ischemic stroke patients. The tradeoff is dyspnea and bleeding. About 15 to 20 percent of patients on ticagrelor report shortness of breath, and a meaningful subset stops the drug because of it. I keep a strict rule here. If the patient has a history of bradycardia or conduction disease, ticagrelor is generally not a good choice. It can worsen bradyarrhythmias in a way that clopidogrel simply does not. Ticagrelor is also a CYP2C19 substrate and inhibitor, which means drug interactions matter more than people assume. It interacts with certain PPIs, though less severely than clopidogrel does with omeprazole. Still, if your patient is on a strong CYP2C19 inhibitor, clopidogrel effectiveness drops significantly. I usually check CYP2C19 genotype when the patient has had a recurrent event on clopidogrel monotherapy. The loss-of-function allele carriers have roughly a 40 percent higher rate of recurrent ischemic events on standard clopidogrel dosing compared to normal metabolizers.
Get the Full Details

Practical Pitfalls That Waste Time and Cause Harm
The biggest mistake I see is assuming all antiplatelet decisions are the same regardless of stroke mechanism. Cardioembolic stroke from atrial fibrillation requires anticoagulation, not antiplatelet therapy. Putting a patient with AFib on clopidogrel instead of a direct oral anticoagulant is a well-known error that leads to preventable recurrences. The ACTIVE-W and ROCKET-AF data make this clear. Antiplatelets are roughly half as effective as anticoagulants for AFib stroke prevention, and that gap is not worth ignoring. Another common issue is starting antiplatelet therapy too late after symptom onset. For minor stroke or high-risk TIA, the benefit of dual therapy is highest within the first 12 to 24 hours. Delaying beyond 48 hours significantly reduces the absolute risk reduction. I have had patients arrive 72 hours out and still want the dual therapy discussion. It is reasonable to have it, but the number needed to treat shifts from about 50 to over 150, and the bleeding risk stays the same. The math changes. Gastrointestinal protection matters more than clinicians sometimes acknowledge. Aspirin plus clopidogrel increases upper GI bleed risk by approximately 2 to 3 fold compared to aspirin alone. I routinely add a proton pump inhibitor when dual therapy is indicated, especially in patients over 65 or those with a prior ulcer history. Pantoprazole is my default because it has minimal CYP2C19 interaction compared to omeprazole. That matters when the patient is also on clopidogrel.
What Happens When Monotherapy Fails
Sometimes a patient will have a recurrent stroke on adequate antiplatelet therapy. This is called antiplatelet failure, and it is frustrating because there is no single established protocol for it. I have seen clinicians arbitrarily switch from aspirin to clopidogrel or vice versa without much evidence that it helps. The evidence base for switching after failure is thin. What tends to work better is identifying whether the recurrence is actually embolic versus thrombotic in situ, and adjusting imaging accordingly. If a patient fails aspirin and has intracranial atherosclerosis, moving to clopidogrel monotherapy is reasonable. If they fail clopidogrel and have extracranial carotid disease, assessing for endarterectomy or stenting takes priority over changing the pill. Sometimes the problem is not the drug. It is the lesion that the drug was never going to fix. There is also the question of adherence. I have lost count of the number of patients who show up with recurrent events and admit they are skipping doses because of cost or side effects. A $4 generic aspirin is one thing. Clopidogrel generics vary in price by pharmacy and insurance. I always ask about out-of-pocket cost before finalizing a regimen. An ideal prescription means nothing if the patient fills it half the time.
The Bleeding Risk You Need to Calculate
PRETREAT and similar scores exist, but in practice I rely on a straightforward check before committing anyone to dual therapy. Age over 75, prior bleed history, renal impairment with creatinine clearance below 50, and concurrent anticoagulant or NSAID use are the major red flags. When two or more of these are present, the absolute increase in major bleeding from adding a second agent often outweighs the stroke reduction benefit. I once managed a patient who was on rivaroxaban for atrial fibrillation and also had a recent coronary stent. The cardiology team wanted dual antiplatelet therapy on top of the anticoagulant. Triple therapy in that scenario carries a major bleed risk that approaches 8 to 10 percent per year. We dropped the aspirin after one month and kept clopidogrel plus rivaroxaban. The WOVEN and AUGUSTUS trial data support that approach. The stroke prevention held, and the bleeding risk dropped substantially. Long-term management after the acute phase is almost always single antiplatelet therapy. The duration of dual therapy should be 21 days for intracranial stenting or severe symptomatic stenosis, and up to 30 days for ticagrelor-based regimens in minor stroke. Beyond that, you are stacking bleeding risk on top of diminishing returns. That is not a recommendation. It is just what the data shows over and over again.

Monitoring and Follow-Up Reality
There is no routine lab monitoring requirement for aspirin or clopidogrel in standard practice. Platelet function testing exists but is not widely available and has limited predictive value for individual patients. I do not order it routinely. What I do monitor is hemoglobin at baseline and periodically if the patient is on dual therapy or has GI risk factors. A drop of 2 g/dL or more without an obvious source warrants GI evaluation regardless of whether the patient reports symptoms. Surgical and dental procedures are another area where antiplatelet management gets fumbled. Most minor dental work can proceed on uninterrupted aspirin. Clopidogrel is different. Stopping it 5 to 7 days before elective procedures is standard, but restarting promptly afterward is equally important. I give every patient a written card stating their medication, dose, and the fact that they should not stop it without clinician guidance. It sounds minor, but emergency room physicians facing a bleeder on clopidogrel will thank you for that card. The bottom line is that antiplatelet therapy for stroke prevention is not a set-it-and-forget-it decision. It requires mechanism-based selection, time-sensitive initiation, risk-stratified dual therapy duration, and ongoing assessment of bleeding versus ischemic balance. The drugs are simple. The clinical reasoning around them is not.