
Handling Anxiety, OCD, and Related Disorders in Clinical Settings
I have spent years working with patients who present with anxiety and obsessive-compulsive spectrum conditions. The documentation, assessment, and treatment pathways are more convoluted than most people realize. This is not a problem with a clean solution. It requires patience and a willingness to navigate systems that were not designed with these disorders in mind. The term you are searching for likely refers to assessment tools and diagnostic criteria used when evaluating patients with these conditions. In practice, the ATI (Assessment and Treatment Interface) framework helps clinicians standardize how they approach these disorders. It covers everything from initial screening to ongoing monitoring. I remember a case where a patient had been misdiagnosed for three years. They presented with what looked like generalized anxiety disorder, but their compulsive behaviors were being overlooked. The standard screening tools did not catch it because the questions were framed around anxiety symptoms, not the ritualistic patterns underneath. I had to go back and re-interview them using a structured OCD inventory. That changed everything about the treatment plan.
The Assessment Process
Getting an accurate diagnosis takes longer than most people expect. The typical workflow involves several steps, and each one has its own pitfalls. Step one is the initial screening. Most clinics use the GAD-7 for anxiety and the Y-BOCS for obsessive-compulsive symptoms. These are quick questionnaires, but they miss a lot. The GAD-7 does not differentiate between types of anxiety. It treats social anxiety the same as panic disorder. The Y-BOCS is better for OCD but only captures obsessions and compulsions. It does not account for related disorders like body dysmorphic disorder or excoriation. Step two is the clinical interview. This is where most assessments fall apart. Clinicians rush through it. They ask the standard questions and move on. I spend at least forty-five minutes on this part. I ask about the patient's daily routine, their sleep patterns, what triggers their symptoms, and how they cope. The answers reveal patterns that standardized tests cannot detect.
Step three is differential diagnosis. This is the hardest part. Anxiety and OCD symptoms overlap with many other conditions. ADHD can look like anxiety. Autistic burnout can look like OCD. Even thyroid issues can present as anxiety. I once had a patient whose anxiety was actually caused by a thyroid condition. The SSRI they were prescribed made it worse before we figured it out. Blood work should be routine, not optional.
Get the Full Details

Treatment Approaches
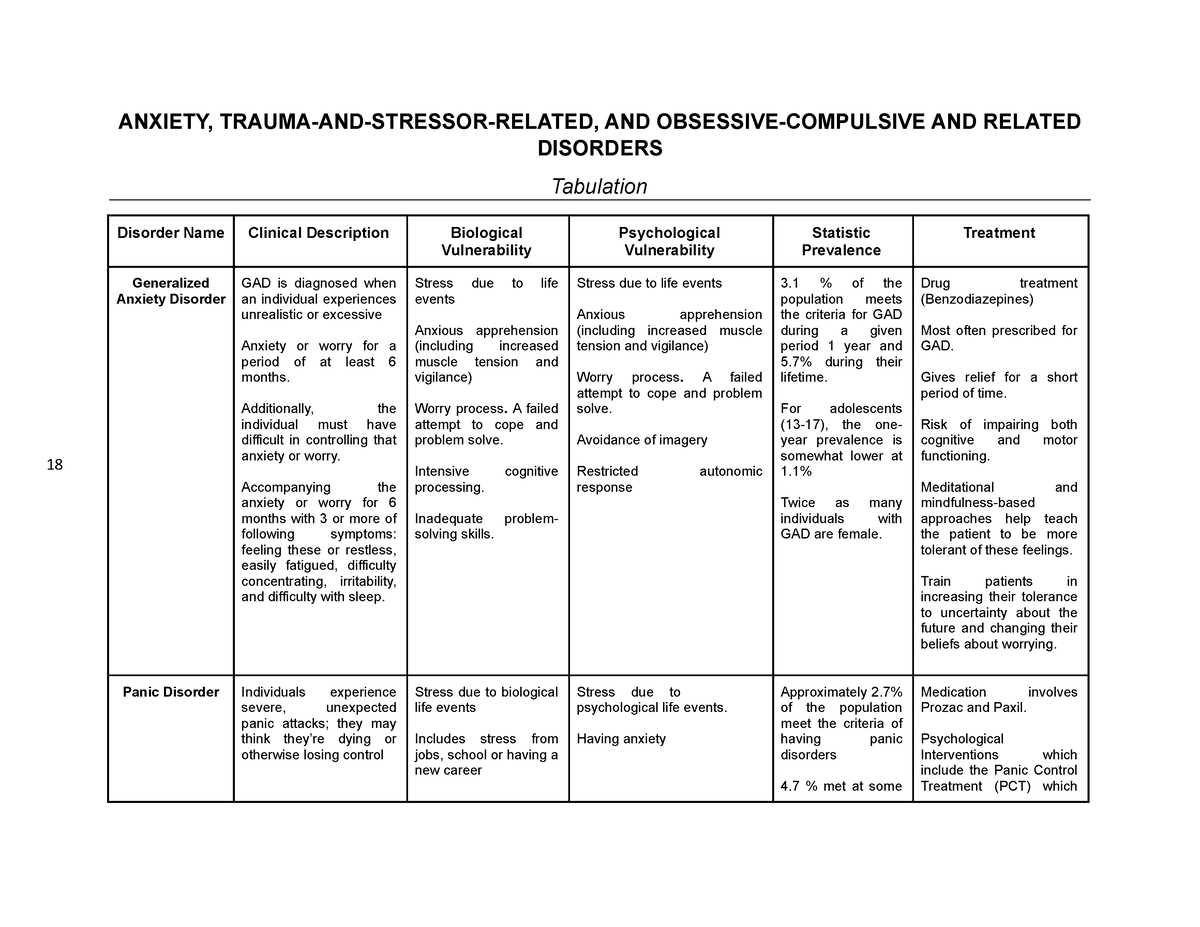
Treatment for these disorders is not one-size-fits-all. The evidence supports several approaches, but each has limitations that are rarely discussed. SSRIs are the first line of medication. Sertraline, fluoxetine, fluvoxamine, and paroxetine are all FDA-approved for OCD. The typical dose for OCD is higher than for depression. Many clinicians start too low. I have seen patients stay on twenty milligrams of sertraline for months because the prescriber was uncomfortable going higher. OCD often requires two to three times the antidepressant dose. It takes six to eight weeks at the target dose to see results. Patience is required. ERP is the gold standard therapy. Exposure and Response Prevention involves deliberately triggering anxiety and then preventing the compulsive response. It sounds simple. It is not. The anxiety can be overwhelming. Drop-out rates for ERP are around thirty percent. Most people quit because the process is unpleasant. The therapists need to be well-trained. Not all CBT therapists are. I have seen patients assigned to therapists who did not understand ERP properly. They ended up doing relaxation techniques instead of exposure. That does not work for OCD.
Combination treatment is often necessary. Medication plus therapy works better than either alone for moderate to severe cases. The data supports this. But getting both simultaneously is difficult. Wait times for ERP specialists can be six to nine months. Many patients start medication and wait. Some improve on medication alone. Most do not. The window for effective treatment is not infinite, but it is also not urgent in the way emergency medicine is. This gap causes real suffering.
Common Pitfalls to Avoid
There are several mistakes that happen repeatedly in clinical practice. Knowing them helps you navigate the system. Pitfall one is under-treating. Mild anxiety and OCD are often dismissed as normal stress. Patients are told to try meditation or exercise. Those are helpful adjuncts, but they are not treatment for clinical disorders. If symptoms interfere with daily functioning, professional help is needed. Insurance companies sometimes push back on this. They want to see severity before approving therapy or medication. Keep documenting the impact on work, relationships, and basic functioning. Pitfall two is over-reliance on medication. SSRIs help, but they are not a cure. Many patients expect medication to remove the symptoms entirely. It does not. It reduces the intensity. Therapy is still required. I have seen patients stop therapy once they feel better on medication. The symptoms return when they stop the medication. The underlying patterns were never addressed. Medication manages symptoms. Therapy changes behavior.
Pitfall three is misattributing symptoms. Anxiety and OCD are frequently misdiagnosed as personality disorders or even psychosis. The rituals in OCD can look like delusions to untrained observers. The avoidance in anxiety can look like schizophrenia-related withdrawal. Proper training in differential diagnosis is essential. If your provider is unsure, seek a second opinion from a specialist.
Navigating Insurance and Access
Access to care is a major barrier. I deal with this almost daily. Here is what I have learned about working within the system. Insurance coverage for mental health has improved under parity laws, but gaps remain. Many plans limit the number of therapy sessions. Twenty sessions a year is common. That is roughly one session a month for six months. For ERP, that is nowhere near enough. I typically recommend sixty to one hundred sessions for a full course of treatment. You will need to advocate for more or find a therapist willing to work within the limitation. Some therapists offer sliding scale fees. Community mental health centers provide lower-cost options. University clinics have training programs with supervised graduate students offering reduced rates. These are legitimate options. The quality can vary, but supervision ensures baseline competence.
Documentation matters. When appealing insurance denials, detailed documentation from your provider is crucial. Letters of medical necessity should include specific diagnoses, functional impairments, and treatment plans. Generic letters are less effective. Push back when insurance companies deny coverage. The appeals process is slow but often successful on the second or third attempt.

Self-Management Strategies
Professional treatment is ideal, but not always accessible. There are evidence-based strategies you can use independently. Psychoeducation is the foundation. Understanding your condition reduces fear and increases motivation. Read about OCD and anxiety from reputable sources. The IOCDF and ADAA websites have patient resources. Books like Brain Lock by Jeffrey Schwartz explain ERP in accessible terms. Knowledge alone does not cure, but it helps you engage with treatment. Self-monitored ERP is possible. The workbook Freedom from Obsessive Compulsive Disorder by Jonathan Grayson guides readers through ERP exercises. It requires honesty and consistency. The exercises are uncomfortable by design. If you skip the discomfort, the technique does not work. Commit to at least thirty minutes daily for several months.
Lifestyle factors matter. Sleep, exercise, and caffeine reduction all impact anxiety and OCD symptoms. Poor sleep increases symptom severity. Caffeine can trigger panic attacks and worsen obsessive thoughts. Exercise reduces anxiety through physiological mechanisms. These are not substitutes for treatment, but they support it. I have patients who ignore sleep and wonder why their symptoms fluctuate. Support groups help. OCD and anxiety can feel isolating. Connecting with others who understand reduces shame. Online communities exist but vary in quality. Look for moderated groups with professional oversight. The OCD Foundation has local and virtual support groups.
When to Seek Immediate Help
Most anxiety and OCD cases are not emergencies. But certain situations require urgent attention. Suicidal ideation is always an emergency. Severe OCD and anxiety can lead to hopelessness. If you are having thoughts of suicide, contact crisis services immediately. The 988 Suicide and Crisis Lifeline is available twenty-four seven. Do not wait. Treatment can help, but safety comes first. Inability to perform basic self-care indicates severity. If OCD rituals prevent eating, sleeping, or hygiene, this is a medical concern. Hospitalization may be necessary. I have admitted patients who had not eaten in days because compulsions consumed their time. This is rare but real.

Panic attacks can be frightening but are not dangerous. They feel life-threatening. They are not. Knowing this reduces secondary anxiety about the attacks themselves. If you are unsure, get medical evaluation to rule out cardiac issues. Once cleared, you can focus on treatment.
What the Research Says
Evidence-based treatment for anxiety and OCD is well-established. The question is access, not efficacy. Meta-analyses show ERP effect sizes around two points. That is large. Medication effect sizes are smaller, around zero to point six. Combination treatment shows additive effects. Relapse rates after medication discontinuation are high, around seventy percent. Relapse after ERP is lower, around thirty percent. Therapy teaches skills that persist. New treatments are emerging. Deep brain stimulation is approved for treatment-resistant OCD. It is invasive and expensive. Psilocybin-assisted therapy is being studied. Early results are promising but preliminary. Clomipramine, a tricyclic antidepressant, is effective for OCD but has more side effects than SSRIs. It is usually reserved for cases that do not respond to first-line treatments.
The Anxiety Obsessive Compulsive And Related Disorders Ati guidelines from professional organizations are updated periodically. The APA and IOCDF publish practice parameters. These are not law. They are recommendations based on available evidence. Deviations are justified when individual patient needs differ from the average.

Personal Observations
I have treated hundreds of patients with these disorders. A few patterns stand out. Early intervention improves outcomes. Patients who receive treatment within two years of symptom onset do better than those who wait longer. Chronicity reinforces neural pathways. The longer symptoms persist, the harder they are to change. This does not mean late treatment fails. It means earlier is better. Family involvement can help or hinder. Educated families provide support. Enabling families accommodate rituals and make treatment impossible. I instruct families to stop helping with compulsions. This is difficult for them. They want to reduce their loved one's distress. But accommodation maintains the disorder long-term. Family psychoeducation is a valuable component of treatment.
Comorbidity is the rule, not the exception. Depression occurs in sixty percent of OCD patients. Other anxiety disorders co-occur frequently. Substance use is common as self-medication. Treatment should address all active conditions. Focusing only on OCD while ignoring depression often leads to poorer outcomes. The stigma persists despite progress. Patients hide symptoms because they feel ashamed. Compulsions are often private. Obsessions can be terrifying. Disclosure is a gradual process. Creating a nonjudgmental environment is essential for honest communication.
Resources
The International OCD Foundation maintains a provider directory and educational materials. Psychology Today has a therapist finder with filters for OCD and anxiety. The Anxiety and Depression Association of America offers webinars and support group listings. Books and workbooks are available through most retailers. Online programs exist but vary in quality. Choose evidence-based options. Crisis support is available through the 988 line and text-based services. For non-urgent questions, telehealth platforms connect patients with licensed providers. Insurance directories list in-network providers. Starting the search early reduces wait times. Treatment works. It is not easy. It requires effort and time. But recovery is possible. Many patients achieve remission. Others learn to manage symptoms effectively. The goal is not perfection. It is functionality and quality of life.
