Writing Anxiety Related To Nursing Diagnosis Correctly
Most nursing students and new grad nurses write this diagnosis completely wrong. I've graded hundreds of care plans and the same mistakes show up every time. Let me walk through what actually works in practice, not what the textbook says should work. The NANDA-I definition of Anxiety Related To Nursing Diagnosis centers on a vague sense of unease or dread that stems from a perceived threat, whether that threat is real, imagined, or anticipatory. The related factors (the "related to" part) determine everything about how you structure your interventions. Get the related factor wrong and your whole care plan drifts into irrelevant territory. This isn't theoretical. I watched a nurse spend three weeks trying to reduce a post-op patient's anxiety with breathing exercises alone, only to realize too late that the anxiety was actually related to uncontrolled pain, not the surgical experience itself. Breathing exercises don't fix pain.
Anxiety Related To Nursing Diagnosis: What Actually Changes
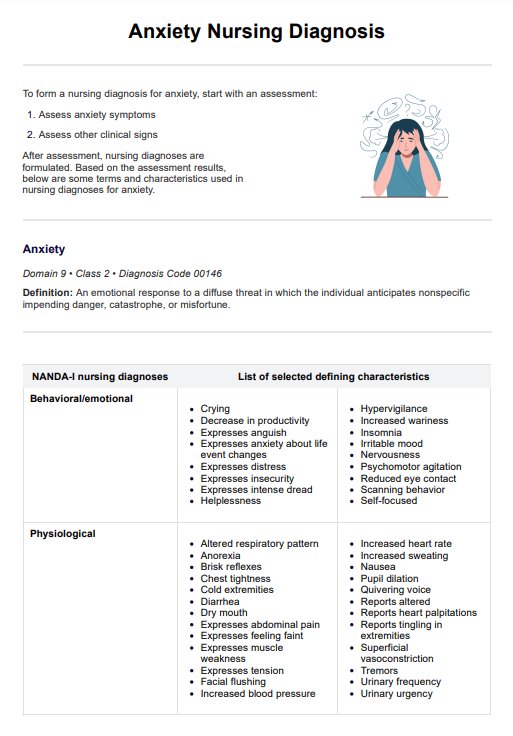
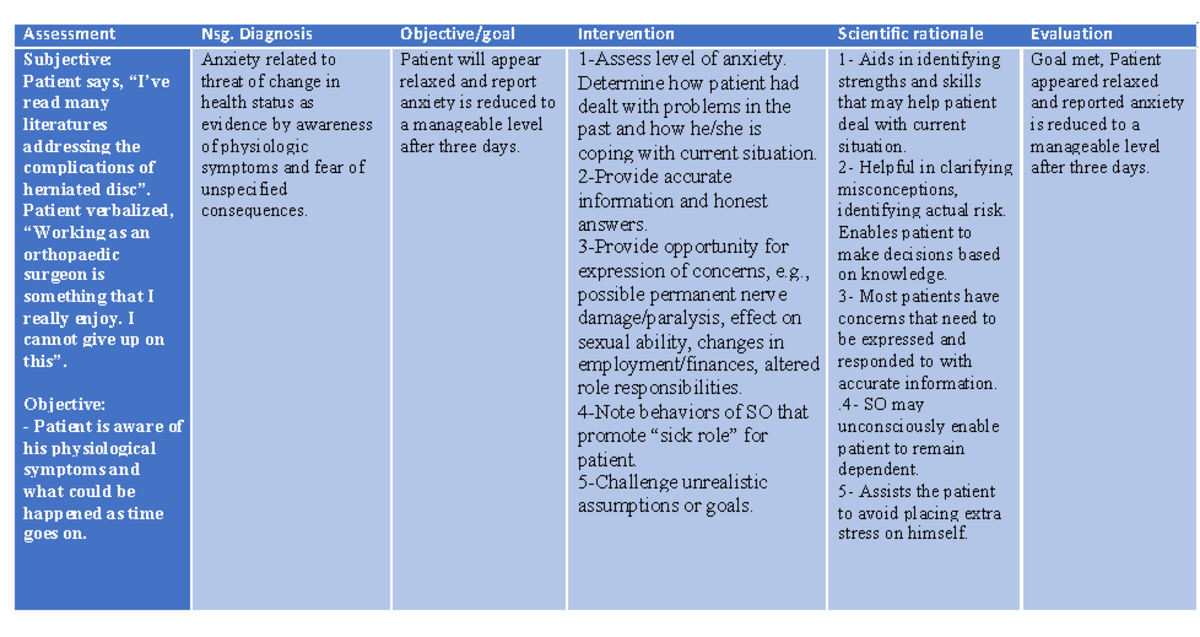
The related factors I see most often misidentified are the scary ones. Anxiety can be related to situational crises, physiological states, knowledge deficits, or environmental changes. The key distinction that most students miss is between anxiety and fear. Fear has a specific, identifiable source. Anxiety does not. If your patient can point at exactly what they're afraid of, that's fear, and you'd document it differently. If they say "I just feel like something bad is going to happen" without being able to name it, that's anxiety. Getting this wrong means you're treating the wrong problem. I ran into a specific edge case last year with a pre-surgical bariatric patient who scored high on every anxiety scale but became nearly unresponsive when I asked what was causing it. She kept saying she was fine. What I eventually figured out was that her anxiety was related to a history of prior traumatic intubation that nobody in the current chart had documented. Standard nursing assessments don't always surface this. The workaround I used was to ask specifically about prior anesthesia experiences and past surgical trauma rather than asking the generic "what are you worried about." It took the conversation in a completely different direction and let me address the actual source instead of performing anxiety reduction for a symptom that wasn't the root cause. When documenting the nursing diagnosis statement, the format needs to be precise. You write it as Anxiety related to [specific related factor] as evidenced by [specific subjective and objective data]. A properly written example: Anxiety related to anticipated surgical procedure as evidenced by patient verbalization of "I can't sleep because I'm worried about what they'll find" and observed tearfulness with tachycardia at 112 bpm during pre-op assessment. Notice the evidence includes both what the patient said and what you measured. Subjective data and objective data need to be there together, and they need to directly support the related factor you chose.
Interventions That Actually Work for This Diagnosis
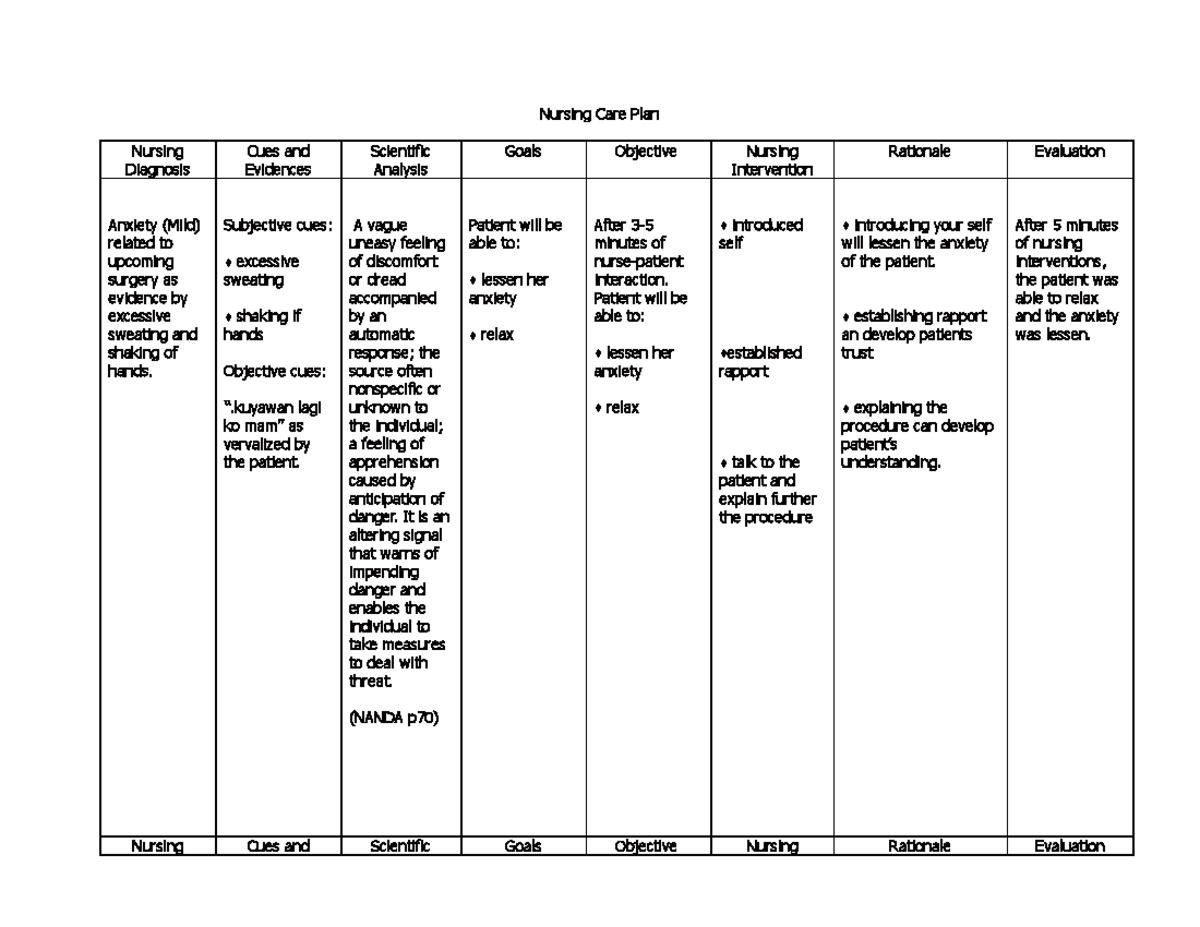
The interventions depend entirely on the related factor, which is why getting that part right matters so much. For anxiety related to situational crisis, the most effective approaches involve information provision, family presence, and controlled environment modifications. For anxiety related to physiological factors like hyperthyroidism or medication side effects, treating the underlying physiological cause is the primary intervention and anxiolytics are secondary. I've found that the standard nursing interventions for anxiety—therapeutic communication, relaxation techniques, environmental modification, and patient education—are only effective when they're matched to the correct related factor. Mismatched interventions waste time and create frustration on both sides. A patient whose anxiety is driven by chronic pain will not respond to guided imagery in any sustained way. The pain needs to be addressed first or simultaneously. Medication administration for anxiety falls under collaborative problems when benzodiazepines or SSRIs are involved. Nursing responsibilities here include monitoring for sedation, assessing respiratory status, checking for drug interactions, and evaluating therapeutic response. The nursing diagnosis still applies because the behavioral and psychological manifestations are within the nurse's scope, but the pharmacological management requires a provider order and ongoing collaboration.
Get the Full Details
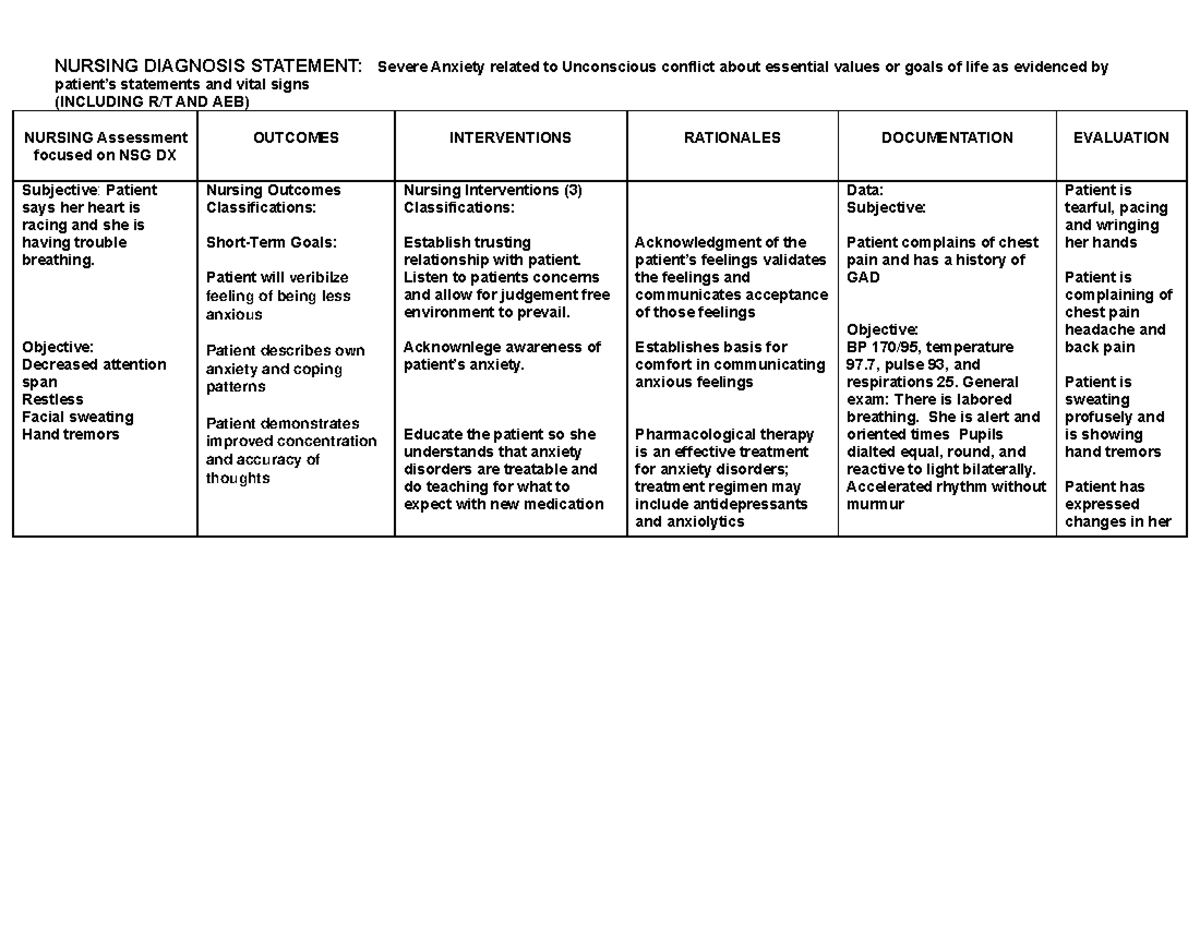
Documentation should reflect ongoing reassessment. Using a validated scale like the Hamilton Anxiety Rating Scale or the State-Trait Anxiety Inventory at regular intervals gives you measurable outcomes. Vague statements like "patient appears less anxious" are insufficient for either clinical handoff or legal documentation. You need baseline numbers and trend data. A patient whose score drops from 28 to 18 on the Hamilton scale over 72 hours tells a clear clinical story that a narrative description cannot match.
Common Mistakes That Undermine the Diagnosis
Writing Anxiety related to unknown as the related factor is a frequent error that I see constantly. It's technically defensible but clinically useless. Any competent reviewer will ask you to justify why you couldn't identify a specific factor, and if your assessment was thorough, you should have one. Try harder before settling on unknown. Another common mistake is confusing Anxiety with Disturbed Thought Processes or Impaired Coping. These are different diagnoses with different interventions. Anxiety is specifically about apprehension and tension. Disturbed Thought Processes involves cognitive distortion. Impaired Coping involves inadequate ability to manage stressors. Patients can and do have all three simultaneously, but each one needs its own diagnosis and its own care plan section. Combining them into one vague diagnosis makes your care plan harder to follow and harder to evaluate. Over-relying on pharmacological outcomes as the sole measure of success is another problem. Benzodiazepines reduce anxiety scores quickly, but they don't teach coping skills. A patient who is chemically sedated into compliance is not demonstrating effective coping. The nursing diagnosis should include outcome criteria that reflect behavioral and cognitive changes, not just medication effect. This is especially important if the patient is being discharged with ongoing anxiety management.
The biggest limitation of the Anxiety nursing diagnosis as a framework is that it doesn't account well for comorbid conditions. A patient with generalized anxiety disorder who is admitted for pneumonia will have anxiety that persists regardless of how well you manage the pneumonia. Standard nursing interventions for Anxiety Related To Nursing Diagnosis may provide temporary relief but won't resolve an underlying psychiatric condition. In these cases, the most honest approach is to document the anxiety accurately, implement appropriate nursing interventions, and ensure clear communication with the patient's psychiatric provider for coordinated care. Pretending the nursing diagnosis alone will solve the problem helps nobody. I also recommend against using Anxiety as a standalone diagnosis when the patient clearly meets criteria for a panic disorder or PTSD. These require specialized interventions that go beyond standard nursing care plan templates. Referencing the existing psychiatric diagnosis alongside the nursing diagnosis keeps the care plan accurate and prevents you from claiming outcomes you can't reasonably achieve with nursing interventions alone.