What a Diabetic Eye Exam Report Actually Contains
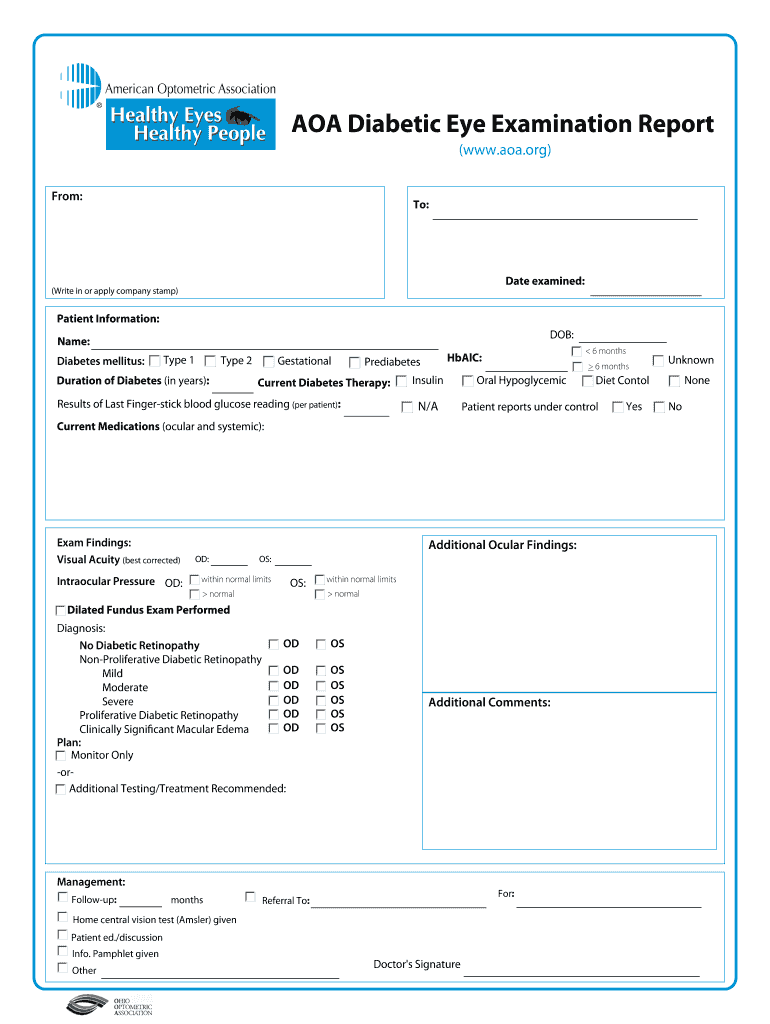
The AOA Diabetic Eye Exam Report is the documentation form that ophthalmologists and optometrists use to record findings during a comprehensive diabetic eye evaluation. It covers best-corrected visual acuity, intraocular pressure, slit-lamp examination results, dilated fundus findings, and the overall assessment of diabetic retinopathy severity. Most practices in the United States follow the American Optometric Association's clinical guidelines, which were updated most recently in 2021. The report itself isn't some proprietary software product. It's a structured clinical document. You'll find it in paper form at most offices, and increasingly as an electronic health record template. The AOA provides guidance documents and sample forms on their website for members, but the core structure is standardized enough that any eye care professional can work with it regardless of which specific form their office uses.
How to Read an Aoa Diabetic Eye Exam Report
I've spent years filling these out and explaining them to patients who bring their reports back to their endocrinologist. Here's what you need to know. The most critical section is the fundus examination findings. This is where diabetic retinopathy gets classified. The report will typically list one of the following: no retinopathy detected, mild non-proliferative diabetic retinopathy (NPDR), moderate NPDR, severe NPDR, or proliferative diabetic retinopathy (PDR). Some reports also include a separate field for diabetic macular edema (DME), which is significant because DME can exist independently of retinopathy stage and requires its own management pathway. Visual acuity numbers matter here, but not in the way people expect. A patient might have 20/25 vision and still have significant macular edema affecting their contrast sensitivity. The report records the Snellen acuity, but the clinician's note about whether the patient can read standard print or needs magnification often tells you more about functional vision than the acuity score alone.
I had a case last year where a patient's report showed only mild NPDR, but the dilated exam revealed cotton wool spots near the macula that weren't captured in the summary field. The written narrative in the exam notes section was where I caught it. That's the gap most people miss. The checkbox sections are quick to fill, but the free-text clinical impression is where the actual diagnostic work lives. Never skip reading that paragraph. Intraocular pressure readings get recorded twice on a proper report — after dilation and ideally before if there was a prior visit. Elevated IOP in a diabetic patient warrants a different follow-up cadence than a normotensive patient with the same retinopathy stage. I've seen reports where the IOP was noted but never referenced again in the assessment, which is a missed opportunity.
Get the Full Details
Where to Find and Download the Form
The AOA doesn't operate a public download portal for their clinical forms. Members have access to template documents through the member resources section of aoa.org. Non-member practitioners and patients usually encounter these reports through their own clinic's electronic health record system or as paper handouts provided at the time of examination. If you're a patient and you want a copy of your report, you're entitled to it under HIPAA. Request it from your provider's office. Most clinics will email a PDF or print a copy within a few business days. There's no fee they can legally charge for simply providing your own records. For clinicians building a new practice or updating their documentation workflow, the AOA's clinical practice guideline on diabetic eye examinations (available to members) includes a recommended structure for the exam report. The 2021 update added specific guidance on optic nerve head assessment and neovascularization elsewhere, which some older templates don't capture adequately.
Common Mistakes I See on These Reports
The first mistake is treating the report as a checklist instead of a clinical narrative. I've reviewed records where every box is checked but the assessment section reads like it was generated from a dropdown menu with no individualized thought. A patient with stable mild NPDR and controlled HbA1c gets the same checkbox pattern as a patient whose glucose has been uncontrolled for two years. The boxes look identical. The clinical meaning is completely different. The second mistake is omitting the reference to systemic control. The report should document whether the patient's diabetes is well-controlled, moderately controlled, or poorly controlled, along with the most recent HbA1c value. This directly affects follow-up timing recommendations. Without it, the endocrinologist receiving the report has no context. I ran into a problem once where a patient's report listed "mild NPDR" but didn't specify whether the finding was unilateral or bilateral. The retinal specialist who received the report assumed bilateral and ordered imaging for both eyes. When we clarified that only the right eye showed changes, the left eye was spared unnecessary dilated imaging and cost. This seems like a minor detail, but it happens more often than I'd like to admit. Always check whether laterality is documented.
Another issue is inconsistent terminology between visits. One year a report says "dot and blot hemorrhages," the next it says "microaneurysms and hemorrhages." Both describe the same finding at the mild NPDR level, but the inconsistency makes it harder to track progression over time. Standardize your language or at least add a note when you're using different terms for the same grade.

What the Report Doesn't Tell You
Here's the thing nobody emphasizes enough: a diabetic eye exam report is a snapshot, not a complete picture. The AOA guidelines recommend annual screening for type 2 diabetes and type 1 diabetes ten years post-diagnosis, but that interval assumes stable findings. If your report shows moderate NPDR, the next exam isn't in twelve months. It's in four to six. If it shows PDR, it's weeks, not months. The report also doesn't capture retinal thickness measurements. That requires OCT imaging, which is a separate diagnostic test. Some practices include OCT printouts with the exam report, but many don't. If you're managing diabetes and you want the full picture, ask whether OCT was performed and request those images separately. A final limitation is that the report reflects what the examiner saw during a single dilated examination. Early diabetic changes can be subtle and examiner-dependent. Two clinicians looking at the same retina might grade it slightly differently. This isn't a flaw in the report format — it's a reality of clinical grading. If you're ever unsure about a classification, a second opinion from a retinal specialist is worth the visit.
The report is a tool. It's useful when you read it carefully and use it to drive next steps. It's not useful when you file it away without understanding what each line actually means for your eye health.



