
Why the Competency Checklist Actually Matters
The AORN Operating Room Skills Competency Checklist is a structured evaluation tool that healthcare facilities use to verify that OR staff can safely perform their assigned clinical duties. It is not optional paperwork. Hospitals need it for credentialing, annual competency reviews, and survey readiness. The alternative is showing up to a TJC survey without documented proof that your nursing staff can competently operate equipment, follow sterile technique, and respond to emergencies. You do not want that conversation. It is a standardized form or framework—originally developed by the Association of periOperative Registered Nurses—that outlines specific knowledge, psychomotor, and professional behaviors expected of operating room personnel. Departments adapt it to match their actual skill sets, whether that is scrubbing cases, circulating, managing anesthesia equipment, or running surgical lasers. The core idea is simple: you define the skill, you create observable criteria, and you document whether the staff member meets the standard each review period. I worked in a 400-bed hospital where we had thirty different OR competency checklists spread across twelve folders. Each charge nurse maintained her own version. When surveyors asked for evidence of competency validation, we spent three days photocopying and organizing binder after binder. We wasted roughly forty hours per audit cycle just hunting for documentation. That was before we consolidated everything into a single digital framework tied to job descriptions.
How to Build and Use One Properly
Start by mapping every role in your surgical suite. Circulating nurses, scrub techs, anesthesia providers, and even support staff who enter sterile fields each have different required competencies. I once had a facility try to use a single blanket checklist for both OR nurses and surgical technologists. It collapsed during a mock survey because the evaluator asked a straightforward question about sterile gloving technique and nobody on the competency committee could answer which sections applied to whom. That mistake cost us a deficiency citation. Every entry needs three components: the skill being evaluated, the acceptable performance standard, and a clear rating mechanism. Use a scale like Not Yet Competent, Developing, Competent, or Advanced. Vague ratings like "Satisfactory" create ambiguity during audits. Be specific. Instead of writing "demonstrates knowledge of surgical instruments," write "correctly identifies and aseptically packages at least 90 percent of common orthopedic and general surgery instrument sets." Concrete criteria prevent evaluator drift between different reviewers. You also need to define the evaluation method. Direct observation is the gold standard but not always practical. I have seen departments rely heavily on self-assessment or chart review alone, which is inadequate for psychomotor skills. For procedures like surgical hand antisepsis, gowning, gloving, and instrument setup, you must watch the person perform the task. For knowledge-based items like surgical site preparation protocols or patient positioning guidelines, written assessments or verbal questioning work fine. Mix methods by skill type. Do not apply one method uniformly across the board.
Common Pitfalls I Have Seen
The most frequent failure mode is treating competency as an annual checkbox rather than a continuous process. I worked at a center where the entire OR staff completed their annual evaluations in two weeks. Evaluators rushed through observations, marked everything competent without truly watching, and then signed off on thirty pages of forms in a single sitting. That is not validation. That is a signature factory. Competency should be embedded into daily workflow. A brief focused observation during an actual case is more valuable than a ten-page simulated exercise done in a conference room. Another issue is using outdated standards. OR technology changes fast. If your checklist still references bipolar cautery settings from 2015 or lists old sterile draping protocols that no longer reflect current AORN guidelines, your documentation is technically incorrect. I once had a preceptor fail a new grad on a competency because the checklist required a drape configuration that had been superseded by updated evidence-based guidelines six months earlier. The evaluator was following a template he had not reviewed in three years. Fix your source documents annually.
Get the Full Details

Practical Implementation Steps
Step one: Gather the current AORN guidelines and your facility policies. Cross-reference them against your actual job descriptions. If a procedure appears in your checklist but nobody in your department performs it, remove it. If a procedure your department performs daily is absent from the checklist, add it with a clear criterion. Step two: Assign ownership. Designate a competency committee with representatives from nursing, surgical technology, anesthesia, and infection control. This committee should meet quarterly to review the checklist, update criteria based on policy changes, and train evaluators so scoring remains consistent across departments. Without standardization, you get the rater reliability problem where one evaluator is strict and another is lenient on the exact same skill. Step three: Choose your tracking system. Paper checklists are still used in some smaller hospitals but they create massive tracking headaches. Digital systems with built-in reminders for expiring competencies save real time. My facility moved to a cloud-based platform and cut our annual review completion rate from about 62 percent to 98 percent within the first year. The primary reason was automated alerts reminding staff and managers of upcoming due dates rather than relying on paper calendars or memory.
Step four: Document everything. The evaluation itself, the date, the evaluator signature, the staff member signature, and any remediation plans if the person did not meet the standard. Remediation is a critical piece that most checklists overlook. If someone scores Not Yet Competent, the form should include a section for a remediation plan with a specific timeline and a re-evaluation date. I have seen departments skip this entirely and just mark "needs improvement" without a follow-up, which leaves a gap in the legal record if something goes wrong clinically.
A Realistic Edge Case
Here is a scenario I dealt with directly. We had a traveling nurse who arrived with national certification and prior hospital competency documentation. She had performed countless laparoscopic cases. Our checklist required a hands-on skills assessment before she could independently circulate. She pushed back hard, saying her credentials should be accepted and she should not have to repeat training. The policy was clear: every clinician, regardless of background, completes the facility-specific checklist on their first shift in a new department. I let her complete a modified abbreviated version focusing only on our specific equipment and EHR system rather than the full clinical skills assessment. That took about twenty minutes instead of two hours. She felt respected, we maintained policy compliance, and she was cleared to work by end of day. The workaround of creating a streamlined bridging assessment for experienced travelers solved the conflict without compromising patient safety standards. Competency checklists are not a perfect solution. They create administrative burden. A single comprehensive OR competency program can require hundreds of evaluation forms per year across a mid-sized department. The time investment is real. Expect evaluators to spend roughly fifteen to twenty-five minutes per skill assessment depending on complexity. For a staff of fifty with thirty required competencies each, that is potentially 375 to 1,250 evaluator hours annually. Budget accordingly or you will burn out your charge nurses. Another limitation is that checklists measure minimum standards, not excellence. Passing a competency does not mean someone is a subject matter expert. It means they meet the baseline. I have seen highly competent surgeons and nurses get marked competent because they performed to the minimum criterion rather than demonstrating deeper proficiency. The form cannot capture nuance. Pair it with peer review and case-based discussions to fill that gap.
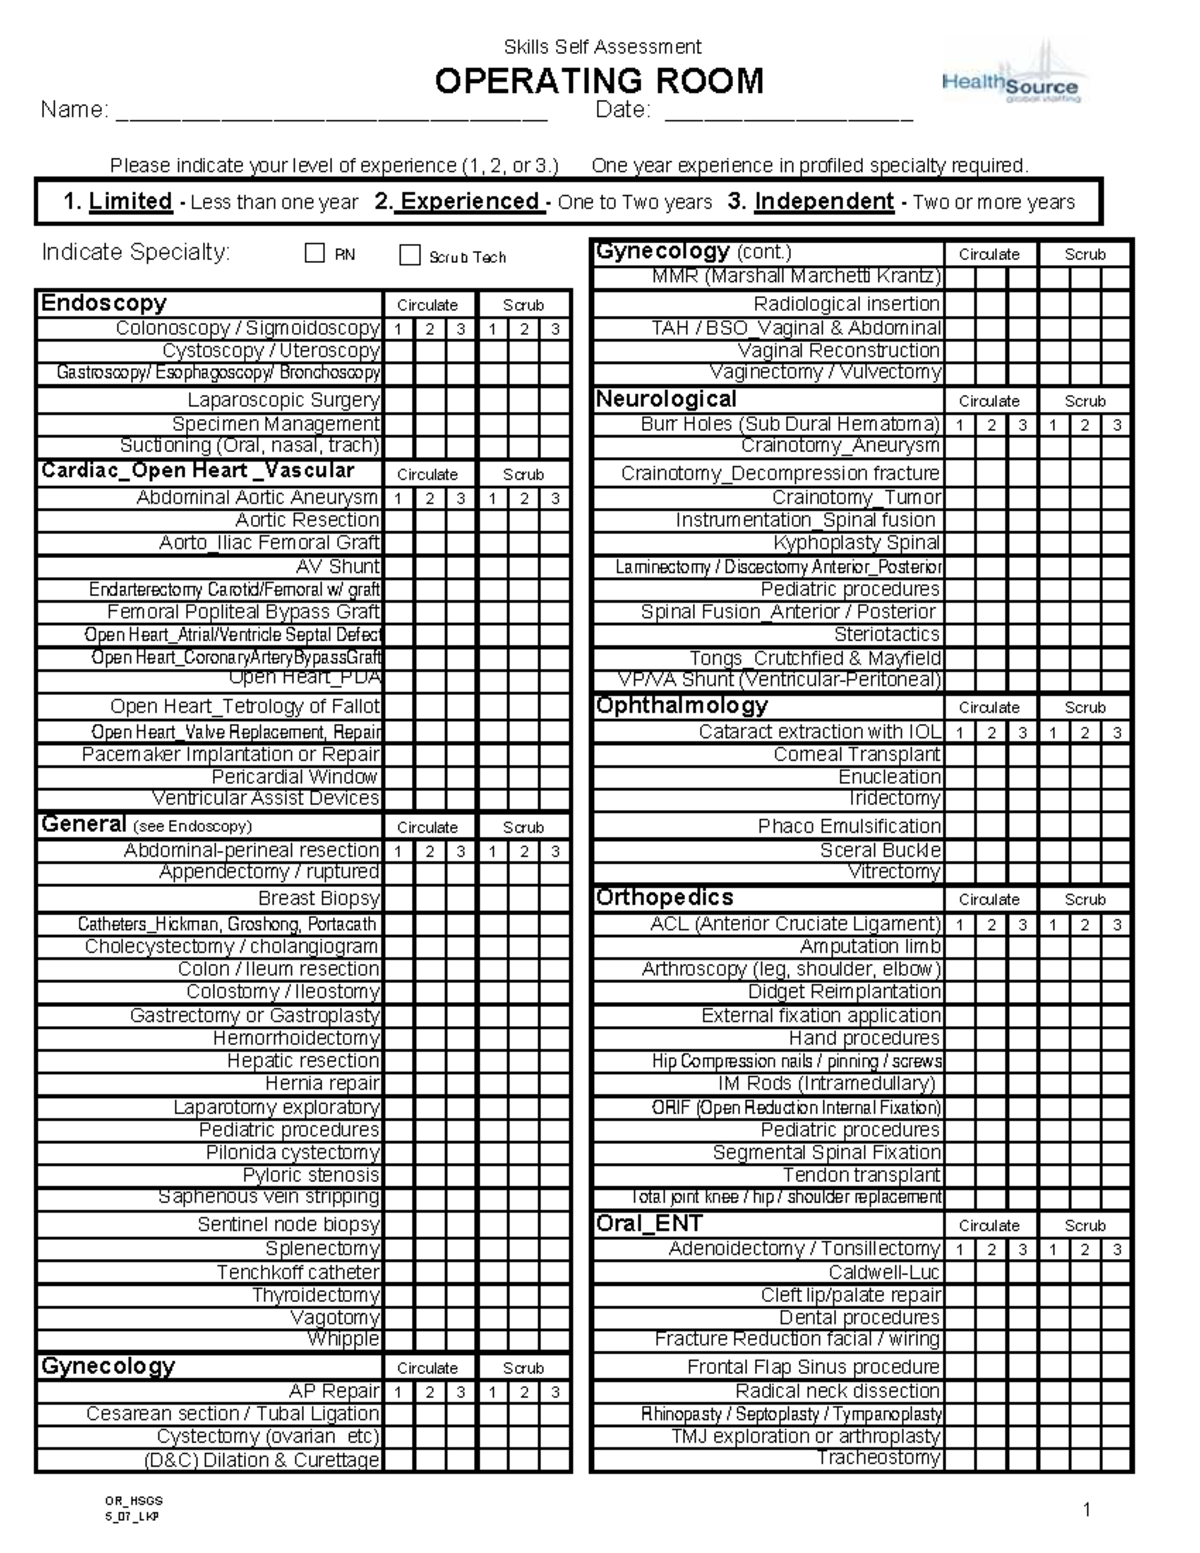
If your facility is small with limited resources, consider joining a regional healthcare network that shares standardized competency frameworks. Several communities in the Midwest and Southeast have collaborative agreements where participating hospitals adopt common checklists and share evaluator training modules. This reduces duplication of effort and aligns your documentation with broader regional standards, which also helps during joint surveys.
Where to Find the Aorn Operating Room Skills Competency Checklist
The checklist itself is not a single universal document you download from AORN and implement wholesale. AORN provides guidelines and recommended domains for competency, but each hospital customizes the actual checklist to fit its procedures, equipment, and policy requirements. AORN members can access sample frameworks and competency resources through the AORN online library and membership portal at aorn.org. Many health system simulation labs and nursing leadership conferences also distribute adapted templates that you can modify for your facility. Start with the AORN guidelines on perioperative nursing practice standards, then build your operational document from there rather than searching for a ready-made PDF that claims to cover everything. Those generic versions tend to be too broad to be useful and often miss facility-specific requirements that matter during actual surveys.


