A Practical Look at Using Group B Stroke Assessments
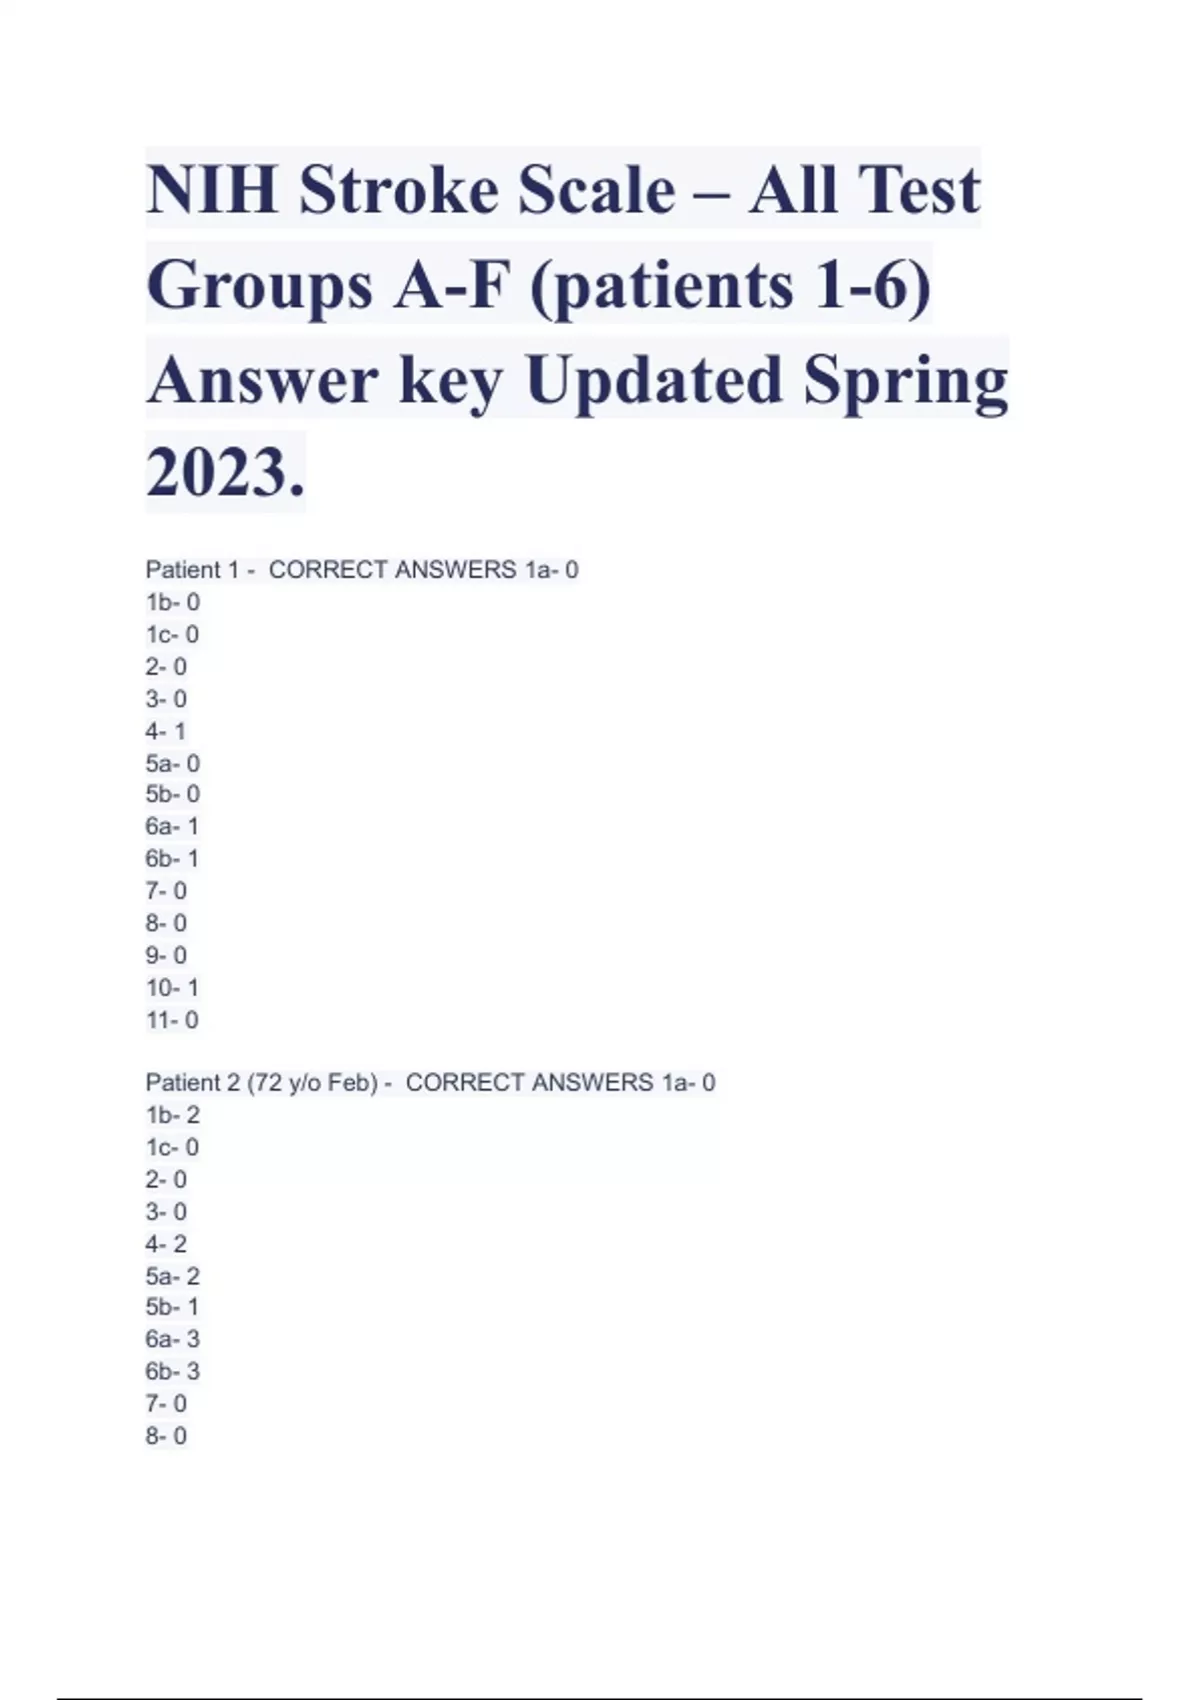
I've spent years working with NIH Stroke Scale protocols across different clinical environments, and the one thing nobody tells you about Group B assessments is how much they vary depending on who's administering them. I used Apex Innovations Nihss Group B documentation for about two years in a medium-sized hospital network before moving to a different system. Here's what actually happens when you're working with it day to day. The NIHSS evaluates stroke severity across eleven categories: consciousness, gaze, visual fields, facial palsy, arm motor function, leg motor function, limb ataxia, sensation, language, speech, and dysarthria. Group B within the Apex Innovations framework refers to a specific tier of patient assessment documentation meant for moderate-severity stroke presentations. Patients in this category typically score between 5 and 15 on the standard scale. The system was designed to standardize scoring across departments that didn't previously have a unified approach. Before Group B existed in practice, I saw nurses, residents, and attendings all score the same patient slightly differently. The variation mattered because treatment decisions sometimes hinged on a single point difference.
How the Assessment Process Works
The Group B workflow starts with eligibility verification. You confirm the patient meets stroke symptoms criteria, check their last known well time, and verify there are no contraindications to the full assessment. Then you proceed through the eleven items in order, recording each score immediately rather than rounding at the end. That last part sounds minor but it's where most errors creep in. I remember one specific case where a nurse rounded every score down by one point in her head because she was confident the patient had mild deficits. The total came out as a 6 instead of the actual 9. That one-point difference is enough to change whether a patient gets considered for certain interventions. The Apex system flags these inconsistencies through its audit trail, which was useful but not always timely.
Where People Go Wrong
The biggest issue I encountered was the language item, specifically item 2a. Evaluators tend to rush through the naming and repetition components because they assume the patient will pass. But if someone has subtle aphasia from a left hemisphere event, they might produce correct words with slight paraphasic errors that count as impaired. I've watched experienced clinicians miss this twice in the same week. A second common mistake involves the proprioception component of the sensory item. If you don't actually close the patient's eyes and test each finger individually while they can't see their hand, you're not properly assessing sensory function. Tapping the hand or just asking if they feel touch doesn't count. The Group B protocol emphasizes this distinction more than the basic NIHSS does, but I found that people still skim over it.
Get the Full Details

Scoring and Documentation Nuances
The total score isn't just a sum. The distribution matters for tracking purposes, and Apex Innovations tracks which items contributed most to the final score. A patient scoring 8 entirely from motor deficits reads differently in the system than a patient scoring 8 spread across sensation, language, and coordination. Your interpretation of severity should reflect that difference. There's also the repeated assessment question. Group B documentation requires follow-up NIHSS at specific intervals depending on your protocol. Some institutions want it every four hours. Others want it after any neurological change. The system supports both but expects you to justify whichever interval you choose in the notes.
Edge Cases That Annoy Everyone
Intubated patients create a real headache for the language and speech items. You can't assess language normally, so you mark it as not assessable. Same thing with severe facial trauma or pre-existing conditions like Bell's palsy. The Apex system handles these with special notations, but I found that not all downstream systems read those notations correctly. I once had a transferred patient whose Group B documentation showed "intubated - language not assessable" and the receiving hospital's system interpreted it as a zero score rather than a gap. The workaround I used was to add a plain-language note alongside every not-assessable item. Something as simple as "patient intubated, language and speech cannot be assessed at this time" prevented misinterpretation at three different transfer sites. The digital notation field wasn't enough on its own.
Limitations Worth Acknowledging
Group B isn't a substitute for clinical judgment. The scale has known limitations when applied to certain populations. Elderly patients with baseline cognitive impairment often score artificially high on the orientation and language items. Stroke patients with pre-existing aphasia or motor deficits from prior conditions can't be accurately reassessed against their own baseline. In those cases, you document the baseline condition separately and note that the NIHSS score reflects acute change on top of chronic deficit. There's also the question of inter-rater reliability. Even with standardized training, different clinicians will score the same patient differently about 15 to 20 percent of the time. Group B documentation helps reduce that gap through its detailed item guidance, but it doesn't eliminate it entirely. The best practice I found was having two clinicians independently score high-stakes patients and reconcile differences together rather than accepting the first person's score at face value.

Getting Started
If you're looking to implement this in your workflow, start by making sure your team completes the official training module. The self-study materials are free through the Apex Innovations portal, and the certification takes roughly two hours for someone familiar with basic NIHSS. Newer clinicians should budget four to six hours to work through the practice cases carefully. The official download and certification portal is at apexinnovations.com/nihss. They also offer annual refresher modules that I'd recommend rather than letting your team go more than a year without recertification. Scores drift over time without practice, and Group B documentation quality reflects that drift. One more practical note: keep a printed scoring sheet at the bedside even if you're entering everything digitally. Paper is faster for quick reference during an active assessment, and when the Wi-Fi drops or the system lags, you won't be stuck staring at a blank screen trying to remember whether arm drift scores a 1 or a 2. It's a small thing, but after missing a score on a live system entry, I never went back.



