Scoring Newborns at One and Five Minutes
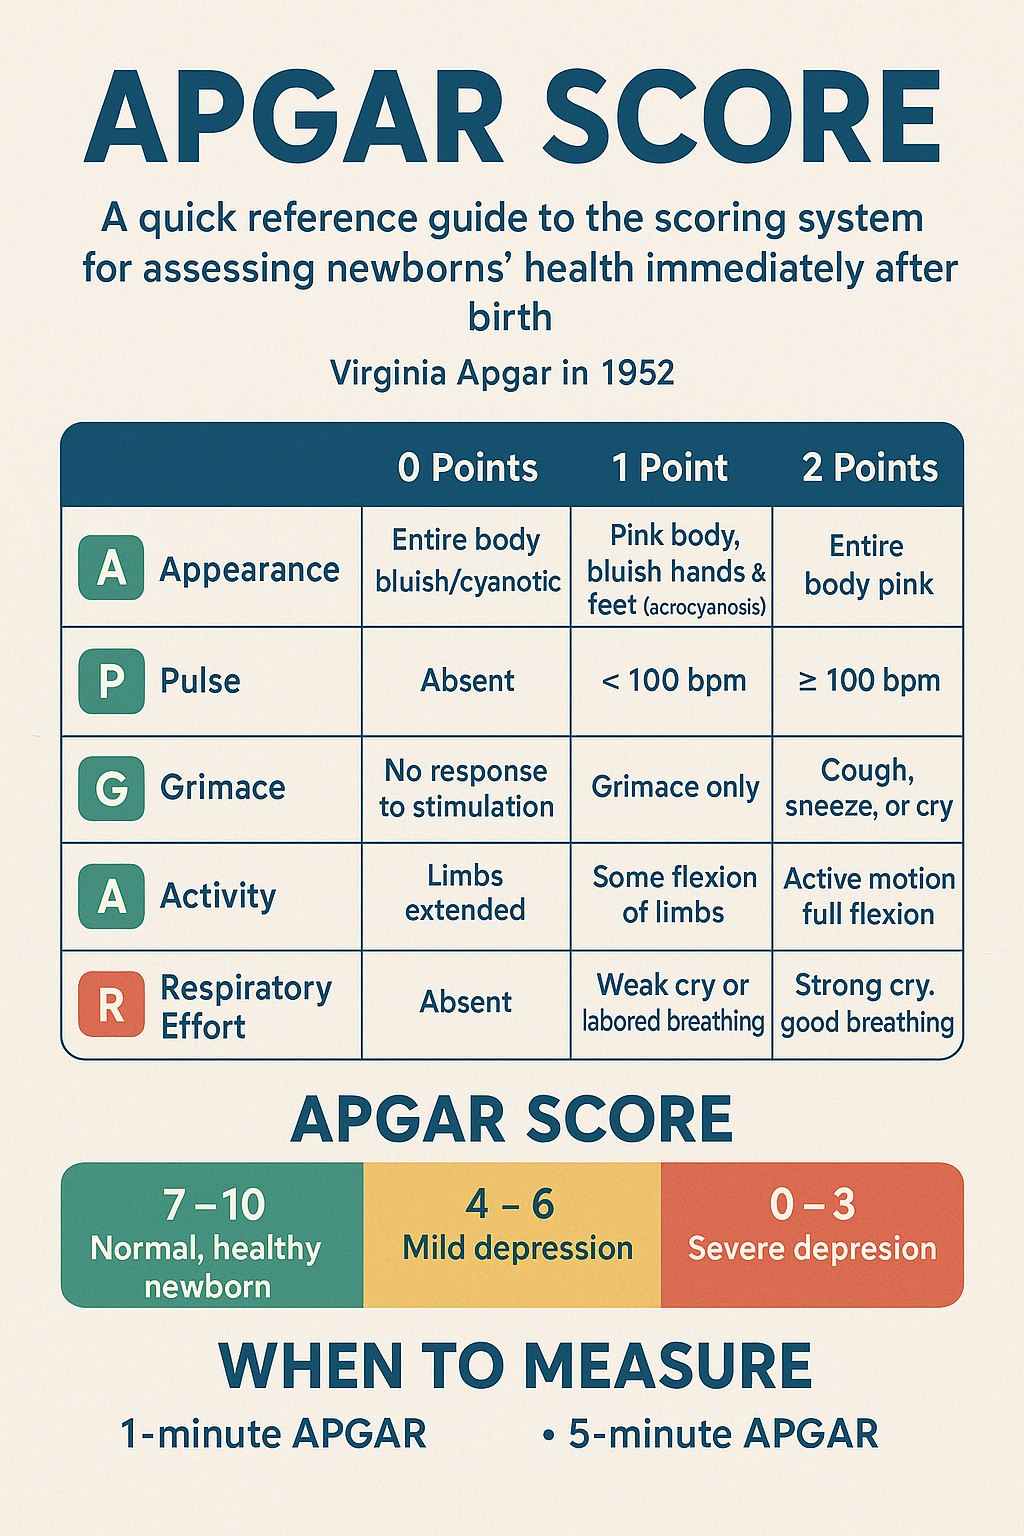
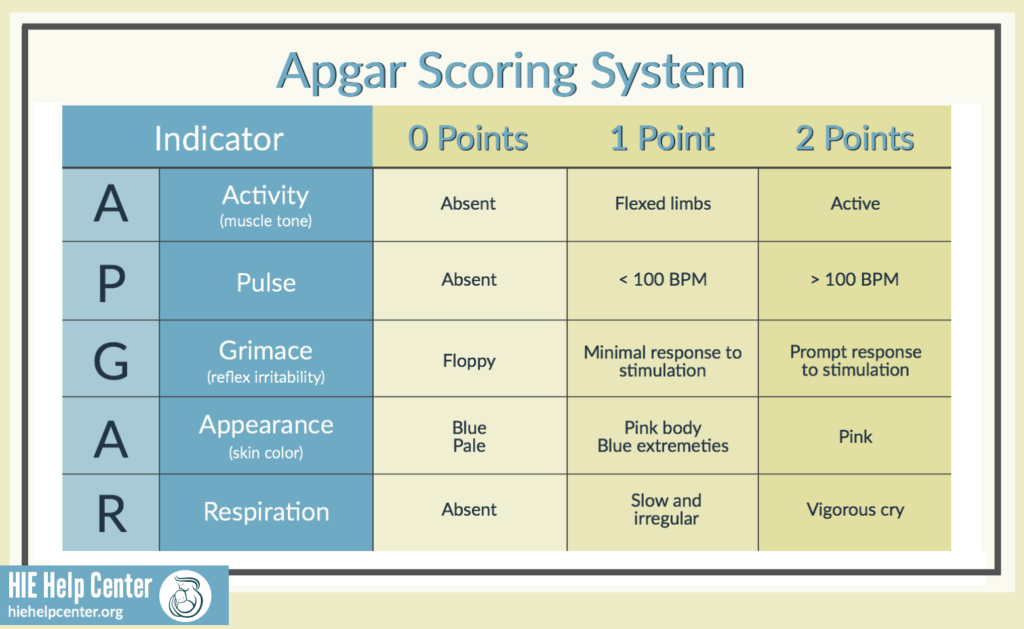
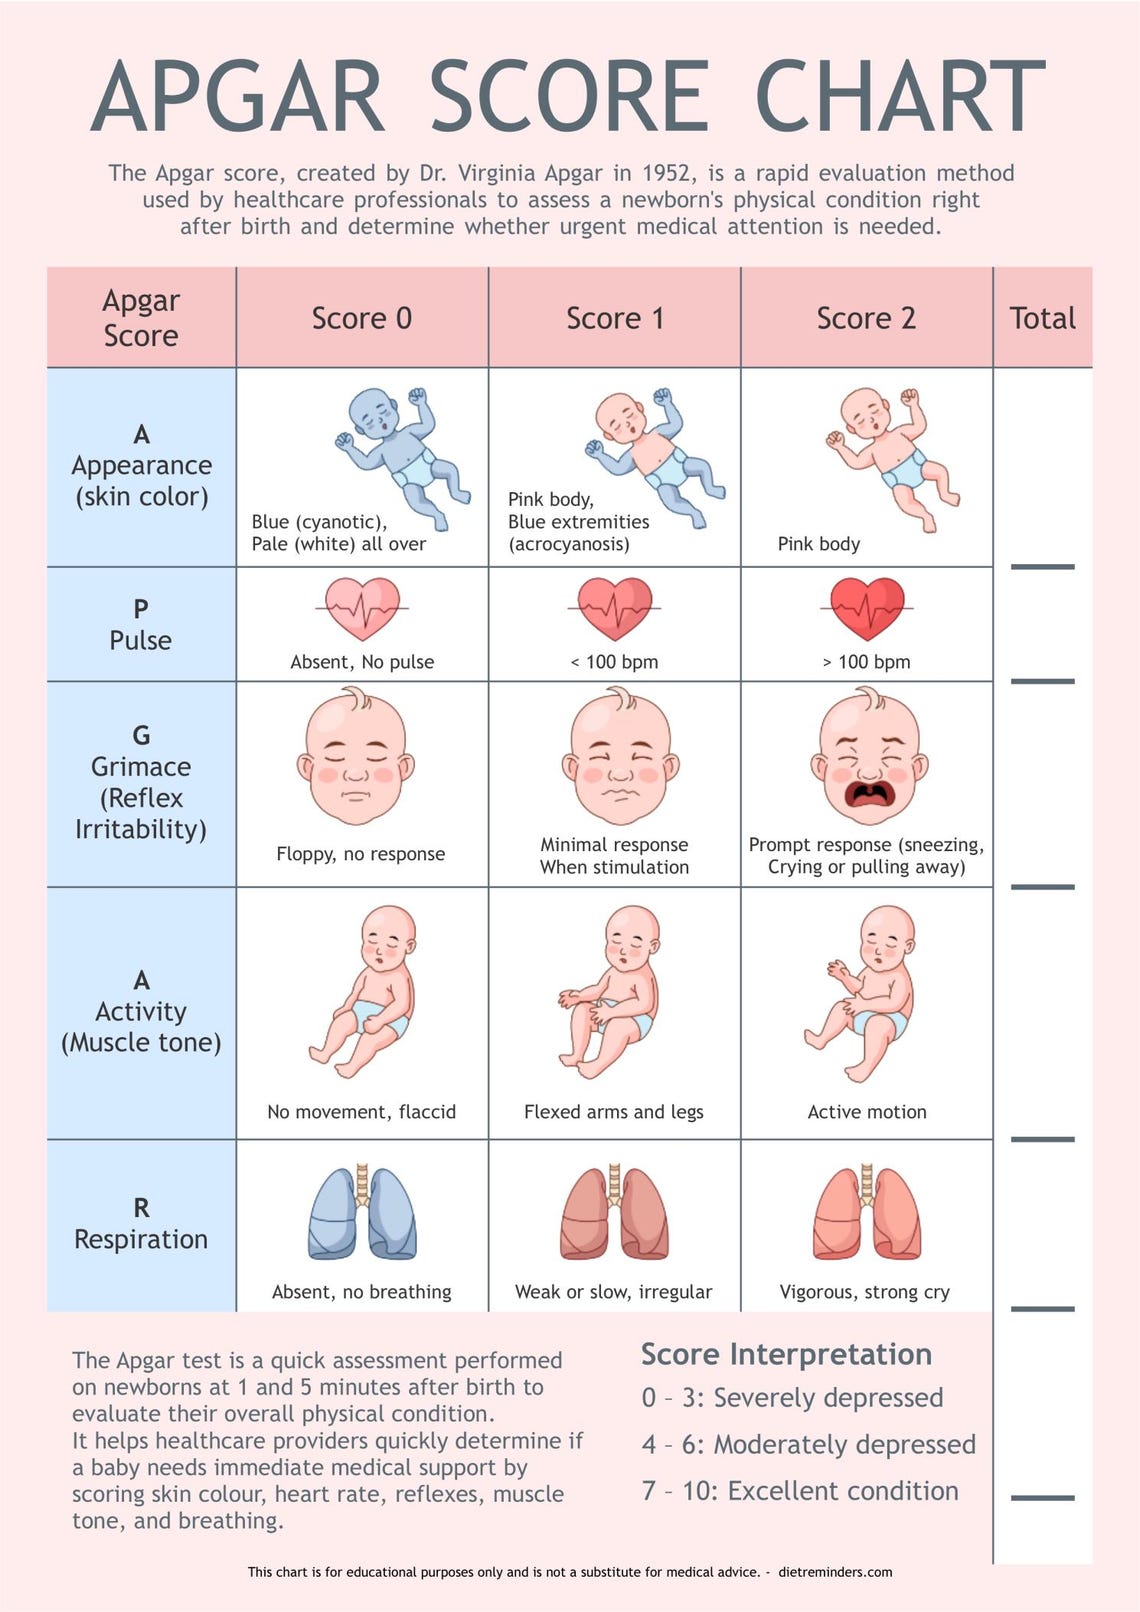
The Apgar Assessment Tool is a quick method for evaluating a newborn's condition right after birth. It scores five categories on a scale of zero to two each, giving a total out of ten. Heart rate, respiratory effort, muscle tone, reflex irritability, and color. Done at one minute and again at five minutes. That's basically it. The tool was created in 1952 by Virginia Apgar and has been refined slightly since then, but the core concept hasn't changed. I need to be blunt about what this tool does and doesn't do. It is not a diagnostic instrument. It does not predict long-term outcomes reliably. It tells you whether a baby needs immediate resuscitation or supportive care right now. Nothing more, nothing less. A score of three at one minute doesn't mean the baby has brain damage. A score of eight doesn't guarantee everything is perfect. It means the baby is breathing well, the heart is beating strongly, and there's no urgent problem requiring intervention.
Apgar Assessment Tool
Here's how I actually use it in practice, because the textbook version and the real version are slightly different. The five categories are straightforward, but the devil is in the details. Heart rate — palpate the base of the umbilical cord or listen with a Doppler. Less than 100 beats per minute gets a one. Above 100 gets a two. Below 60 is a zero. I learned early that if the cord pulse isn't visible and you can't get a quick Doppler reading, you don't sit there for thirty seconds counting. Note what you can confirm and move on. A vague "maybe around 100" is worse than documenting an incomplete assessment and going back. Respiratory effort — crying and breathing well is a two. Slow, irregular, or absent respiration is a zero or one depending on how weak it is. I've seen people miss this one by focusing only on whether the baby is crying. A baby can be making effort but just not vocalizing loudly, especially preterm infants. The effort matters more than the noise. Check for chest movement, nasal flaring, grunting.
Muscle tone — active motion with flexed extremities is a two. Some flexion is a one. Limp is a zero. This is the category where I see the most variation between scorers. Preterm babies will almost always score a one here because their neuromuscular system isn't mature enough for robust flexion. Don't punish a 28-weeker for being a 28-weeker. That's what the gestational age context is for. Reflex irritability — sneeze, cough, or cry vigorously in response to stimulation. I usually flick the sole of the foot or suction the nose. A vigorous response is a two. Some grimace or weak cry is a one. No response is a zero. The stimulation needs to be appropriate. Too gentle and even a healthy baby might not respond. Too harsh and you're just provoking a startle reflex, not assessing irritable response. Color — completely pink is a two. Body pink, extremities blue (acrocyanosis) is a one. Completely blue or pale is a zero. This is the most commonly misinterpreted category. Acrocyanosis is normal in the first few minutes. Nine out of ten newborns will be acyanotic at one minute and still be perfectly fine. Don't drop a full point for blue hands and feet at one minute if everything else looks normal. That's why the five-minute score matters more clinically.
Get the Full Details

I remember one specific case that taught me something about this tool. A baby was delivered via emergency C-section for fetal distress. The Apgar at one minute was a four — heart rate 110, slow respirations, some flexion, a grimace to stimulation, and completely blue. Standard interpretation would say significant depression. But this baby was 34 weeks, the cord was double-looped around the neck, and the mother had received a lot of magnesium sulfate during labor. The five-minute score jumped to seven, and by 15 minutes the baby was fully pink and feeding. What I learned from that was that the Apgar Assessment Tool doesn't account for maternal medication effects or gestational age adjustments. I now flag any low early score in preterm or medicated mothers immediately so the team knows not to assume permanent compromise. There's a common pitfall I want to address head-on. People treat the one-minute score as the definitive number. It isn't. The five-minute score is more meaningful. The American Academy of Pediatrics and the American College of Obstetricians and Gynecologists have both published statements noting that Apgar scores at five minutes and beyond are more predictive of outcomes than the one-minute score. A score below five at five minutes warrants continued assessment and possibly repeated scoring at 10, 15, and 20 minutes. But even then, it's a snapshot, not a prognosis. Another nuance that doesn't get enough attention: the Apgar score should be completed by the time the baby is ten minutes old. If you're still scoring at 15 minutes because you were distracted by something else, you've already missed the window where this tool is actually useful. It's designed to be fast. Two minutes maximum. If it's taking longer, you're either overthinking it or someone else should be scoring while you focus on the baby.
The limitations are real and worth stating plainly. The tool is subjective. Two trained observers can score the same baby differently, especially on muscle tone and reflex irritability. It doesn't account for the clinical context — why the baby was delivered, what the fetal monitoring showed, what medications were given. It's a descriptive tool, not an analytical one. For predicting neurodevelopmental outcomes, research shows that scores below three at five or 10 minutes have some association with cerebral palsy and cognitive impairment, but the positive predictive value is low. Most babies with low Apgar scores do not have adverse neurological outcomes. Conversely, many babies with poor outcomes had normal Apgar scores. If you need a formal reference or want to download a scoring sheet for your unit, the original methodology is in the public domain. The American Academy of Pediatrics provides reference materials on their website, and major obstetric textbooks have standardized worksheets. You don't need a proprietary tool — the scoring system itself is free to use anywhere. Just make sure your documentation template captures the individual category scores, not just the total, because a total of five tells you nothing about whether the baby has a heart rate of 60 and cyanosis or a heart rate of 120 with poor tone and no respiratory effort. The bottom line is simple. The Apgar Assessment Tool is a rapid triage method, not a comprehensive newborn evaluation. Use it correctly at one and five minutes, document the breakdown, interpret it in clinical context, and don't let it become a number that drives anxiety for parents without explanation. A low score is an indication to assess and support, not a diagnosis of doom.