How to Actually Find the Apical Pulse When You're Being Tested
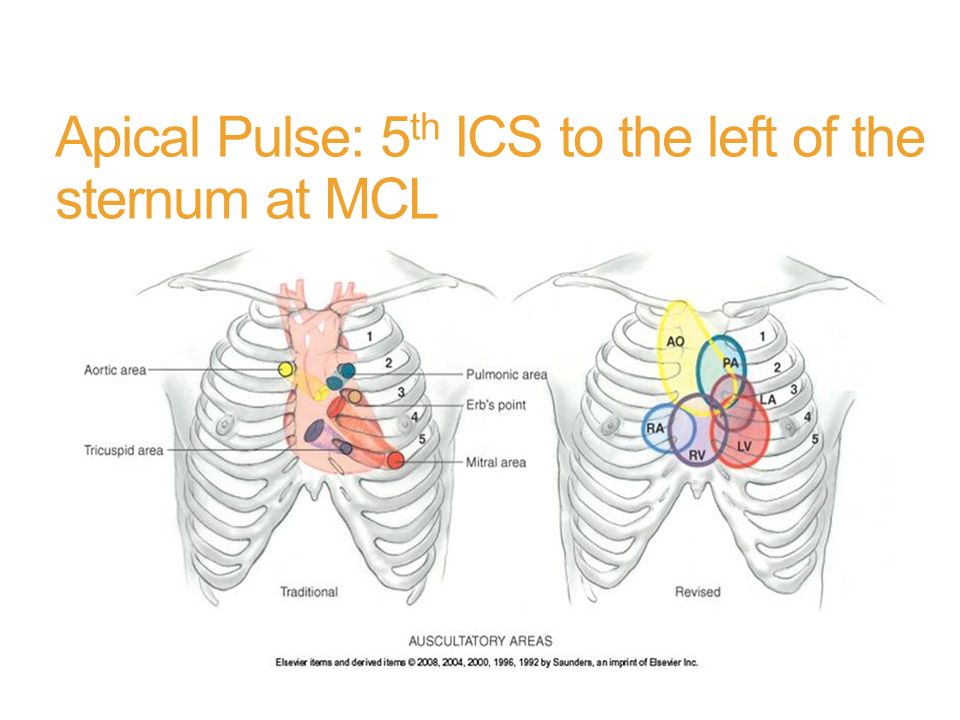
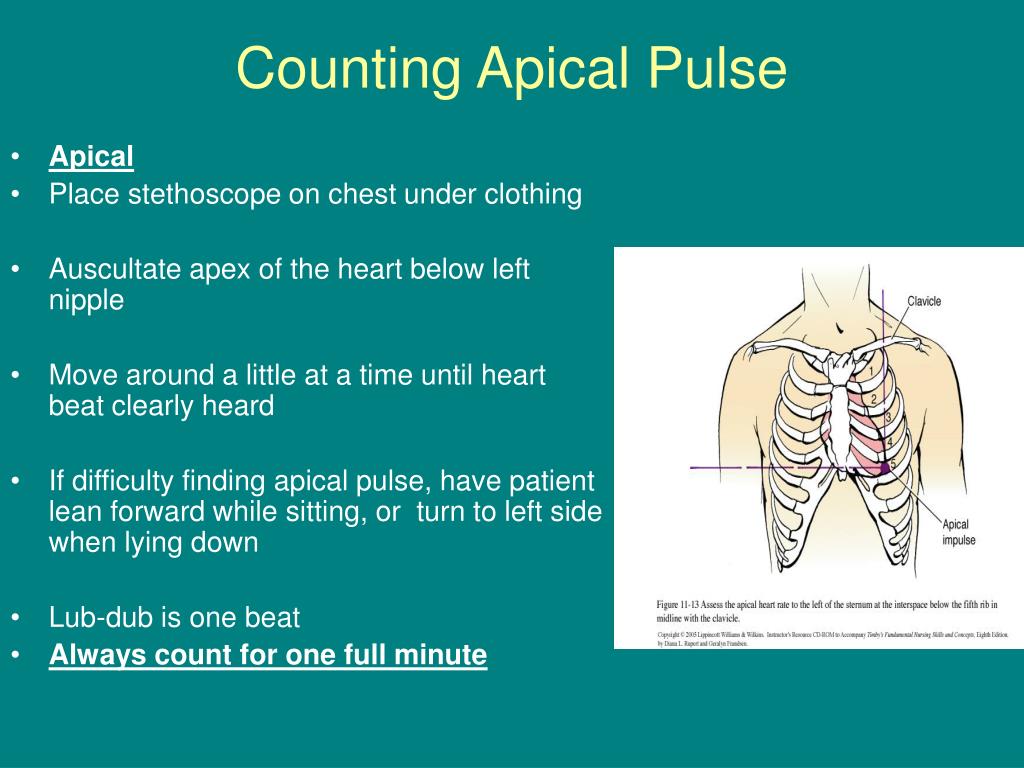
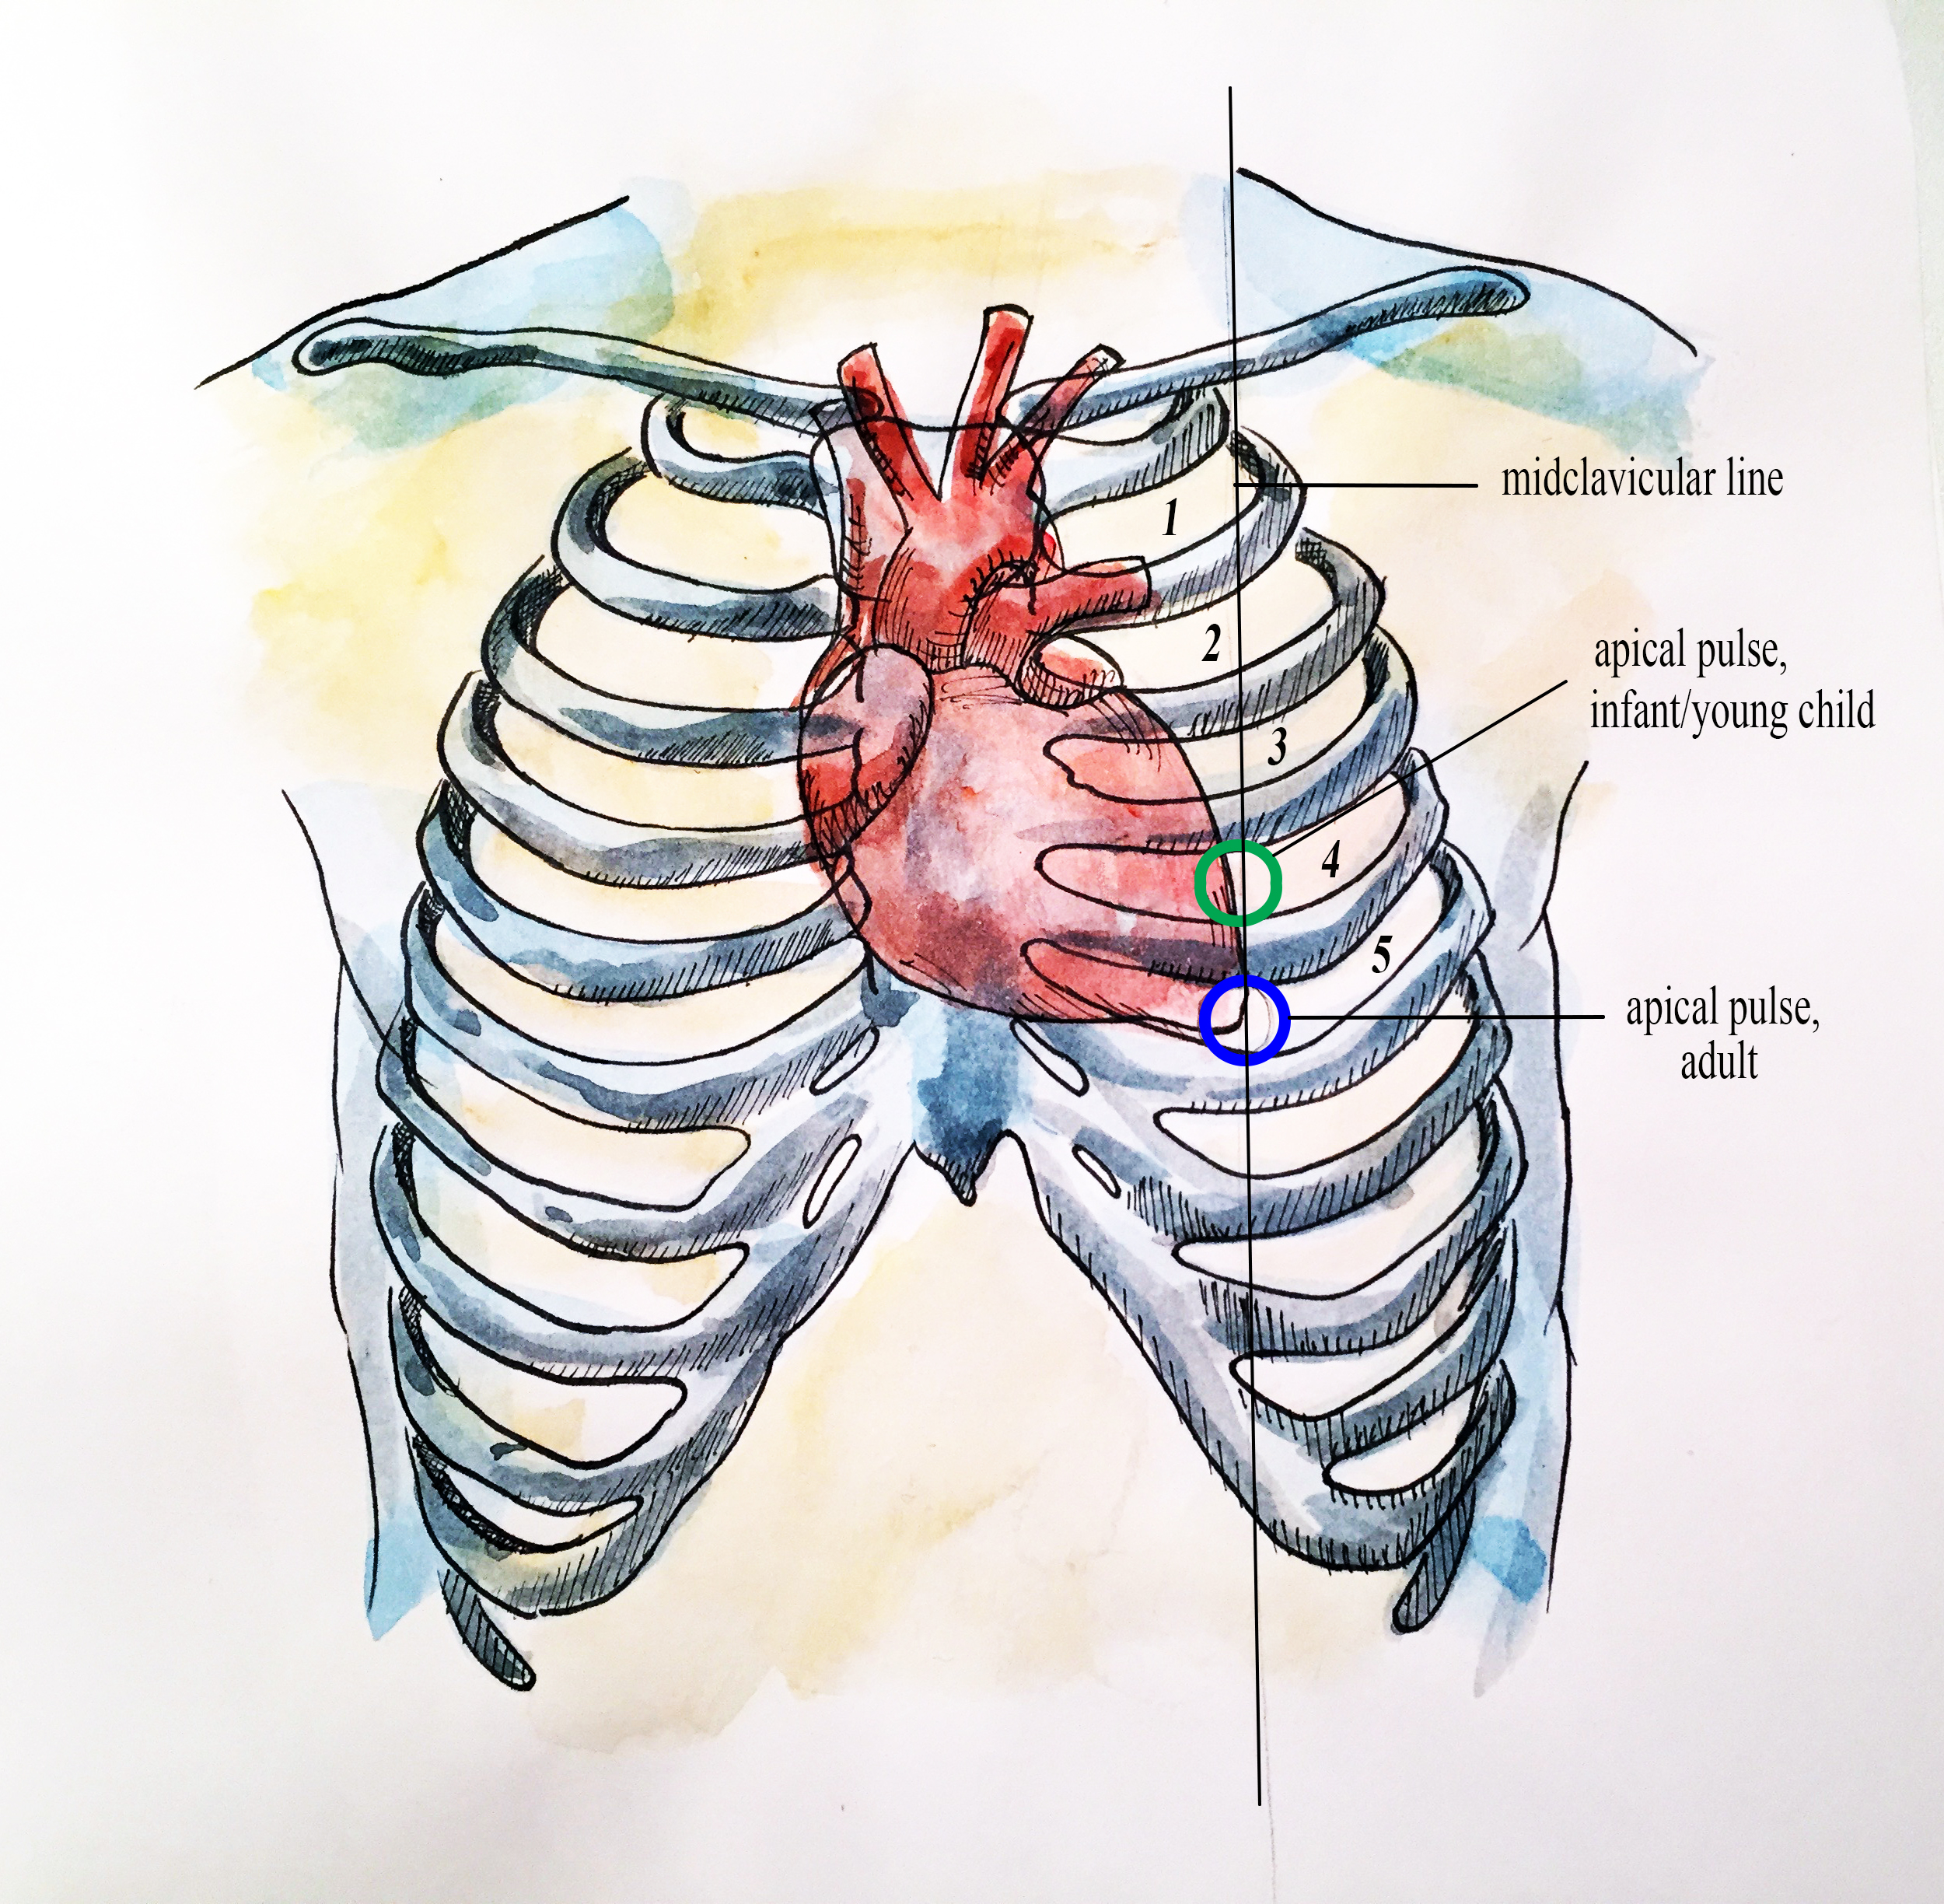
The apical pulse is found at the fifth intercostal space along the left midclavicular line. This is where the heart's apex touches the chest wall most directly, producing the point of maximal impulse. Most textbooks show you a diagram of a perfect body and expect you to memorize it. Real patients are not diagrams. I spent my first clinical rotation assuming every patient would present the landmark clearly. They don't. I was trying to locate the pulse on a 280-pound man with significant abdominal adiposity during an OSCE, and I spent four minutes pressing around his lower sternum while my examiner watched with increasing disbelief. I ended up having him lean forward and slightly roll to his left, which brought the apex closer to the chest wall. That position change alone made the difference between feeling nothing and catching a clear, regular beat.
Apical Pulse Location Pictures
When you search for reference images, most diagrams you'll find show the landmark on a standard anterior chest illustration. They almost always mark the 5th intercostal space at the midclavicular line with a small dot or arrow. The midclavicular line is the vertical line dropping straight down from the midpoint of the clavicle. The intercostal space is the gap between two ribs, not on the rib itself. These pictures are useful for initial orientation but they don't capture the variation you'll actually encounter. Search terms that yield better results: "apical impulse anatomical diagram," "PMI location anterior chest wall," "point of maximal impulse palpation." A few medical education sites like Kenhub and the American Heart Association's nursing resources have cleaner illustrations than random image searches.
The Method Nobody Emphasizes Enough
Start by having the patient lie supine at a 30 to 45-degree angle. Expose the chest adequately. Place the bell of your stethoscope lightly at the expected landmark—the 5th intercostal space, left midclavicular line. If you can't find it on the first attempt, move one intercostal space up or down and one centimeter medial or lateral. The apex can shift due to body habitus, pregnancy, ascites, or cardiomegaly. Here's the counter-intuitive part that most students miss: the pulse is often easier to see before it's easy to hear or palpate. In thin patients, you can literally watch a subtle rhythmic bulge at the landmark. That visual confirmation tells you exactly where to place your stethoscope. In overweight patients, the bulge disappears, so you rely more on careful palpation with the pads of your fingers rather than your palm. Your palm has too much sensitivity noise. Another thing that trips people up: the midclavicular line shifts. In a large female patient or someone with significant breast tissue, the clavicular midpoint is still the same anatomical landmark, but the breast tissue obscures the area below it. I learned to trace the midclavicular line from the clavicle down and then identify the intercostal space by counting ribs, not by guessing based on surface appearance. Counting from the second rib down is more reliable than trying to count upward from the xiphoid process, because the xiphoid is variable and often hard to identify precisely.
Get the Full Details
Common Pitfalls
The most frequent error is confusing the apical pulse with the carotid pulse. If you're palpating too high or too medial, you'll feel the carotid instead. The carotid is in the neck, obviously, but in obese patients the neck contour is less defined and it's surprisingly easy to mistake a transmitted carotid vibration for the apical impulse. The carotid pulse is also much stronger and more superficial. If your pulse feels like it's right under the skin rather than deeper, you're likely on the wrong structure. A second pitfall is using the apex of the stethoscope instead of the bell for initial location. The diaphragm is better for hearing heart sounds once you've confirmed the location, but the bell is more sensitive to the lower-frequency components of the apical impulse during palpation. I switch to the diaphragm once I've confirmed I'm at the right spot because that's what gives you the clearest S1 and S2 for rate and rhythm assessment. The apical pulse cannot be reliably felt in some patients. Severe COPD with hyperinflated lungs pushes the diaphragm down and the heart into a more vertical position, moving the apex away from the chest wall. In these cases, percussion is useful: dullness at the left 5th intercostal space roughly at the midclavicular line confirms the heart border. Echocardiography is the definitive alternative when physical examination fails, which is more often than you'd think in critically ill or morbidly obese patients.
What the Pictures Don't Show You
Reference images make the anatomy look static. In reality, the apex beats. It moves. During inspiration, the diaphragm descends and the heart shifts slightly, moving the apex laterally and inferiorly. During expiration, it returns toward its resting position. If you're teaching this or learning it, don't just look at a still picture. Watch a video of palpation if you can find one. YouTube has several clinical skills channels that show the actual hand placement and the subtle displacement you're feeling for. The normal apical pulse is confined to an area no larger than a coin, roughly 1 to 2 centimeters in diameter. If the impulse is diffuse or displaced laterally beyond the midclavicular line, that suggests cardiomegaly or a lateral shift of the heart due to conditions like a left pneumothorax. The location picture you studied assumes a normal heart position. Abnormal findings require you to adapt. Recording the exact location matters in clinical documentation. "Apical pulse 88 bpm, regular, located at 5th ICS left MCL" is complete. "Heart rate normal" is not. When you're documenting for a supervisor or transferring care, precision prevents errors. I've seen patients sent for unnecessary imaging because a previous note said "apical impulse palpable" without specifying location, and the receiving team couldn't reconcile it with their own examination findings.