How to Actually Find the Apical Pulse Rate Location
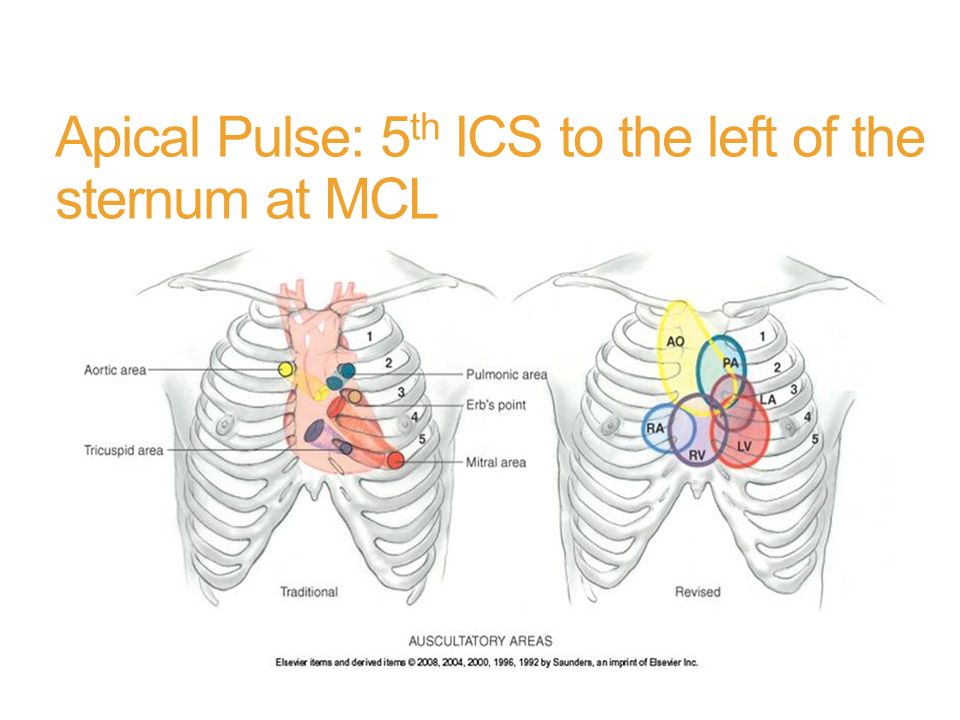
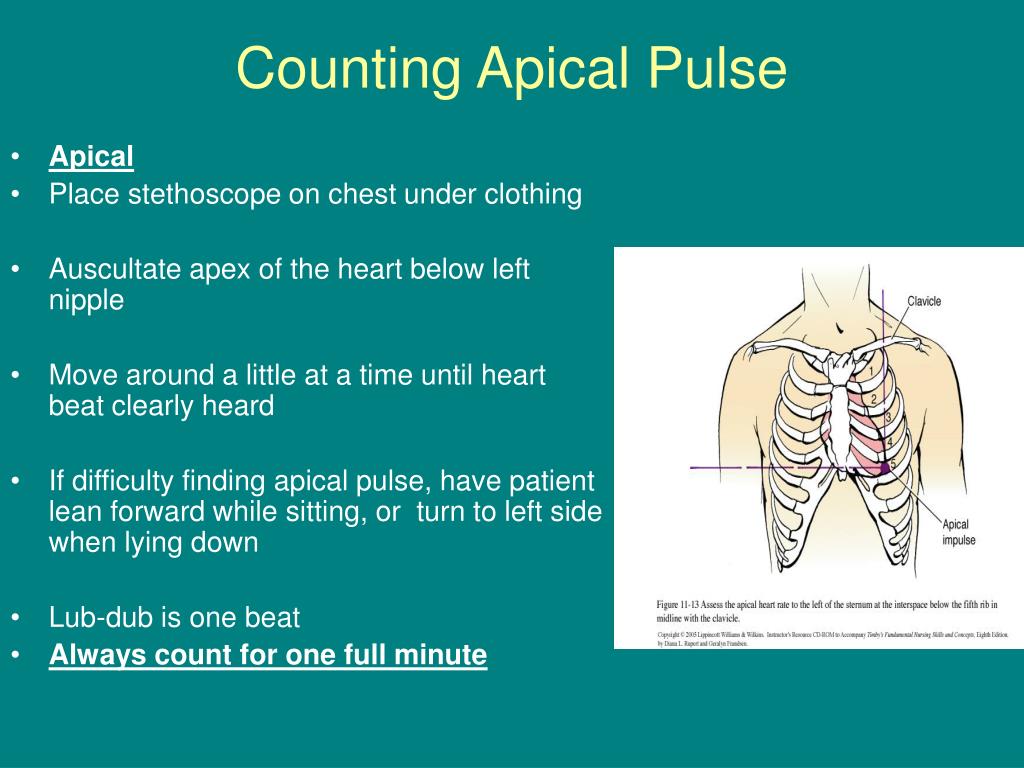
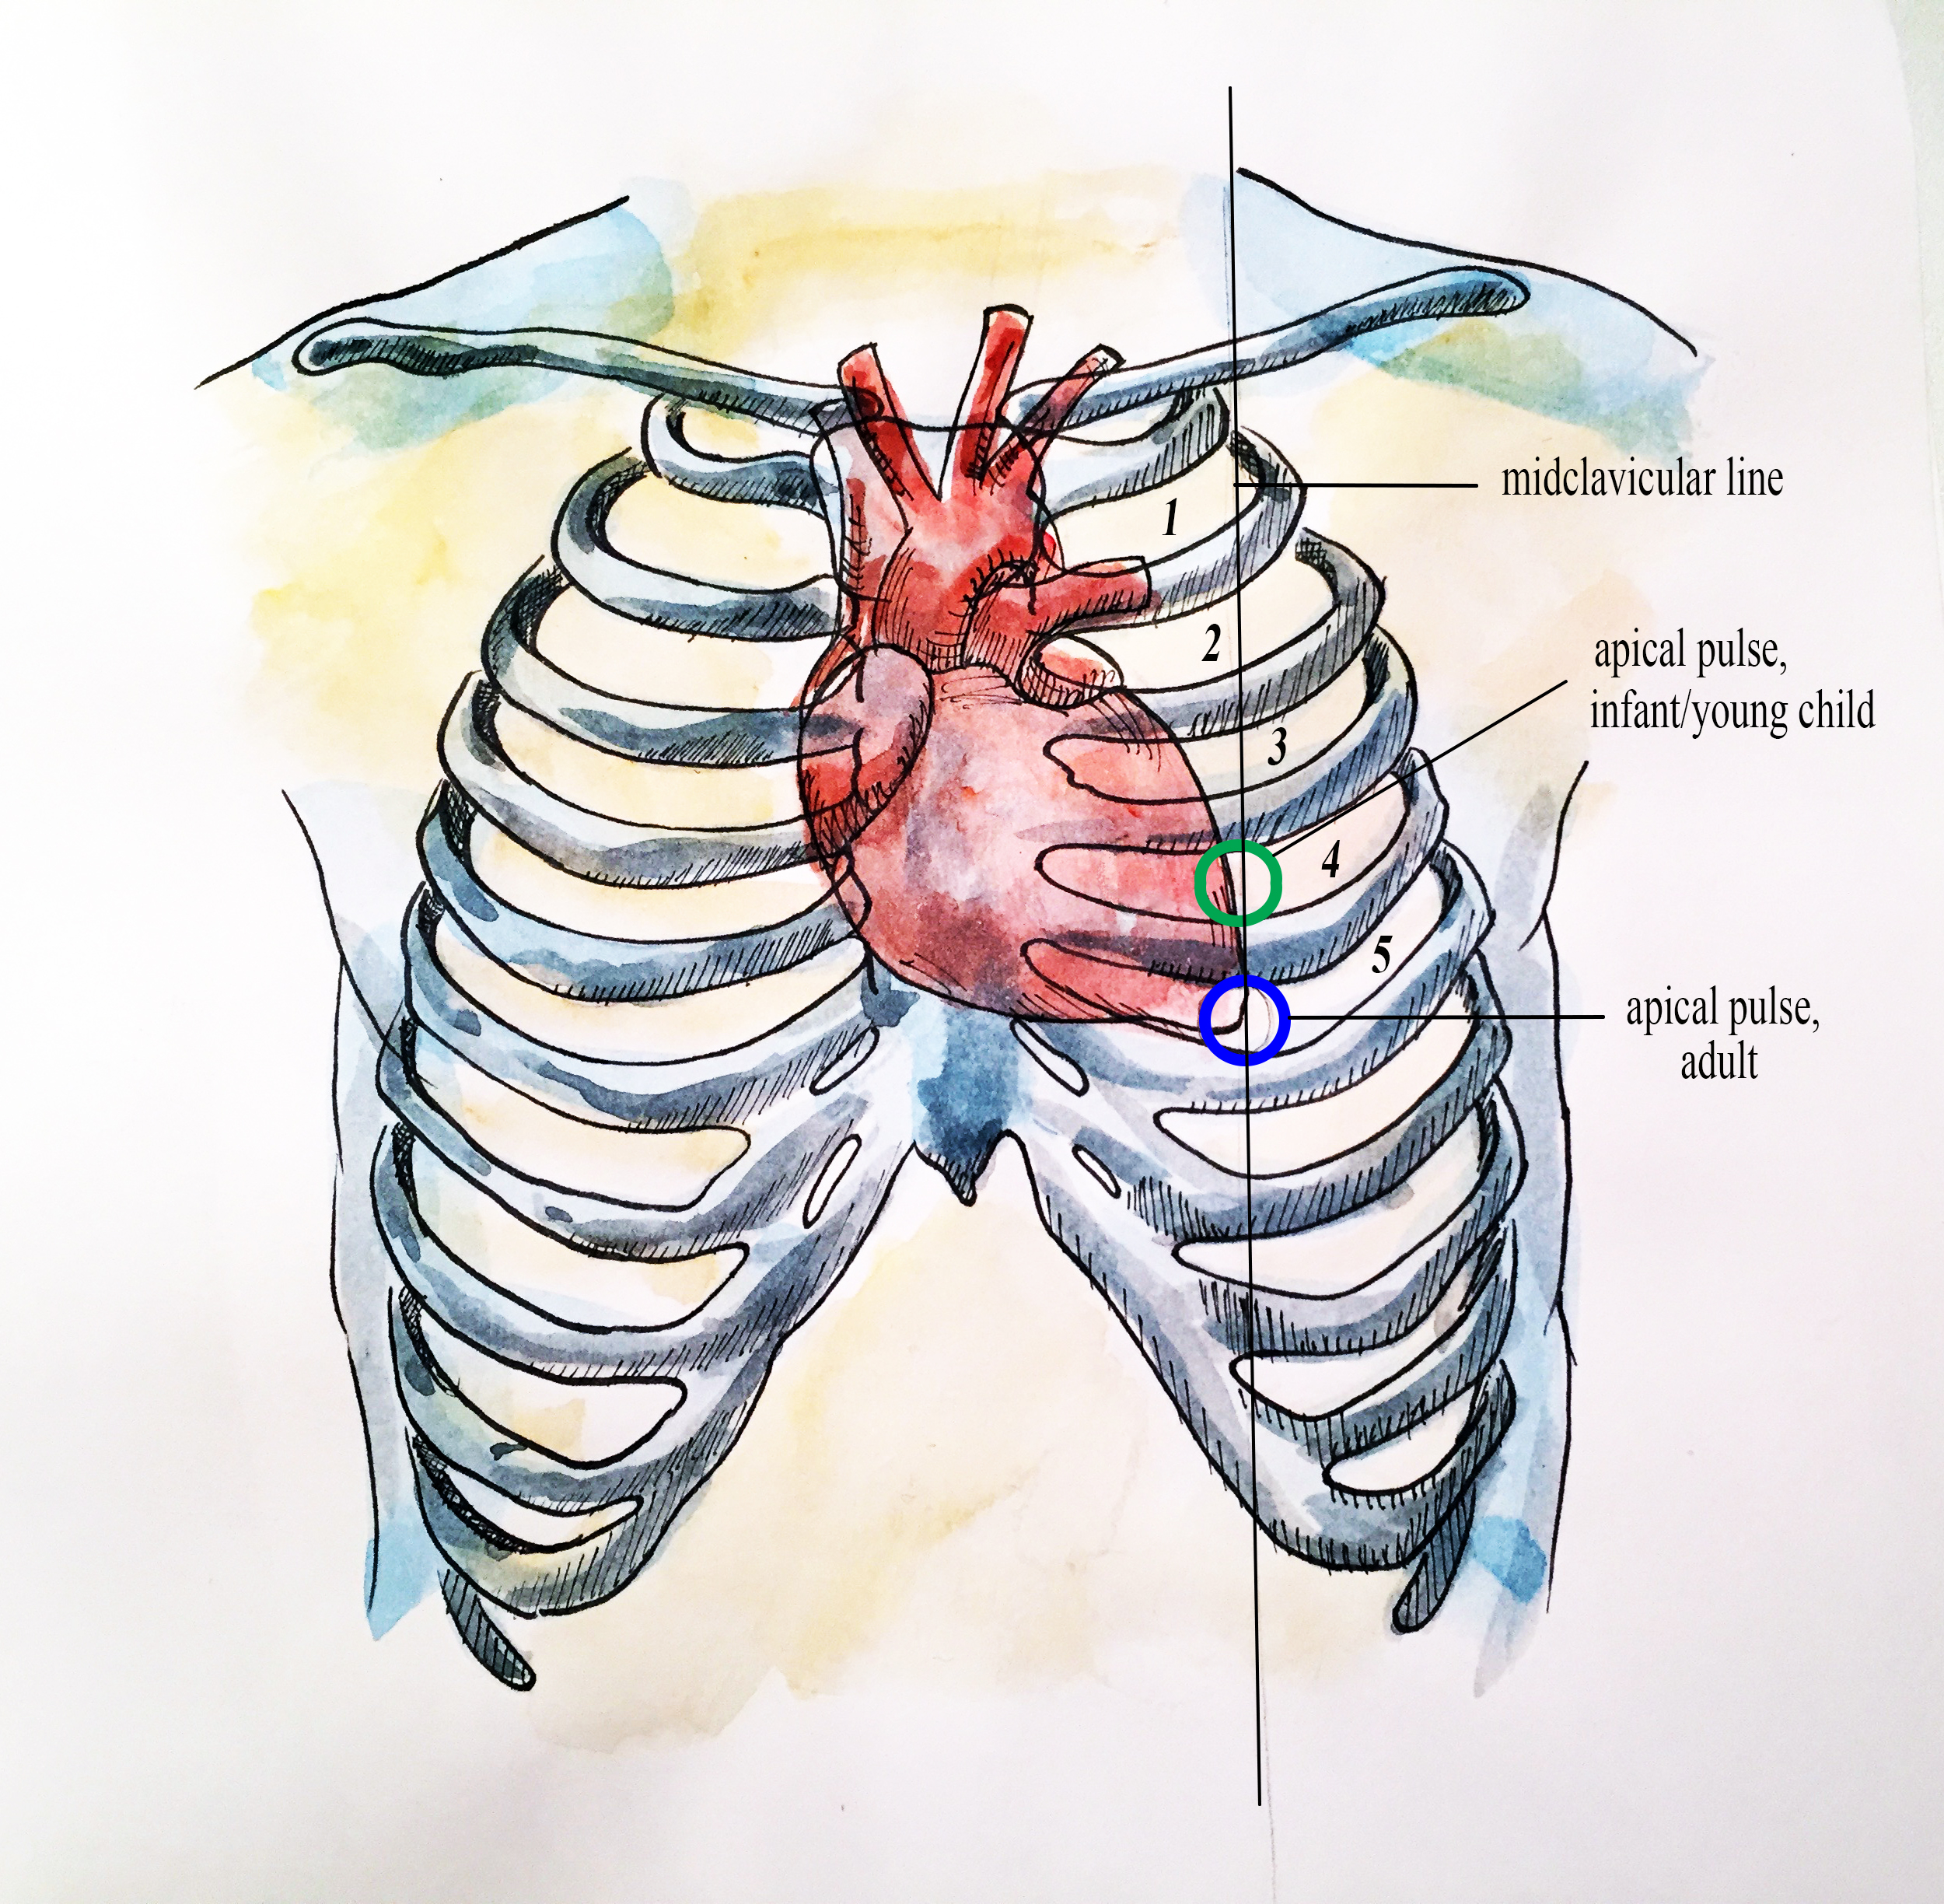
The apical pulse rate location is where you listen to the heart through the chest wall, usually at the fifth intercostal space near the midclavicular line on the left side. It is the standard way to measure heart rate when peripheral pulses are unreliable. I have been doing this for years and most people still get it wrong on the first try, which is why I am writing this instead of doing something else. You need a stethoscope, obviously, but not just any cheap one from a pharmacy. The diaphragm needs to be clean and the tubing should not be cracked. Old rubber creates noise that will mess with your reading. Find the costal notch first, then move down to the space between the fifth and sixth ribs. That is where the apex sits in most adults. You press lightly and listen for two distinct sounds — S1 and S2. If you hear a murmur, note it. Do not ignore it because someone told you not to.
Why Apical Pulse Rate Location Matters More Than Radial
Radial pulse checks fail constantly when patients are hypotensive, in shock, or have peripheral vascular disease. When blood pressure drops below 80 systolic, the radial pulse becomes unreliable or disappears entirely. The apical approach still works in those cases because you are listening directly to the ventricular contraction. I once worked a Code Blue where the monitor showed atrial fibrillation but the radial pulse was too weak to count. The apical rate came back at 112 irregular, confirming what the ECG later showed. Counting those beats took about 30 seconds of focused listening. A radial check would have wasted the entire code on a ghost pulse. There is a common mistake here that beginners make repeatedly. They count for six seconds and multiply by ten. That gives you a quick number, but if the rhythm is irregular, which it often is in patients who actually need an apical check, you are going to be off. Count a full minute every time when the rhythm is irregular. The difference between 96 and 114 beats per minute changes management decisions. Six-second estimation is fine for stable sinus rhythm in healthy patients. It is not fine for anything that requires clinical precision. Another thing nobody warns you about is patient positioning. The standard position is supine with the head of the bed elevated to 30 to 45 degrees. If you roll the patient onto their left side, the apex moves laterally and you might miss it entirely. I lost a valid reading once because the patient had shifted during a long assessment and I was still counting where I thought the point should be. I moved the stethoscope two centimeters to the left and there it was — a strong, regular S1. Always confirm the point before you start counting. Palpate the precordium first if you are unsure. The PMI, or point of maximal impulse, will guide you to the right spot in most cases.
Body habitus changes everything. In obese patients, the landmarks are harder to find. The fifth intercostal space might be obscured by breast tissue or abdominal fat. In those situations, start at the nipple line as a rough guide, then slide up or down while palpating for the PMI. Some patients with severe COPD have a downward displaced apex, and others with cardiomegaly have it pushed laterally. A normal apical pulse rate location sits at the fifth intercostal space at the midclavicular line, but "normal" shifts with pathology. Don't trust the textbook position blindly. There is also the matter of auscultation technique itself. Place the diaphragm firmly enough to occlude the skin underneath, but not so hard that you distort the chest wall. You want direct contact. Lean in. Use both earpieces angled forward to match your ear canal orientation. One earpiece loose and you are listening through ambient noise instead of heart sounds. I have seen nurses stand three feet away from the patient and call it an apical assessment. That is not how it works. If you are dealing with a pediatric patient, the location is different. The apex in children sits higher, usually at the fourth intercostal space. The heart is positioned more horizontally in their chest cavity. Using the adult landmark on a child will give you a weak or absent sound and waste time. Age matters here, not just size.
Get the Full Details
The apical pulse rate location remains the most accurate bedside method for heart rate determination when you cannot rely on pulse oximetry or peripheral pulses. It requires practice and patience. You will miss beats early on. Your ears will fatigue. The environment will be noisy. These are all solvable problems. Find the correct space, confirm with palpation, count for a full minute in irregular rhythms, and adjust for body habitus and age. That is the process. Everything else is details.