
Understanding the Two Divisions of the Human Skeleton
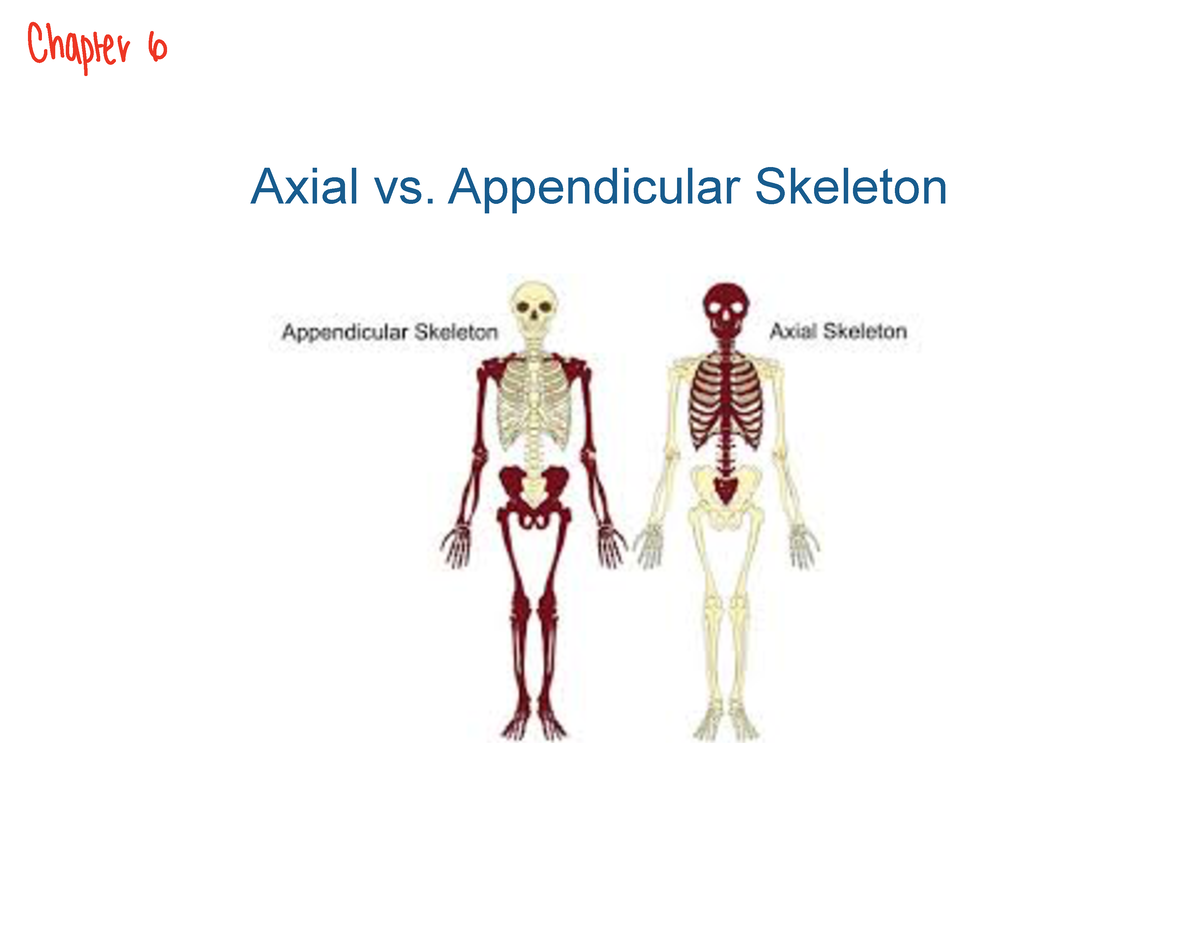
The human skeleton breaks down into two main regions, and most anatomy resources handle this at a surface level. I've found that students and even practitioners sometimes mix up the boundaries between these divisions when they're working with clinical imaging or trying to map structural relationships. Let me walk through how I approach this. The axial skeleton consists of 80 bones arranged along the central axis of the body. This includes the skull (22 bones plus the hyoid and 6 ossicles), the vertebral column (26 bones including fused sacrum and coccyx), the rib cage (24 ribs plus the sternum), and a few supporting structures. It runs vertically through the core. The appendicular skeleton contains the remaining 126 bones, making up 206 total in the adult human. This group covers the pectoral girdles (clavicles and scapulae), the upper limbs (humerus, radius, ulna, carpals, metacarpals, phalanges), the pelvic girdle (hip bones), and the lower limbs (femur, patella, tibia, fibula, tarsals, metatarsals, phalanges). The reason this distinction matters in practice comes down to function and developmental origin. Axial bones protect vital organs and provide structural scaffolding. Appendicular bones handle locomotion and manipulation. They also develop through different embryological pathways — axial structures largely from somites and neural crest cells, while appendicular elements form from lateral plate mesoderm. That developmental split shows up later in certain pathological conditions.
Where Things Get Messy in Practice
I ran into a real problem once while reviewing CT scans of a trauma patient. The radiologist had marked fractures involving the axial skeleton, but they were missing a subtle avulsion fracture at the base of the xiphoid process where it articulates with the body of the sternum. That's technically axial, but it sits right at the junction where clinicians start thinking about appendicular relevance for surgical access and stabilization. The patient had significant blunt force trauma to the epigastrium, and on the initial reading, only two rib fractures and a T12 compression fracture were noted. Three days later, a repeat scan with thinner cuts revealed the xiphoid fracture along with a sternocostal dislocation at the 7th rib interface. Missing that kind of boundary case can shift a treatment plan entirely. My workaround was straightforward: I started cross-referencing the anatomical landmarks against a consistent mental checklist. For any thoracic or abdominal trauma, I systematically note every rib-sternum articulation, the xiphoid-sternal junction, and the costovertebral joints where the axial and appendicular systems communicate biomechanically. It adds maybe thirty seconds per scan, but it catches things that matter.
Counter-Intuitive Points Beginners Miss
Here are a couple of things that aren't obvious from a textbook diagram. First, the boundary between axial and appendicular isn't as clean as people think. The clavicle is classified as appendicular because it's part of the pectoral girdle, but it articulates directly with the axial skeleton at the sternoclavicular joint. The hyoid bone is axial, yet it has no direct bony articulation with any other bone — it's suspended by ligaments and muscles from the skull. These edges matter when you're studying joint pathology or planning surgical approaches. Second, the pelvic girdle causes confusion across the board. The hip bones (ilium, ischium, pubis) are appendicular, but they articulate with the axial skeleton at the sacroiliac joints via the sacrum. When you look at weight-bearing mechanics, the force path goes from the spine through the sacroiliac junction into the hip. That means a stress fracture in the sacral ala — axial territory — can present with symptoms that feel exactly like a hip injury. I've seen this misdiagnosed more than once in clinical settings, usually because the referral pattern mimics femoral head pathology.
Get the Full Details
A Practical Framework for Learning This
Rote memorization of bone counts works for exams but breaks down quickly. Instead, I teach people to map the skeleton in layers. Start with the axial core: skull, spine, rib cage. Then add the girdles — clavicle and scapula anteriorly, hip bones posteriorly and laterally. Finally, add the limb bones radiating outward. This gives you a spatial model rather than a list. When studying pathologies, track which region each condition affects and note the transition zones. These are where complications happen. The costovertebral and costotransverse joints sit between rib (appendicular girdle-adjacent) and vertebra (axial). The acromioclavicular joint connects scapula to clavicle, both technically appendicular but functionally linked through the Sternoclavicular joint to the axial skeleton. Understanding these links changes how you interpret range-of-motion limitations or referred pain patterns. A note on limitations: Some anatomical classification systems treat the hyoid bone differently, and a few sources count the vertebral column as 33 individual segments rather than 26 bones due to the fusion states of the sacrum and coccyx. These discrepancies are real and can trip you up if you're comparing study materials across different curricula. I've found that being explicit about your counting convention at the start of any analysis prevents most of these issues. Just pick one system and stick with it throughout.
The take-away here isn't that the axial versus appendicular distinction is arbitrary — it's fundamentally useful. But the usefulness comes from understanding the boundaries and the exceptions at those boundaries, not from memorizing which side of the line a given bone falls on. The transitions are where things actually happen in the body.


