How to Write ABA Session Notes That Actually Survive an Audit
Most ABA session notes get written in the last twenty minutes of a session or immediately after. That timing is usually fine, but it means you're relying on memory for things that genuinely fade fast. I've watched clinicians lose track of whether a client responded to a visual prompt or needed a physical guide, then guess on the form and create a data integrity problem that shows up six months later during a case review.
The method itself is straightforward once you stop treating documentation like paperwork and start treating it as clinical data. You record the target behavior with its operational definition intact. You note the antecedent conditions. You record the consequence and what type of reinforcement was delivered. You track prompt level, mastery status, and any medical or behavioral changes during the session. That's it. The complexity comes from doing it accurately across multiple programs in a single session.
Here is what a complete session note entry actually looks like in practice:
Target Behavior: Mand for break using PECS card. Antecedent: Task demand presented (math worksheet, 5 problems). Response: Client placed card on therapist hand within 3 seconds. Prompt Level: Independent. Data: 4 out of 5 trials correct. Reinforcement: Break given immediately following correct mand. Session Duration: 45 minutes. Programs Targeted: Manding (break request), Academic (math compliance), Motor imitation. Behavioral Changes: Client elevated heart rate noted at beginning of session; resolved after first mand for break was honored. Plan: Continue current reinforcement schedule; add distractor condition next session.
That note tells someone else everything they need to know. It also tells an auditor you actually knew what happened. Vague entries like "worked on mands" or "client had a good session" are the single biggest source of billing discrepancies I see. They don't describe a behavior. They describe a feeling.
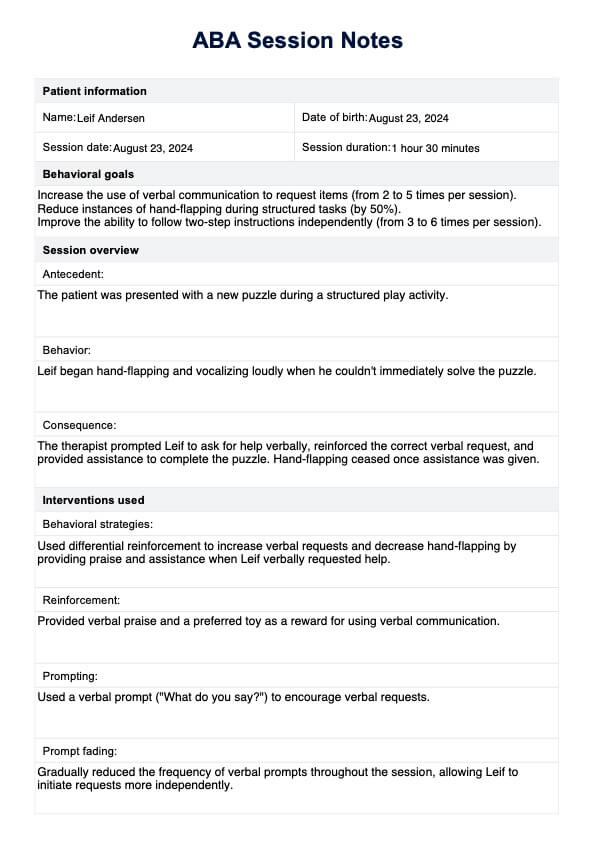
Applied Behavior Analysis Aba Session Notes Examples
You'll find templates online that look clean and organized. Most of them are missing the functional context that makes them defensible. A template that says "Behavior: Tantrum. Duration: 8 minutes. Frequency: 2 occurrences" is not sufficient for an insurance audit or a supervisor review. It doesn't say what the tantrum looked like operationally, what triggered it, what maintained it, or what replacement behavior was taught during that window.
A better example would read: "Behavior: Tantrum, operationally defined as screaming above conversational volume combined with body drop to floor. Antecedent: Therapist attempted to transition from preferred activity (iPad) to non-preferred (academics). Replacement behavior taught: mand for 'break' using gesture prompt. Client achieved independent mand on 3 of 5 opportunities. DRI implemented throughout session. Data supports continuation of current intervention plan."
The second example takes longer to write but saves you hours of clarification requests later.
I keep a mental checklist that takes about forty-five seconds to run through before I close a session. Was the top target behavior documented with its operational definition? Is the antecedent specific enough that another clinician could replicate the condition? Did I note prompt level and fading status? Is there a clear link between the data collected and the plan for next session? If the answer to any of those is no, I go back and fix it before leaving the room.
The hardest part isn't the format. It's the discipline of staying consistent across dozens of clients every week. I've seen people switch between frequency counts, duration recording, and latency measurement on the same program depending on how they felt about the session. That inconsistency makes it impossible to track real progress over time. Pick a measurement method for each target behavior and stick with it. Your future self will thank you.
Where People Go Wrong With Session Documentation
The most common error I encounter is conflating data collection with behavior description. A data sheet and a narrative note serve different purposes. The data sheet is for graphs and trend analysis. The narrative note is for context. When you try to make the narrative note do both jobs, it ends up doing neither well.
Another mistake is writing notes that reflect what should have happened rather than what actually happened. This usually comes from stress or time pressure. You intended to fade prompts on the tacting program but ended up using full physical guidance the entire time. Writing "prompt faded to gestural level" on the note creates a paper trail that doesn't match the raw data. Auditors cross-reference these routinely. The fix is simple: write what you actually did, note the deviation, and adjust the plan accordingly. That's clinical integrity, not failure.
A third issue is insufficient detail on generalization attempts. If you worked on a skill in the therapy room but also attempted it at the sink or during snack time, that belongs in the note. Generalization data is what separates a clinic-bound skill from an actually learned skill. Missing it makes the treatment look narrower than it was and gives supervisors incomplete information about client progress.
What Happens When Documentation Fails
Poor notes don't just create administrative headaches. They directly impact treatment decisions. When a supervisor reviews a case and sees inconsistent data recording or missing antecedent information, they can't determine whether a behavior is decreasing due to intervention or fluctuating because of uncontrolled variables. This leads to either unnecessary program changes or failure to change programs that need changing. Both outcomes waste time and reduce client progress.
Insurance reviews operate the same way. A denial isn't usually about the service itself. It's about the inability to verify that the service was medically necessary based on the documentation provided. You can provide excellent direct services and still get denied if the notes don't demonstrate necessity and progress with enough specificity.
Templates vs. Structured Forms
Free downloadable templates exist in abundance. Some are decent. Most are too generic to be useful across different client populations. A template designed for a preschool client with autism won't work for an adolescent with developmental delays who presents entirely different target behaviors and reinforcement strategies.
The better approach is building your own structured form around the data elements that matter for your specific caseload. Include fields for: client identifier, date, session start and end time, target behavior with operational definition, antecedent condition, prompt level, response accuracy, reinforcement delivered, any behavioral incidents with function hypothesis, generalization attempts, and plan for next session. Keep it to one page per client per session. Anything longer becomes unsustainable during busy clinical weeks.
Electronic platforms have made this easier. Systems like CentralReach, ABA Connect, and RethinkBehavioral include built-in note templates that align with insurance requirements. They also auto-populate data for graphing, which eliminates the transcription step where most errors occur. The tradeoff is that these platforms have a learning curve and monthly costs. For solo practitioners or small clinics, the time savings usually justify the expense within the first few months.
A Specific Problem I Ran Into
About three years ago, I was working with a client whose challenging behavior was intermittent but intense. The behavior occurred primarily during math instruction and was documented as "refused to work" across multiple sessions. The data looked flat. No progress. No regression. Just consistent refusal.
I went back and re-examined the antecedent conditions across twelve sessions. The pattern I found was that the behavior never occurred on the first problem of a set but escalated on the second or third. The antecedent wasn't "math demand." It was "sustained demand beyond two items." That distinction changed everything. We restructured the program into two-item sets with a break or preferred activity between sets. Within four sessions, the refusal dropped from occurring on every session to occurring on approximately one in six sessions.
The lesson here is that session notes need to capture enough environmental detail to allow pattern recognition. If you only write the obvious antecedent, you'll miss the subtle variables that actually drive the behavior. I now include a column on my forms for "possible contributing factors" that I fill in during the session rather than after. It catches things like client fatigue, recent medication changes, or environmental distractions that wouldn't occur to me in a retrospective write-up.
The Counter-Intuitive Part
Better documentation doesn't always mean more notes. Sometimes it means fewer notes with higher signal-to-noise ratio. I've seen clinicians write two pages of narrative per session. Half of it was clinical observation that belonged in a supervision log, not a session note. The other half was redundant data that already existed on the data sheet. The result was a document that was thorough on paper but difficult to extract useful information from quickly.
A session note should be retrievable in under thirty seconds by another qualified professional. If it takes longer, you've included too much irrelevant information or organized it poorly. The goal is utility, not comprehensiveness for its own sake.
What This Approach Doesn't Solve
No documentation system fixes poor clinical judgment. If you're targeting the wrong behaviors, using ineffective reinforcement strategies, or failing to conduct proper functional assessments, your notes will accurately reflect that failure. Documentation is a mirror, not a cure.
It also doesn't eliminate the administrative burden entirely. Even with streamlined templates and electronic systems, session notes typically consume twenty to thirty minutes per day for a full caseload. That's time taken from direct service or rest. The workaround is batching. Write notes for similar clients back to back when the context switching cost is lowest. Don't jump between a nonverbal preschool client and a verbal adolescent client and expect clean transitions. Your brain needs a moment to reset between different behavioral profiles.
If you're managing a large caseload and the current system is unsustainable, consider whether the issue is the documentation method or the session structure. Sometimes shorter, more frequent sessions with focused targets produce better outcomes and require less documentation overhead than longer sessions trying to cover too many programs. That's a clinical decision, not a documentation one, but they're connected.