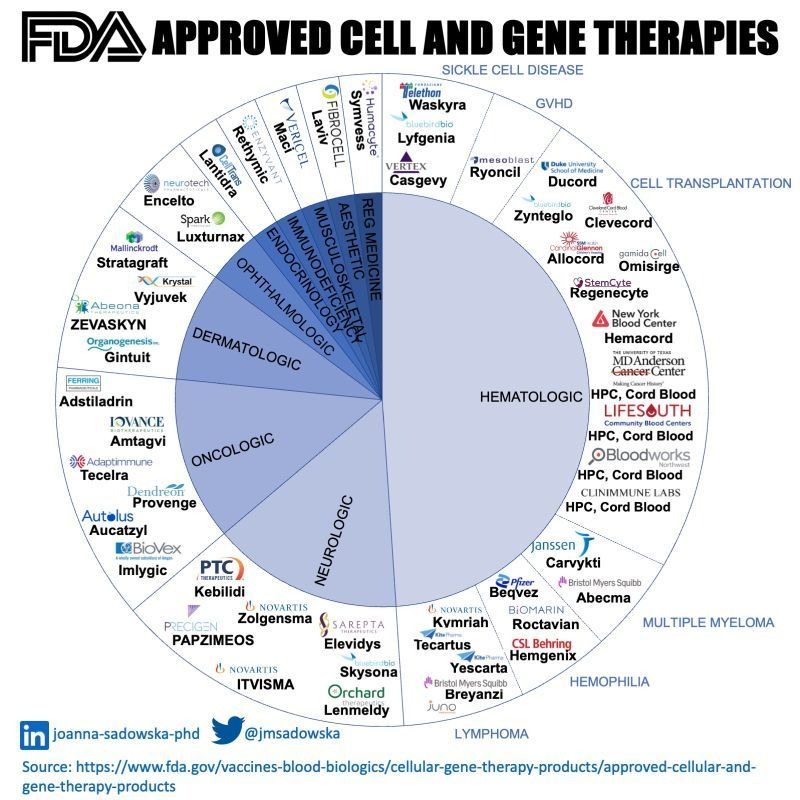
So You Want to Track Approved Cell And Gene Therapies
I spent roughly three years trying to build a reference tool for clinicians who needed quick access to the status of various therapies. The first problem nobody warns you about is that the regulatory landscape shifts constantly. An approval in Europe doesn't mean anything in the US, and vice versa. China and Japan have their own tracks. If you're building something to track these, you need a database that can handle multiple jurisdiction states per therapy. I learned this after shipping a v1 that listed only FDA approvals and spent two weeks fielding angry emails from European researchers who couldn't figure out why orphan designations and conditional marketing authorizations from the EMA were missing. The fix was adding jurisdiction-aware rows and color-coding the approval type so users could tell at a glance whether something was fully approved, under priority review, or still in phase 3.
Approved Cell And Gene Therapies: How They Actually Work
The basic mechanism is straightforward once you strip away the press releases. In gene therapy, a viral vector carries a corrected or new piece of genetic material into patient cells. The most commonly used vectors are adeno-associated viruses (AAV) and lentiviruses. AAV tends to be used for non-dividing tissues like retina and liver. Lentivirus integrates into the host genome and is the standard for CAR-T cell therapies where you're modifying immune cells ex vivo before returning them to the patient. Cell therapies work differently depending on the modality. CAR-T involves extracting T cells from a patient, engineering them to express a chimeric antigen receptor targeting a specific tumor antigen, expanding them in culture, and reinfusing them. The product is autologous, meaning it's personalized to that one patient. Allogeneic products use donor-derived cells and can be off-the-shelf, but they carry higher rejection risk and more complex immunogenicity data requirements. The hard part is not understanding the biology. It's the regulatory and manufacturing infrastructure around it. Every batch is essentially a clinical trial in itself. You need GMP-compliant facilities, chain-of-traceability systems, and quality control testing that runs for weeks before a single dose can be released to a patient.
Building Your Own Tracker or Database
If you want to create something useful, start with the public sources. The FDA maintains a list of approved gene therapies and cellular products. Their page isn't well-designed but it is accurate. The EMA has a dedicated section for advanced therapy medicinal products. WHO has a registry, though it's more of a reporting mechanism than a live tracker. ClinicalTrials.gov gives you the pipeline information that never makes it into commercial summaries. I built mine using a simple SQLite database with one table per jurisdiction and a master index that cross-references them by substance name and INN. The key insight is to normalize by the active substance, not the brand name. Kymriah and Yescarta both target CD19 but are completely different products with different safety profiles. Mixing them up because they share an indication will get you in trouble fast. For the data entry workflow, I used a combination of web scraping from the FDA and EMA pages and manual verification. About 40 percent of the entries required human review because the automated extraction picked up press releases and proposed indications that were never actually approved. This took me longer than I wanted to admit but it was the difference between a useful tool and a liability.
Get the Full Details

Approved Cell And Gene Therapies You Should Know About Right Now
As of mid-2024, the landscape includes roughly two dozen approved products across the US, EU, and Japan. On the US side, you have the CAR-T therapies: Kymriah and Yescarta for certain lymphomas, Tecartus for mantle cell lymphoma and ALL, Breyanzi for autoimmune conditions and lymphoma, Abecma and Carvykti for multiple myeloma. Then there's Lyfgenia for sickle cell disease and Casgevy, the first CRISPR-based therapy approved for both sickle cell and transfusion-dependent beta thalassemia. Luxturna remains the only approved gene therapy for a genetic condition affecting the eye, and Zolgensma is still the most expensive single dose anywhere in medicine. Roctavian for hemophilia A got EMA approval but stalled at the FDA due to manufacturing and immunogenicity concerns that are still being resolved. In the EU, the list is similar but with some notable gaps. Several therapies approved in the US haven't received marketing authorization in Europe yet, usually because the benefit-risk assessment differed or the manufacturer chose not to pursue it. Japan's approvals tend to lag both by about two years, which creates a real access problem for patients in markets without domestic manufacturing.
Pitfalls and Where Everything Breaks Down
Here's what nobody puts in the marketing materials. Autologous CAR-T has a failure rate that's not discussed enough. I watched a patient's T-cell product fail to expand adequately during manufacture, which meant they never got the infusion. There's no workaround for that at the point of care. The patient loses time, potentially their window of eligibility, and moves on to a different therapy or clinical trial. The cold chain logistics for these products are brutal. Some CAR-T products need to be delivered within a specific window and cannot be frozen. I once dealt with a shipment that got delayed at a customs facility for eleven hours because the temperature monitoring log had a gap. The vendor refused to accept it back and the hospital couldn't use it. The patient had to reschedule and wait for a new leukapheresis procedure, which took another two weeks. Another issue that trips people up: orphan drug designation is not approval. A therapy can carry an orphan label for rare diseases and still be nowhere near commercially available. I see this confuse researchers constantly. Same with accelerated approval. The FDA can grant accelerated approval based on surrogate endpoints, and the full confirmatory trial may never complete. Vaxteq is an example where the pathway shows its limits.
Cost is the third major breakdown point. These therapies routinely cost between three hundred thousand and two million dollars per course of treatment. Insurance coverage varies wildly even within the US. Prior authorization processes can add six to eight weeks of delay. I've seen patients start treatment through clinical trials simply because the insurance route was taking too long and the disease was progressing.

Where to Find Reliable Data
The FDA CBER website is the primary source for US approvals. Their gene therapy pages get updated whenever a new product gets licensed or a labeling change occurs. The EMA's homepage for advanced therapies serves the same function in Europe. For global tracking, the International Society for Cellular Therapy publishes a periodic report that's more reliable than most commercial summaries. If you're building something yourself, I'd recommend starting with a JSON structure that maps each therapy to its INN, target antigen or gene, vector type, approval jurisdictions, and current clinical status. I settled on that after trying a relational model that became impossible to maintain as jurisdictions added new entries every few months. Flat JSON files synced from official APIs turned out to be the least painful approach. The biggest gap in available data is real-world safety outcomes. Post-marketing surveillance for these therapies is still maturing. Long-term follow-up requirements are typically fifteen years, which means most published data only covers the first three to five years. Adeno-associated virus vectors can integrate at off-target locations and the clinical significance of that is still being worked out. You won't find definitive answers on that in any regulatory filing today.