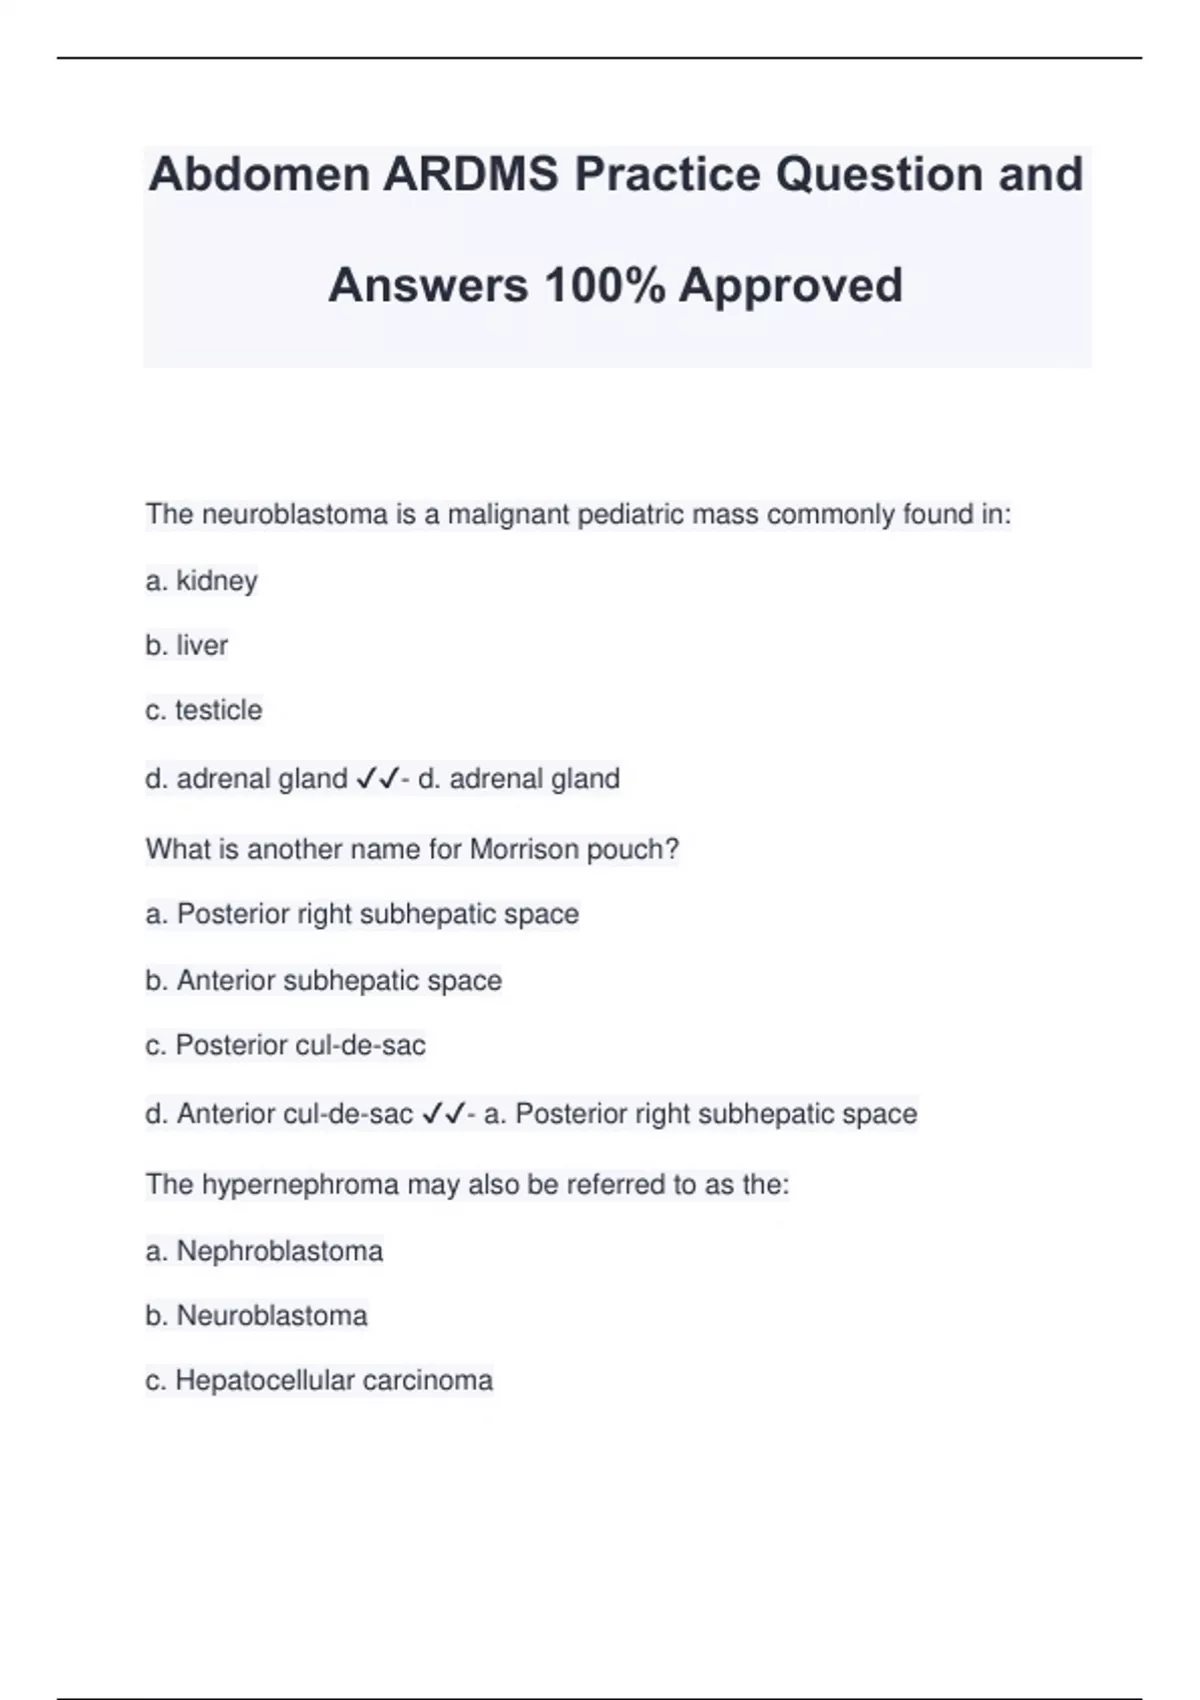
Preparing for the ARDMS Abdomen Registry Exam
The ARDMS Abdomen (AE) exam tests your ability to identify normal anatomy, recognize pathology, and apply measurement standards across hepatic, pancreatic, splenic, renal, vascular, and retroperitoneal structures. It is a computer-based test with roughly 120 questions, most of which are image-based. You get about 2 hours. The pass rate hovers around 65-70%, which means roughly one in three first-time takers does not clear it on their initial attempt. I spent about six weeks prepping last year, and the hardest part was not the content itself but the image recognition pace. I had studied hepatobiliary anatomy until it was second nature, but on practice tests I kept hesitating on Doppler waveforms in the portal venous system because the sample volume placement looked slightly off on a few questions. That hesitation cost me time I couldn't get back. My workaround was to go through the practice question bank twice in timed mode — first pass for accuracy, second pass purely for speed — and I started flagging any waveform question I answered incorrectly. By the third week, my average time per image question dropped from about 45 seconds to under 30.
Ardms Abdomen Practice Test
The most effective way to prepare is to simulate the actual testing environment as closely as possible. The exam interface shows one question at a time with a built-in timer. Most candidates use dedicated practice question banks from sources like Lake Region Medical's ARDMS prep materials, or commercial platforms like Echo Sim and SonoSim. Some residents rely on the SPI/Abdomen review books paired with an online Q-bank. Whatever you choose, make sure the images are high resolution — blurred ultrasound images on a practice test will not train your eyes for what you see on exam day. Here is how I structured my study routine. Week one and two were content review. I went through the liver, pancreas, spleen, kidneys, and major vessels section by section, focusing on what the exam actually asks about rather than trying to memorize everything in the textbooks. The registry does not ask you to perform a complete exam protocol — it asks about the most commonly tested pathology findings and the measurements that matter clinically. For the liver, that meant cirrhosis staging, focal lesion characterization (hemangioma, HCC, FNH, cysts), biliary obstruction patterns, and portal hypertension signs. For the pancreas, chronic pancreatitis calcifications and pseudocysts showed up far more often than rare neuroendocrine tumors. I learned to prioritize accordingly. Week three and four shifted to active practice. I did two full-length practice exams every other day, then reviewed every single wrong answer immediately while the question was still fresh. This is where most people lose ground — they take a practice test, check their score, and move on without understanding why they missed a question. I kept a notes document where I wrote down the specific concept behind each error. One pattern I noticed was that I consistently misidentified porta hepatis landmarks when the gallbladder was contracted. I went back and reviewed the biliary tree anatomy, specifically the relationship between the cystic duct, common bile duct, and common hepatic duct in transverse view at the porta hepatis. After that review, my accuracy on those questions jumped from about 60% to roughly 90%.
The final two weeks were pure drill. I stopped reading new material and focused entirely on timed question sets. My target was answering at least 80% of practice questions correctly under timed conditions before scheduling the actual exam. I also practiced using the exam's annotation tools — zoom, rotate, freeze — because on the real test you can manipulate images but not all software simulators give you that functionality. If your practice platform does not include these tools, find one that does or practice on a machine that does. What the exam covers in detail The AE exam is divided into several content domains. General abdominal and retroperitoneum questions make up the largest chunk. This includes the liver parenchyma and vasculature, biliary tree, pancreas, spleen, adrenal glands, kidneys, and abdominal aorta with its branches. Vascular questions can include Doppler interpretation of the hepatic artery, portal vein, splenic vein, and renal arteries. You should be comfortable identifying normal spectral waveforms and recognizing abnormal patterns like reversed diastolic flow in the hepatic artery, which suggests elevated intrahepatic resistance, or non-pulsatile portal venous flow, which indicates portal hypertension.
Get the Full Details

Obstetric and gynecological content appears in smaller numbers but is still fair game. The exam sometimes mixes in early pregnancy dating questions or basic fetal biometry, though these are less common than the abdominal content. You should at minimum know the basic first-trimester landmarks and crown-rump length measurement guidelines, since they occasionally appear as straightforward questions. Pitfalls that catch people off guard One counter-intuitive thing about the exam is that it does not always present the most obvious pathology first. A question might show a seemingly normal liver on grayscale and then ask about a subtle finding on Doppler. The answer is not always the large mass you spot immediately — sometimes it is the slightly blunted hepatopetal flow pattern or a small hypoechoic lesion that only becomes apparent when you adjust the gain. I learned to consciously slow down and evaluate the entire image field before committing to an answer, rather than locking onto the most prominent abnormality.
Another common mistake is misinterpreting the question stem. Some questions ask you to identify the structure shown, others ask about the diagnosis, and some ask what the next step in management should be. These are fundamentally different, and the exam writers intentionally place similar images with different question stems to test whether you are actually reading carefully. I lost points on a few practice questions because I assumed the question was asking for a diagnosis when it was actually asking for the anatomical structure. I started underlining the key verb in each question stem — identify, diagnose, recommend — which helped me stay focused. LIMITATIONS of practice tests No practice test perfectly replicates the real exam. The image quality on some third-party question banks is lower than what you will see on the actual exam. The timing pressure is also different — on the real test, you cannot go back to previous questions once you move forward, but some practice platforms let you review and change answers freely. This creates a false sense of security. If your practice scores are consistently 85% or higher on a platform that allows answer changes, expect them to drop by 5-10% on the actual timed exam. I saw this happen to myself and to several study partners. The gap was not due to lack of knowledge but due to the stricter time constraints and the no-return policy.
Additionally, practice questions tend to over-represent certain pathologies while under-representing others. I noticed my question banks featured plenty of hemangioma and simple cyst cases but relatively few pancreatic lesion questions compared to what I saw on the actual exam. You cannot rely solely on any single Q-bank. Supplement with textbook atlas review and, if possible, case discussions with sonography colleagues who have recently taken the exam. What to do on exam day Arrive 15 minutes early with two forms of identification. The Pearson VUE testing centers are strict about this. Bring a small snack and water if allowed — the exam is 2 hours and a lot of mental energy goes into rapid image discrimination. Wear layers because testing rooms vary in temperature. During the exam, flag any question you are uncertain about and move on. The flag feature lets you return to it later, but do not sit on a hard question for more than a minute or two. Your time per question averages out to about 1 minute and 10 seconds, and dwelling on one question steals time from several easier ones you could answer quickly.

Resources worth looking into Berry and Reeder's Diagnostic Sonography is a solid comprehensive reference, though it is dense. Rumack's Diagnostic Ultrasound covers the with excellent atlas-quality images. For quick review, the ARDMS Study Guide by the American Registry itself is free and provides an outline of all exam topics with recommended readings. Online, the Lake Region website offers a smaller but well-curated question bank specifically for the Abdomen specialty. Several Reddit communities and Facebook groups for sonography students also share recently released exam topics, though the accuracy of those shared memories varies. If you put in consistent, focused preparation and use practice tests strategically rather than just as score checkpoints, the AE exam is very passable. It rewards pattern recognition built through repetition more than it rewards deep theoretical knowledge. Train your eyes, manage your time, and do not overstudy the rare conditions — focus on the common ones until recognizing them is automatic.