Why People Wear Sweats to Job Interviews And Call It Coping
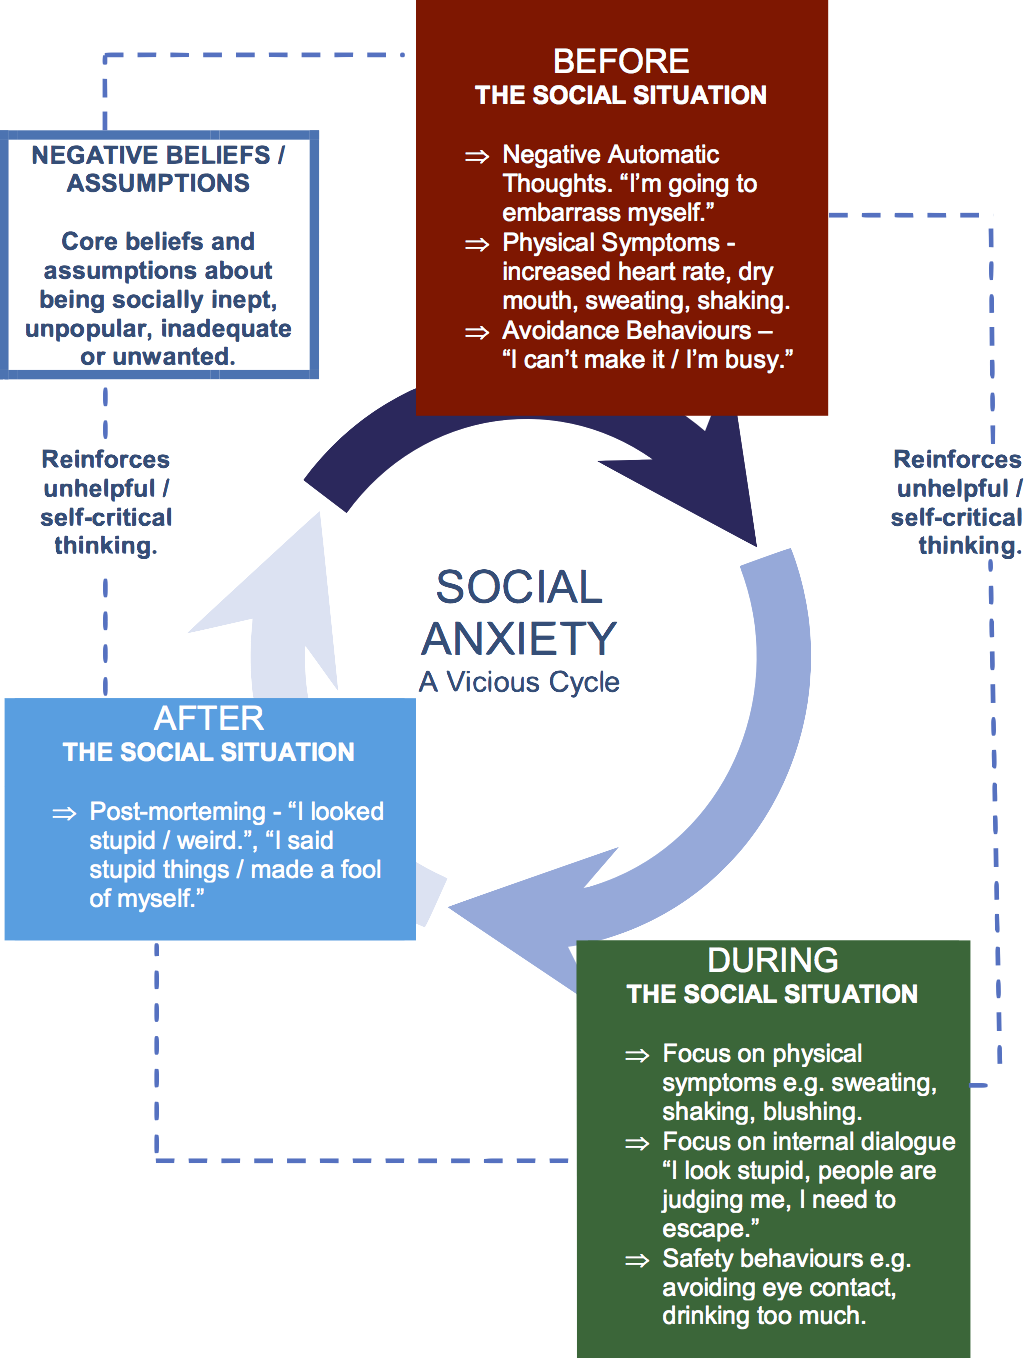
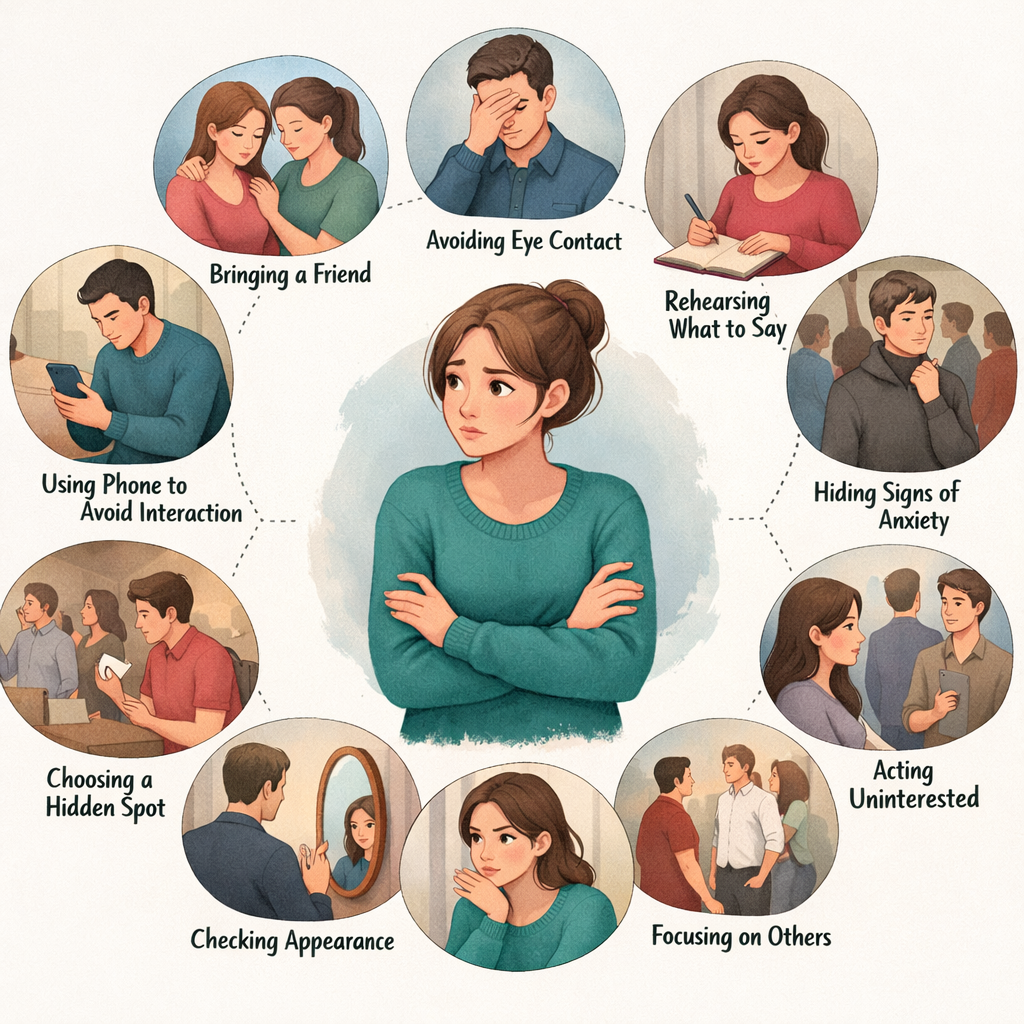
There is a category of behavior that shows up constantly in therapy offices and group chats. I have watched clients spend years perfecting their avoidance toolkit. Some of it is obvious, some of it is barely visible. The blanket term people use is safety behaviors. In clinical language, these are mental or behavioral acts that reduce anxiety in social situations such as wearing bland clothes, rehearsing lines before speaking, staying near exits, avoiding eye contact, or mentally checking yourself for signs others can detect. Here is the part most people do not understand about safety behaviors. They work. They reduce anxiety in the short term. That is exactly why they are so hard to stop.
Understanding What Are Mental Or Behavioral Acts That Reduce Anxiety In Social Situations Such As Wearing Bland Really Do
A safety behavior is any action, mental or physical, that a person performs to reduce the likelihood of a feared outcome or to cope with distress in an anxiety-provoking situation. The classic examples are well documented in cognitive behavior therapy literature. Rehearsing what you will say before entering a meeting. Arriving early to a party so you are not caught unprepared. Wearing neutral, boring clothing so you do not draw attention. Carrying water as an excuse to pause. Standing close to the door. The mechanism is straightforward. Anxiety rises, you perform the behavior, anxiety drops. The brain records the correlation between the behavior and relief. Next time, the behavior becomes the default route. Over weeks and months, the repertoire expands. What starts as one coping strategy becomes a full system of avoidance maintenance. I worked with someone for about eight months who could not attend client meetings without wearing the same gray hoodie every single time. She said it made her feel invisible, which she interpreted as safe. When we started exposing her to situations without the hoodie, she reported panic at levels she had not felt since college. The hoodie was not making her anxious. The hoodie was preventing her from learning that the situation itself was tolerable.
The Problem With Short-Term Relief
Safety behaviors create a learning block. This is the counter-intuitive part that most people miss. When you use a safety behavior, you never get disconfirmation of your fears. If you believe people will judge you unless you rehearse everything, and you rehearse everything and nothing bad happens, your brain attributes the positive outcome to the rehearsal, not to the inherent safety of the situation. The maladaptive belief stays intact. In exposure therapy terms, this is called inhibitory learning failure. You are getting habituation to the situation, but not the kind of learning that changes the underlying threat assessment. After treatment, people who relied heavily on safety behaviors tend to relapse at higher rates than people who learned through unrestricted exposure. There is a specific edge case that most guides ignore. Sometimes the safety behavior itself becomes the trigger. I had a client who wore noise-canceling headphones everywhere. After three months of treatment, she reported that removing the headphones caused more anxiety than keeping them on, even though she still wore them. The object had shifted from coping tool to anchor. This happens because the anxiety reduction became associated with the object itself through classical conditioning, not just through the functional relationship to the situation.
Get the Full Details

How To Identify Your Own Safety Behaviors
The first step is usually noticing patterns you have normalized. Keep a log for two weeks. Every time you feel social anxiety, record what you did in the five minutes before the feeling peaked. Common items on the list include: Planning exactly what you will say. Checking your appearance in reflective surfaces before leaving. Positioning yourself where escape is easiest. Monitoring your own heart rate or breathing. Bringing objects that give you a sense of control. Avoiding topics that might invite extended interaction. Using alcohol or medication as a precondition for attendance. Lying about why you cannot attend. The most deceptive safety behaviors are the ones that look productive. Reading the agenda before a meeting. Writing out questions in advance. Arriving twenty minutes early. These feel responsible. They are often just structured avoidance dressed in professional clothing.
Removing Safety Behaviors Without Losing Your Mind
The evidence-based approach is behavioral experiment design, not willpower. You do not just stop. You systematically test whether the feared outcome actually occurs when the safety behavior is absent. The protocol works like this. Start with one behavior and one low-anxiety situation. Pick something that feels slightly uncomfortable but not destabilizing. If you normally rehearse your opening line before introductions, go to a social gathering where you know at least one person and do not rehearse anything. Observe what actually happens. Most people report that conversations proceed normally. Some report awkward moments. Almost no one reports the catastrophic outcome they predicted. This process usually takes between four and eight sessions to complete for a single behavior. The timeline depends on how entrenched the behavior is and how consistently you practice. I have seen clients make rapid progress when they stuck to the schedule, and stalled for months when they skipped sessions or switched targets mid-experiment.
There is a practical limit to what behavioral experiments can address. Safety behaviors that serve a genuine functional purpose should not be removed. If someone uses noise-canceling headphones because they have sensory processing differences, that is accommodation, not avoidance. If someone rehearses presentations because they are learning a new language, that is skill-building. The distinction matters clinically and ethically. The rule of thumb is simple. If the behavior is driven by fear of social evaluation rather than practical necessity, it is likely a safety behavior worth investigating. For people with severe social anxiety disorder, complete removal of safety behaviors without support can be counterproductive. Some clients need pharmacological support, structured group therapy, or accommodation modifications before they are ready for full exposure work. There is no moral obligation to push through panic. The therapeutic goal is expansion of tolerance, not destruction of coping capacity. The most sustainable outcome I have observed is when people replace safety behaviors with approach behaviors. Instead of wearing gray to avoid attention, they wear one small item that reflects personal taste. Instead of rehearsing every sentence, they practice letting conversations drift. Instead of standing by the exit, they position themselves in the center of the room and stay for the full duration. The shift from avoidance to engagement tends to produce lasting change because it builds new learning pathways rather than simply removing old ones.