Understanding the Nine-Region Abdominal Assessment
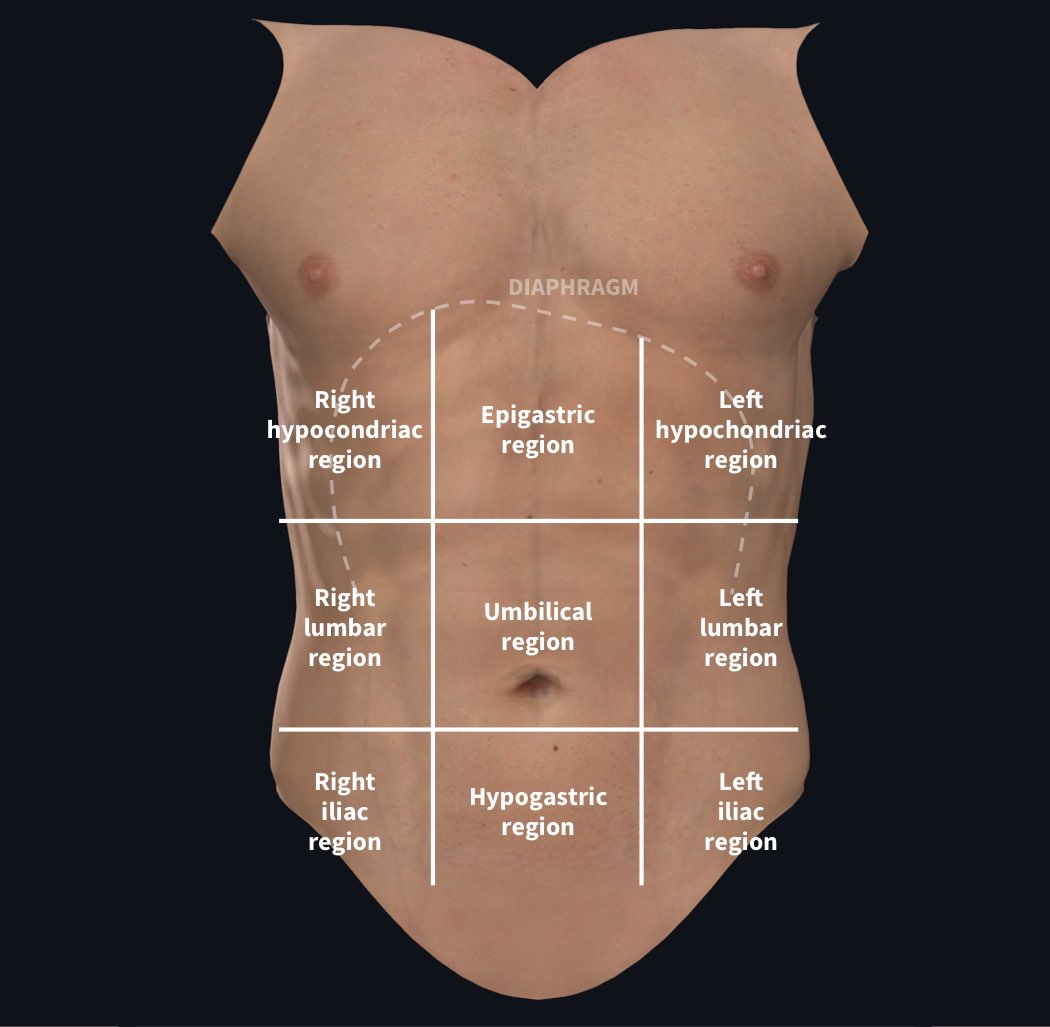
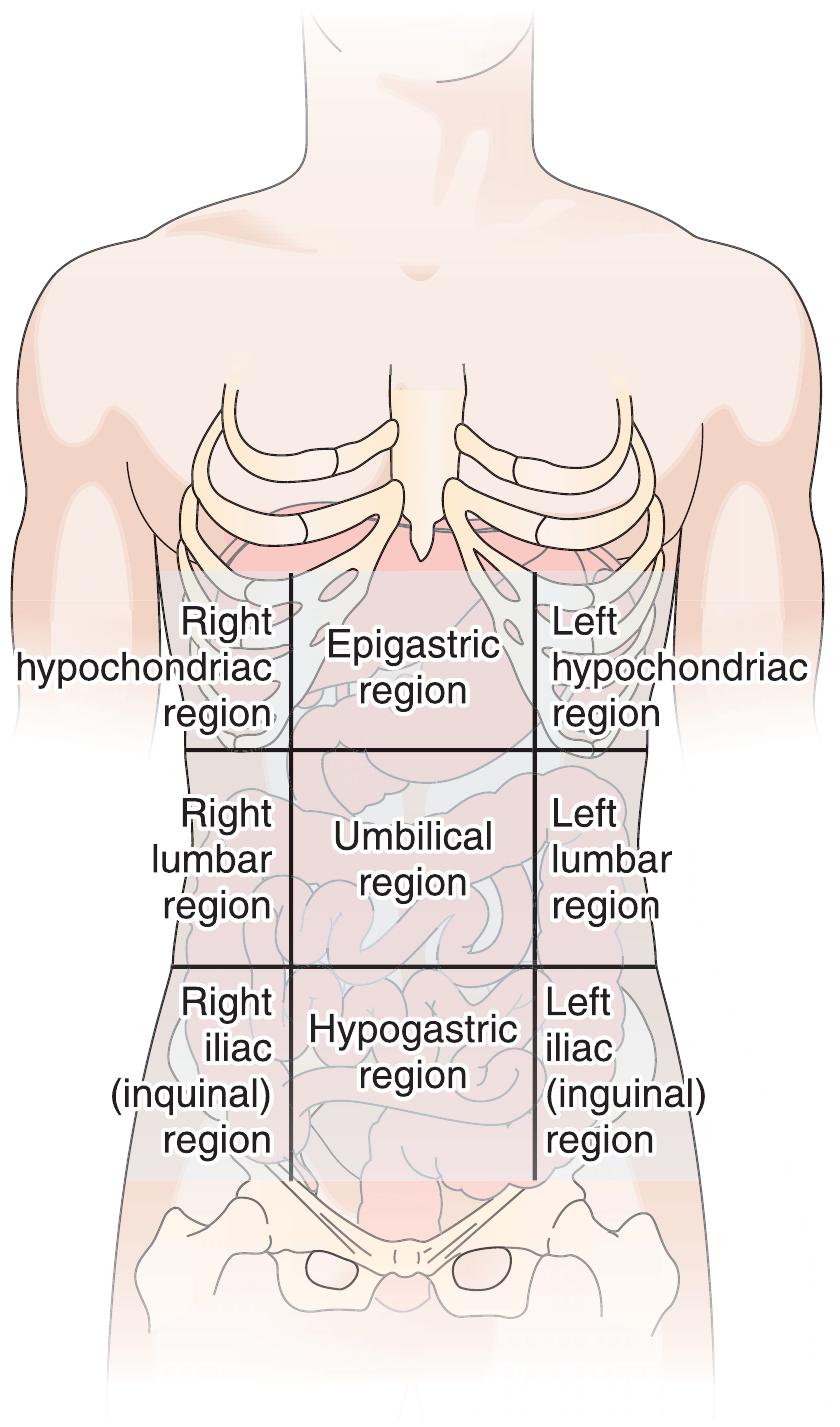
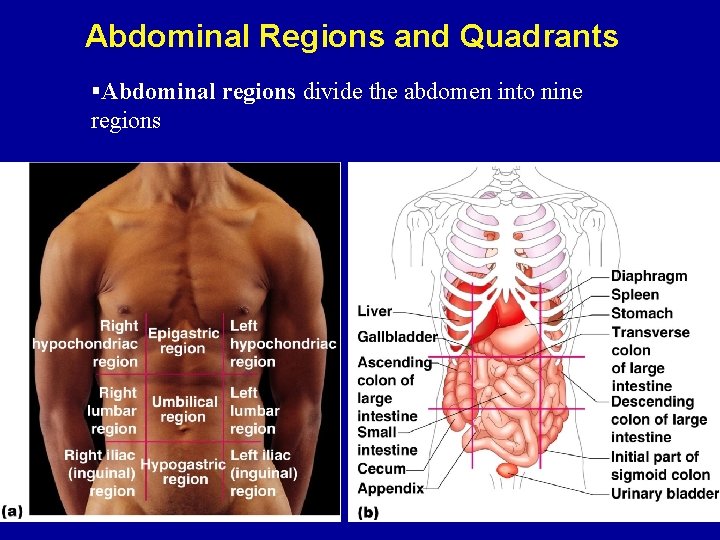
The abdomen gets divided into nine regions for clinical purposes, and most people only learn about the right upper quadrant or the epigastric area. The reality is messier than what textbooks show. I've spent years working through abdominal assessments in busy emergency settings, and here's what actually matters when you're trying to map Areas Of Abdomen 9 correctly. Start with the surface landmarks. You need the xiphoid process, the costal margins, the anterior superior iliac spines, and the pubic symphysis. Draw two vertical lines along the midclavicular planes and two horizontal lines—one through the subcostal plane and one through the intertubercular plane. That gives you nine zones. The upper horizontals catch liver, gallbladder, and stomach issues. The middle ones deal with pancreas, small intestine, and kidney concerns. The lower thirds involve bladder, reproductive organs, and sigmoid colon.
Common Mistakes When Learning Areas Of Abdomen 9
The biggest problem I see is that people rush through palpation without proper relaxation technique. A tense patient makes the whole exam unreliable. About two years ago, I was working a late shift and had a patient who reported pain in the left lower quadrant. Standard Areas Of Abdomen 9 assessment pointed toward diverticulitis. I pressed the area and got nothing—no rebound, no guarding. Then I had them breathe deeply and relax while I rechecked. Turned out the real issue was a hernia in the inguinal region that wasn't showing up on the initial exam. The patient had been clenching because they were anxious about being examined. I used a different approach: I had them bend their knees and rest their arms at their sides, then I examined from behind first while they weren't watching my hands. That technique changed everything about how the abdominal wall responded. Another counter-intuitive thing nobody tells you: the order of examination matters more than individual steps. Inspect, auscultate, percuss, then palpate. Doing palpation first messes up bowel sound detection. I've seen residents skip auscultation entirely and then wonder why their diagnosis of gastroenteritis was completely wrong. The sounds are still there if you take two minutes to listen properly. There's also a nuance with referred pain patterns. Pain in the right upper quadrant doesn't always mean gallbladder. Liver capsule stretch from hepatitis, subphrenic abscess, or even pneumonia can present there. I once had a patient whose "appendicitis" was actually lower lobe pneumonia radiating to the right lower quadrant. The Areas Of Abdomen 9 framework helped me track where the pain started and where it went, which eventually pointed away from the appendix.
Practical Application for Different Scenarios
If you're studying for clinical exams, focus on the clinical correlations for each zone.RUQ contains liver, gallbladder, duodenum, head of pancreas, right kidney, hepatic flexure, and right adrenal gland. RLQ involves cecum, appendix, right ovary, right fallopian tube, right ureter, and terminal ileum. LUQ has stomach, spleen, body of pancreas, left kidney, splenic flexure, and left adrenal gland. LLQ covers sigmoid colon, left ovary, left fallopian tube, left ureter, and bladder dome. The central zones—epigastric, umbilical, and hypogastric—contain the transverse colon, small bowel, aorta, and various retroperitoneal structures. The problem with nine-region division is that it's not always precise enough for every situation. Some anatomical variations mean organs sit slightly differently than textbook diagrams suggest. Obesity shifts things around. Previous surgeries create adhesions that move things. Pregnancy distorts the normal layout entirely. In these cases, quadrant examination (four-quadrant method) often works better than the full nine-region breakdown. I should mention that the nine-region system has real limitations. It's most useful for surface mapping and initial assessment, but imaging studies like ultrasound and CT are far more accurate for definitive diagnosis. No amount of physical exam skill replaces a good CT scan when you're dealing with something like a retroperitoneal hemorrhage or a strangulated bowel. The physical exam narrows the differential; imaging confirms it.
Get the Full Details

For self-examination, check your own abdomen monthly. Note any new lumps, asymmetry, or tenderness. The umbilical region is where you'll often notice things first because it's central and accessible. If you find something unusual, don't panic, but don't ignore it either. Most abdominal findings turn out to be benign, but early detection of anything suspicious makes treatment significantly easier. When teaching this material to others, I always emphasize that learning the Areas Of Abdomen 9 system is step one, but clinical judgment matters more than memorization. The zones are guides, not rules. Patient presentation, history, and context all factor in. A young woman with pelvic pain needs a different approach than an elderly man with sudden onset abdominal pain. Both might involve the same regions, but the urgency and differential change completely based on the person in front of you.