Understanding Areolar Connective Tissue
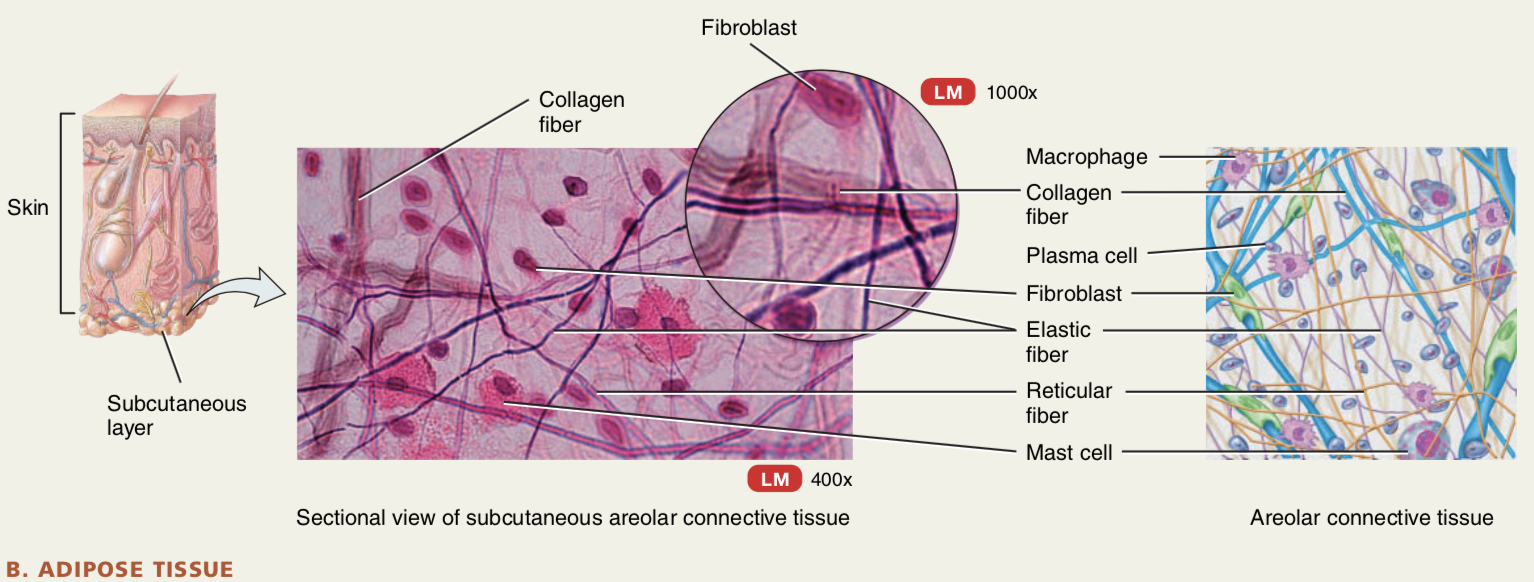
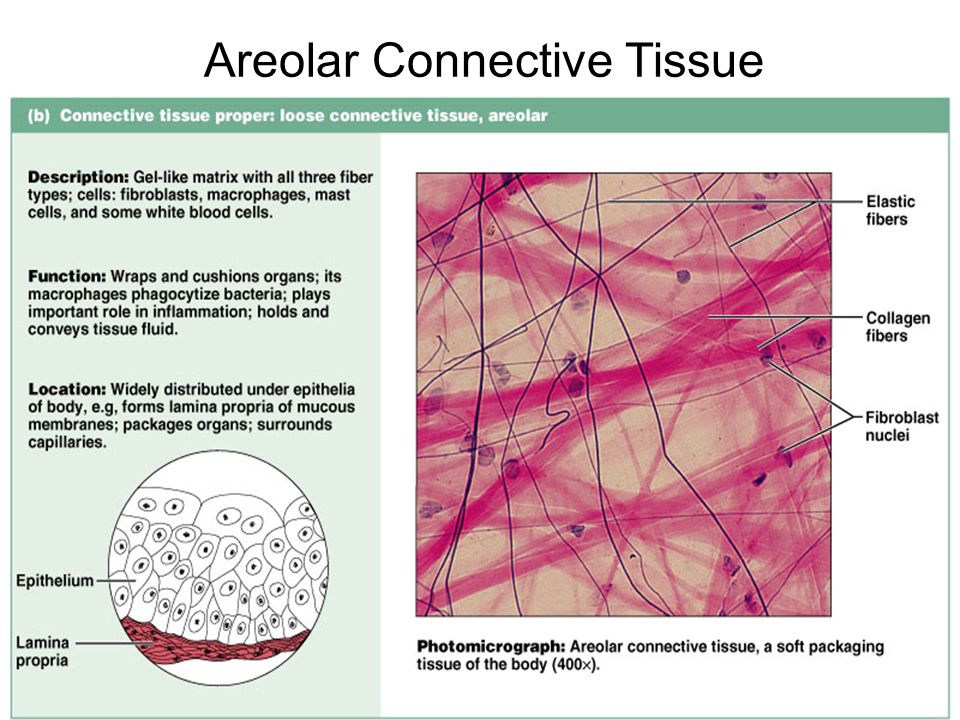
Areolar connective tissue is the most widespread type of loose connective tissue in the human body. It sits beneath the skin as the hypodermis, wraps around blood vessels and nerves, fills spaces between muscles, and lines body cavities. The name itself doesn't tell you much, but the structure is straightforward: it consists of loosely arranged collagen and elastic fibers suspended in a gel-like ground substance, with scattered fibroblasts, macrophages, mast cells, and adipocytes. When students first learn histology, they tend to memorize location lists and move on. That approach works for passing an exam, but it falls apart when you actually need to use this knowledge in a clinical or research setting. The tissue is everywhere, which is exactly the problem.
Common Areolar Connective Tissue Location Sites
The Areolar Connective Tissue Location is not restricted to one or two places. You will find it subcutaneously from the dermis down to the fascia. It surrounds organs in the abdominal and thoracic cavities as mesentery and serosal layers. It occupies the oral cavity within the lamina propria under the mucous membranes. It lines the eyelids, the scrotum, the penis, and the areola of the breast. It also forms the supportive framework of the liver, pancreas, and spleen as the stroma. In the eye, it is present in the choroid layer between the sclera and the retina. What ties all these sites together is function, not anatomy. This tissue provides a permeable matrix that allows immune cells to patrol, fluids to drain, and nutrients to diffuse. That permeability is why it is also the primary site for inflammatory responses and why edema becomes so visible there first.
Practical Considerations in Dissection and Histology
I have spent years working with this tissue in both gross anatomy labs and histology workflows, and the gap between textbook descriptions and actual practice is wider than most guides admit. Here is what matters when you are actually handling it. When dissecting, areolar tissue appears as a pale, semi-translucent sheet that separates cleanly from denser structures. That separation is useful, but it is also misleading. The tissue is not uniformly loose. In some regions, particularly around the eyelids and the male genitalia, it is exceptionally thin and delicate. A sharp dissection tool will tear through it before you even realize you are applying force. I use blunt-tipped forceps and a scalpel held at a shallow angle, almost scraping rather than cutting. This preserves the plane between areolar tissue and the underlying fascia. It takes more time initially, but it saves hours of reworking damaged specimens later. For histology, the standard formalin fixation works, but there is a specific issue with thin sections from areolar-rich regions. The ground substance is mostly proteoglycans and glycosaminoglycans, which wash out during routine processing. If your protocol includes prolonged alcohol dehydration or xylene clearing, the tissue can collapse entirely, making fiber identification nearly impossible. I switch to a shorter ethanol series and skip the extended xylene step. Instead, I use a clearant substitute like Histoclear for half the normal duration. The results show collagen and elastic fibers with far more clarity, and slides from the same specimen stay usable for months longer.
Get the Full Details

Counter-Intuitive Points That Beginners Miss
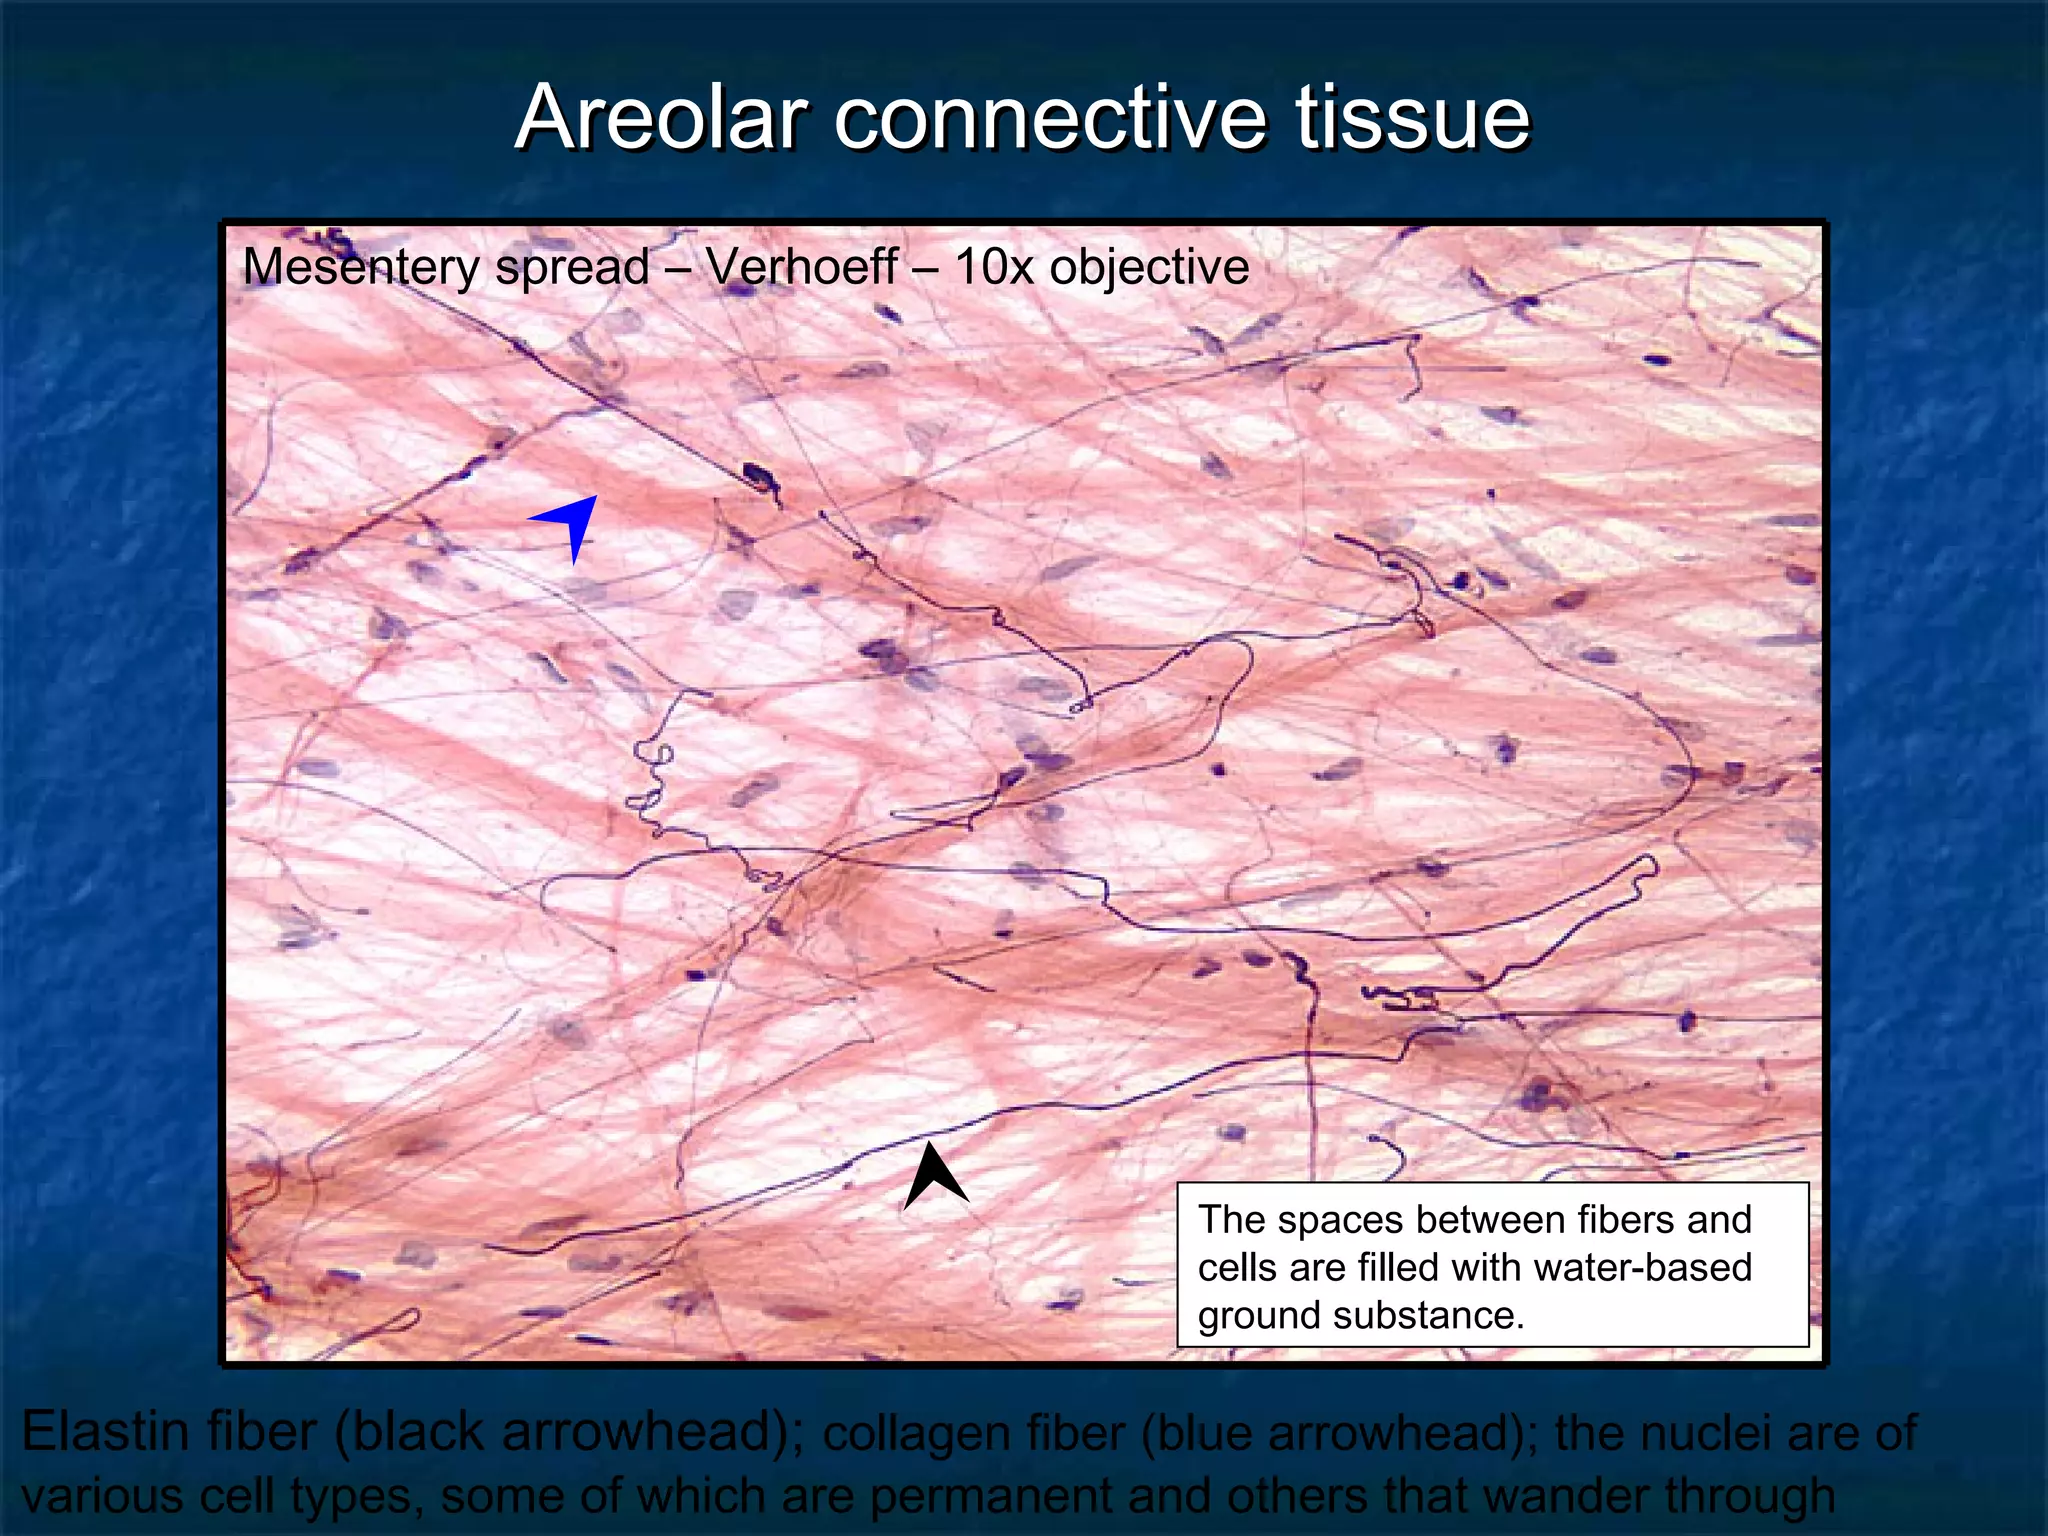
Most introductory courses treat areolar tissue as passive filler. It is not. It actively regulates fluid balance through its ground substance composition. The hyaluronic acid concentration determines how much interstitial fluid can be held before pressure builds and edema manifests. This is clinically relevant in conditions like lipedema, where the molecular composition of the matrix in subcutaneous areolar tissue is altered, not just the volume of fat cells. Another point that rarely gets emphasized is the role of adipocytes within areolar tissue. They are not randomly distributed. In certain regions like the periorbital area and the lower abdominal wall, adipocytes cluster in distinct lobules separated by fibrous septa. When you see a histology slide that appears to have "too much fat" for typical areolar tissue, you are likely looking at a region where adipose conversion is a normal feature, not a pathology. Mistaking this for a sample contamination error is a common mistake in undergraduate labs. The elastic fiber network is also more extensive than most H&E stained sections reveal. Standard staining does not highlight elastin well. If you need to assess the structural integrity of areolar tissue, especially in vascular or pulmonary applications, you should use Verhoeff-Van Gieson or Elastica stain. The additional twenty minutes of preparation time is worth it for the specificity you gain.
Limitations and Where This Knowledge Breaks Down
Areolar connective tissue is abundant and accessible, but that advantage comes with constraints. The same permeability that makes it useful for nutrient exchange also makes it a primary route for infection spread. In clinical scenarios involving cellulitis or necrotizing fasciitis, the tissue planes within areolar regions allow pathogens to move rapidly along paths that are invisible from the surface. This is not a theoretical concern. I have seen cases where the apparent boundary of an infection on imaging was wrong because the pathogen had tracked through areolar planes deeper than expected. Another limitation is in surgical reconstruction. When grafts or flaps are placed into areas rich in areolar tissue, the integration depends heavily on revascularization through that loose matrix. In patients with chronic steroid use or advanced diabetes, the ground substance composition changes, and neovascularization slows significantly. The graft may appear viable initially but fail weeks later. There is no reliable predictive test for this beyond assessing the patient's overall metabolic state before proceeding. If you are working with areolar tissue in a research context and need to isolate specific cell populations, standard collagenase digestion protocols can be too aggressive. Fibroblasts from areolar tissue are more sensitive to enzymatic breakdown than those from dense regular connective tissue. I reduce collagenase concentration to 1 mg/mL and extend incubation to 90 minutes at 37°C with gentle agitation. This yields a higher viable cell count without excessive debris, though the trade-off is a longer prep time.
Summary
The practical study of areolar connective tissue goes well beyond memorizing a list of locations. Understanding how it behaves during dissection, how it responds to different histological protocols, and where its limitations create real-world problems is what separates competent work from amateur results. The tissue is universal in its distribution but variable in its behavior, and treating it as a single uniform entity will lead to consistent errors.