Arkansas LPN Scope of Practice: What You Actually Do Day to Day
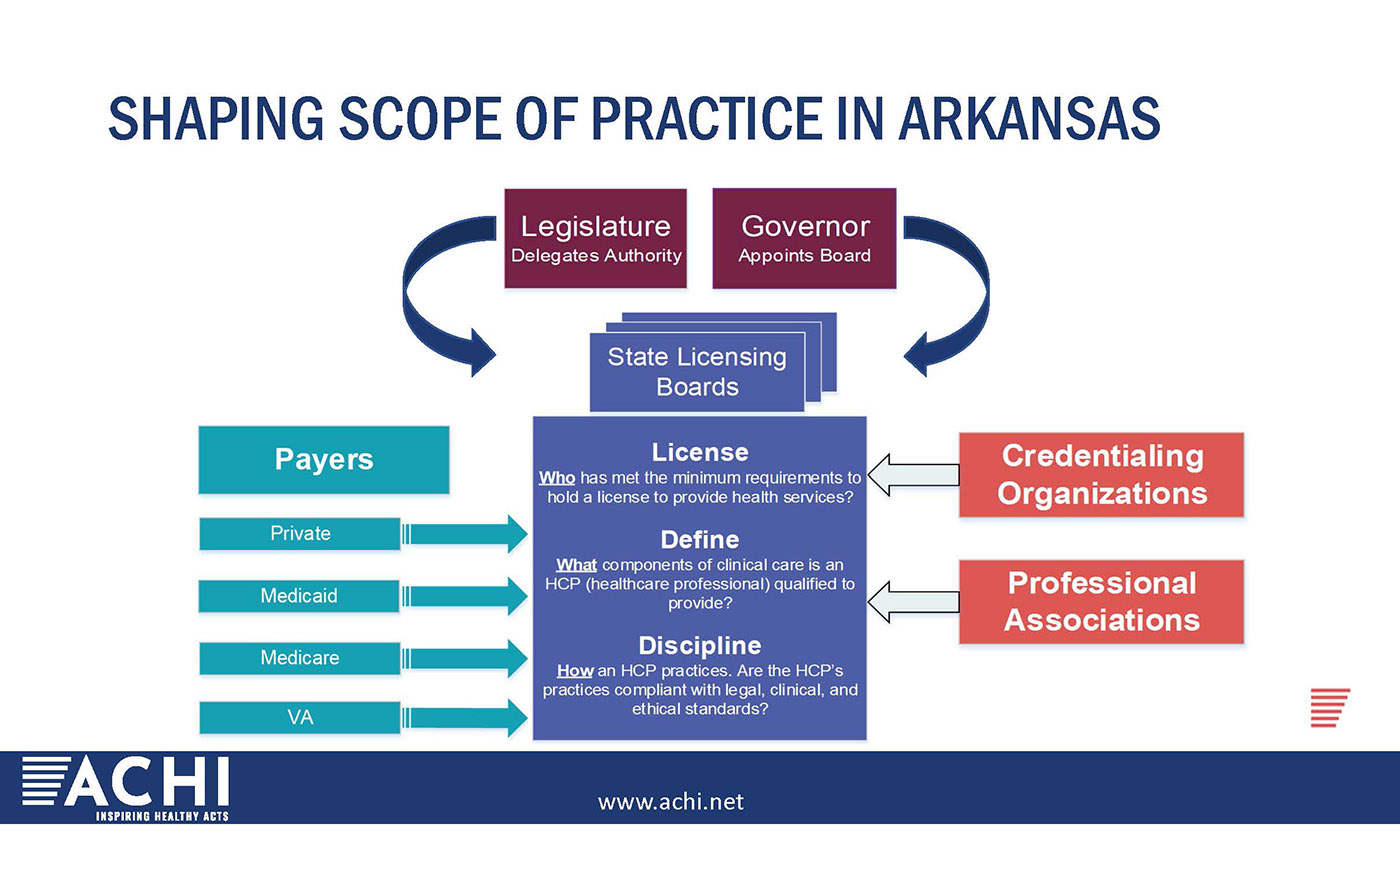
The Arkansas State Board of Nursing regulates what Licensed Practical Nurses can and cannot do in the state. The official scope is outlined in the Arkansas Nurse Practice Act and the Board's administrative rules. I work in a long-term care facility in Little Rock, so most of what I know comes from dealing with this stuff directly rather than reading policy documents in a vacuum. LPNs in Arkansas practice under the supervision of a physician, dentist, podiatrist, or registered nurse. That "supervision" part matters more than people realize. It's not the same as having someone standing over your shoulder at all times, but it does mean certain decisions and assessments have to come from an RN or provider level, not yours.
Understanding the Arkansas Lpn Scope Of Practice
Here's what an LPN in Arkansas is generally authorized to do: Administer medications by oral, topical, intramuscular, subcutaneous, and intradermal routes. IV push medications are allowed under specific conditions and with appropriate training, though many facilities restrict this internally beyond what the Board permits. Starting and managing IV fluids falls within scope as long as you have the required competency validation from your employer. Performing focused assessments on stable patients, collecting data, and reporting changes to the supervising RN or physician. This is where the line gets fuzzy. LPNs can and do assess patients, but comprehensive nursing assessments are an RN responsibility. In practice, I've seen LPNs document significant clinical findings that turned out to be the first indicator of sepsis in a resident, and the RN followed up with the full assessment. Both roles are doing their part within the scope.
Providing wound care including dressing changes and wound measurements. Catheter insertion and care. Drawing blood for lab work if trained and credentialed through your facility. Administering vaccines. Patient education on medications, disease processes, and self-care techniques. Documenting care in the medical record. What an LPN in Arkansas cannot do independently: initiate a nursing care plan, perform the initial comprehensive admission assessment, administer blood products, titrate IV medications, or delegate nursing tasks to unlicensed personnel. Those are RN or provider responsibilities.
Get the Full Details

The Delegation Question Is Where Most Problems Come Up
The biggest source of confusion I see isn't about the medication routes or procedures listed in the rules. It's about delegation. Arkansas allows LPNs to delegate certain tasks to unlicensed assistive personnel, but only tasks that are within the LPN's own scope and only when the LPN has verified competency in that task. I ran into a specific problem last year involving a CNA who was assigned to help a patient with feeding tube care. The LPN on the unit had never actually demonstrated competency in PEG tube care, even though it's technically within the LPN scope. I pushed back on the assignment because delegating something you haven't validated yourself on creates liability for everyone. The workaround was straightforward — the charge RN took over that task for the shift, and the facility scheduled the LPN for competency validation the next week through their in-service coordinator. It added about two hours of scheduling hassle, but it prevented a potential board complaint. The trick most people miss is that the LPN's ability to delegate doesn't exist in a legal vacuum. Your facility's policy might be stricter than the Board's rules. Some hospitals prohibit LPNs from delegating anything beyond vital signs and ambulation assistance. Before you assume you can delegate a task, check both the administrative rules and your employer's policy manual. The Board sets the floor, not the ceiling.
IV Therapy Scope Specifics
Arkansas LPNs can initiate peripheral IVs and manage IV therapy, but the Board requires documented competency completion. This isn't something you can self-credential. Your employer has to evaluate you and sign off on it. Most LPN programs in Arkansas include some IV training, but program completion alone doesn't authorize you to start IVs at work. The facility does that separately. IV push medications are a more complicated area. The Board permits LPNs to administer IV push drugs, but certain facilities restrict this to RNs only through internal policy. If you're looking to work in a hospital setting and IV push is important to your role, you'll need to verify what each facility allows before accepting a position. Nursing homes and skilled nursing facilities tend to be more permissive since their patient populations typically don't require that level of IV intervention.
Assessment vs Monitoring — Know the Difference
This is a counter-intuitive point that trips up new LPNs constantly. The Arkansas LPN scope allows you to collect data and monitor patients, but the nursing process term "assessment" as used in comprehensive care planning belongs to the RN. In plain language, you can notice that a patient's skin is warm and dry, their respiratory rate is elevated, and they're reporting increased pain. You document those observations. You report them. That's monitoring and data collection, and it's entirely within your scope. What you cannot do is synthesize those findings into a nursing diagnosis and determine the overall plan of care without RN or physician direction. The distinction matters because if a board inquiry comes your way, the difference between "I collected and reported data" and "I made an independent clinical judgment" can be the difference between a clean record and a reprimand. The practical reality is that experienced LPNs often function as the clinical eyes and ears of a unit. You catch things first because you spend the most time at the bedside. But knowing when to escalate versus when to document and continue monitoring is a skill that comes from experience, not from a textbook definition of scope.

Limits and Where the Scope Falls Apart
The scope as written doesn't account well for rural healthcare settings. I've worked shifts in outlying counties where there wasn't an RN physically present on the unit for hours at a time. The Board requires supervision, but the practical reality is that you're functioning with phone-and-pager-level access to an RN who may be thirty miles away. In those situations, you operate under the standard of care for what a reasonably prudent LPN would do given the resources available, but that's a legal interpretation, not a day-to-day guide. Another gap: the rules don't clearly address telehealth-related nursing activities. If an RN is providing remote oversight and needs you to perform a task as part of that continuum, the delegation chain gets murky. You're taking direction from an RN, but that RN isn't in the building. This area is evolving and the Board hasn't issued explicit guidance yet. Until they do, most facilities handle it through written agreements between the provider and the supervising RN.
Where to Find the Official Rules
The Arkansas Board of Nursing maintains the current Nurse Practice Act and administrative rules on their website. The relevant sections cover licensure requirements, scope of practice definitions, and disciplinary procedures. The Board also publishes position statements on specific topics like IV therapy and delegation that provide additional clarification beyond the rules themselves. If you're studying for the NCLEX-PN or preparing for Arkansas licensure, the Board's candidate handbooks and the Arkansas Code Annotated title on nurse practice are the primary sources. They're dense reading, but they're the authoritative text. Third-party review materials summarize the scope, but summaries occasionally miss updates. The Board revises rules periodically, usually after feedback from stakeholders or in response to legislative action. The practical takeaway is that the Arkansas LPN scope is functional but not as expansive as the RN scope, and it operates within a framework of supervision and delegation that requires ongoing attention to both state rules and facility policy. Most LPNs navigate this without issue because the day-to-day work stays well within clear boundaries. The problems tend to come from edge cases — delegation decisions, IV therapy questions, and the assessment-versus-monitoring line — where knowing the rules isn't enough and you also need to understand how they're applied in your specific work environment.



