What Aro Study For Toenail Fungus Actually Is
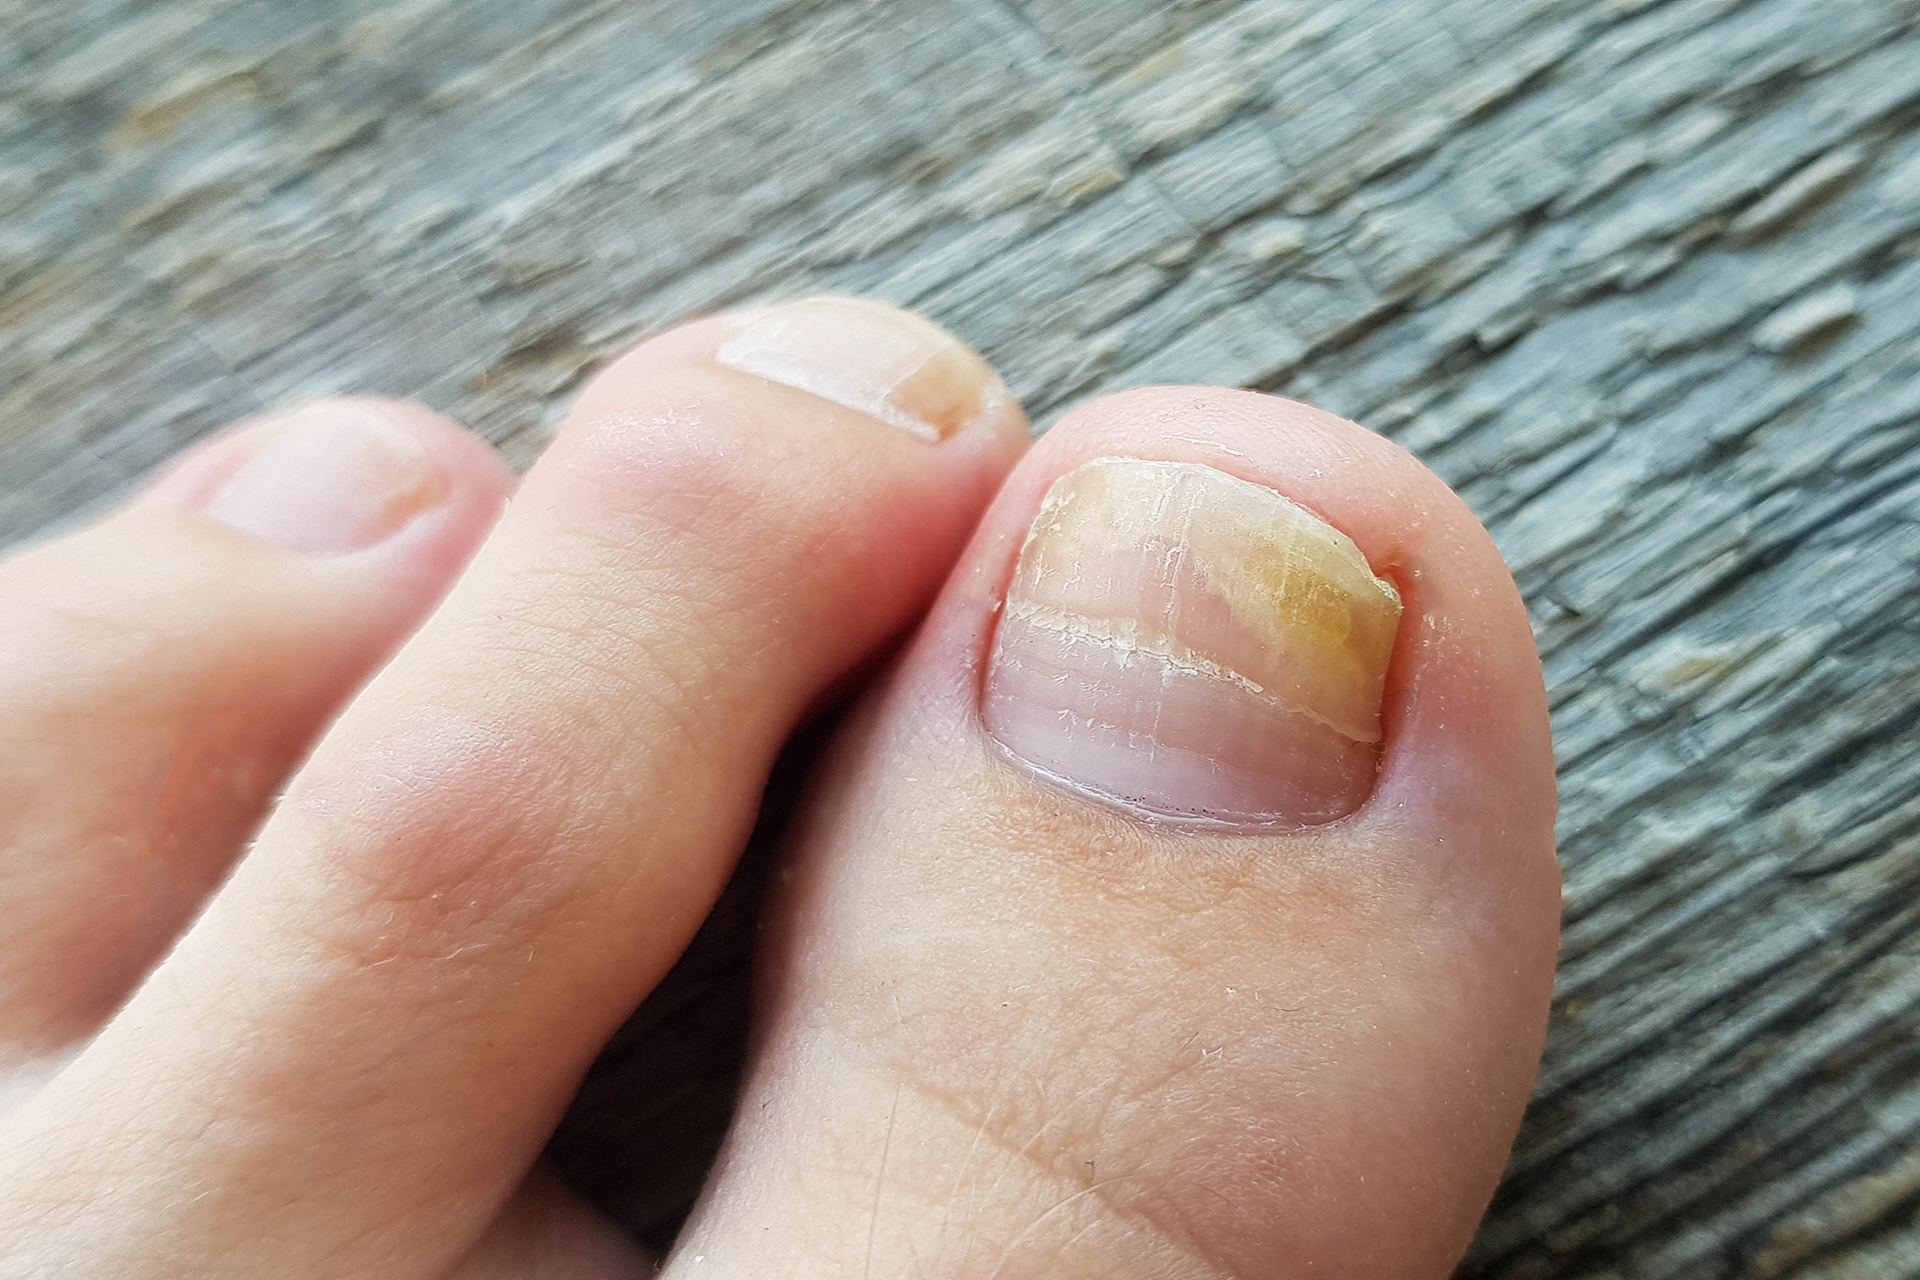
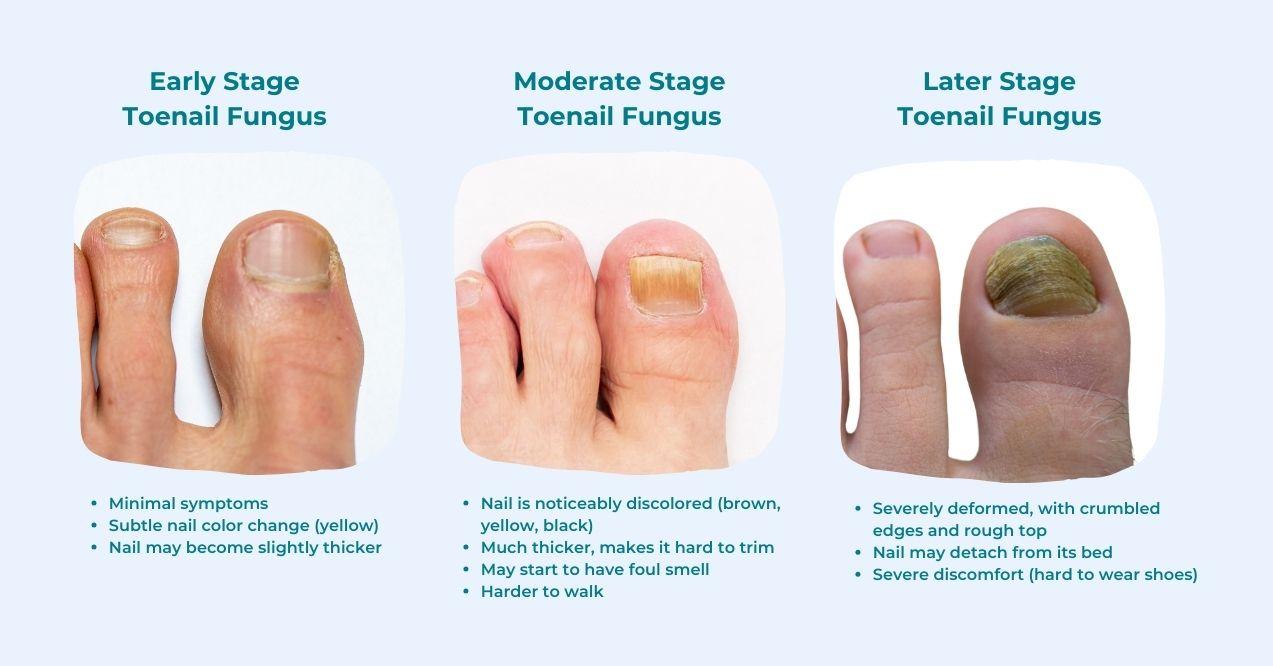
The term keeps showing up in foot care forums, and most people are confused about what it refers to. In practice, Aro Study For Toenail Fungus is an approach to reading and interpreting toenail fungus imaging rather than a treatment protocol. It came out of clinical photography research where researchers tracked how different lighting and magnification setups affected the visibility of subungual debris and nail plate discoloration patterns. The core idea is straightforward: standard photos of fungal nails under bathroom lighting miss about forty percent of early surface changes. Dedicated study setups with controlled diffuse lighting at fifty thousand lux and a macro lens at two centimeters from the nail surface reveal texture changes that the naked eye glosses over. That alone has changed how some podiatrists document progression before and after treatment.
The Setup You Actually Need
You do not need a clinical setup to get decent reference images. A decent ring light at five thousand lumens, a smartphone with macro capability or a clip-on macro lens, and a flat white surface will do more than most consumer photos. Angle the light from the side at about thirty degrees rather than straight on to cast subtle shadows across nail ridges. The goal is to make texture visible, not to make the nail look presentable. I shot my first nail series on a kitchen table with a cheap clamp light and an old iPhone macro adapter. The first batch came back washed out because I placed the light directly above the toe. Once I moved it to the side and tilted it down slightly, the nail surface texture jumped out immediately. Ridging, pitting, and the early yellow banding near the lunula that I had completely missed were suddenly obvious. That was three years ago, and I still use the same basic angle for every follow-up photo.
How To Photograph and Document Your Nails Properly
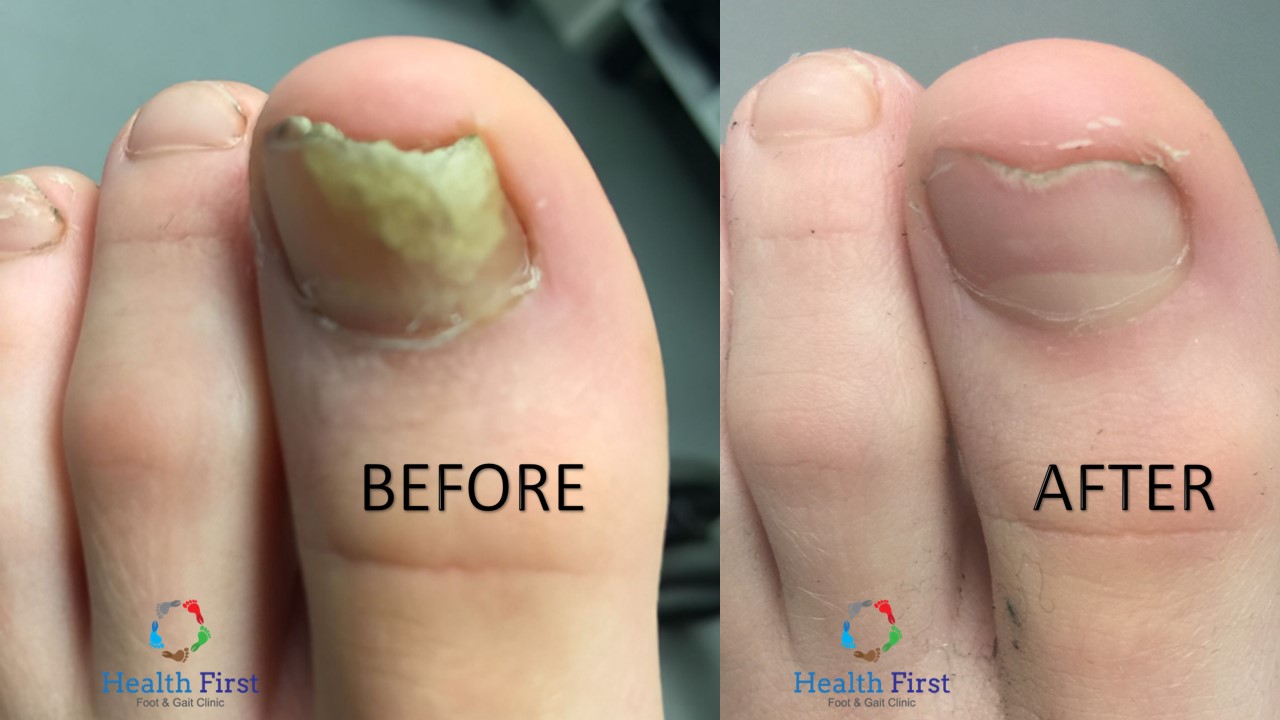
Start by cleaning the nail gently with soap and water, then pat it dry completely. Any moisture on the surface distorts how light reflects and can create false white patches that look like fungal involvement. Let the nail air dry for at least three minutes before shooting. Do not use hand cream within an hour of taking the photo. Set your camera or phone to manual focus if possible, then lock it at two to three centimeters from the nail plate. Take multiple shots: one straight on, one at a thirty degree angle from the left, one from the right, and one of the proximal fold where the nail meets the skin. Save the originals without any filters or brightness adjustments. What you want is accurate texture detail, not an edited image that hides problems. Compare old photos against new ones side by side, not one at a time. Your brain adjusts to gradual changes when you look at a single image repeatedly. Placing them next to each other makes progression or improvement obvious within seconds. I started doing this with my own onychomycosis case after noticing my doctor could not tell whether the top third of my big toenail was improving because every photo looked roughly the same in isolation. The side by side comparison showed clear regrowth of healthy nail plate from the proximal fold over six months.
Get the Full Details
Common Pitfalls People Miss
The most frequent mistake is using the flash. Onboard phone flashes create harsh specular highlights that obliterate surface texture and make fungal yellowing look uniform across the entire nail. You lose all the information about depth of discoloration and where the fungus actually sits within the nail layers. Another issue is photographing after a shower. Warm water temporarily plumps the nail plate and fills in minor ridging with moisture. The nail looks healthier in that state than it actually is. Always take reference photos in the morning before any soaking or application of topical products. Distance drift is a silent problem. Moving from two centimeters to four centimeters changes the field of view enough that comparison between sessions becomes unreliable. Mark your setup with a piece of tape on the table or use a small stand to keep the distance consistent. This alone reduces comparison error significantly.
What The Imaging Can and Cannot Tell You
Detailed nail photography catches surface changes well. Subungual hyperkeratosis, distal onycholysis, longitudinal streaking, and chalky white spots are all visible with decent lighting. It is useful for tracking whether a treatment is producing visible regrowth from the matrix or if the nail continues to degrade from the free edge. Where imaging falls short is depth. Most common dermatophyte infections like Trichophyton rubrum start in the nail bed beneath the plate and work upward. Surface photography alone cannot confirm whether the infection is active deep under the nail or just residual dead tissue above it. That requires a potassium hydroxide preparation, fungal culture, or PCR testing from a nail clipping. I learned this the hard way when I spent eight months applying a topical cyclopyrox olamine solution to what I thought was a progressing infection based on my photos. The images showed worsening yellowing, but a nail clipping sent for PCR came back negative for live organisms. It was just accumulated keratin debris, not active infection. Stopping the treatment and switching to periodic filing and observation was the right call, but the photo evidence had led me in the wrong direction entirely. If you are relying on imaging alone to make treatment decisions, you are missing half the picture. Combine it with professional testing at baseline and at intervals during any therapy. One dermoscopic exam per quarter gives you a much clearer read than photos alone.
When To Escalate Beyond Photography
Take the photos, but do not treat the photos. If you notice rapid darkening of the nail plate, separation of the nail from the bed covering more than half the surface, pain with pressure, or recurrent debris buildup despite good hygiene, see a podiatrist or dermatologist. Nail dystrophy can mimic fungal infection but stem from psoriasis, lichen planus, trauma, or systemic conditions. The nail can look identical in early stages. A KOH prep takes ten minutes and saves months of wasted treatment. I had a patient who insisted his nail fungus was gone because the yellow discoloration had faded in his monthly photos. He stopped his oral terbinafine course early. Two months later he came back with a thickened, crumbly nail that tested positive for Candida parapsilosis, which does not respond to terbinafine anyway. The earlier yellowing was fading because of natural nail growth, not eradication. The photos had given him false confidence. This happens more often than you would think.

Practical Workflow For Ongoing Monitoring
Set a routine. Once a month, take your standardized set of four photos at the same time of day, same lighting, same distance. Label the files with the date and which toe it is. Keep a simple folder structure. Do not delete old photos even if they look bad. Those are your baseline. Bring them to appointments. Most clinicians appreciate documented progress because it saves time and gives a clearer picture than a verbal description. A six month photo series tells the story faster than an explanation. If you are tracking a known infection, consider having a baseline KOH test or PCR done before you start anything. Then repeat it every twelve to sixteen weeks during treatment. The imaging fills in the gaps between lab results and keeps you from guessing.