Ultrasound-Guided Brachial Artery Access: A Practical Walkthrough
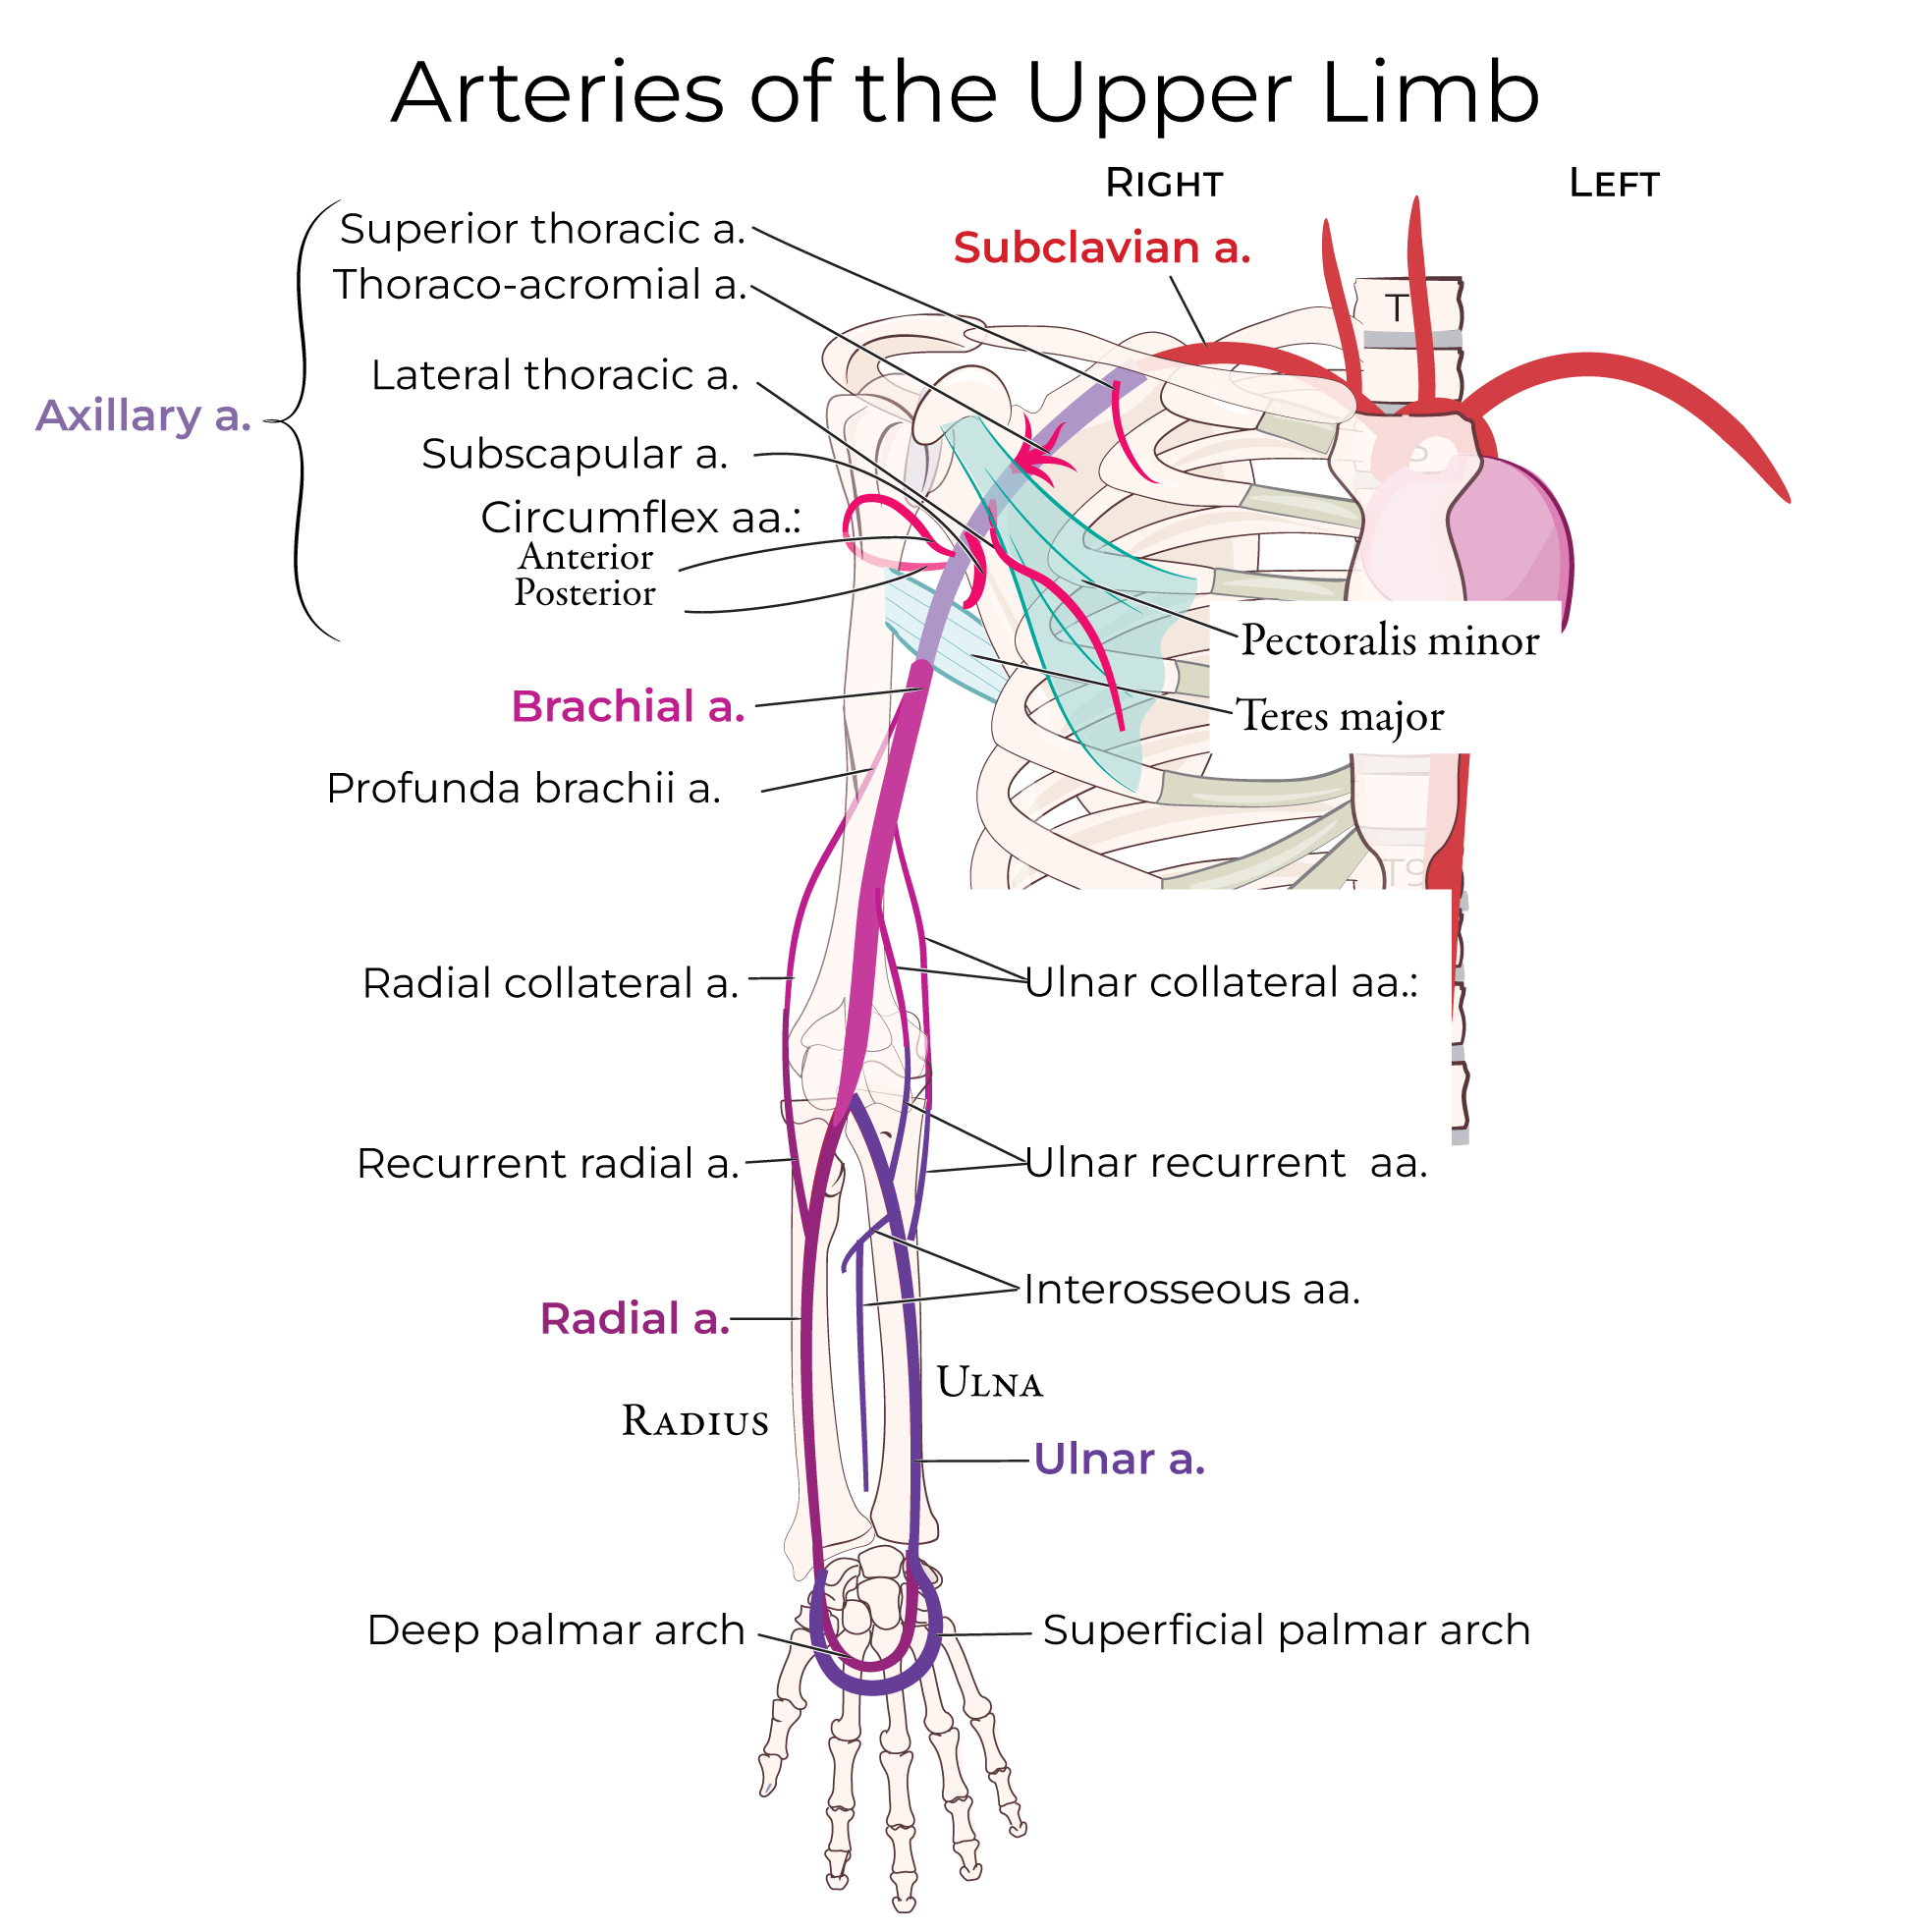
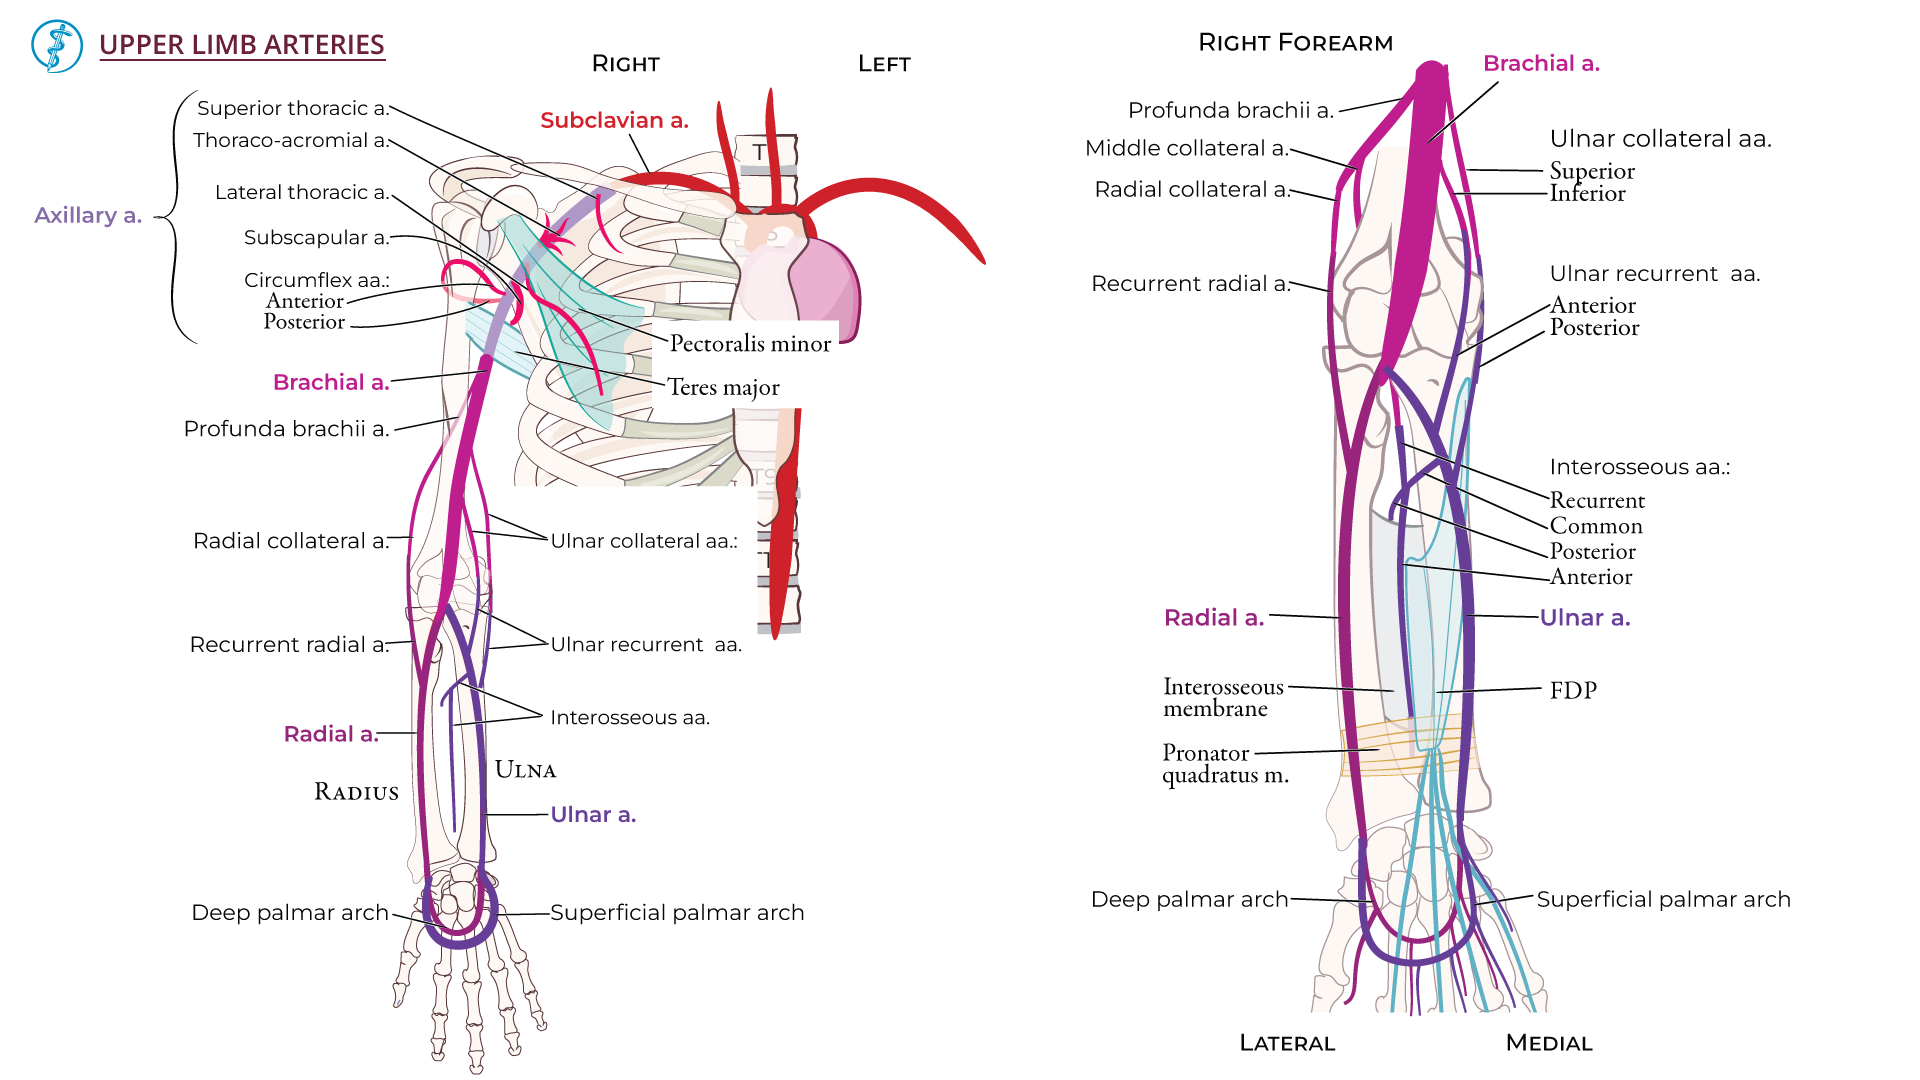
The brachial artery in the arm is nowhere near as straightforward as the femoral approach, even though most textbooks make it look simple. It sits deep between the biceps and triceps, runs alongside the median nerve the entire way, and has very few meaningful collaterals distally. When you mess this up, you mess it up badly. I learned that the hard way during a difficult central line placement in a trauma bay about eight years ago. Understanding the arterial layout of the upper extremity isn't just academic. It determines whether you can safely place a line, get a clean reading, or avoid injuring something you shouldn't. The superficial branching pattern is consistent, but the depth and exact anatomical relationships shift based on body habitus, positioning, and even the degree of hydration. This variability is what makes the arm artery tricky in practice. Start with the basilic vein. It runs along the medial side of the arm and is usually the easiest surface landmark to find. The brachial artery lies just medial and slightly deep to it. In the cubital fossa, the artery sits lateral to the biceps tendon and medial to the lacertus fibrosus. That's where pulse palpation works best.
From there it travels down the midline of the arm. It doesn't give off any major branches until it reaches the elbow, where it bifurcates into the radial and ulnar arteries. The deep brachial artery (profunda brachii) branches off near the surgical neck of the humerus. If you're doing an approach from the lateral aspect, this vessel is one you need to visualize before going in. I once missed it on ultrasound because I was scanning too distally. The resulting hematoma kept the patient for three days. Never skip the proximal scan. The axillary artery continues from the subclavian and becomes the brachial at the inferior border of the teres major. It gives off the anterior and posterior circumflex humeral arteries, plus the subscapular branch. These are relevant if you're considering a higher approach, which most clinicians don't do routinely but should know about.
Ultrasound Technique Step by Step
Use a high-frequency linear transducer. Put it perpendicular to the artery first to identify it as a round, pulsatile structure with good wall definition. Then rotate it longitudinal to trace the vessel and confirm there's no thrombus or stenosis before you commit to a stick. For needle insertion, I prefer the out-of-plane technique for beginners and in-plane for more experienced hands. The angle matters more than the method. Keep it around 30 to 45 degrees. Going too steep increases the chance of going through the far wall and creating a pseudoaneurysm. Saline injection before advancing the needle helps. A tiny amount of saline through the needle tip will show up on ultrasound and confirm you're in the correct tissue plane before you actually puncture. This takes maybe ten seconds and can save you from multiple blind passes.
Get the Full Details
Common Pitfalls and How to Avoid Them
Here's something most guides don't emphasize enough: the median nerve is right there. It's not a rare complication. It happens regularly. When you're targeting the brachial artery, keep the nerve in your field of view the entire time. If it looks compressed or displaced, adjust your approach angle. Don't just push forward hoping for the best. Another issue is arteriospasm. Younger patients, anxious patients, cold rooms — all of it triggers it. If you feel resistance on needle advancement and there's no blood return, back off slightly and wait. Warm compresses help. I use a small heating pad on the arm for five minutes before the attempt in patients who seem particularly tense. It reduces spasm significantly in my experience. Distal embolization is rare but catastrophic. It usually happens when you're dealing with atherosclerotic plaque or when you're manipulating the artery aggressively. Use the smallest gauge catheter you can for your purpose. Don't advance anything past the needle tip without visual confirmation.
A Real Problem I Encountered and the Workaround
I was placing a radial artery line in a patient with severe peripheral vascular disease and virtually no palpable pulse. Ultrasound showed the vessel was calcified and barely compressible. Standard technique wasn't working. I kept missing the lumen on needle passes. What ended up working was switching to a short 22-gauge angiocath instead of the standard introducer needle. The shorter device gave me better tactile feedback and required less depth penetration. I also used a lower insertion angle — closer to 20 degrees — which kept the tip within the visible ultrasound window the entire time. Got it on the second try. The standard longer needle would have gone straight through.
Branching Patterns Within Arterial Anatomy Upper Extremity
The radial artery arises from the bifurcation and runs along the lateral forearm. It's the preferred site for arterial lines and coronary angiography access. The ulnar artery runs medially and is larger in caliber but deeper and more variable in its course. The interosseous artery arises proximally and supplies the posterior compartment. It's not typically accessed percutaneously but is important to recognize on imaging if you're evaluating trauma or compartment syndrome. A counter-intuitive fact: the radial pulse can be present even when the brachial pulse is barely palpable in some patients with proximal subclavian or axillary disease. Don't rely solely on distal pulses to rule out proximal problems. Check both sides and use ultrasound to compare flow characteristics.

Limitations and When This Approach Fails
Ultrasound-guided upper extremity arterial access is not a universal solution. In patients with extensive edema, severe obesity, or prior surgical scarring in the area, the anatomy can be too distorted for reliable imaging. I've had cases where the brachial artery simply couldn't be visualized due to overlying soft tissue. In those situations, switch to the femoral route. It's faster and safer than forcing an upper extremity approach in hostile anatomy. Another hard limitation: coagulopathy. If the patient is on therapeutic anticoagulation or has a significant bleeding disorder, the risk-benefit ratio shifts dramatically. Small hematomas in the arm can compress the neurovascular bundle and cause ischemic complications. I don't attempt this in patients with an INR above 1.5 or platelet counts below 50,000 without significant hematology consultation. Fistula formation is another underappreciated risk. Arteriovenous fistulas can develop at the puncture site, especially with repeated attempts or large-bore sheaths. They're often silent until they cause distal ischemia or heart failure from the shunt. If you suspect one, get a duplex ultrasound and refer to vascular surgery. Early intervention prevents serious morbidity.
The learning curve for this technique is steeper than femoral access. Expect to make more attempts initially. Practice on phantoms or willing colleagues before touching patients. Having a trained sonographer or attending physician available during your early cases dramatically reduces complications. Time spent on supervision now saves hours of management later.