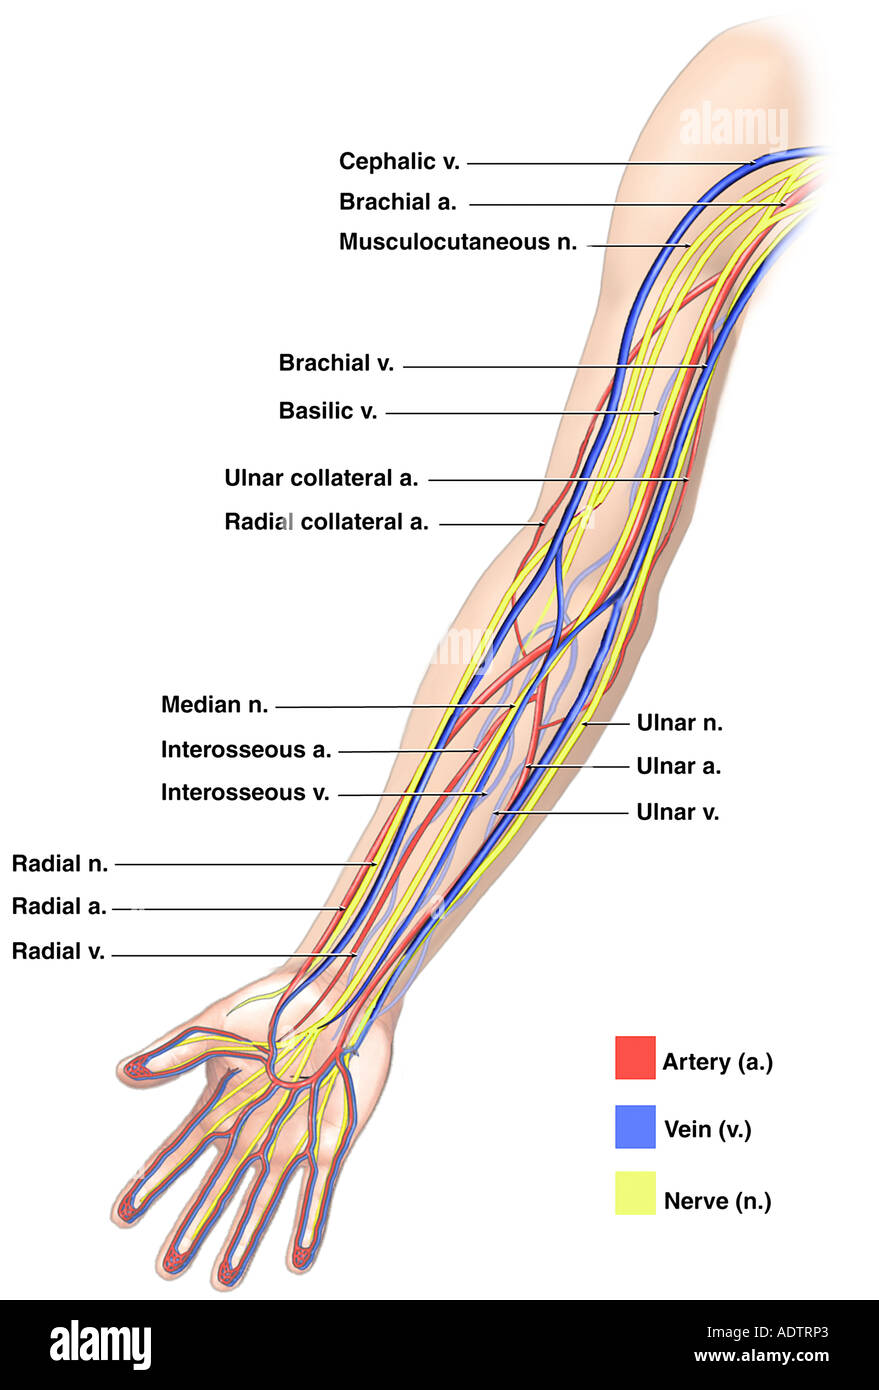
Understanding the Arterial Supply to the Upper Extremity
The brachial artery runs down the anterior compartment of the arm, and it is the primary vessel you are working with if you need vascular access or are studying upper limb anatomy. It is a continuation of the axillary artery at the lower border of the teres major muscle. Most people learn that it bifurcates into the radial and ulnar arteries at the cubital fossa, but the practical details matter more than the textbook description when you are actually dealing with this region. I spent several years doing ultrasound-guided arterial line placements and brachial artery catheterizations before I stopped doing them regularly. One particular case stands out where the anatomy was not what anyone would expect from a standard diagram. The patient had a persistent truncus brachialis, meaning the brachial artery did not split at the expected level. Instead, it continued as a single trunk down to the proximal forearm before giving off both radial and ulnar branches much more distally than usual. Attempting a standard radial stick by surface landmarks in that case was a mistake. I fell back on real-time ultrasound visualization and traced the vessel proximally until I found the bifurcation point, which ended up being approximately 8 centimeters distal to the antecubital crease rather than the typical 2 to 3 centimeters. The procedure took about twelve minutes longer than a routine placement, and honestly, it could have gone badly if I had just trusted palpation alone.
Clinical Considerations With Arteries In The Arm
Palpation of the brachial pulse is straightforward in most adults, but The profunda brachii artery, also known as the deep brachial artery, is a branch thatIt arises from the posterior aspect of the brachial artery in the upper arm and descends through the radial groove on the humerus. This is the vessel that can be injured during mid-shaft humeral fractures, and it is one reason why neurovascular compromise is a common complication of these fractures. I have seen post-reduction angiograms ordered for suspected vascular injury after simple mid-humeral fractures where the mechanism suggested significant force. The timing matters here. If you suspect injury to this system, do not wait more than six to eight hours for definitive imaging, because prolonged ischemia significantly increases the risk of compartment syndrome and permanent functional deficits. Blood pressure measurement using the brachial artery remains one of the most common clinical procedures in medicine. The cuff size matters significantly more than most practitioners realize. An undersized cuff on a large-arm patient can overestimate systolic blood pressure by 10 to 15 millimeters of mercury, and an oversized cuff can underestimate it by a similar margin. I once managed a hypertensive emergency in a patient whose arm circumference was approximately 42 centimeters. The default medium cuff on the wall monitor gave a reading of 180 over 110, but switching to the large adult cuff dropped the reading to 162 over 98. That difference changed the entire management approach, moving from aggressive IV labetalol administration to oral medication adjustment and discharge planning. The correct cuff width should cover approximately 80 percent of the arm circumference, and the bladder should encircle at least 40 percent of the limb.
Anatomical Variants and Clinical Pitfalls
High-riding bifurcation of the brachial artery is one of the more common anatomical variants, occurring in approximately 10 to 15 percent of limbs. Instead of splitting at the cubital fossa, the brachial artery divides at the level of the mid-humerus or even higher. This variant is clinically significant for several reasons. First, it makes brachial artery catheterization more challenging because the target vessel may be shorter proximally. Second, it increases the risk of iatrogenic injury during surgical procedures in the antecubital region, because the surgeon may not expect the bifurcation to be more proximal than typical. I encountered this during a carpal tunnel release where I needed to ligate a persistent median artery, which turned out to be arising from a high brachial bifurcation rather than the normal pattern. The radial artery recurrence is another variant that surgeons should be aware of, particularly when planning free tissue transfers or vascular access procedures. In some patients, the radial artery is not the dominant supply to the hand, and the ulnar artery provides the majority of palmar arch perfusion. Preoperative duplex scanning should be routine when planning flap harvesting from the forearm, because failing to assess collateral circulation can result in ischemic complications post-operatively. The Allen test remains the standard bedside assessment, but it has significant limitations, particularly in patients with peripheral vascular disease or diabetes, where the test sensitivity drops to approximately 60 percent. Complementing the Allen test with Doppler waveform analysis or near-infrared spectroscopy improves accuracy substantially. Compartment syndrome of the forearm is a surgical emergency that can result from arterial injury or reperfusion following ischemia. The pressure threshold for fasciotomy is typically 30 millimeters of mercury or less, but clinical judgment matters more than the number alone. I managed a case where the compartment pressure was 28 millimeters of mercury but the clinical findings were unequivocal, and delaying surgery for additional monitoring would have been a mistake. The five compartments of the forearm require decompression, and failing to release all five can result in persistent ischemia and permanent functional deficits. The timing is critical. If you suspect compartment syndrome, do not wait more than four to six hours from symptom onset, because prolonged compression significantly increases the risk of Volkmann ischemic contracture and permanent nerve damage.
Get the Full Details

Practical Techniques for Arterial Access
Seldinger technique for brachial artery catheterization remains the standard approach for central venous access when other sites are not suitable. The procedure requires local anesthetic infiltration, wire introduction under fluoroscopic or ultrasound guidance, and serial dilation before sheath placement. Complication rates are approximately 2 to 5 percent for major adverse events, including hematoma formation, arterial thrombosis, and distal embolization. The risk increases significantly in patients with coagulopathy, diabetes, or peripheral vascular disease, where the vessel wall is more fragile and healing is delayed. Ultrasound-guided radial artery cannulation has become the preferred technique in most intensive care units, with success rates exceeding 95 percent compared to approximately 70 to 80 percent for landmark-based approaches. The time savings are substantial. A experienced operator can complete a ultrasound-guided radial stick in approximately two to three minutes, compared to five to ten minutes for repeated landmark-based attempts. The cost-benefit analysis favors ultrasound guidance in most settings, particularly for inexperienced operators or difficult patients where multiple attempts increase the risk of complications substantially. The dorsalis pedis artery remains an alternative site for arterial blood gas sampling when radial access is not feasible, but the procedure carries different risks and considerations. The pulse is often difficult to palpate in elderly patients or those with peripheral vascular disease, and the vessel diameter is smaller than the radial artery, increasing the risk of thrombosis and ischemic complications. I have seen cases where dorsalis pedis arterial line placement resulted in foot ischemia requiring surgical intervention, particularly in patients with underlying diabetes or smoking history. The risk-benefit ratio favors radial access whenever possible, and alternative sites should be reserved for specific clinical scenarios where upper extremity access is contraindicated or not feasible.
Common Misconceptions About Upper Limb Arteries
The assumption that the brachial artery is always superficial and easily accessible is incorrect in many patients. Deep brachial arteries, particularly in obese individuals or those with significant muscle mass, can be located several centimeters below the skin surface, making blind techniques ineffective and dangerous. Ultrasound visualization should be considered routine rather than optional when dealing with difficult arterial access, because failing to visualize the vessel increases the risk of posterior wall penetration and hematoma formation substantially. The belief that collateral circulation to the hand is always adequate is another misconception that can lead to serious complications. Patients with occlusive vascular disease, prior surgeries, or congenital variants may have compromised collateral flow, and arterial ligation or prolonged compression can result in ischemic tissue loss. Pre-procedural assessment of collateral circulation using the Allen test or Doppler analysis is essential, and proceeding without this assessment in high-risk patients is negligence by any reasonable standard. The consequences of inadequate collateral assessment can include digital amputation, chronic pain, and permanent functional impairment that significantly affects quality of life. The notion that arterial spasm is a rare complication of arterial catheterization is factually incorrect. Spasm occurs in approximately 5 to 15 percent of arterial line placements, particularly in young patients, those with anxiety, or when using larger catheter-to-artery ratios. The spasm can be transient or persistent, and in severe cases, it can result in complete occlusion requiring pharmacological intervention or catheter removal. Prophylactic topical nitroglycerin or verapamil application has been shown to reduce spasm rates by approximately 40 to 50 percent, and incorporating this simple measure into your procedural protocol can prevent significant complications without adding substantial time or cost to the procedure.