Managing Joint Pain When Your Hands Won't Cooperate
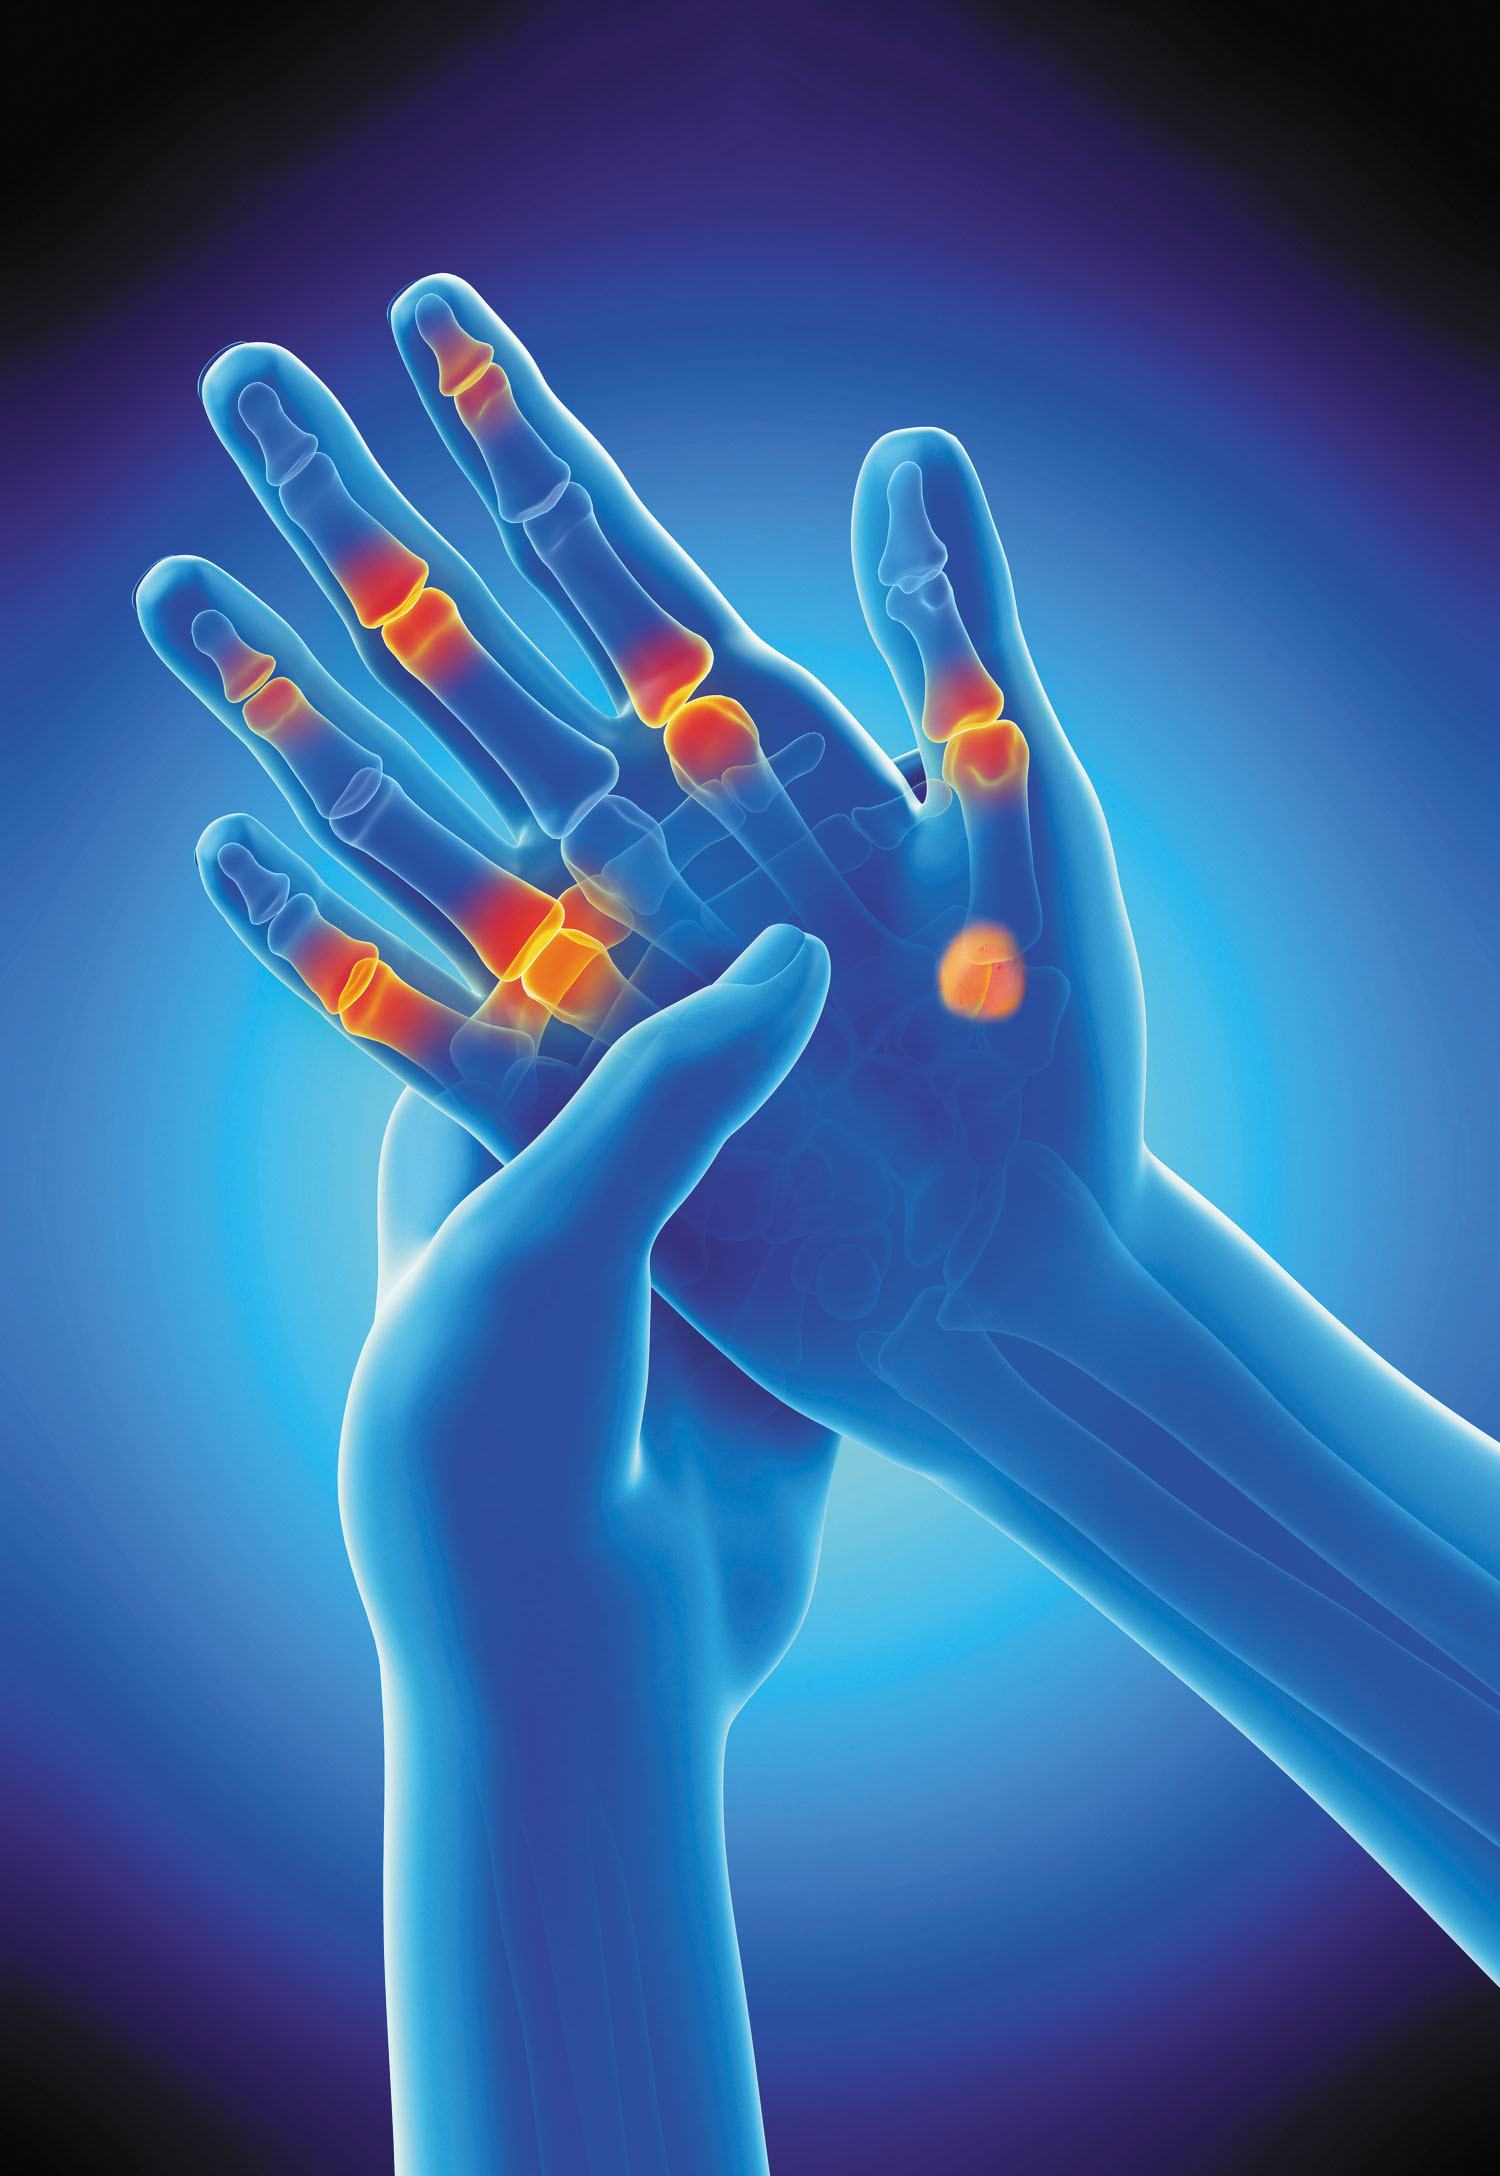
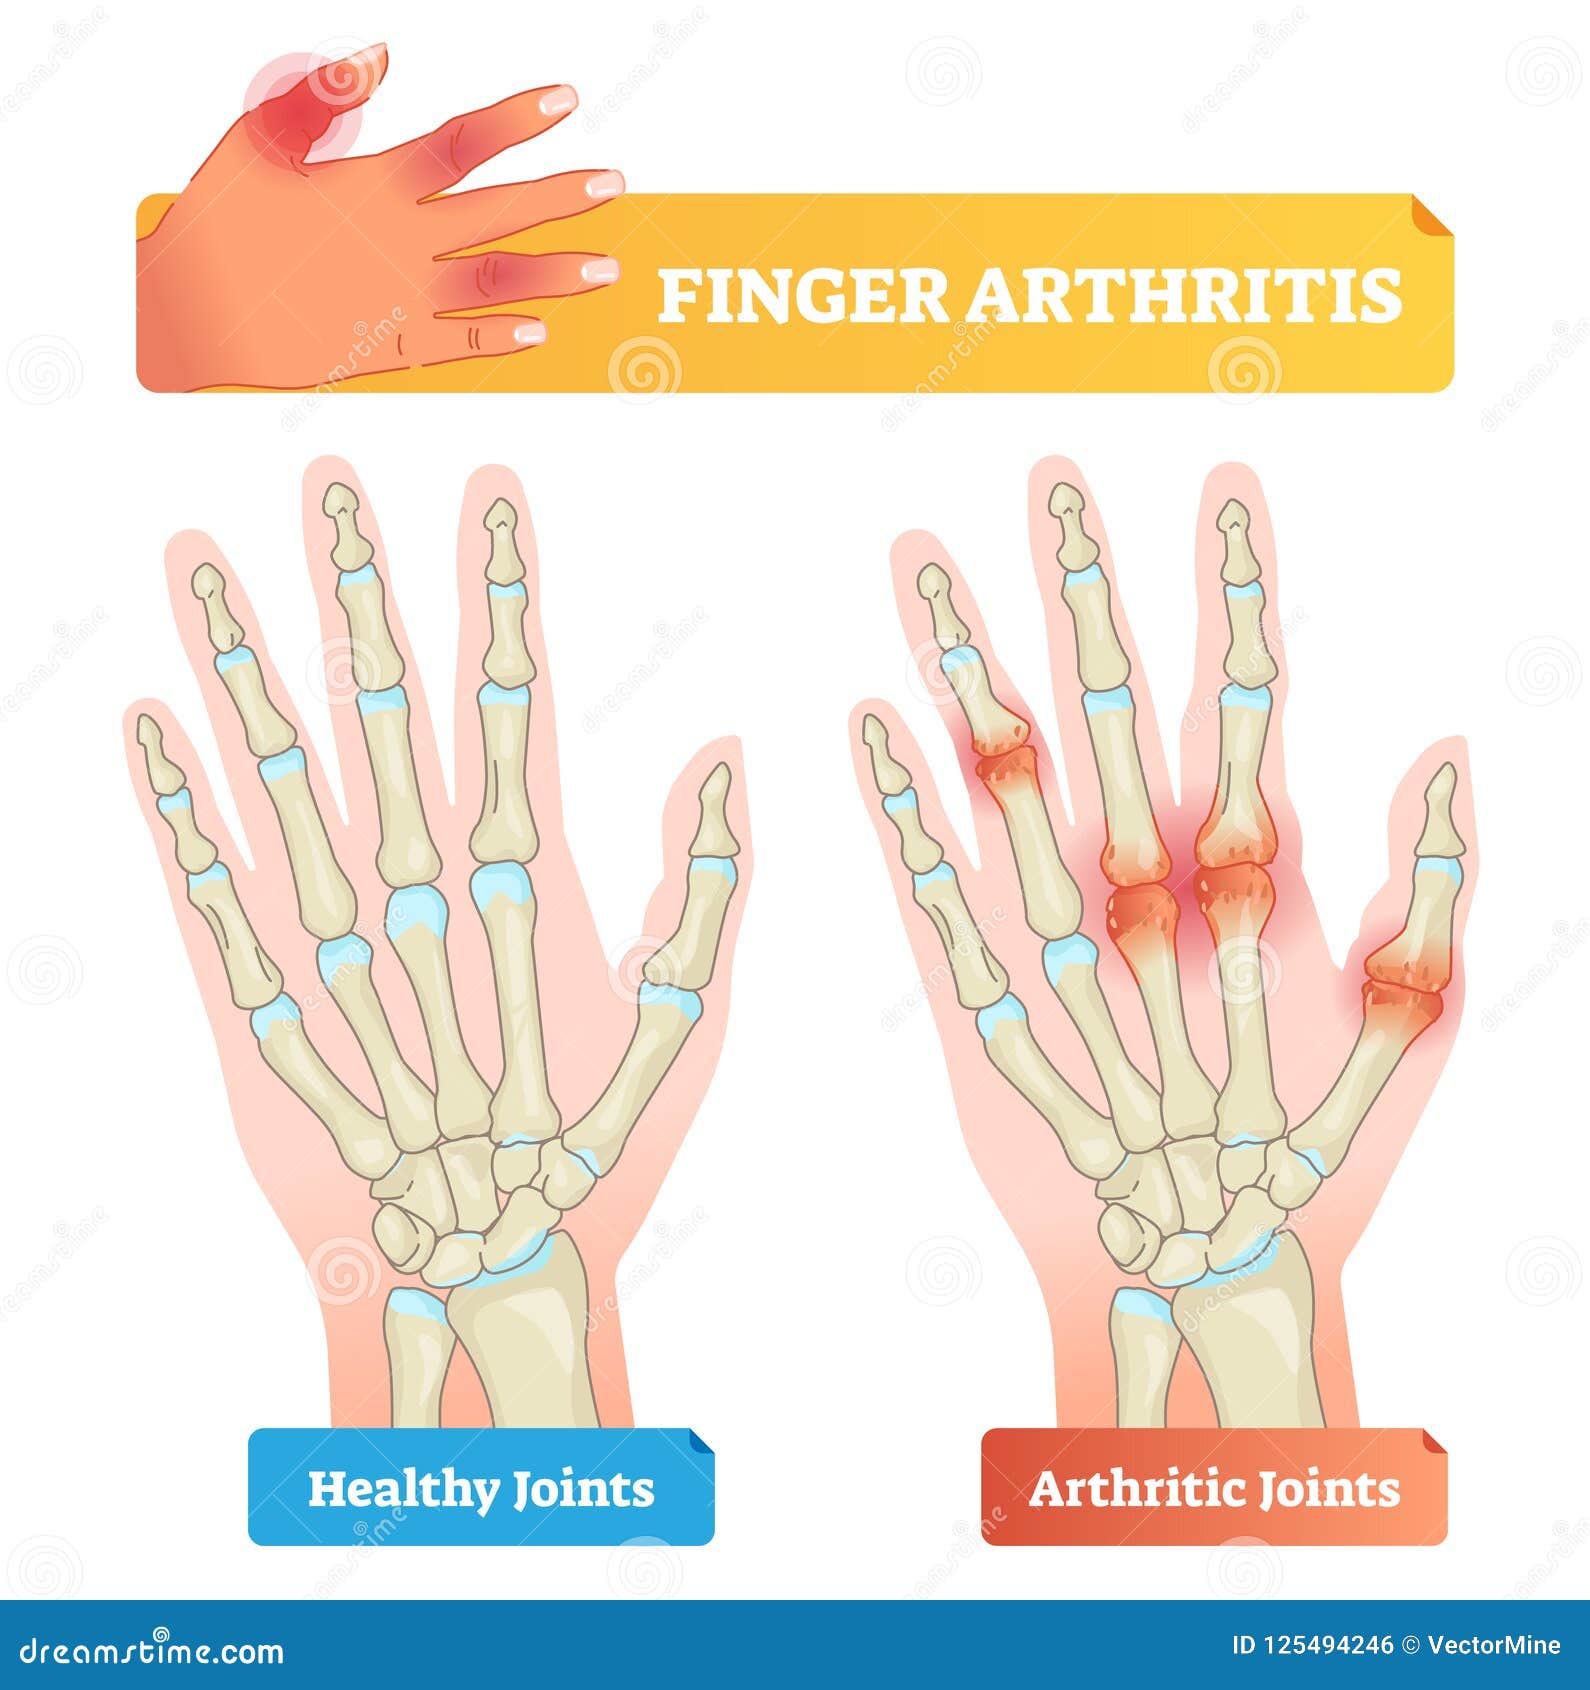
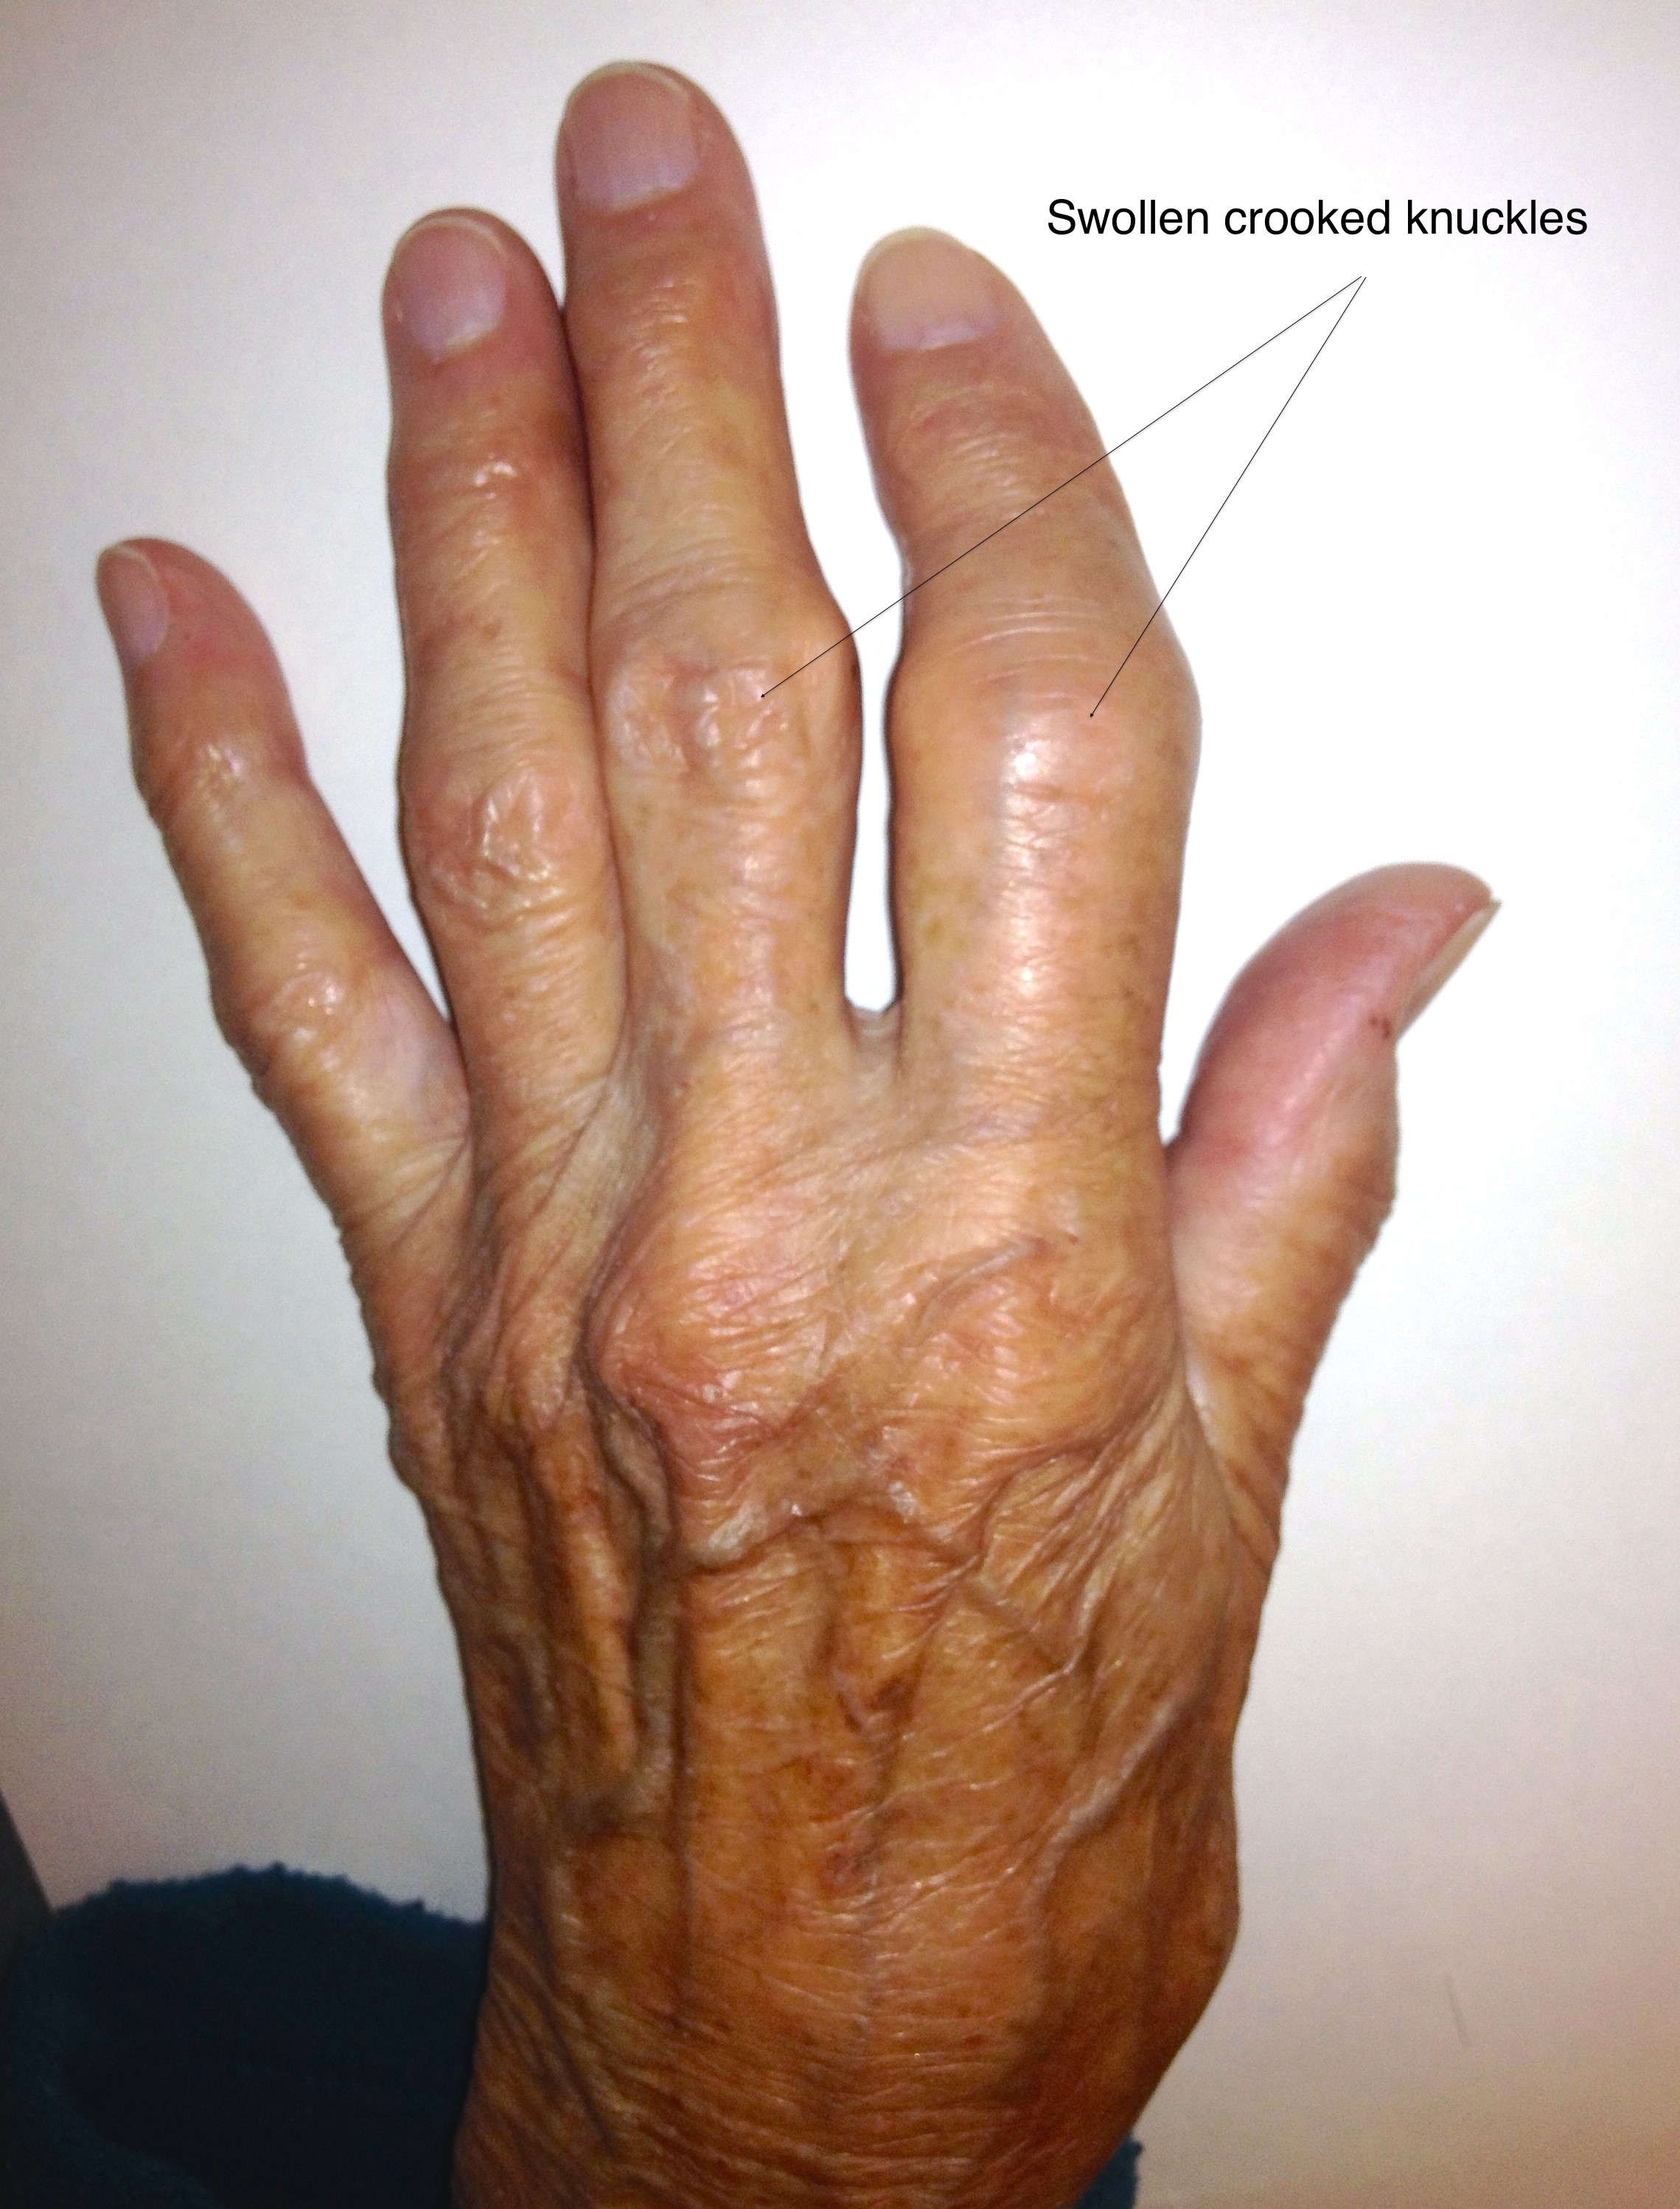
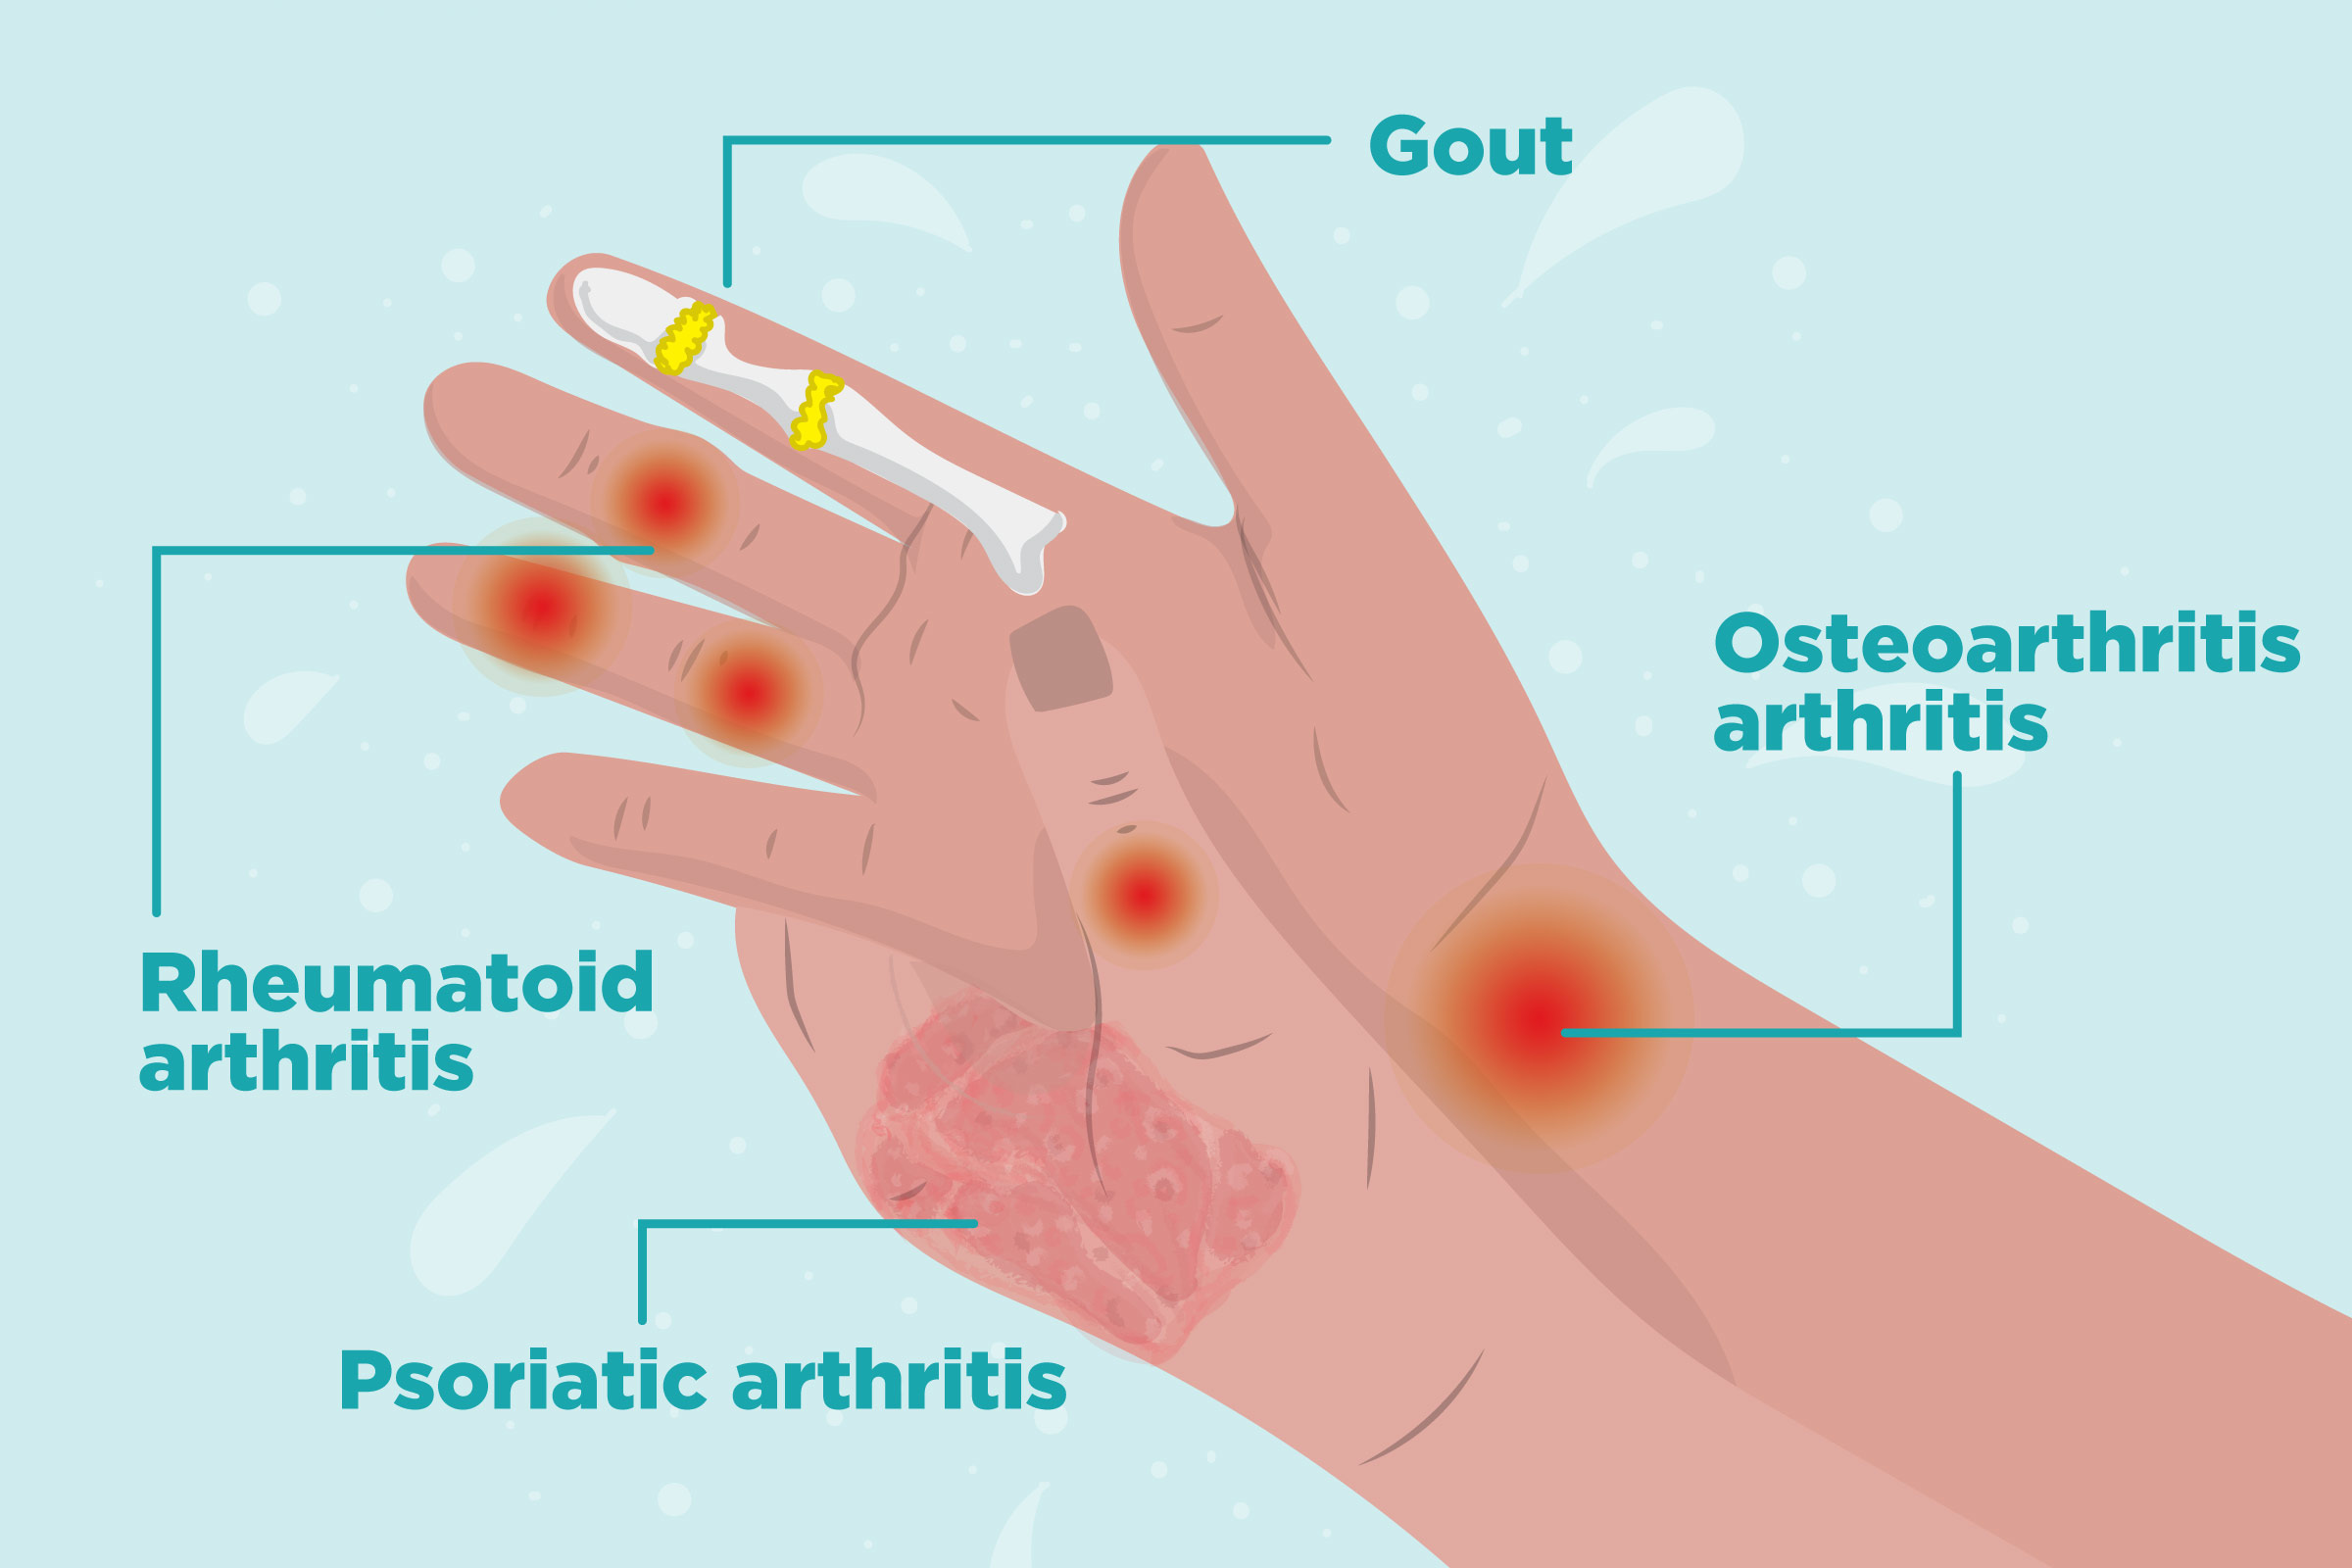
Most people don't realize how much arthritis changes the mechanics of everyday tasks until they're standing in the kitchen trying to open a jar and their fingers just won't bend right. It's not just pain. It's the loss of function. I've spent years watching patients try to push through activities instead of adapting, and it only makes the stiffness worse over time. The first thing to understand is that hand arthritis typically falls into two camps. Osteoarthritis shows up as bony enlargements at the base of the thumb or the fingertips, creating nodes that limit range of motion. Inflammatory types like rheumatoid arthritis cause symmetrical swelling, morning stiffness lasting over an hour, and systemic symptoms that no grip aid will fix. Getting the right diagnosis matters because the management strategies diverge completely after that point.
What You Actually Need to Know About Arthritis Of Hands And Fingers
I see the same mistake repeatedly. People buy silicone ring grips and ergonomic utensils on impulse without thinking through which joints are actually affected. A thickened grip helps if your issue is pinch strength at the thumb CMC joint. It does absolutely nothing for you if your problem is nodal OA at the distal interphalangeal joints where the bone spurs physically block full extension. You need to map your own limitations first. Here is a practical workaround I found that most clinicians don't bother explaining. When opening containers, stop using your thumbs entirely. Instead, brace the lid against the heel of your palm and rotate your entire forearm. The thumb CMC joint takes a massive force load during twisting motions, and sparing it during high-resistance tasks buys you months of function. I learned this from a patient who couldn't open any packaging without escalating her pain to a four out of ten within ten minutes. After switching to palm-bracing, she could handle grocery bags again without medication beforehand. Heat before activity, ice after. That sequence sounds simple but almost nobody gets it right. Warm water soaks for ten to fifteen minutes before doing your exercises loosen the joint capsule enough to actually gain range of motion. If you stretch cold, you're just irritating inflamed tissue. Then ice for ten minutes after to keep the post-activity flare down. I recommend a simple gel pack you can slip into the fridge and grab without thinking about it. The ones that require freezing for hours are too much effort when your hands are already sore.
Topical NSAIDs like diclofenac gel are genuinely effective for hand OA and dramatically safer than oral versions for long-term use. The British Society for Rheumatology and the American College of Rheumatology both recommend them as first-line pharmacological treatment. The trick is applying enough. Most people dab a pea-sized amount on each knuckle and call it a day. You need a strip about the length of your finger per joint, rubbed in thoroughly until absorbed. The topical formulation doesn't penetrate deeply, so coverage matters more than quantity per joint. Splinting deserves more serious attention than it gets. A thumb spica splint worn only at night or during aggravating activities can reduce CMC joint degeneration progression by limiting abnormal motion. The catch is compliance. They feel clunky and hot, and most patients stop wearing them after two weeks. I tell my patients to wear theirs for just one hour in the evening while watching television. That alone reduces next-morning stiffness significantly without making them feel disabled all day. Small consistent doses beat perfect theoretical usage every time. Exercises should focus on maintaining grip strength and independence, not on forcing painful ranges of motion. Squeezing a soft foam ball for thirty seconds repeated five times, three days a week, builds intrinsic hand muscle without grinding the joint surfaces. Finger extensions against a light rubber band work the opposing muscles that tend to atrophy. I've seen patients who only stretch and never strengthen end up with weaker joints that flared more often than before.
Get the Full Details
The counter-intuitive part that surprises most people is that rest alone does not help. Complete immobilization of arthritic hands causes the supporting soft tissues to stiffen and weaken. You need movement within a pain-free range. The goal is controlled motion, not rest, and not pushing through sharp pain. There is a middle ground that takes some experimentation to find. Joint protection techniques should be learned from an occupational therapist if at all possible. Proper body mechanics, leverage use, and activity modification can extend the time between flares by months. But if an OT visit isn't feasible, the core principles are straightforward. Use your palms and forearms instead of your fingers whenever possible. Push doors open with your body weight rather than your hand. Carry loads across both hands instead of gripping with one. Some supplements show modest evidence. Glucosamine and chondroitin have mixed results in trials, but a subset of patients report meaningful relief. Turmeric extract at standardized doses around 500 milligrams daily has anti-inflammatory properties that appear in several studies. Neither replaces medical treatment but neither causes significant harm for most people. Avoid anything making extraordinary claims. The supplement industry preys on chronic pain sufferers relentlessly.
When surgery becomes the conversation, metacarpophalangeal joint replacement or thumb CMC arthroplasty are the common options for end-stage disease. Recovery timelines are measured in months, not weeks. Pre-habilitation with strengthening and range of motion work before surgery produces measurably better outcomes. Patients who go into surgery with weak hand muscles and contracted joints recover slower and less completely than those who optimize function beforehand. The hardest adjustment is accepting that some days will be worse than others regardless of what you do. Weather changes, hormonal shifts, and stress all influence flares independently of your routine. Having a floor-level plan for bad days, where you do the absolute minimum to maintain function without triggering a prolonged flare, prevents the boom-and-bust cycle that exhausts your reserves and prolongs suffering. If your symptoms include prolonged morning stiffness beyond an hour, symmetrical joint involvement, or systemic features like fatigue and fever, you need a rheumatology referral promptly. Delaying treatment in inflammatory arthritis allows irreversible joint damage to accumulate. Early intervention changes the trajectory. For osteoarthritis, the timeline is more flexible but the principles of protection, strengthening, and adaptation remain the same.
Most over-the-counter aids are adequate for mild cases. A $15 adaptive key opener, a jar grip from a pharmacy, and a tube of diclofenac gel will handle the majority of daily frustrations. The investment skyrockets only when the disease progresses past what assistive devices can compensate for. Prevention at the mild stage is cheap. Managing advanced deformity is not. I keep a small tray of essentials by the couch: thumb splint, gel pack, diclofenac, foam ball, and a few heavy-grip utensils. Having them in one place means I'm not fumbling around when my hands are already stiff and frustrated. Friction compounds suffering, and reducing unnecessary steps during a flare matters more than people realize.