ASA Physical Status Classification
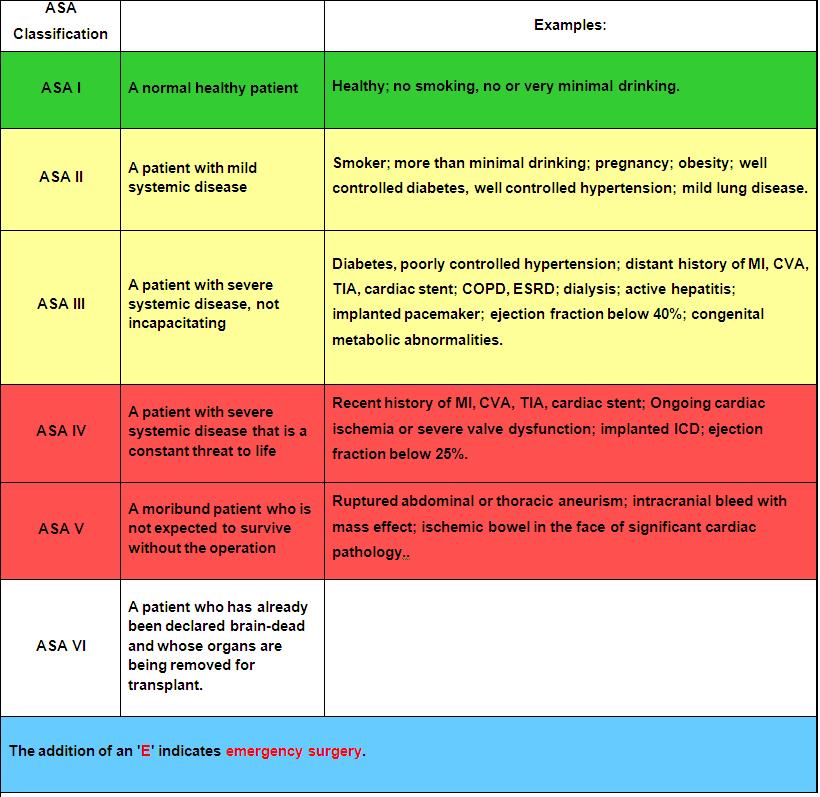
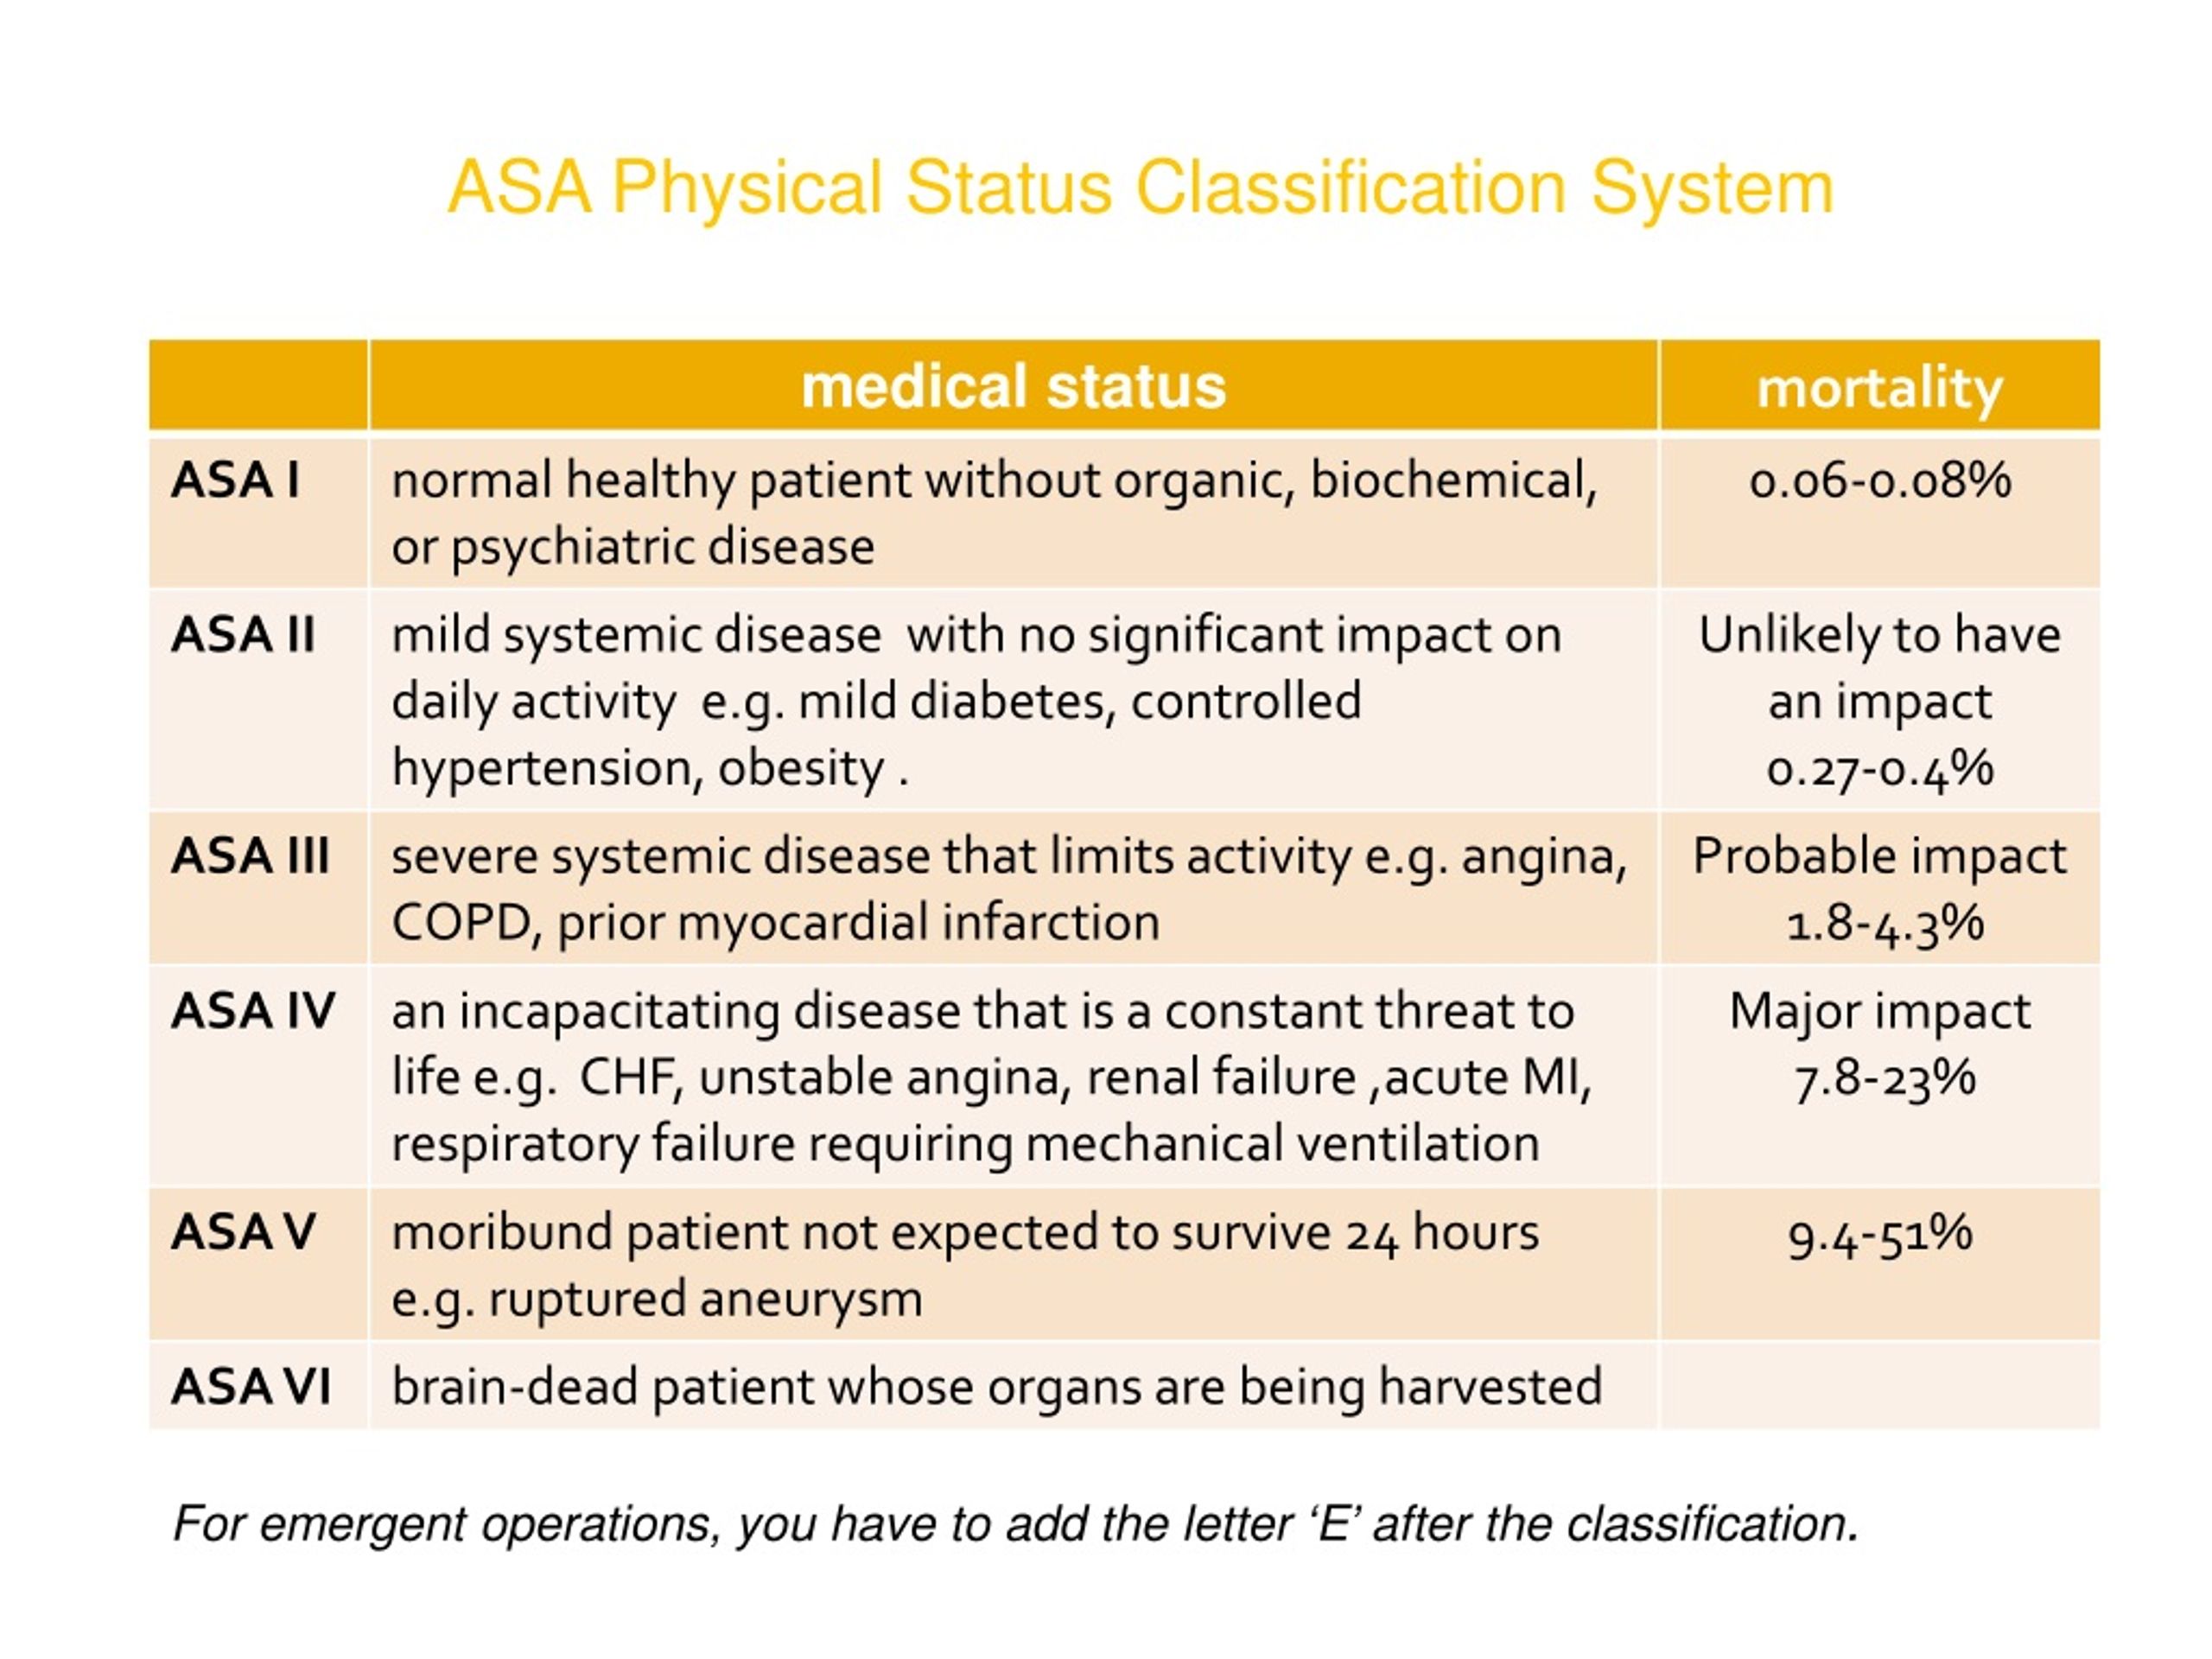
ASA Physical Status Classification is a system anesthesiologists use to score a patient's health before surgery. It runs from 1 to 6, with an optional E for emergency cases. That's really all there is to it. The American Society of Anesthesiologists created it back in 1941, updated it in 1963, and has revised it since then. Most people just look at it as a rough shorthand for communication, but it actually matters for risk stratification and insurance purposes. The scores are straightforward on paper: ASA 1 - A normal healthy patient. No medical issues. Someone who exercises regularly, doesn't smoke, no medications.
ASA 2 - A patient with mild systemic disease. Well-controlled hypertension, mild asthma, a current smoker, or pregnancy counts here. ASA 3 - A patient with severe systemic disease. This is where it gets murky. Diabetes with end-organ damage, COPD that limits activity, heart failure that's been stabilized with medication, morbid obesity. It doesn't mean the disease is untreatable, just that it's significant. ASA 4 - A patient with severe systemic disease that is a constant threat to life. Recent stroke, sepsis, advanced heart failure, end-stage renal disease not on dialysis, or acute coronary syndrome within the past 40 days.
ASA 5 - A moribund patient who is not expected to survive without the operation. Ruptured abdominal aneurysm, massive trauma, irreversible shock. ASA 6 - A declared brain-dead patient whose organs are being removed for donation. You add E for emergency, which roughly doubles the perioperative mortality risk. That modifier applies regardless of the base score.
Get the Full Details

Common Mistakes When Assigning ASA Physical Status Classification
I've seen this misclassified constantly in my years doing pre-op assessments. The biggest mistake is lumping all diabetics into ASA 3. If someone has type 2 diabetes on metformin with normal HbA1c and no complications, they're ASA 2. It's only when you have evidence of end-organ damage—retinopathy, nephropathy, neuropathy—that it becomes ASA 3. People assume the diagnosis itself bumps the score, and that's wrong. The classification is about physiological derangement, not just having a chronic condition. Another common error involves psychiatric conditions. Someone with well-controlled depression on SSRIs is ASA 1 or 2 depending on other factors. It only escalates if the psychiatric disease causes significant functional limitation. I had a case once where a patient with severe bipolar disorder who was non-compliant with medication and had recent hospitalizations was classified as ASA 2 by the referring clinic. When I saw them pre-op, they were actively psychotic and couldn't give informed consent. That's ASA 3 minimum, probably ASA 4 depending on how you view the instability. The referral paperwork didn't reflect any of that. Morbid obesity is another area where people rush. BMI over 40 alone doesn't automatically make someone ASA 3. It depends on whether the obesity causes significant functional impairment or comorbidities. A BMI of 45 with normal pulmonary function and no sleep apnea is still ASA 2. But add obstructive sleep apnea on CPAP, or cor pulmonale, and you're firmly in ASA 3 territory.
Where the System Falls Apart
The ASA score isn't a predictive tool. It was never designed to be one. It's a communication device. The original intent was to standardize how anesthesiologists describe their patients to each other. You'll hear it used for retrospective mortality studies, and it does correlate weakly with outcomes, but it's a blunt instrument. Two ASA 3 patients can have dramatically different operative risks depending on what that "severe systemic disease" actually is. I worked through a project where we tried to use ASA scores to benchmark surgical site infection rates across three hospitals. It fell apart immediately. ASA 3 meant something slightly different at each institution. One hospital was liberal with ASA 3 classifications and another was conservative. The data looked noisy until we stripped out the ASA variable entirely and switched to actual comorbidity indices. The Charlson Comorbidity Index gave us much tighter groupings for risk adjustment. The score also doesn't account for surgical risk. An ASA 2 patient undergoing major vascular surgery has a very different risk profile than an ASA 2 patient having a cataract extraction. ASA alone tells you nothing about the procedure. That's why you'll see it paired with the ACS NSQIP surgical risk calculator or the STS database for cardiac cases. Those tools incorporate ASA alongside operative variables and give you actual predicted complication rates.
Emergency designation is another gray area. The guidelines say "emergency" means the delay between decision and operation would increase the threat to life or body part. But that's subjective. A ruptured ectopic pregnancy is clearly emergency. Is a hip fracture in an 85-year-old emergency? The patient is stable. The surgery won't happen within hours. Yet most institutions code these as E because waiting 24 to 48 hours increases mortality. The guidelines don't really address this kind of boundary case, and different anesthesiologists interpret it differently. There's also the issue of pediatric classification. The ASA system was designed for adults. Kids with congenital conditions that would be ASA 3 in an adult might be different in a neonate because their baseline physiology is completely different. I've seen pediatric anesthesiologists struggle with this on cases involving complex congenital heart disease. The ASA score captures the severity but doesn't help you think through the actual anesthetic management.
What I Actually Do Before an Operation
I don't just look at the ASA score on the chart. I verify it against the actual clinical picture. I'll pull the most recent labs, check the echocardiogram if there's any cardiac history, review the pulmonary function tests. The score on the admission sheet might be wrong, and it's usually wrong because someone checked the box without thinking about it. Here's a specific situation that comes up more often than you'd expect. A patient comes in scheduled for a elective knee arthroscopy. Their ASA is listed as 2. They have hypertension controlled on lisinopril. On further review, I find they have Stage 3 chronic kidney disease with a creatinine clearance of 35. That changes things. The hypertension isn't just a number, it's end-organ damage. They should be ASA 3. Not a huge difference in scoring, but it matters for medication management. Lisinopril needs to be held. Fluid management changes. Post-op monitoring requirements shift. If I'd just accepted the ASA 2 on the chart, I would have missed that. I also look for things the score doesn't capture. Frailty is a big one. An ASA 2 patient who is frail has higher complication rates than an ASA 2 patient who isn't frail. The score doesn't measure it. I use the Clinical Frailty Scale alongside ASA when it matters. For orthopedic cases in elderly patients, frailty is often a stronger predictor of complications than the ASA score itself.
Functional capacity matters too. Can the patient climb a flight of stairs? If someone is ASA 3 with COPD but can climb two flights without stopping, their perioperative risk is lower than the score suggests. If someone is ASA 2 but can barely walk across a room, the opposite is true. Metabolic equivalents are useful here. Less than 4 METs indicates poor functional capacity and warrants closer cardiac evaluation before surgery.
How to Use This Properly
Assign the ASA score after the full pre-operative assessment, not before. I've seen residents assign ASA 2 at admission and then discover significant cardiac disease during workup, only to realize they'd already documented the wrong score in the chart. The score should reflect what you actually know, not what you assume at first glance. Document the rationale. Just writing "ASA 3" on a form doesn't help anyone. Add a brief note about why. "ASA 3 for Class III heart failure with LVEF 35% on lisinopril and furosemide." Now the next clinician understands the severity. It also protects you if someone questions the classification later. Reassess before induction. The ASA score is a snapshot, and patients change. A patient who was ASA 2 in the clinic can become ASA 4 on the table if they go into septic shock or have a myocardial infarction. The classification should be dynamic, not something you fill out and forget.

If you need a reference, the ASA website has the official guidelines. They're published in the journal Anesthesiology. The most recent update is from 2020, though the core classification hasn't changed substantially. For practical purposes, most of what you need is available in the ASA Quick Reference document, which is freely accessible online. It's a single page and covers the essentials without the bureaucratic language of the full guideline.