How ASHA Evidence Based Practice Actually Works in the Clinic
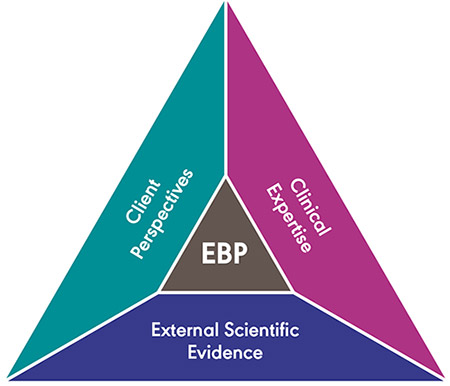
Most people treat it like a checkbox. They cite a single study from 2014 and call it a day. That is not what it means. The American Speech-Language-Hearing Association defined evidence-based practice around three pillars: best available research evidence, clinician expertise, and client/patient values and preferences. All three have to be present. Skip one and you are just doing opinions with citations.Understanding Asha Evidence Based Practice
Here is how I use it. Before I start any new intervention with a patient, I pull up recent systematic reviews on PubMed or search the ASHA Learning Center. I look for the strength of the evidence using their grading system. Then I ask myself whether that evidence actually applies to the person sitting in my chair. A study on stroke patients with aphasia tells me nothing about a five-year-old with developmental language disorder. So I filter. I remember working with a pediatric patient who had consistent evidence supporting a particular language intervention model, but the family refused it. They had tried other approaches and felt this was too rigid for their child's personality. I spent about two weeks finding alternative studies that supported a more play-based approach, then built a plan that hit the same treatment targets differently. The outcome was the same. The evidence still held. The family stayed engaged. One thing nobody tells you about implementing Asha Evidence Based Practice is that your own experience often outweighs the research in real time. You will see a technique fail repeatedly in your clinic even when the literature says it works. That does not mean the evidence is wrong. It means your population, your caseload pressure, your reimbursement structure, or your own skill level creates a bottleneck. I stopped fighting that reality about three years ago. Now I document when I deviate from the research and note why. It keeps me honest and it looks good during audits.
Getting the Resources You Actually Need
ASHA publishes multiple resources directly relevant to evidence-based practice. You can find practice guidelines, systematic reviews, and evidence maps on their website. The main ones I use regularly are the clinical practice guidelines available through ASHA ProFind and the peer-reviewed journals like the American Journal of Speech-Language Pathology. There is also the Journal of Communication Disorders and Language, Speech, and Hearing Research. Some of this requires membership or institutional access. If you do not have university library credentials, I would recommend using PubMed Central for free full-text articles and Google Scholar with the "since 2020" filter to keep things current. Older studies still get cited too often. A lot of them.
Common Mistakes I See Every Week
The biggest one is confusing a single randomized controlled trial with a complete evidence base. One study is a data point. It is not a foundation. I have seen clinicians build entire treatment plans on a paper that had a sample size of twelve and a funding conflict with the manufacturer of the device they recommended. Another mistake is ignoring the client component entirely. I watched a SLP team try to use a protocol that the research strongly supported for adult aphasia, but they did not consider that their patient was a bilingual Spanish-English speaker who worked a full-time job. The protocol assumed single-language monolingual therapy. It failed. Completely. We adjusted by integrating both languages and shifting session timing. The evidence still applied, just not in the way the original authors designed it. There is also the trap of over-relying on expert opinion disguised as evidence. Just because a well-known practitioner swears by a method does not make it evidence-based. ASHA's framework specifically calls that out. The hierarchy they use puts systematic reviews and meta-analyses at the top, single studies in the middle, case reports and expert opinion near the bottom. Knowing where your source sits in that hierarchy matters more than whether it sounds convincing.
Get the Full Details

Practical Steps I Follow
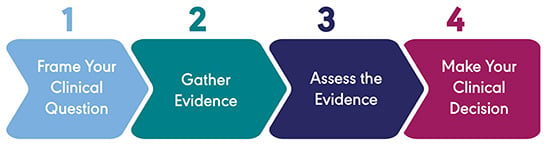
First, I define the clinical question using PICO format. Patient or population, Intervention, Comparison, Outcome. It sounds academic but it forces you to be specific. "Treat stuttering" is not a question. "Does fluency shaping improve oral reading fluency in adolescents with developmental stuttering compared to stuttering modification?" is a question I can actually research. Second, I search with a time limit. I give myself twenty minutes. If I cannot find at least one systematic review or a handful of relevant RCTs in that window, I stop and reconsider whether this is a situation where evidence simply does not exist yet. That is a real possibility, especially with rare disorders or emerging intervention techniques. In those cases, I document the gap and proceed with caution, monitoring outcomes closely. Third, I appraise the evidence using a standard tool. The CASP checklist works for qualitative studies. For quantitative research I use the Joanna Briggs Institute critical appraisal tools. These take about five minutes per article. Most clinicians skip this step entirely and just read the abstract. That is where things go wrong.
Fourth, I integrate. The research tells me what works. My experience tells me how to adapt it. The patient tells me what is acceptable and sustainable. All three inputs go into the plan. None of them gets veto power on their own.
What This Approach Cannot Do
Evidence-based practice does not replace clinical judgment. It does not handle situations where the patient's circumstances make the recommended intervention impossible. Insurance coverage, transportation, family dynamics, comorbid conditions, and cultural factors all matter and none of them appear in a research paper. I have had to abandon evidence-supported interventions because a family could not manage the homework requirements. That is not a failure of EBP. It is a limitation of it. If you need a more flexible framework for cases where research evidence is sparse or contradictory, I sometimes fall back on shared decision-making models combined with outcomes monitoring. You track the patient's progress with standardized measures regardless of which intervention you choose. If the numbers move, you keep going. If they do not, you switch. It is slower and it requires more data collection, but it keeps you from anchoring on a single study when the patient right in front of you is not responding. I still use ASHA's evidence-based practice framework as my starting point. It keeps me from making decisions that are purely intuitive. But I treat it as a scaffold, not a cage. The real work happens in the space between the research and the person sitting across from you.