How to Understand Aspirin's Drug Classification
I spent years working in pharmacy before moving into clinical pharmacology, and one of the most common questions patients ask is whether aspirin counts as an NSAID or something else entirely. The answer depends on who you're talking to, which is annoying but honestly accurate.What Is Aspirin Class Of Drug?
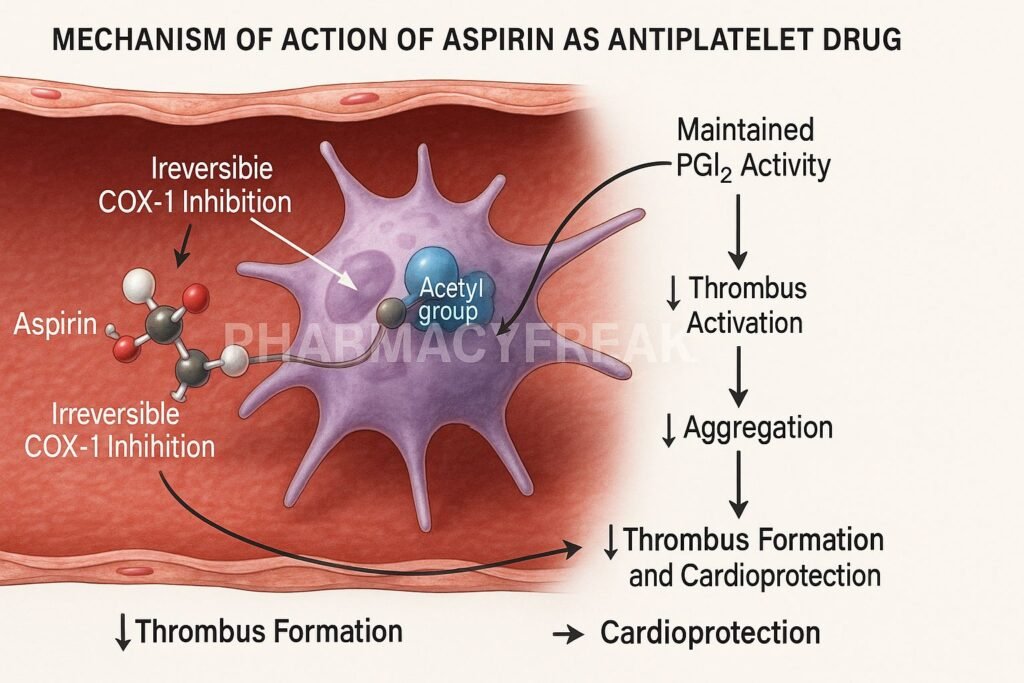
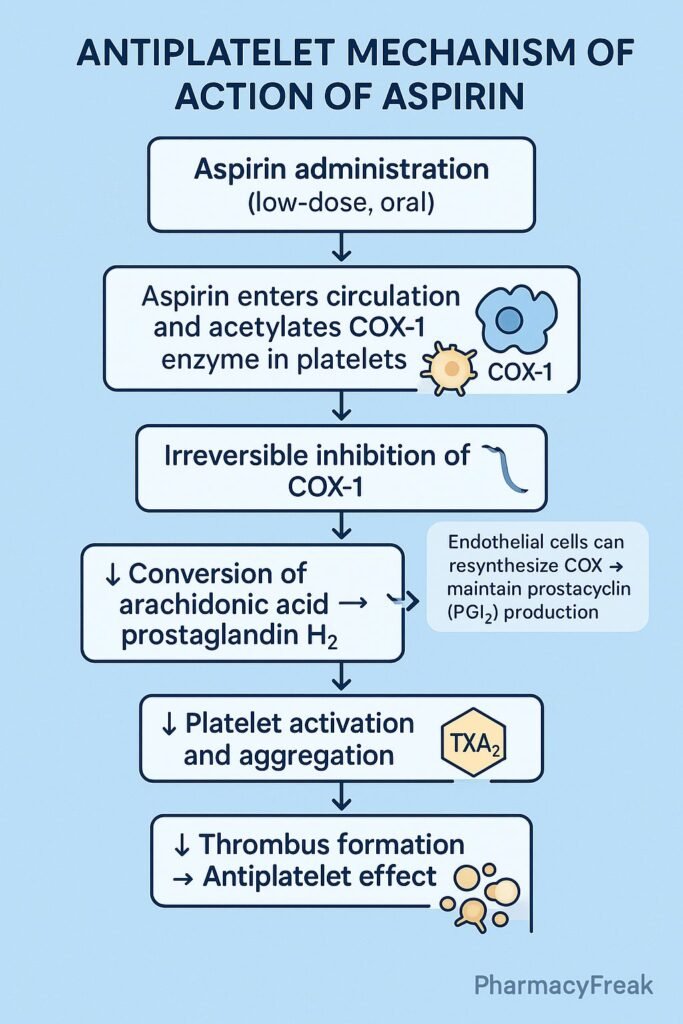
Aspirin belongs to the salicylate family, which makes it technically an NSAID, but its mechanism does enough things differently that some references classify it separately. It irreversibly inhibits cyclooxygenase enzymes COX-1 and COX-2 by acetylating a serine residue in the active site. Most other NSAIDs do reversible binding instead, which matters when you're dealing with platelet aggregation over a patient's entire platelet lifespan.For pain relief, aspirin is considered a mild analgesic antipyretic at doses around 325 to 650 milligrams. The antiplatelet effect kicks in at much lower doses, usually 81 milligrams daily for cardiovascular protection. I've seen people confuse these two uses and accidentally double up on dosing when switching from prescription cardiology protocols to OTC pain management, which can cause GI bleeding without any warning signs in elderly patients. Here's something most beginner pharmacology resources don't emphasize: aspirin's salicylate metabolite gets excreted renally, and at high doses the urine pH determines how much reabsorption happens. Alkalinizing the urine with sodium bicarbonate is actually the standard treatment for acute aspirin overdose because it traps the drug in the renal tubules. I learned this the hard way when a colleague nearly missed the connection during an emergency rotation back in residency.
Practical Classification Issues
Drug reference databases vary on how they categorize aspirin. Some list it purely under NSAIDs, others create a separate salicylate category, and a few flag it as an antiplatelet agent first and foremost. The confusion isn't accidental, it reflects the real pharmacological ambiguity.When I'm documenting medication lists for patients, I categorize aspirin as a salicylate NSAID with antiplatelet properties. This avoids the mistake of assuming it has the same renal risk profile as ibuprofen or naproxen at equivalent anti-inflammatory doses. Aspirin at cardioprotective doses carries minimal renal risk compared to traditional NSAIDs, but the bleeding risk remains proportionally higher because of that irreversible platelet inhibition. I ran into a problem last year managing a patient on low-dose aspirin who needed dental surgery. The standard protocol before 2016 was to stop aspirin five to seven days pre-procedure, but newer cardiovascular guidelines changed that recommendation significantly. Stopping aspirin in patients with recent coronary stents can trigger stent thrombosis, which has mortality rates around 20 to 45 percent depending on timing. I had to coordinate between cardiology and oral surgery to determine that the bleeding risk from a simple extraction was acceptable compared to the cardiac risk of cessation.
Common Pitfalls
Reye's syndrome is the most dangerous pediatric concern, affecting children under 19 who develop viral infections and take aspirin. It causes acute encephalopathy and liver failure with roughly 25 percent mortality. This is why pediatricians strictly avoid aspirin for fevers in that age group, preferring acetaminophen or ibuprofen instead.Another issue involves drug interactions that patients don't report. Warfarin plus aspirin increases major bleeding risk substantially, yet people often continue OTC aspirin while on anticoagulants without telling their prescriber. I've reviewed charts where patients were on both therapies for years without anyone recognizing the interaction because the aspirin wasn't on the prescription list. Aspirin also interferes with losartan's uricosuric effect, which matters for gout patients. The mechanism involves competition for renal organic anion transporters. Most clinicians miss this interaction because it doesn't show up in basic drug interaction checkers, but it's well documented in nephrology literature.
Get the Full Details

What Works in Practice
When classifying aspirin for clinical documentation, use the full descriptor: salicylate NSAID with irreversible antiplatelet activity. This captures both its anti-inflammatory classification and its unique pharmacological behavior. Single-word categories fail because aspirin genuinely sits at the intersection of three drug classes.For patients asking whether they should continue aspirin during illness, the answer depends on indication. Secondary cardiovascular prevention generally warrants continuation even with minor infections, unless there's active bleeding or severe dehydration. Primary prevention decisions require more nuance and should be individualized based on cardiovascular risk scores rather than blanket recommendations. The dosage distinction matters practically too. Enteric-coated 81 milligram tablets behave differently than regular 325 milligram tablets regarding absorption timing and GI irritation, even though the active ingredient is identical. I've seen patients switch formulations and experience different side effect profiles without understanding why, which usually traces back to the coating material and dissolution characteristics rather than the aspirin itself. If you need to look up aspirin classification in pharmaceutical databases, search under salicylates first, then NSAIDs as a secondary category. Some systems like Lexicomp and Micromedex have crossed-references that point you to both classifications, but you need to know to follow both paths or you'll miss relevant interaction data filed under only one heading.