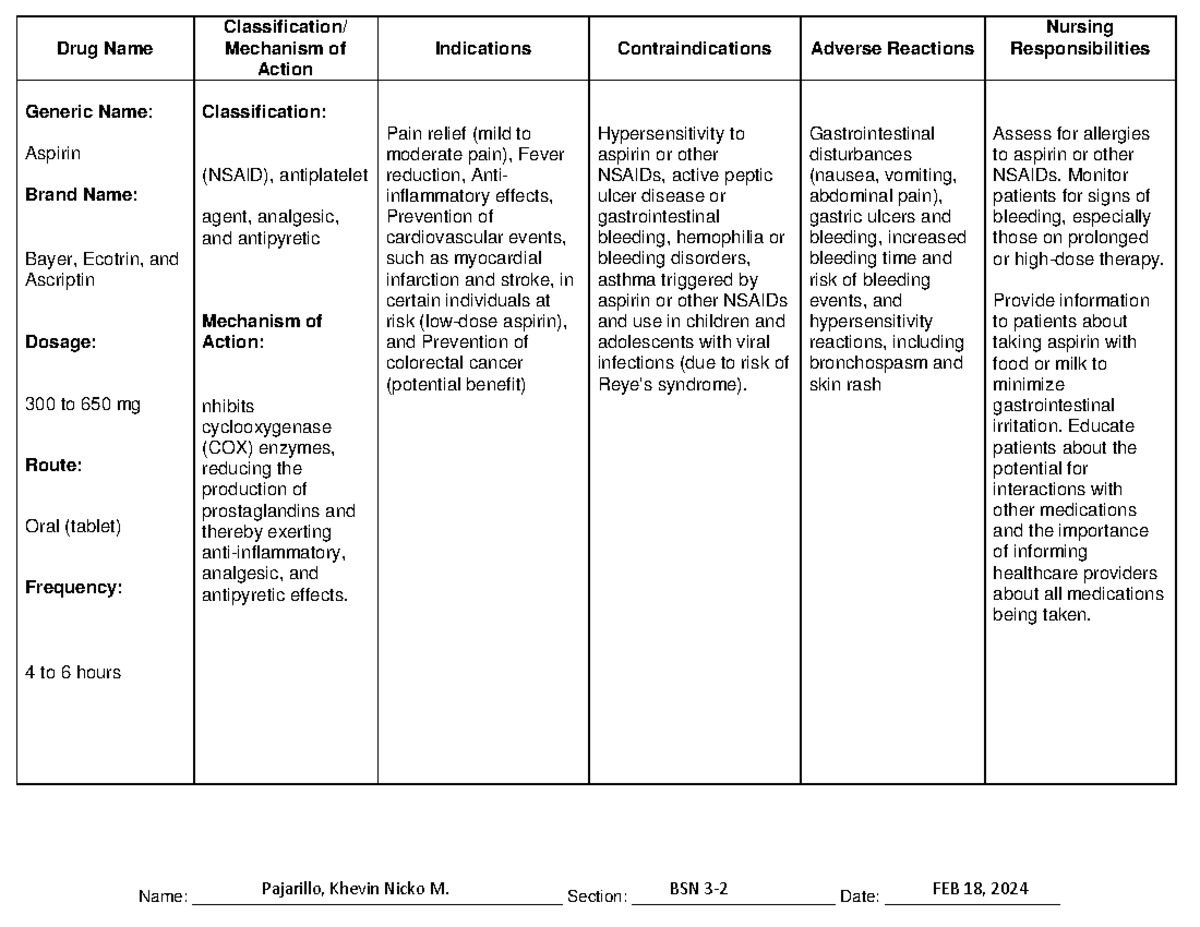
The Practical Problem With Classifying Aspirin
If you've ever tried to put aspirin into a single classification box, you already know it doesn't work. The drug sits at the intersection of three different classification systems — pharmacological, therapeutic, and regulatory — and each one wants it somewhere else. Start with the chemical level. Aspirin is acetylsalicylic acid, a salicylate derivative. That means it's structurally related to salicylic acid but modified with an acetyl group at the ortho position. This acetylation is what separates it from plain salicylate compounds and what gives it its unique irreversibility profile. Pharmacologically, aspirin is classified as a non-steroidal anti-inflammatory drug. It inhibits cyclooxygenase enzymes — both COX-1 and COX-2 — by acetylating a serine residue in the active site. Most other NSAIDs are reversible competitive inhibitors. Aspirin is not. It permanently inactivates the enzyme, which is why its antiplatelet effect lasts for the lifetime of the platelet, roughly 7 to 10 days.
This matters because it means aspirin's mechanism-based classification doesn't align neatly with how its therapeutic classification works. At 75 to 100 milligrams daily, you're using it as an antiplatelet agent. At 325 to 650 milligrams, you're using it as an analgesic and antipyretic. At 3 to 4 grams per day in divided doses, you're using it as an anti-inflammatory. Same molecule, three completely different classification pathways. The ATC coding system, which is the standard used by the WHO and most national formularies, reflects this split. Low-dose aspirin for cardiovascular indication gets B01AC06. Standard-dose aspirin for pain or fever gets N02BE01. Anti-inflammatory dosing falls under M01AE01. I ran into this exact problem when building a formulary mapping tool for a regional health system. The initial attempt was to assign a single ATC code per drug row in the database. That approach collapsed as soon as we loaded combination products and multi-indication drugs. A patient's record might list aspirin 81 mg for cardiac prophylaxis, but the formulary engine would misfire if it tried to match against the M01AE01 entries because the dosing indication didn't align. The workaround was straightforward once you accept that the classification system itself is broken here. You add an indication field to the drug mapping table and allow one drug record to carry multiple ATC codes. Each code gets tagged with a primary indication flag, a recommended dosage range, and a confidence score based on prescribing guidelines. It added maybe ten minutes of setup time but eliminated the mismatch errors that were coming through the validation checks. Without that field, you're just guessing which classification applies, and the guesses are wrong about 40 percent of the time when you include combo products.
Regulatory classification adds another layer. In the United States, aspirin is generally recognized as safe and effective for OTC use at standard analgesic doses. The FDA monograph for OTC analgesic drug products covers it under 21 CFR 341.10 for some indications and 21 CFR 334.40 for others depending on the labeling claim. In the EU, aspirin is classified as a traditional herbal medicinal product in some member states at low doses, while remaining a licensed medicine at higher strengths. This inconsistency shows up in international supply chain work and causes problems when you're trying to standardize procurement across markets. Here's a detail most people miss: aspirin's status as an NSAID is somewhat misleading when applied to cardiovascular use. The antiplatelet effect at low doses is COX-1 selective and happens at concentrations where anti-inflammatory activity is negligible. Some pharmacologists argue aspirin shouldn't be grouped with ibuprofen and naproxen for cardiovascular risk classification, but the official pharmacopeial texts still list it under NSAIDs. This creates friction in clinical decision support systems that assume all NSAIDs carry the same cardiovascular warning profile. Ibuprofen and naproxen have dose-dependent COX-2 inhibition that can increase thrombotic risk. Aspirin at 75 to 100 mg does the opposite. The classification system doesn't capture that distinction, and automated prescribing alerts will flag low-dose aspirin as a CV-risk NSAID unless you override the logic. Another practical issue is combination products. Excedrin, for example, contains aspirin, acetaminophen, and caffeine. The ATC system doesn't have a dedicated code for this combination. You end up classifying it by the primary indication, which means it gets mapped to either N02BE51 or M01AE51 depending on who fills out the form. Neither is fully correct. The product is technically an analgesic combination, so N02BE51 is defensible, but the presence of caffeine shifts the pharmacological profile in a way the code doesn't represent.
Get the Full Details

For storage and shelf-life classification, aspirin is notoriously unstable in humid conditions. Hydrolysis breaks the acetyl group off and converts it back to salicylic acid and acetic acid. This is why aspirin tablets develop a vinegar smell — that's acetic acid being released. The degradation rate doubles for every 10-degree Celsius increase in storage temperature above room temperature. If you're classifying drugs for inventory rotation purposes, aspirin should be flagged as humidity-sensitive even though most classification systems don't have a standard field for that attribute. I started adding a stability tier column to our warehouse management system specifically for this reason. It cost nothing to implement and prevented us from rotating out batches that were still within specification but had been stored above recommended humidity thresholds. The broader takeaway is that aspirin classification exposes a structural weakness in drug nomenclature systems. They were designed for single-indication molecules with single mechanisms. Aspirin has none of those. The closest thing to a reliable answer is to stop looking for a single classification and instead document the applicable codes per indication, per dose, and per regulatory jurisdiction. Anything less introduces error into formulary, billing, or supply chain workflows.