Nursing Legal Liability: Telling Assault From Battery on the Floor
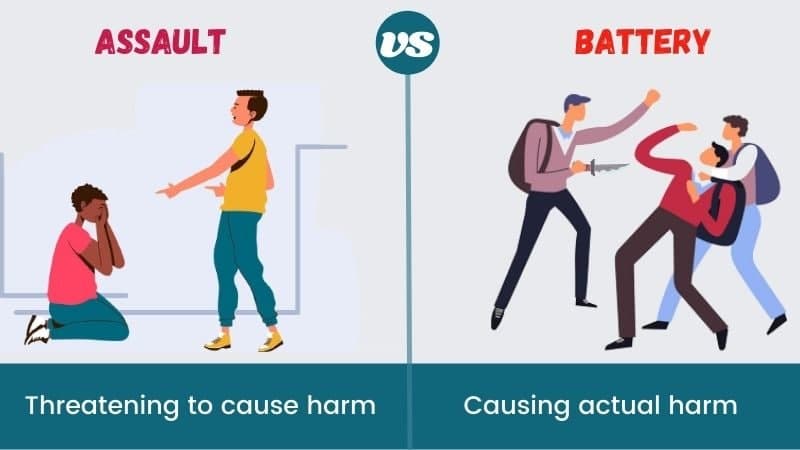
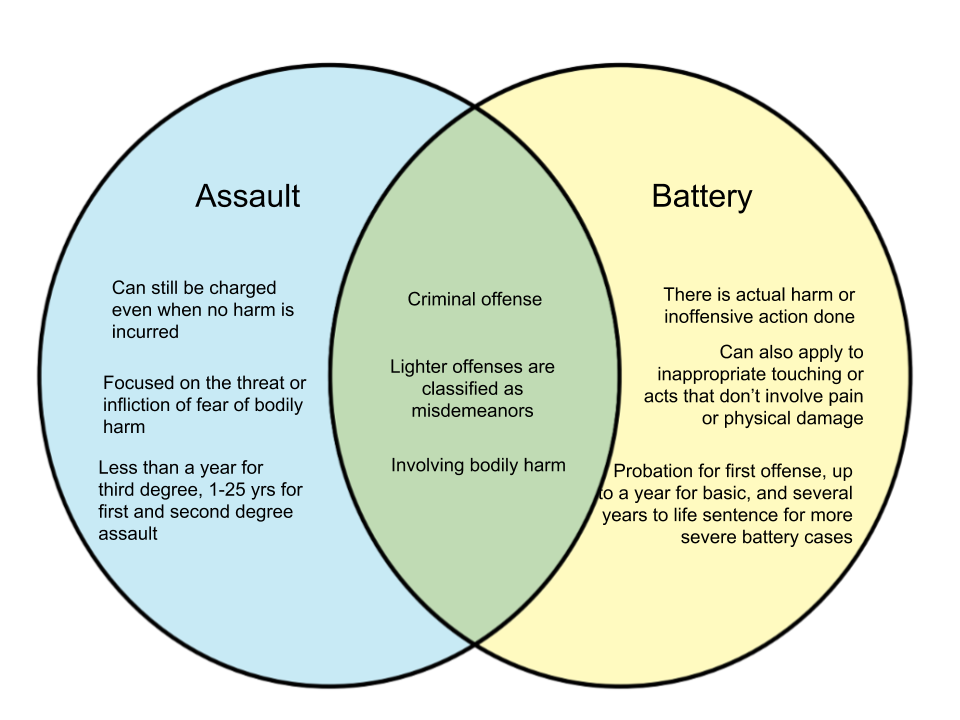
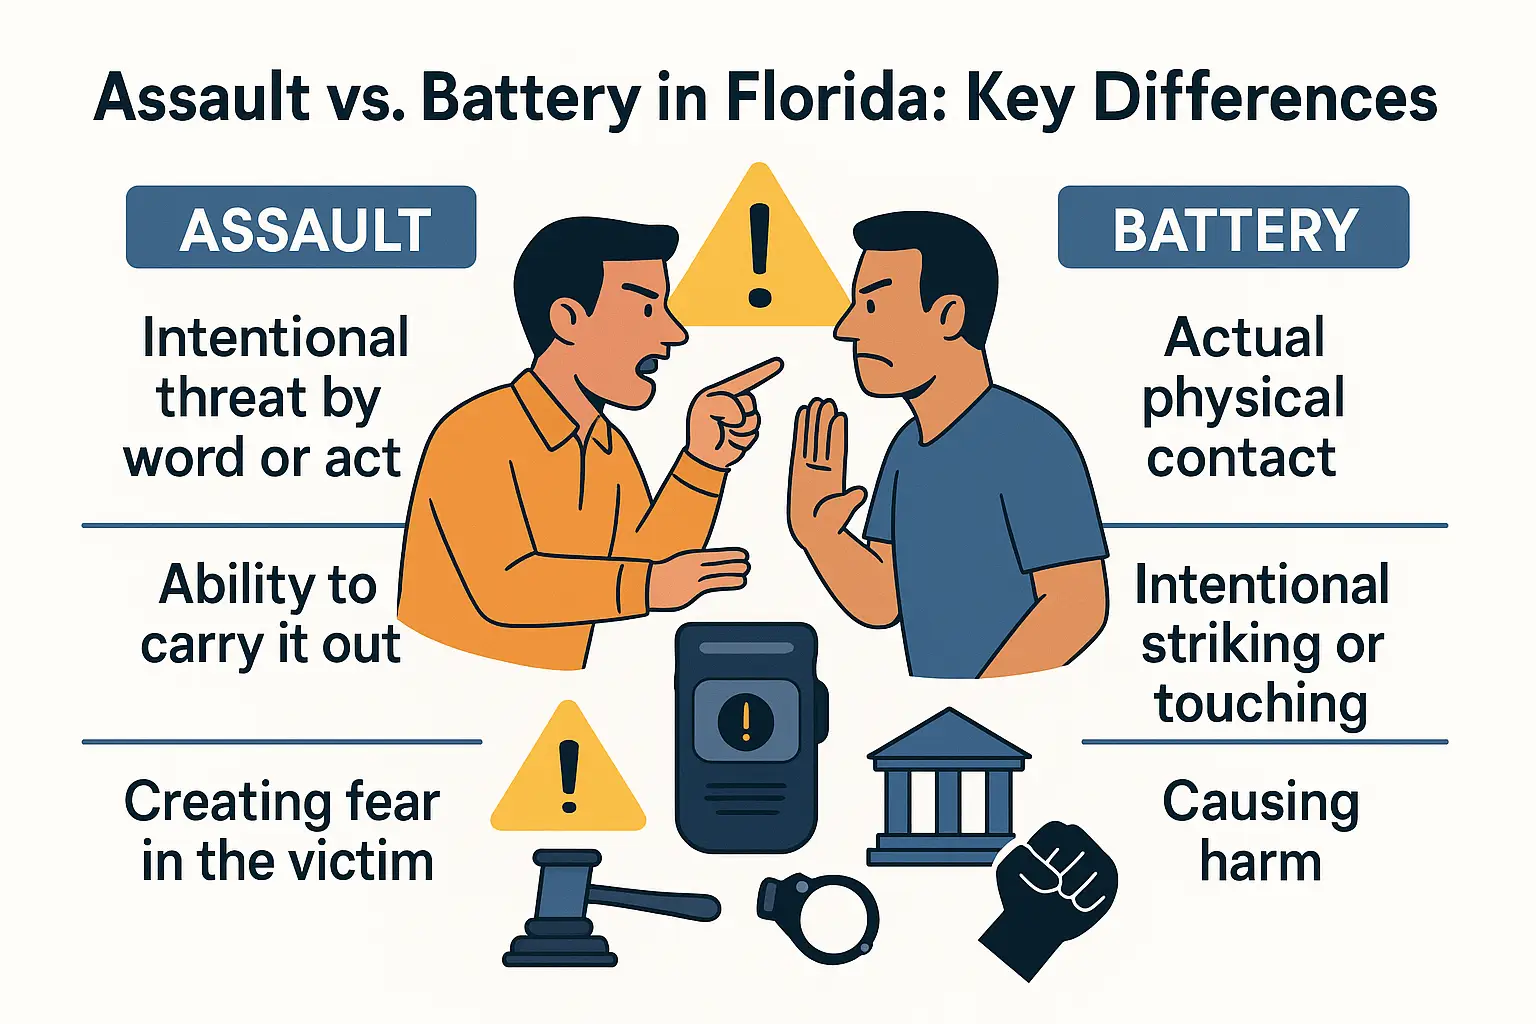
Most nursing students mix up assault and battery because the legal definitions don't match how people use those words in everyday conversation. In a legal context, and especially in nursing malpractice cases, the distinction matters for your license review and any civil suit. Here is how it actually breaks down. Assault in nursing law is the intentional act that causes a patient to reasonably fear imminent harmful or offensive contact. No physical touch required. Threatening to restrain a patient without following your facility's protocol, raising a hand near them while you have a tone of voice that signals force, or picking up a syringe and saying you're going to give them a shot when they have not consented and there is no medical indication — these can all qualify as assault if a reasonable person in the patient's position would fear immediate harm. Battery is the actual unwanted physical contact performed intentionally. Administering medication after the patient clearly withdrew consent, performing a procedure outside your scope of practice, or touching a patient's body in a way that serves no clinical purpose crosses into battery territory. The contact does not need to cause injury. A single unwarranted injection is sufficient for a battery claim.
The Core Legal Elements You Need to Memorize
Both torts share a few baseline elements but diverge on the contact requirement. For assault you need: intent, reasonable apprehension of harm, and imminence. The patient must actually perceive the threat. If a nurse makes a noise behind a patient who is asleep and unaware, there is no assault because there was no apprehension. Intent means the nurse acted deliberately, not accidentally. A stumble that bumps into a patient is negligence at worst, not assault. For battery you need: intent to make contact, the contact itself, and lack of consent. The contact must be offensive or harmful under a reasonable person standard. Consensual care, such as inserting an IV after proper explanation and agreement, is never battery. Withdrawing consent mid-procedure and the nurse continuing anyway converts the act into battery from that moment forward.
How This Plays Out in Real Practice
I dealt with a situation last year where a patient with early dementia kept pulling at a peripheral IV line. The nurse used a soft wrist restraint without a physician order and without a full restraint evaluation. When the patient became agitated and tried to remove the device again, the nurse moved toward the patient with the restraint in hand. The patient retreated against the bed rail, clearly frightened. The charge was both assault and battery. The restrained motion with the device present constituted assault because the patient had reasonable apprehension of imminent harmful contact. The subsequent application of the restraint without an order was the battery. The facility settled the civil claim separately from the board action. The nurse received a reprimand and mandatory legal education, but the case stayed on record for three years.
Get the Full Details
Common Pitfalls That Beginners Miss
The first trap is assuming that clinical justification erases the tort. It does not. A valid medical reason might protect you in a negligence analysis, but it does not automatically negate assault or battery if the patient lacked capacity to consent and no surrogate provided it. Consent is the dividing line, not clinical necessity. The second trap is assuming that gentle touch cannot be battery. A patient with cognitive impairment may appear compliant, but if they lack decision-making capacity and no authorized surrogate is available, any non-emergent physical contact is technically battery. Capacity assessments are not optional here. Document the capacity evaluation or the source of surrogate consent.
A Practical Workaround for High-Risk Situations
When a patient is agitated and you need to administer time-sensitive treatment, use the two-witness documented refusal and emergency protocol instead of forcing the issue. I started requiring two licensed witnesses to observe the patient's capacity assessment and refusal, then escalated to the attending and ethics consult when there was a conflict. This usually adds about twelve minutes to the process but eliminates the liability gap entirely. For emergent situations where delaying treatment poses an immediate threat to life or limb, the emergency exception applies, but you still need to document the nature of the emergency and the specific interventions performed. Your chart is your primary defense. Record the patient's stated consent or refusal in their own words. Note the time, the specific procedure, the information provided to the patient about risks and benefits, and the patient's response. If you use a restraint, document the order number, the assessment findings, the type of restraint, monitoring intervals, and the eventual discontinuation. Vague notes like "patient cooperative" are worthless in a legal proceeding. Write what actually happened. Civil liability is not the only risk. Many states treat battery by a healthcare provider as a misdemeanor or felony depending on the severity and whether there was intent beyond the scope of practice. Assault can also carry criminal penalties when it involves a threat with a medical device. Your state board will typically receive notification from law enforcement or the hospital's risk management office. The criminal case and the board proceeding run independently, so a dismissal in one does not guarantee the other will drop.
This framework does not handle every edge case cleanly. Consent issues involving minors, guardianship disputes, and advance directive conflicts often fall into gray areas that require legal counsel rather than a simple checklist. The emergency exception is frequently litigated because the boundary between emergent and non-emergent is not always clear at the point of care. When in doubt, pause and get a consult rather than proceeding under an assumption. The practical takeaway is that assault and battery in nursing are consent and intent cases, not injury cases. A single unwitnessed moment without proper authorization is enough for both a board complaint and a civil suit. Your documentation practices and your willingness to involve the care team before escalating physically are the things that actually protect you.
Resources and Further Reading
The American Nurses Association publishes ethics and legal guidelines that map directly onto these concepts. Your state's board of nursing website will have the specific statutes and administrative codes relevant to your jurisdiction. Hospital risk management departments usually maintain local policies on restraint use and consent procedures that exceed the minimum legal requirements. I found the state-specific nursing practice act particularly useful during the scenario I described earlier, since it defined exactly what constituted permissible emergency intervention in my region.