The Practical Guide to Cranial Nerve Assessment for Nurses
Cranial nerve assessment is one of those skills nursing students learn in sim labs and then abandon until a code or a neurological admission forces them to remember it. The twelve nerves sound impressive on paper. In practice, you are really checking four functional systems: vision, eye movement, facial sensation and expression, and swallowing. Everything else is detail work. The trick is not memorizing the full mnemonics but building a consistent pattern that takes about six to eight minutes on a cooperative patient and fifteen to twenty minutes when you are also managing IV lines, monitors, and an anxious family in the room. I have watched nurses skip CN VIII entirely on med-surg floors because they do not have a tuning fork. I have also watched junior residents waste ten minutes trying to elicit a gag reflex in a patient who just had a stroke and has a depressed bulbocavernosus reflex anyway. Both are common failures. Neither has to happen if you approach the exam with the right sequence and a clear idea of what each nerve is actually telling you.
What Assessing Cranial Nerves Nursing Actually Looks Like at the Bedside
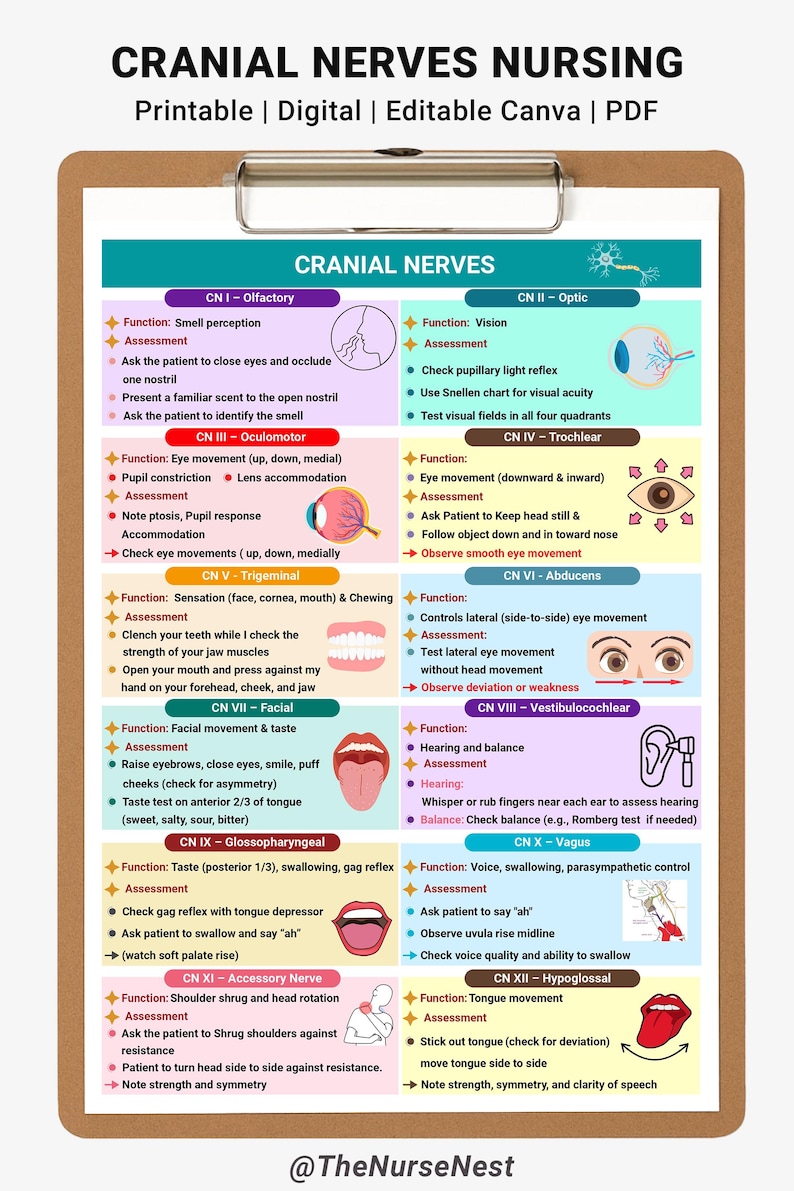
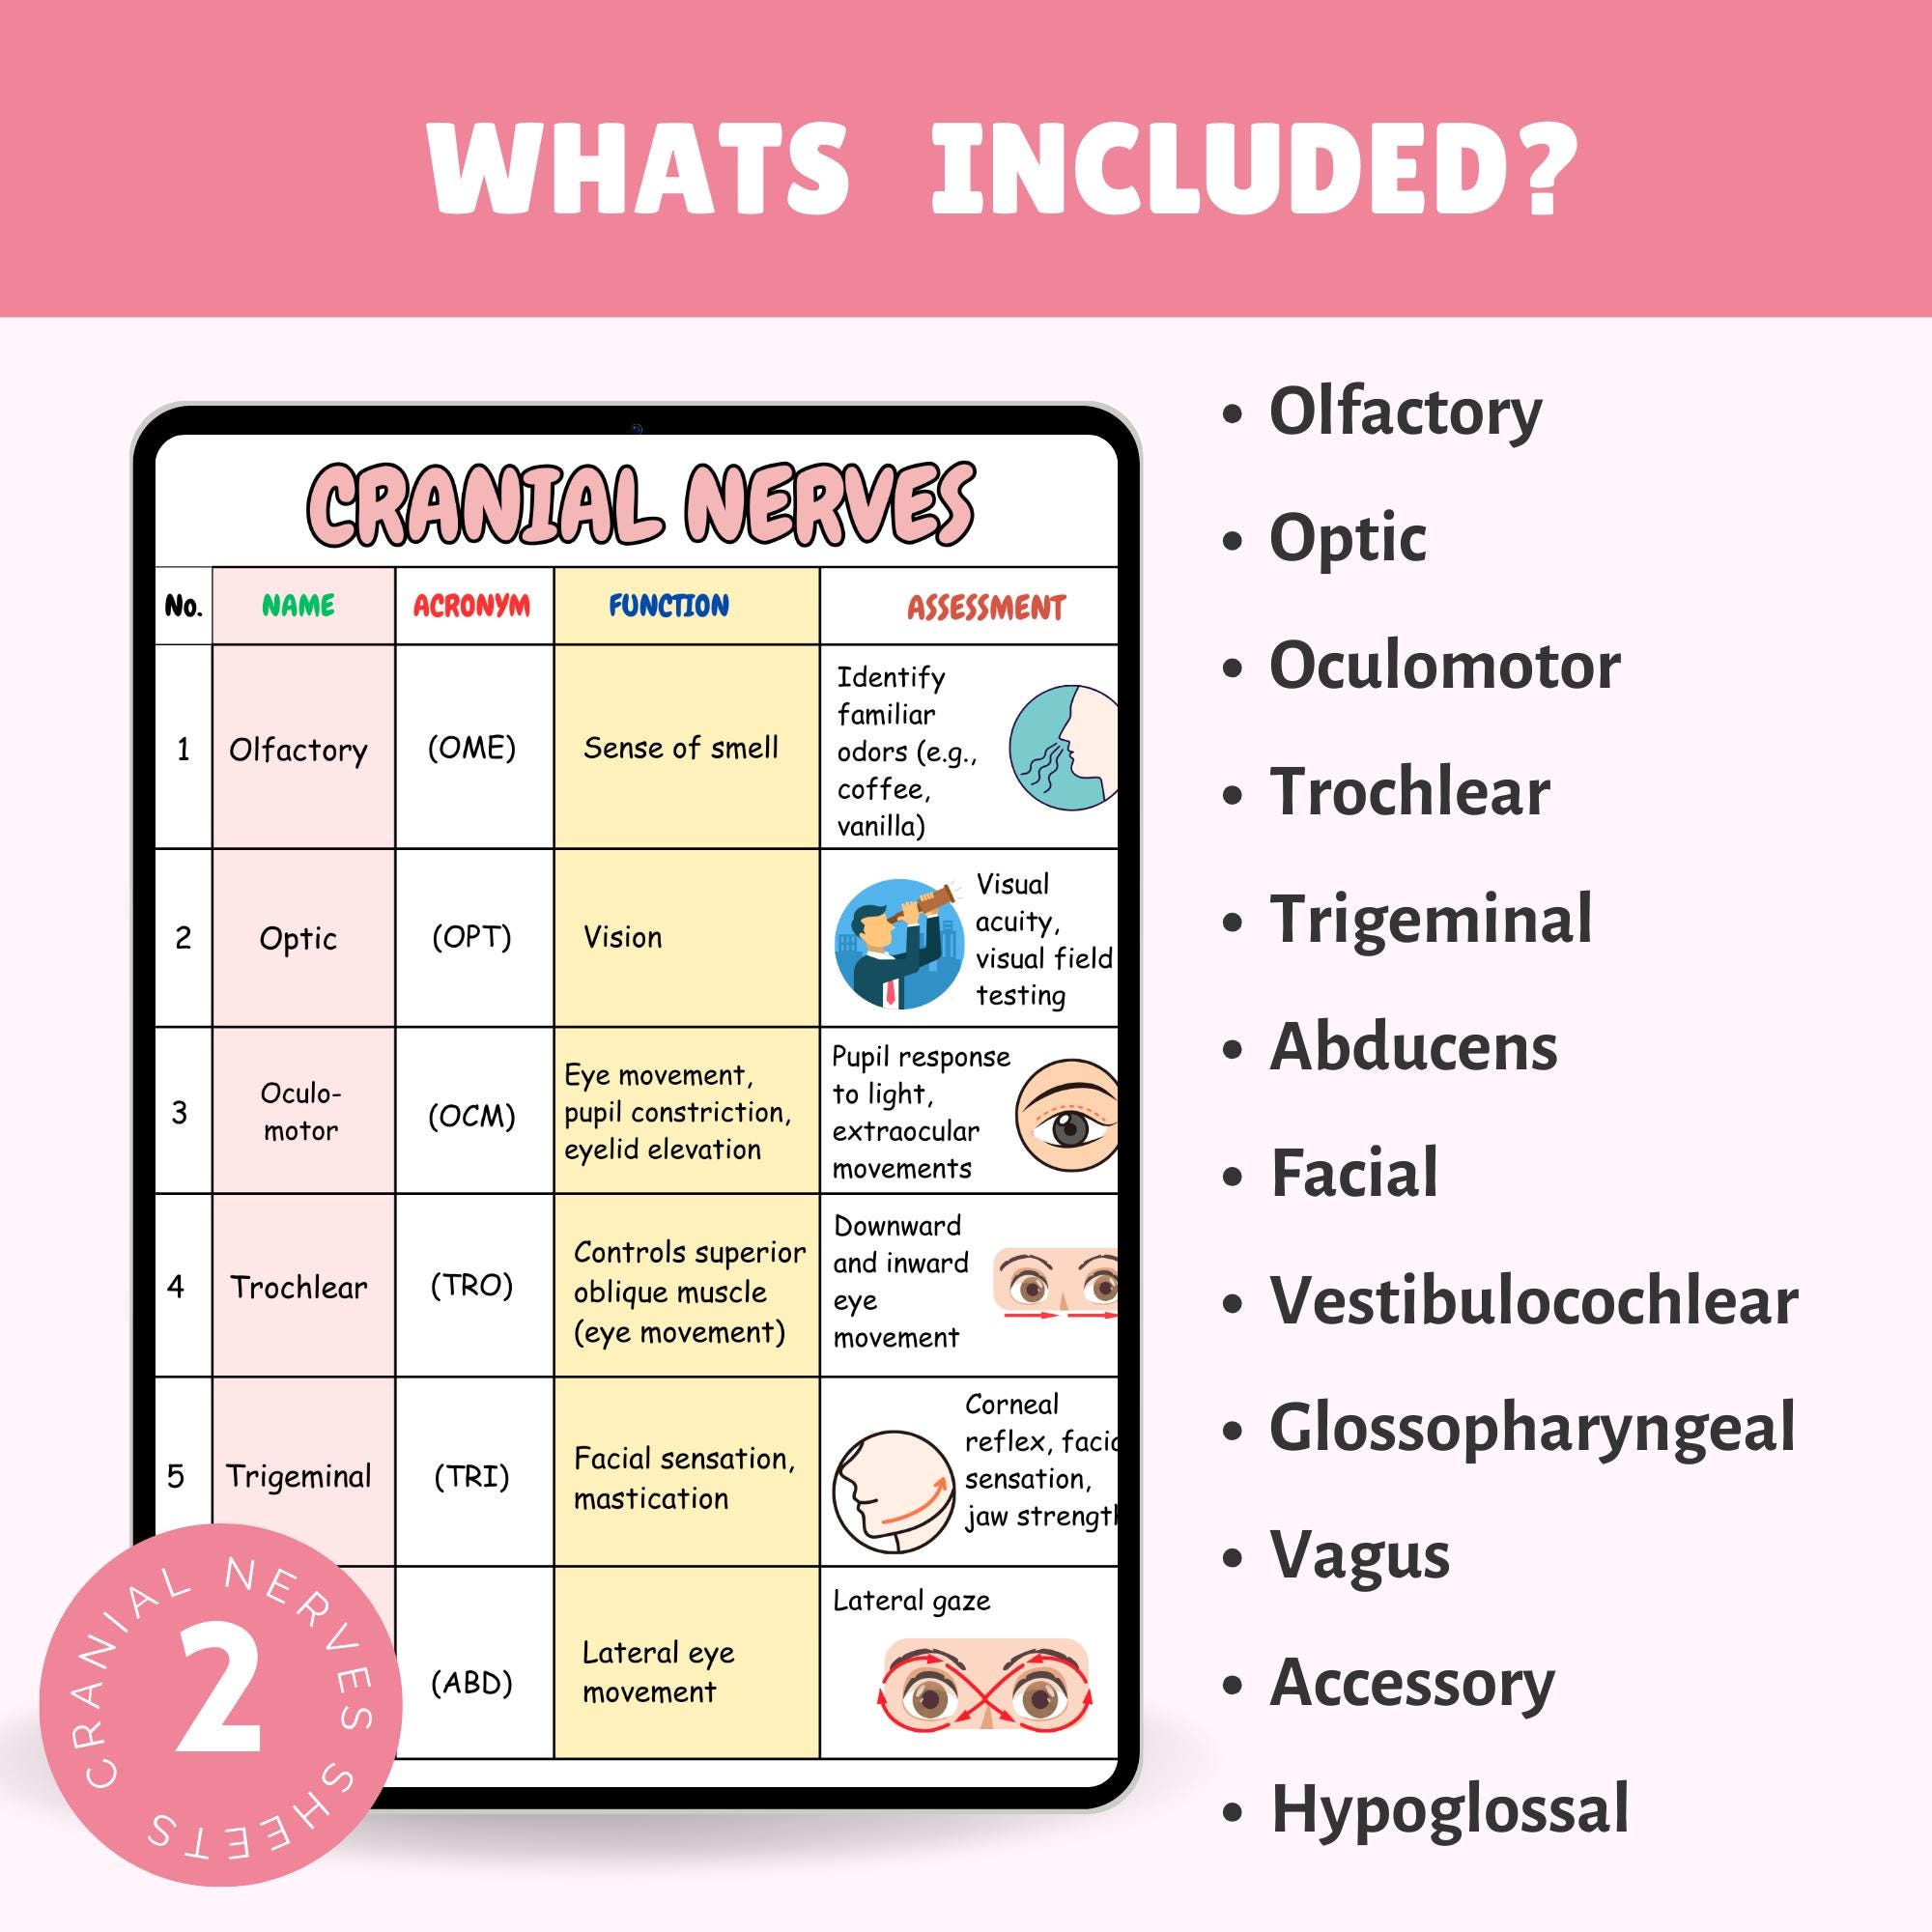
Start with CN II, III, IV, and VI together because they belong to the same orbital system. Ask the patient to follow your finger or a pen light through the six cardinal fields of gaze while you watch for nystagmus, lag, or ptosis. Test pupils with a bright light in a dimmed room. The normal response is brisk constriction in both eyes within half a second. If one pupil is sluggish or dilated, do not move on yet. A fixed unilateral pupil changes the entire urgency of the situation. I once spent twenty minutes chasing a peripheral line in a trauma bay while the neurologist was already calling a CT for a blown pupil we missed during the primary survey. It still gives me a bad feeling. Move to CN V by testing corneal reflex with a wisp of cotton from the periphery of the cornea, not the center. The patient should blink. Then have them clench their jaw while you palpate the masseter and temporalis muscles for symmetry. This is where most people stop, but the sensory branches matter too. Ask the patient to close their eyes and identify light touch on the forehead, cheek, and jaw. Asymmetric sensation here points to central or peripheral pathology in ways that gross motor testing will miss. CN VII is facial expression. Ask the patient to raise eyebrows, close eyes tightly, smile, and puff cheeks. asymmetry on one side with forehead sparing suggests an upper motor neuron lesion. Loss of forehead movement on the same side means a lower motor neuron problem like Bell's palsy. I keep a mirror on my assessment cart because patients rarely believe they have facial droop until they see it, and documenting that they could not see their own asymmetry has legal significance when outcomes are poor.
CN VIII is hearing. Screen with a whispered voice test at each ear. If you need more precision, a 512 Hz tuning fork does Weber and Rinne in under two minutes. Weber lateralizes to the affected ear in conductive loss and to the good ear in sensorineural loss. Rinne shows air conduction greater than bone conduction in normal ears and sensorineural loss, and bone greater than air in conductive loss. Most ward assessments skip this entirely because the equipment is nowhere to be found. Keep a tuning fork in your supply drawer and learn the technique. The difference between knowing and not knowing becomes obvious during a sudden hearing complaint in a septic patient. CN IX and X are glossopharyngeal and vagus. Swallow assessment starts before you even ask about the gag reflex. Watch the patient swallow saliva. If they are drooling or clearing their throat repeatedly, the swallow mechanism is impaired regardless of gag response. The gag reflex itself is unreliable as a standalone test. Patients with depression, prior intubation, or chronic gastritis often have a blunted gag without neurological disease. I document the presence or absence but always pair it with a bedside swallow screen using a small sip of water if the patient is awake and cooperative. If they cough, the swallow is compromised and speech therapy needs to evaluate them before oral intake. CN XI is accessory nerve. Ask the patient to shrug shoulders against resistance and turn their head against resistance. Weakness here is usually subtle and appears later than other deficits. I check it automatically because shoulder weakness changes positioning orders and pressure ulcer risk.
Get the Full Details

CN XII is hypoglossal. Ask the patient to stick out their tongue and move it side to side. Atrophy or fasciculations indicate lower motor neuron disease. Deviation toward the weak side is the key finding. I always ask patients to say "oh" while watching tongue position because some people hold their tongue off to one side voluntarily when asked to protrude it, which mimics pathology.
Common Mistakes That Lead to Missed Findings
The biggest mistake is testing in isolation instead of in functional groups. Eye movements, pupils, and facial sensation belong together because lesions in the brainstem or cavernous sinus affect multiple nerves simultaneously. Testing CN III alone tells you almost nothing. Testing the orbit as a system reveals whether a problem is localized or diffuse. Another frequent error is assuming that normal fundoscopy rules out increased intracranial pressure. Papilledema is a late sign. You can have elevated ICP without visible disc swelling, especially in early or intermittent episodes. I learned this the hard way during a night float when a post-craniotomy patient had normal pupils and normal fundi on quick check but was increasingly somnolent. We called neurosurgery and found a hematoma. The fundi had been normal because the swelling had not yet reached the optic disc. Regular pupillary and level-of-conscience checks caught it first. A third mistake is rushing CN V and VII because they feel boring. These nerves are among the earliest to show changes in raised ICP and brainstem compression. Slowed corneal reflex and decreased facial sensation often precede motor weakness by hours. Document them carefully.
Medication effects confuse the picture. Opioids cause pinpoint pupils that mimic CN III compression. Anticholinergics cause dilated, sluggish pupils that mask the normal light response. Benzodiazepines blunt the gag reflex and slow eye movements. Always ask what the patient has received in the last few hours before you interpret a cranial nerve finding as structural. A good rule of thumb is that pharmacological effects are symmetric and gradual. Structural lesions tend to be asymmetric and may fluctuate with position or arousal.
When the Standard Assessment Fails and What to Do Instead
Sedated or intubated patients cannot follow commands. In these cases, assess brainstem reflexes instead of voluntary responses. Pupillary light reflex, corneal reflex, gag, and cough are all brainstem-mediated and do not require cooperation. Temperature testing with cold water in the ear (caloric stimulation) evaluates CN VIII and the brainstem when spontaneous eye movements are absent. I use this regularly in the ICU for comatose patients and find it far more informative than guessing from documentation in the chart. Patients with baseline deficits require a different strategy. A stroke survivor with chronic facial droop, a Parkinson's patient with masked facies, or someone with myasthenia gravis will fail portions of the exam regardless of new pathology. The workaround is to establish a baseline on admission and track change, not absolute value. Document exactly what you see and compare to the previous exam. If a patient's baseline is a left facial droop from a prior stroke and you now see right-sided weakness as well, that is meaningful. If you see the same left droop with no new findings, that is also meaningful. Context is everything. For patients who cannot protect their airway, skip the gag reflex and go straight to a formal swallow evaluation by speech pathology. Relying on gag to determine oral intake safety is dangerous. The sensitivity of gag for aspiration is poor. A recent systematic review puts the positive predictive value around thirty percent. In other words, a present gag does not mean the patient can swallow safely, and an absent gag does not mean they cannot. Use the clinical swallow screen and referral protocol instead.
Documentation That Actually Helps the Next Nurse
Stop writing "CN II-XII intact." That phrase is meaningless without context. Write what you tested and what you found. "PERRL, EOMI, no nystagmus. Facial symmetry noted with forehead wrinkling. Corneal reflex present bilaterally. Gag present. Tongue midline, no fasciculations." Specific findings let the next person know exactly what was assessed and whether anything changed. When you write "intact," the reader has to guess which nerves you checked and whether you actually did. That guesswork leads to missed deterioration. I keep a quick reference card at the nursing station for the six cranial nerves most relevant to general medical-surgical units: II, III, IV, VI, VII, and IX-X. The others appear in neurology, ENT, and ICU patients. Knowing which nerves matter in which unit saves time and reduces assessment gaps. Med-surg focuses on vision, eye movement, and face. Neurology adds hearing, swallow, and tongue. ICU adds everything and relies more on reflex testing because command-following is unreliable. The assessment itself takes longer to explain than to perform. Once you have a routine, you can complete a focused cranial nerve exam in five to seven minutes with all relevant findings documented in a single note. The initial comprehensive exam with hearing screening and caloric testing when indicated takes about twelve minutes. Anything beyond that is troubleshooting, not routine assessment. If you find yourself spending twenty minutes on a single nerve in a stable patient, you are either over-testing or avoiding the bigger picture.
One practical habit that helped me enormously: always assess cranial nerves after vital signs and before starting treatments. Patients are more cooperative before medications blur their cognition, and you capture the baseline before interventions alter the exam. This sequencing matters more than you might expect, especially on busy shifts when every minute counts and the first abnormal finding dictates the next dozen decisions.