Putting The Assessment And Intervention Model To Work
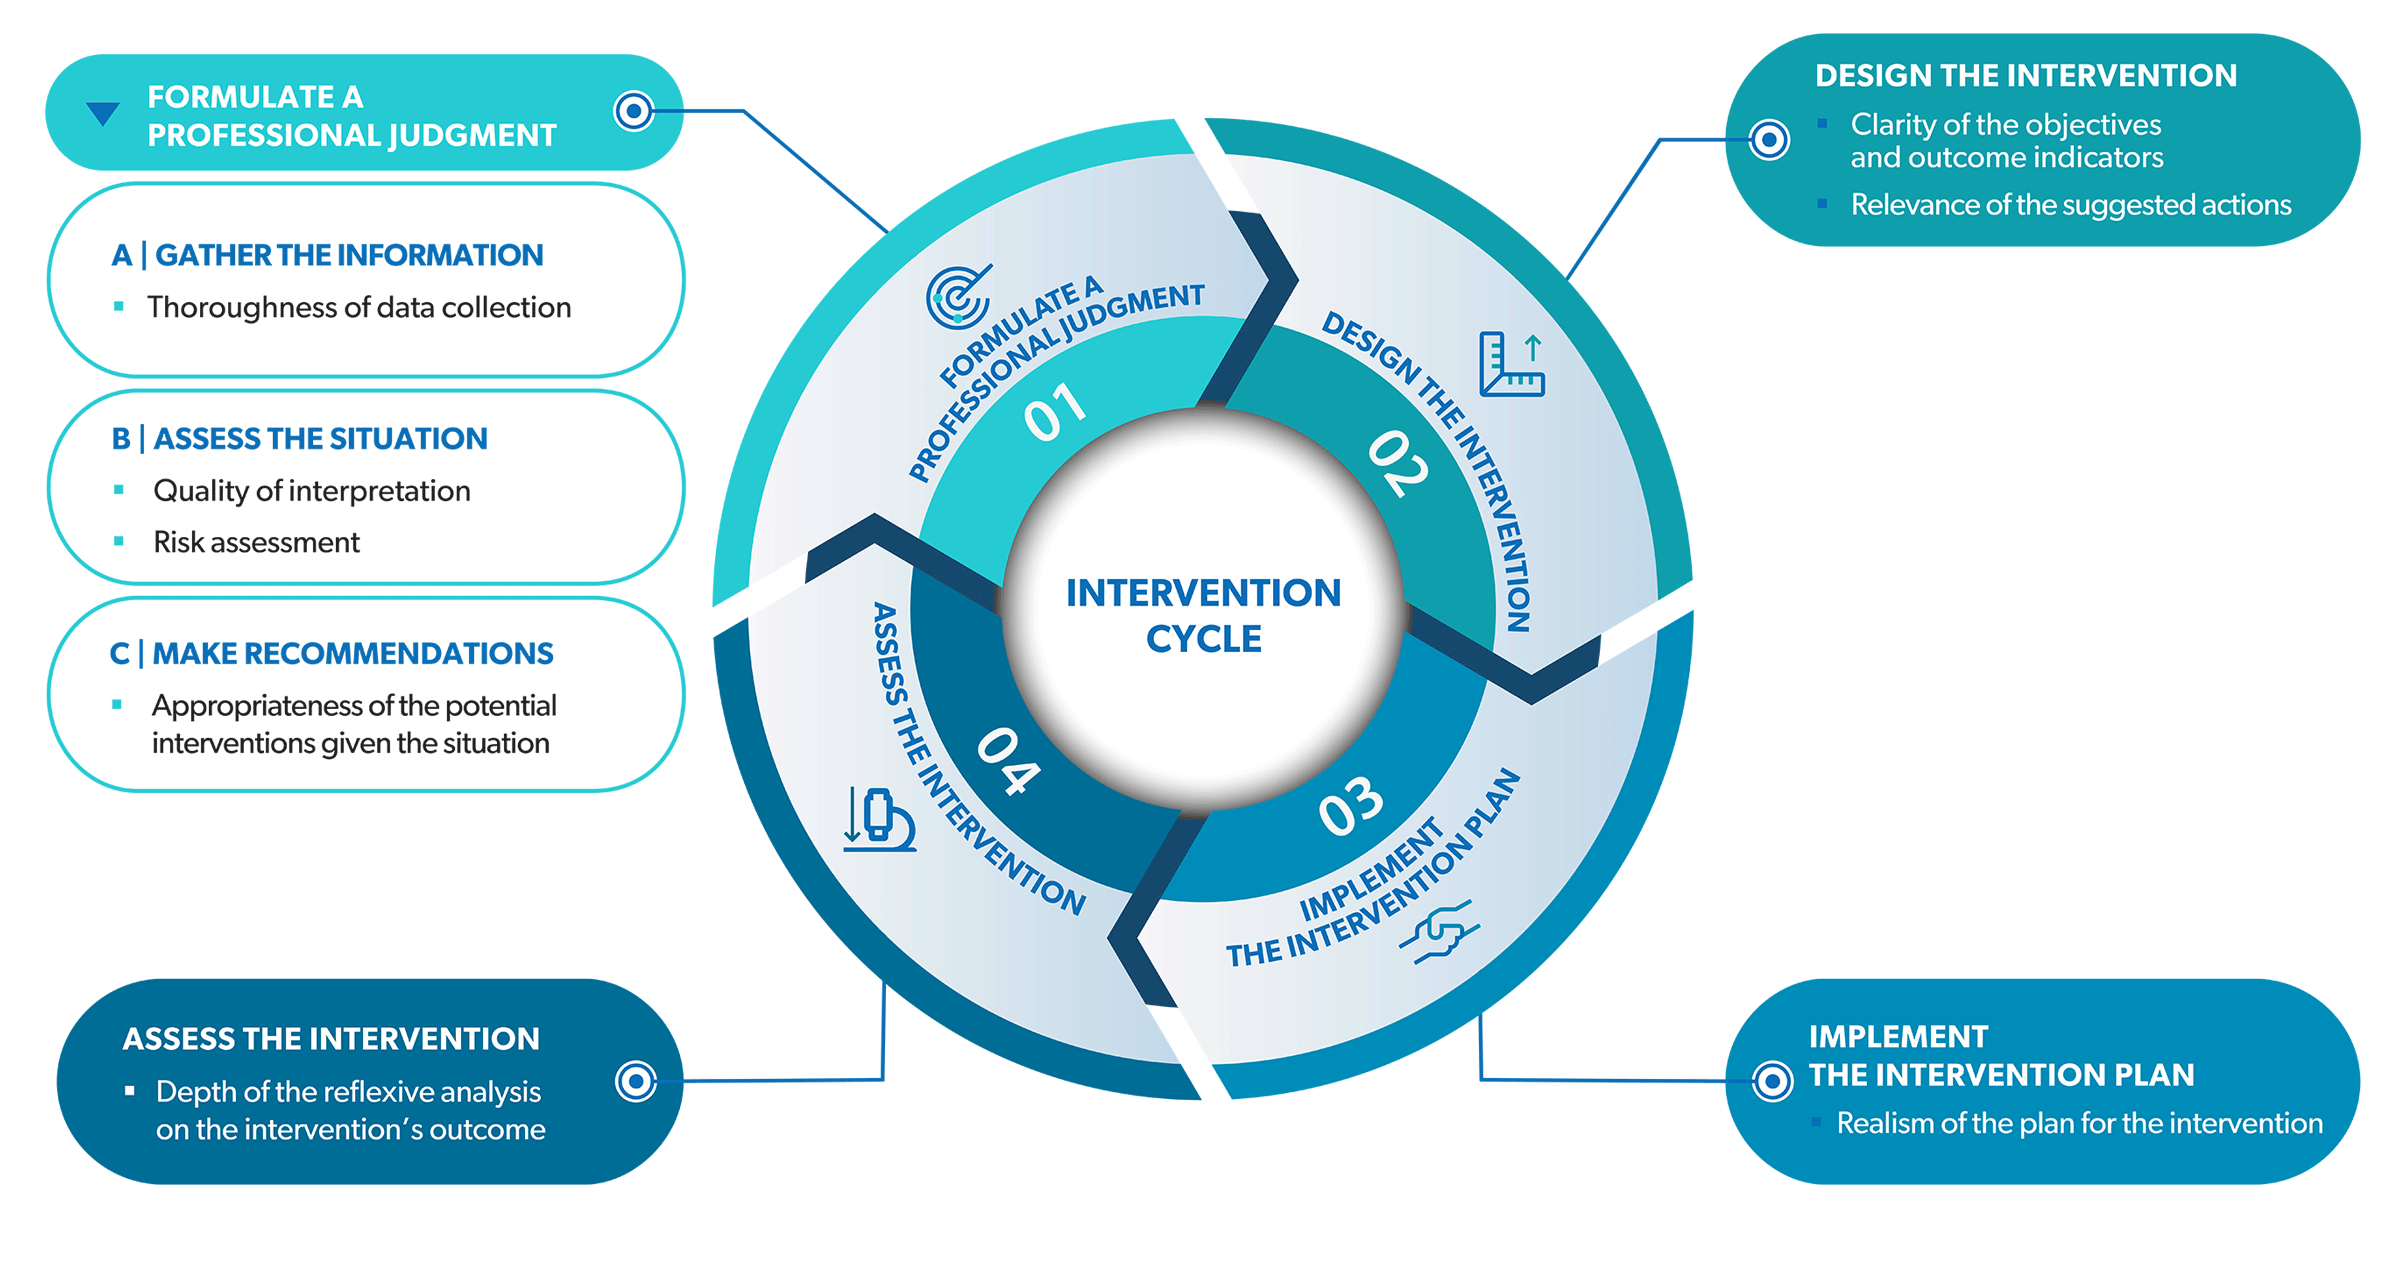
The Assessment and Intervention Model is a cycle, not a checklist. You measure something, decide what's wrong, try a fix, measure again, and adjust. That's it in the simplest terms. But like any cycle, the devil is in how you define the measurement and how quickly you move when the intervention fails. I spent years watching schools and clinics try to use this framework without truly understanding what makes it work or break. Most people treat it as a series of boxes to check before moving to a more intensive tier. The real problem isn't the model itself. It's that the assessment phase is almost always under-resourced and the intervention phase is almost always over-hopeful. Here's what I mean. You administer a screening tool. It flags a student at risk. Then you implement a research-backed intervention with fidelity. Eight weeks later, you re-assess and the data shows no meaningful change. At that point, the model says you escalate. But here's the thing nobody tells you: most of the time, the initial assessment was measuring the wrong thing entirely.
How It Actually Works In Practice
Start with a problem statement that is specific enough to measure. "Reads below grade level" is not a problem statement. It's a label. A real problem statement looks like "Student reads 45 words per minute on Grade 3 passages with 60% comprehension, which is 35 words below the class median and 2 standard deviations below expectations." That kind of specificity matters because it tells you exactly what to target and how to know when you've hit it. Once you have that, you pick an intervention that directly addresses the gap you identified. If the student struggles with phonemic awareness, don't give them repeated reading practice. Those are different skills. I've seen this mistake consistently across both school and clinical settings. People conflate fluency with decoding and then wonder why oral reading fluency interventions aren't moving the needle on comprehension or accuracy. After implementing the intervention, you monitor progress. This doesn't need to be complex. Weekly or bi-weekly progress monitoring using the same type of measurement you used initially is usually sufficient. Curriculum-based measurements, probe scores, short standardized subtests — whatever matches your problem statement. The key is consistency in what you're measuring and how often you're measuring it.
Then you look at the data. Not just the endpoint. The trajectory. A student who goes from 45 to 55 words per minute in eight weeks may still be below grade level, but the rate of improvement matters. It tells you whether the intervention is directionally correct even if it isn't enough on its own. That distinction saves people from throwing out a decent intervention when what they actually need is more intensity or a different instructional approach layered on top.
Get the Full Details

Common Pitfalls I Keep Seeing
The biggest one is assuming that any failure to respond means the student is the problem. Sometimes the intervention itself is flawed, or the dosage is insufficient, or the student has an underlying issue you haven't identified yet. Learning disabilities, vision problems, hearing issues, anxiety, trauma — all of these can look like a failure to respond to an intervention when they're actually the root cause. Another frequent mistake is using norm-referenced tests as progress monitoring tools. These tests aren't designed for that. They're too infrequent, too unstable at the individual level, and too disconnected from the actual curriculum to give you useful feedback between administrations. Use them for initial identification if you must, but switch to curriculum-based measures once you're in the intervention phase. I once worked with a case where a student had been cycled through three tiers of reading intervention over two years with no movement. Every assessment said the same thing: he wasn't responding. We eventually traced it back to an undiagnosed auditory processing disorder that no one had screened for. The interventions were appropriate for typical readers but fundamentally misaligned with his actual deficit. By that point, he had three years of documented non-response on file, which made the eligibility conversation complicated even though the root cause was completely addressable.
The Assessment And Intervention Model In Different Contexts
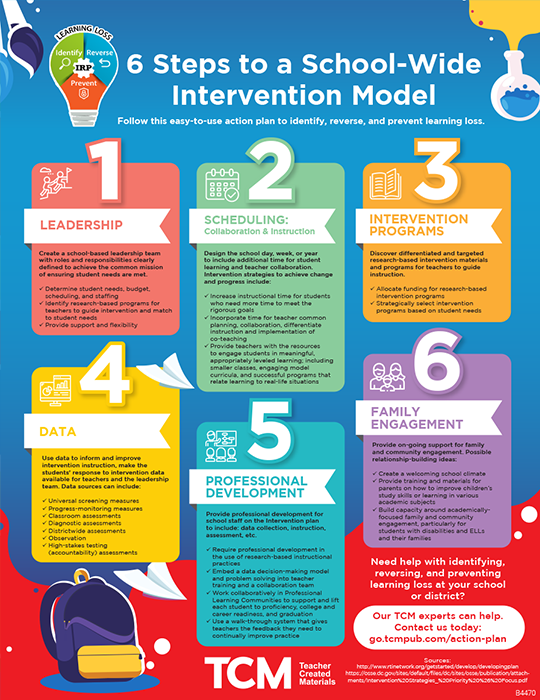
In schools, this framework typically lives under umbrella systems like MTSS or RTI. The tiers are structured: universal screening for everyone, targeted interventions for those who need them, and intensive individualized support for the smallest group. The model works best when the communication between tiers is seamless and when data is actually reviewed on a regular schedule rather than hoarded until an eligibility meeting. In clinical or therapeutic settings, the model looks similar but the language shifts. Instead of tiers, you're looking at levels of care. Instead of curriculum-based measures, you might be using standardized clinical instruments alongside behavioral tracking. The core logic is identical though: assess, intervene, reassess, adjust. One thing that catches people off guard is the difference between response to intervention and response to instruction. RTI assumes the instruction was adequate. If the foundational instruction was poor, then a student's lack of response to Tier 2 intervention doesn't tell you anything about their individual needs. It tells you the school didn't provide effective core instruction in the first place. I've seen this invalidate entire assessment cycles because nobody bothered to verify the quality of the general education program before escalating.
What To Do When The Model Doesn't Work
Sometimes it just doesn't work within the parameters you have. A student may have needs that exceed what the current system can provide. That's not a failure of the model. That's a limitation of the resources and expertise available to you. When you hit that wall, you document it clearly and move toward alternative pathways — whether that's a referral for special education evaluation, a change in placement, or a different therapeutic modality entirely. The model is a tool, not a destination. Using it faithfully doesn't guarantee outcomes, but ignoring it almost guarantees worse ones. The data it produces, even the negative data, is infinitely more useful than intuition or anecdote. Just make sure you're measuring the right thing, applying the right intervention, and being honest about what the results actually mean.