How The Assessment And Intervention Model Actually Works In Clinical Practice
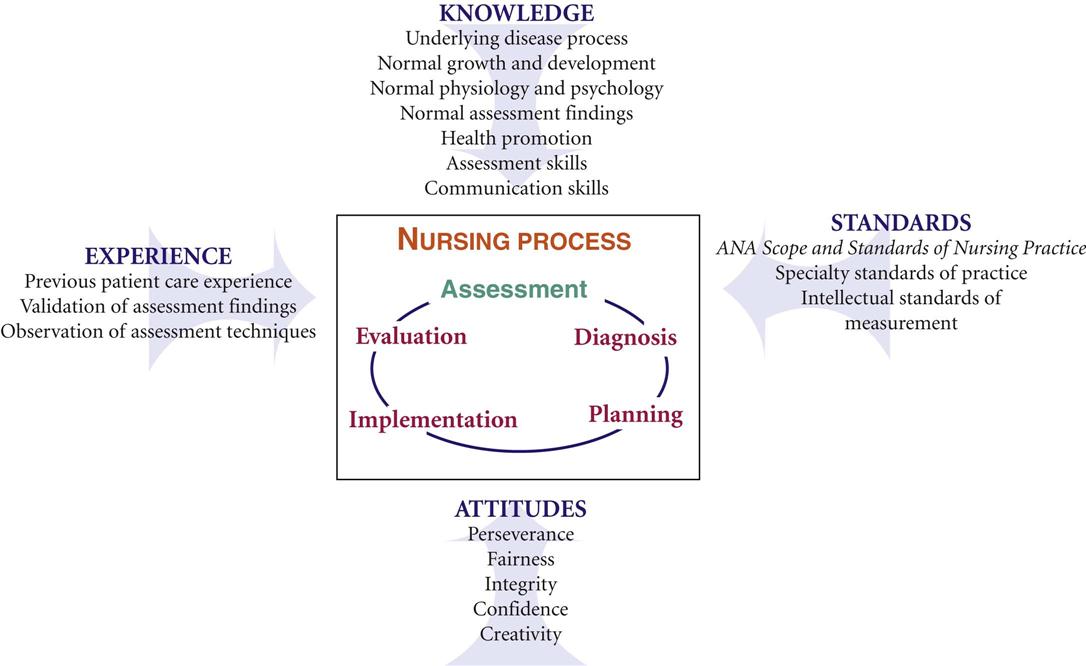
The assessment and intervention model in nursing isn't a single rigid framework you can memorize and apply everywhere. It's a decision-making loop that nursing programs spend weeks teaching you, but the real structure comes from understanding when to deviate from it. Most students learn it as a five-step process: assess, diagnose, plan, implement, evaluate. That's the textbook version. In reality, you're often doing steps three through five while still gathering data for step one because the patient's condition is changing faster than your intake form. I worked in a medical-surgical unit for several years before moving into case management, and the model that actually kept me from making mistakes was the nursing process itself, but applied flexibly. Here's how that looks when you're not in a classroom anymore.
Assessment And Intervention Model In Nursing Step By Step
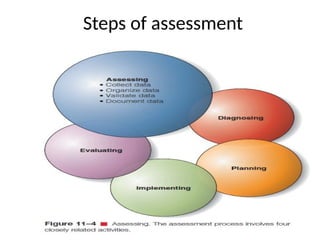
Let me start with assessment because this is where most people, including new nurses I've supervised, go wrong. Assessment is not "taking vitals and writing them down." Assessment is pattern recognition under uncertainty. You're gathering subjective data from the patient, objective data from monitors and labs, and contextual data from the situation all at once, then you're deciding what matters and what's noise. I remember a patient, mid-sixties, admitted for what looked like routine pneumonia. Vitals were borderline. Respiratory rate was 22, heart rate 98, oxygen saturation at 93 percent on room air. The initial assessment checklist would have flagged this as stable enough for routine monitoring. But the patient's speech was slightly slurred and their gait, when they walked to the bathroom, had a new asymmetry. I documented this as altered neurological status alongside the respiratory findings and escalated the assessment rather than waiting for the next scheduled round. Two hours later the patient was decompensating. A CT scan showed a small stroke that had been missed because nobody connected the dots between the respiratory admission and the neurological signs. If I had treated assessment as a checkbox exercise, that patient would have had a much worse outcome. So the first step, assessment, requires you to stay uncomfortable with surface-level data. Write down the numbers, yes. But also write down the thing that doesn't fit the story. That's where the actual clinical value lives.
The second step is nursing diagnosis. This is different from a medical diagnosis. A medical diagnosis is "pneumonia." A nursing diagnosis might be "ineffective airway clearance related to increased secretions and fatigue as evidenced by productive cough and SpO2 below 94 percent." Notice the structure: the problem, the cause, the evidence. That "as evidenced by" part is non-negotiable. Without it, your diagnosis is just an opinion. I've seen care plans written with diagnoses that had no supporting evidence, which made the rest of the process impossible to defend or evaluate properly. Planning comes next, and this is where the model starts to break down in busy units. You're supposed to set measurable, patient-specific goals with timelines. In practice, you're setting goals fast because the attending physician is waiting and the bed needs to turn over. The goal doesn't have to be perfect. It has to be specific enough that you can tell whether you met it or not. "Patient will maintain oxygen saturation above 92 percent on supplemental oxygen" is a goal you can measure. "Patient will breathe better" is not. I usually write goals in a way that my replacement nurse at 7 AM can understand without reading the entire chart. That's a practical constraint most textbooks don't mention. Implementation is the execution phase. This is where you carry out the interventions: administering medications, positioning the patient, coordinating with respiratory therapy, educating the family. The key insight here that you won't find in the orientation packet is that implementation is not a sequence, it's a prioritization problem. You have twelve things to do in twenty minutes. The model treats them as if they happen in order. They don't. You're doing assessment and implementation simultaneously. I learned to talk to the patient while I was documenting, to use the medication pass as a opportunity for a quick reassessment of pain levels and skin condition, to delegate what could be delegated without creating extra handoff friction. The model assumes ideal conditions. Your job is to make it work in real ones.
Get the Full Details
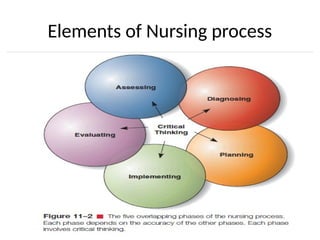
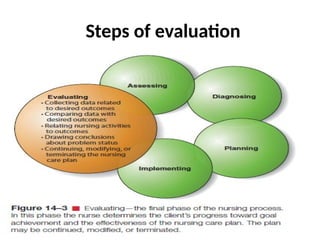
Evaluation is the step everyone rushes through. You check whether the interventions worked, and if they didn't, you go back to assessment and start again. That's the loop. The problem is that evaluation requires a baseline, and if your initial assessment was shallow, your evaluation will be meaningless. I've had situations where a patient's blood pressure dropped after starting a new medication and the nurse on duty attributed it to "normal fluctuation" because the earlier assessments had never established a reliable baseline. That's a failure of the model caused by a failure in the first step, not a failure of the model itself. Knowing that distinction matters. There's a particular edge case with this model that gives people trouble: patients with multiple chronic conditions who present with overlapping symptoms. I had a diabetic patient with peripheral artery disease and early-stage kidney disease who came in with swelling in both legs and confusion. The assessment could have gone several ways depending on which condition you prioritized. I went with the confusion as the primary concern because altered mental status is always higher priority than edema. Turns out it was hyperglycemia with osmotic shifts, not a kidney issue and not a vascular issue. The model works well here, but only if you're willing to let the most dangerous symptom drive the initial diagnosis rather than the most familiar one. Beginners tend to pick the diagnosis that matches the chart history. That's a trap. Another nuance that isn't taught well: the intervention phase includes communication interventions. Documenting a change in condition, calling the physician, notifying the family, updating the interdisciplinary team. These are interventions too, and they're often the ones that determine whether the clinical interventions succeed or fail. I once watched a wound care nurse spend forty minutes on a pressure ulcer dressing while the patient's antibiotic was overdue by three hours because nobody had communicated the timing conflict to the pharmacy. The model includes communication as part of implementation, but it rarely gets the same emphasis as the hands-on procedures.
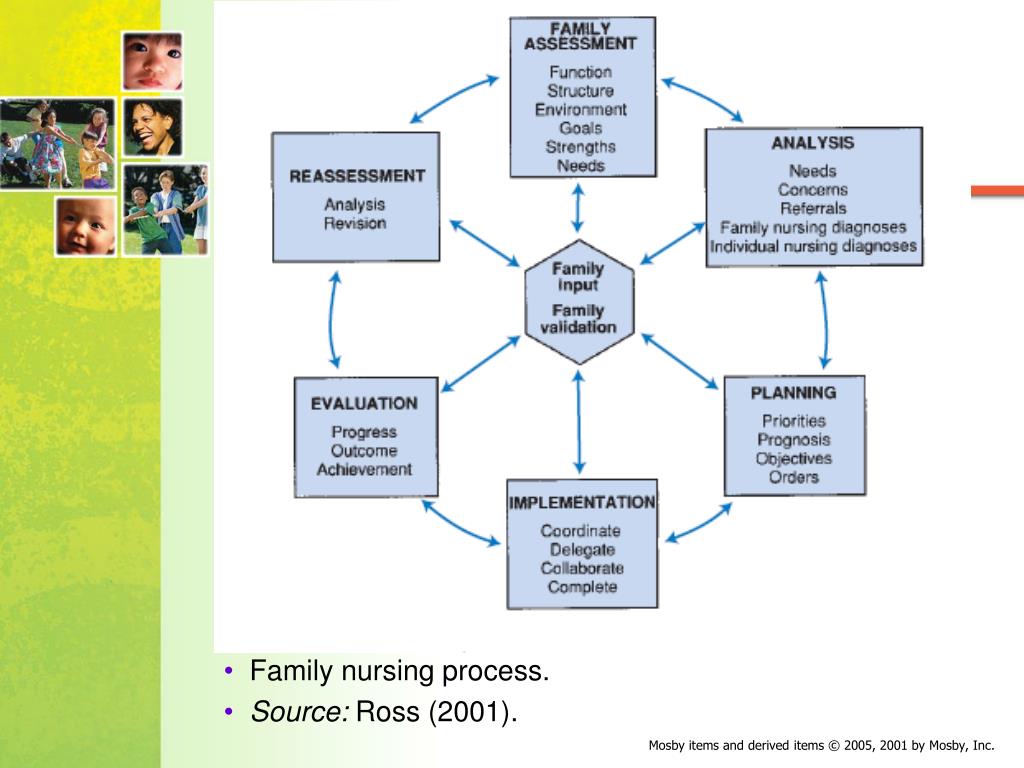
If you're looking for a structured way to apply this, the ADPIE framework Assessment Diagnosis Planning Implementation Evaluation is the standard shorthand. It maps directly onto the nursing process I described. Some programs also use the Nursing Intervention Classification system for standardizing intervention terminology, which helps with documentation and handoffs but adds complexity that isn't always necessary for everyday practice. One limitation of this model that deserves more attention: it assumes the nurse has sufficient information to make accurate assessments. In reality, you're often working with incomplete data, especially in emergency or fast-transition settings. The workaround is to make your assumptions explicit in your documentation and revisit them quickly. "Assessment suggests possible sepsis based on elevated heart rate and decreased urine output, pending culture results" is honest and actionable. Pretending you have more certainty than you do is dangerous. The model also struggles with patients who are non-adherent or whose social situation makes the planned interventions impossible. I had a heart failure patient discharged with a clear plan for fluid restriction and daily weight monitoring who went back to a living situation where he shared a kitchen with three other people and had no reliable source of scale. The assessment was accurate, the diagnosis was correct, the plan was appropriate for an ideal scenario, and the intervention failed because the context didn't support it. In those cases, the model needs to be augmented with a social assessment that's as thorough as the physical one, and that's something the traditional framework doesn't emphasize enough.
For anyone studying this or applying it at work, the practical takeaway is simpler than the textbooks make it. Assess thoroughly and question your first impression. Diagnose with evidence, not intuition alone. Plan with specificity and the next shift in mind. Implement by prioritizing, not just proceeding. Evaluate honestly and close the loop. The model is a tool, not a script. It works when you use it, and it fails when you treat it like a checklist you complete instead of a reasoning process you inhabit.