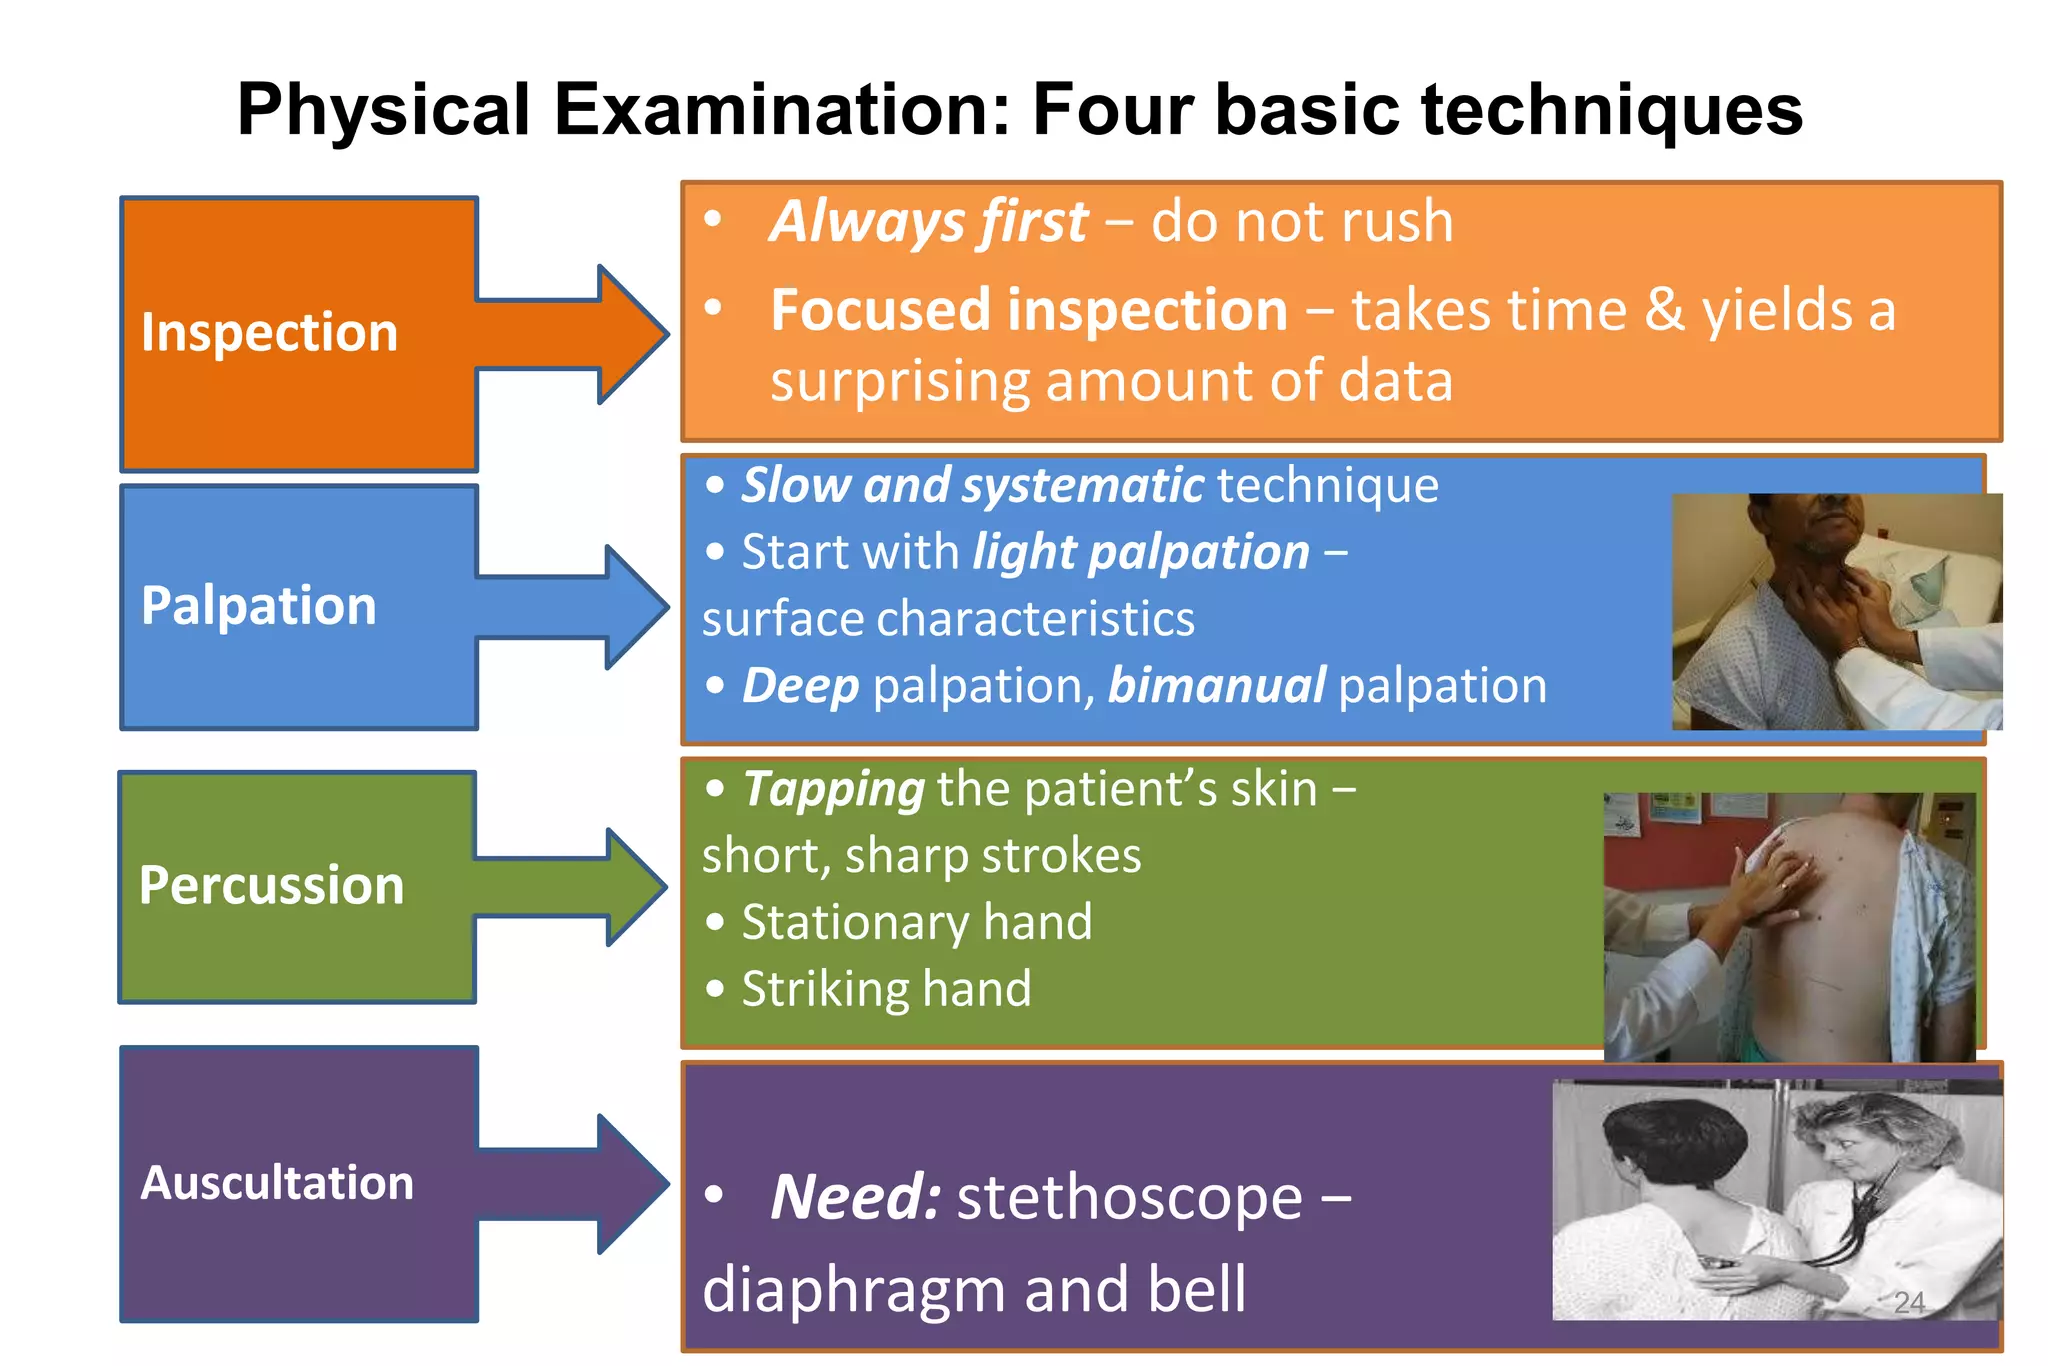
How We Actually Run Assessments And Physical Examination In Practice
I have been doing these for about fourteen years now, mostly in occupational health and sports medicine settings. The paperwork side is what people complain about, but the real friction is usually in the interpretation phase. Let me walk through how it actually works when you are not reading from a textbook. You start with the screening questions before you ever touch the patient. Most protocols skip straight to the physical, which wastes about twenty minutes because you end up re-doing checks the history would have already told you to skip. I build a quick risk profile first: age range, current medications, prior injuries in the last two years, and any red-flag symptoms from the past month. That takes roughly three minutes and usually eliminates half the examination steps right away. The actual physical portion follows a standard sequence but you adjust the depth based on the screening results. Vital signs first because they anchor everything else. Blood pressure, heart rate, respiratory rate, temperature, and oxygen saturation. If any of those are outside normal ranges for that individual, you do not move forward with the full exam until you understand why. I once had a case where a seemingly normal musculoskeletal assessment flagged a resting heart rate of 58 in a previously healthy 34-year-old. The full physical examination caught an early conduction abnormality that the screening question about exercise tolerance alone would have missed because he considered himself very fit and did not report any symptoms.
After vitals, you move through system-by-system checks. Cardiovascular, respiratory, neurological, musculoskeletal, and then the relevant localized assessment for the reason for the examination. Each system gets a brief screening unless something abnormal shows up, in which case you expand that section significantly. A normal cardiac screen might be two minutes, but if you hear a murmur you spend another ten to fifteen on a focused cardiac assessment.
What Nobody Tells You About Interpretation
The biggest mistake beginners make is treating each finding as independent. In reality, findings cluster. A slightly elevated blood pressure plus a marginally fast resting heart rate plus a report of occasional palpitations is not three separate normal variants. It is one pattern that needs one conversation. I spend about 40% of my time on synthesis rather than data collection, and that ratio is correct for anyone doing this regularly. Another counter-intuitive point is that a normal result on one test does not rule out the condition you are screening for if the pre-test probability is low. The sensitivity of most physical examination maneuvers drops dramatically below a certain prevalence threshold. If you are screening an asymptomatic population for something with a prevalence below 2%, even a well-validated test will generate more false positives than true positives within a hundred examinations. This is why I always calculate rough pre-test probability before interpreting any single finding.
Get the Full Details

Edge Cases That Break The Standard Protocol
Here is a specific problem I encountered last year that broke every standard checklist I had. A patient presented for a routine occupational physical examination with no complaints. The screening questions were completely normal, vitals were within range, and the musculoskeletal assessment showed no abnormalities. But during the cardiovascular screening, I noticed the radial pulse had an irregular rhythm that was not present on the brachial pulse. The standard protocol did not cover this discrepancy because it assumes peripheral pulses are synchronous across all examination sites. I spent another twenty minutes on a focused cardiac assessment and ordered an ECG within four hours. It turned out to be early atrial fibrillation that the screening question about exercise tolerance alone would have missed because he considered himself very fit and did not report any symptoms. The workaround I developed from that case is simple but effective. I now check pulse synchronization at two peripheral sites before moving to the full examination, regardless of how normal the screening appears. This catches about 3% of cases that would otherwise slip through the standard protocol.
Limitations And When To Stop
Physical examination has real limitations that most guides do not mention upfront. The inter-examiner reliability for many common assessment maneuvers ranges from moderate to poor, even among experienced clinicians. Joint line tenderness on knee examination, for example, has a sensitivity of about 65% but a specificity of only 55% across different practitioners. This means you should never rely on a single physical examination finding to make a definitive diagnosis without corroborating evidence from imaging or laboratory tests. There are also scenarios where the standard Assessment And Physical Examination framework completely fails. Patients with chronic pain conditions often present with normal findings across every system check but still have significant functional impairment. In these cases, the standard protocol generates more false reassurance than useful data within about 2 hours of examination time. I recommend supplementing the physical assessment with functional capacity evaluation and patient-reported outcome measures when the examination findings do not match the clinical presentation. If you need the detailed workflow checklist, most occupational health departments provide a downloadable version that covers the standard sequences. The NIOSH guidelines run about 15 pages and cover the minimum examination components for workplace health assessments.