A Practical Guide to the Abdominal Exam
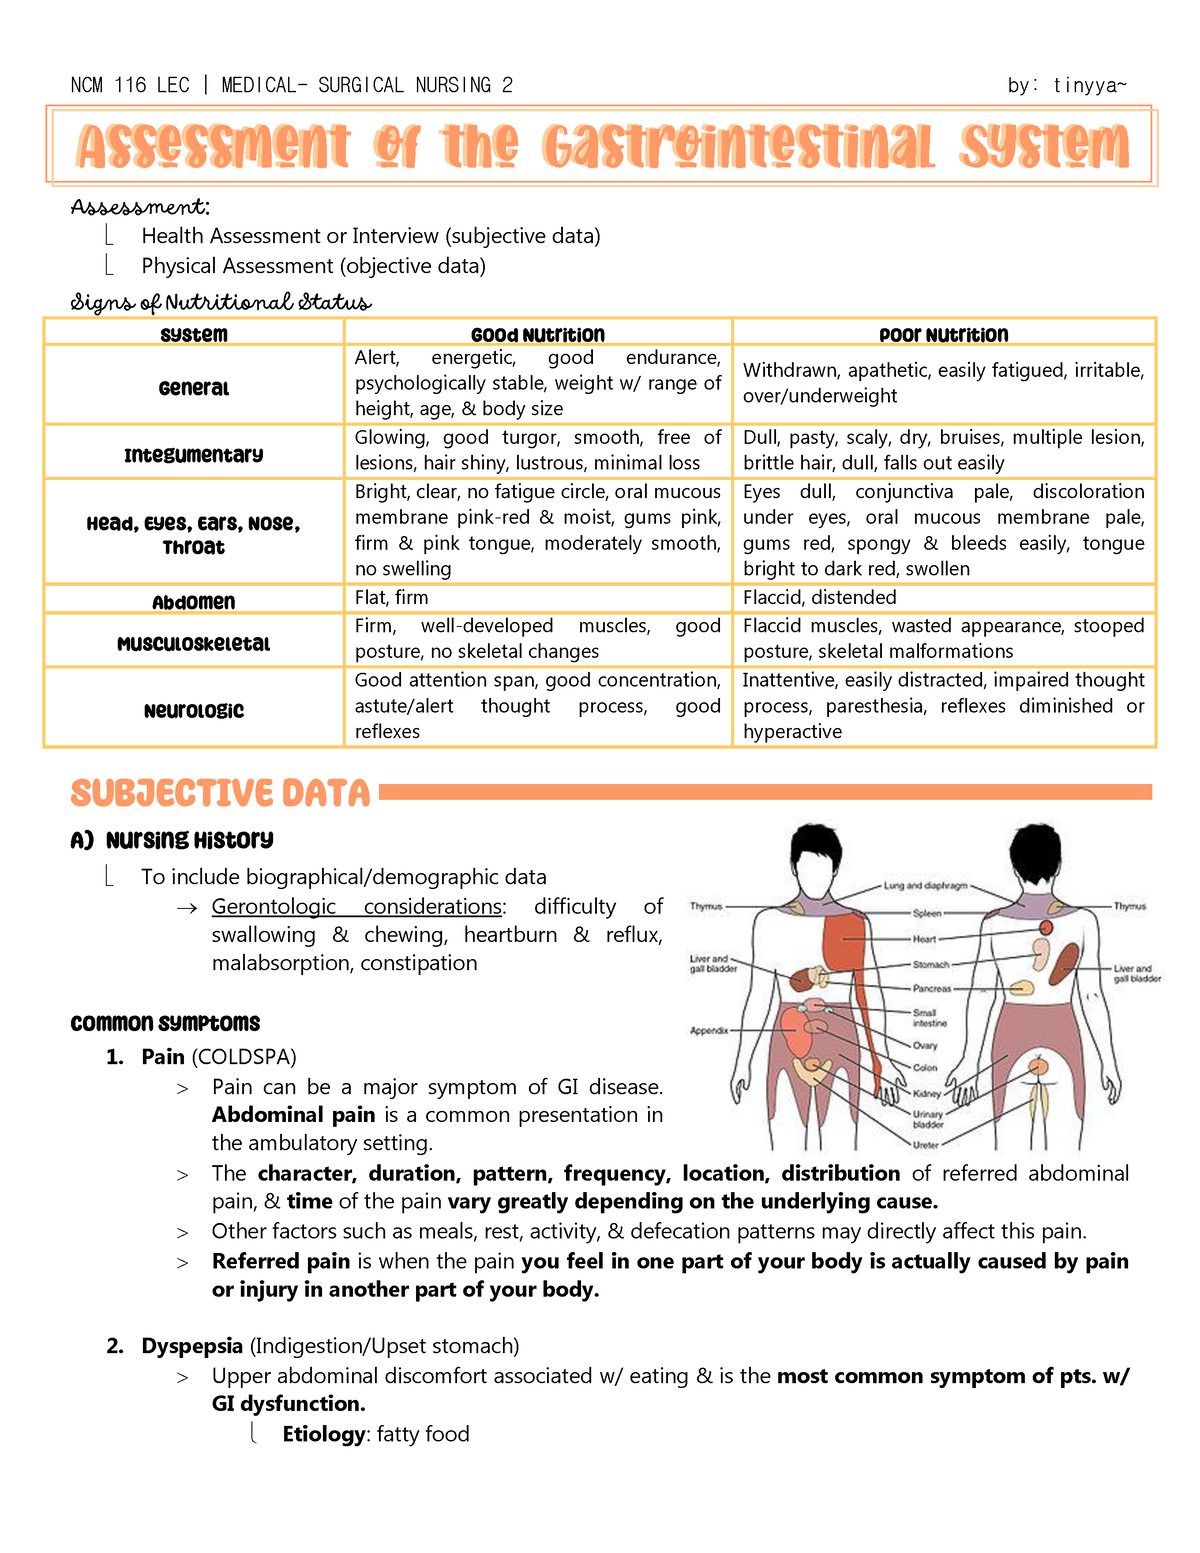
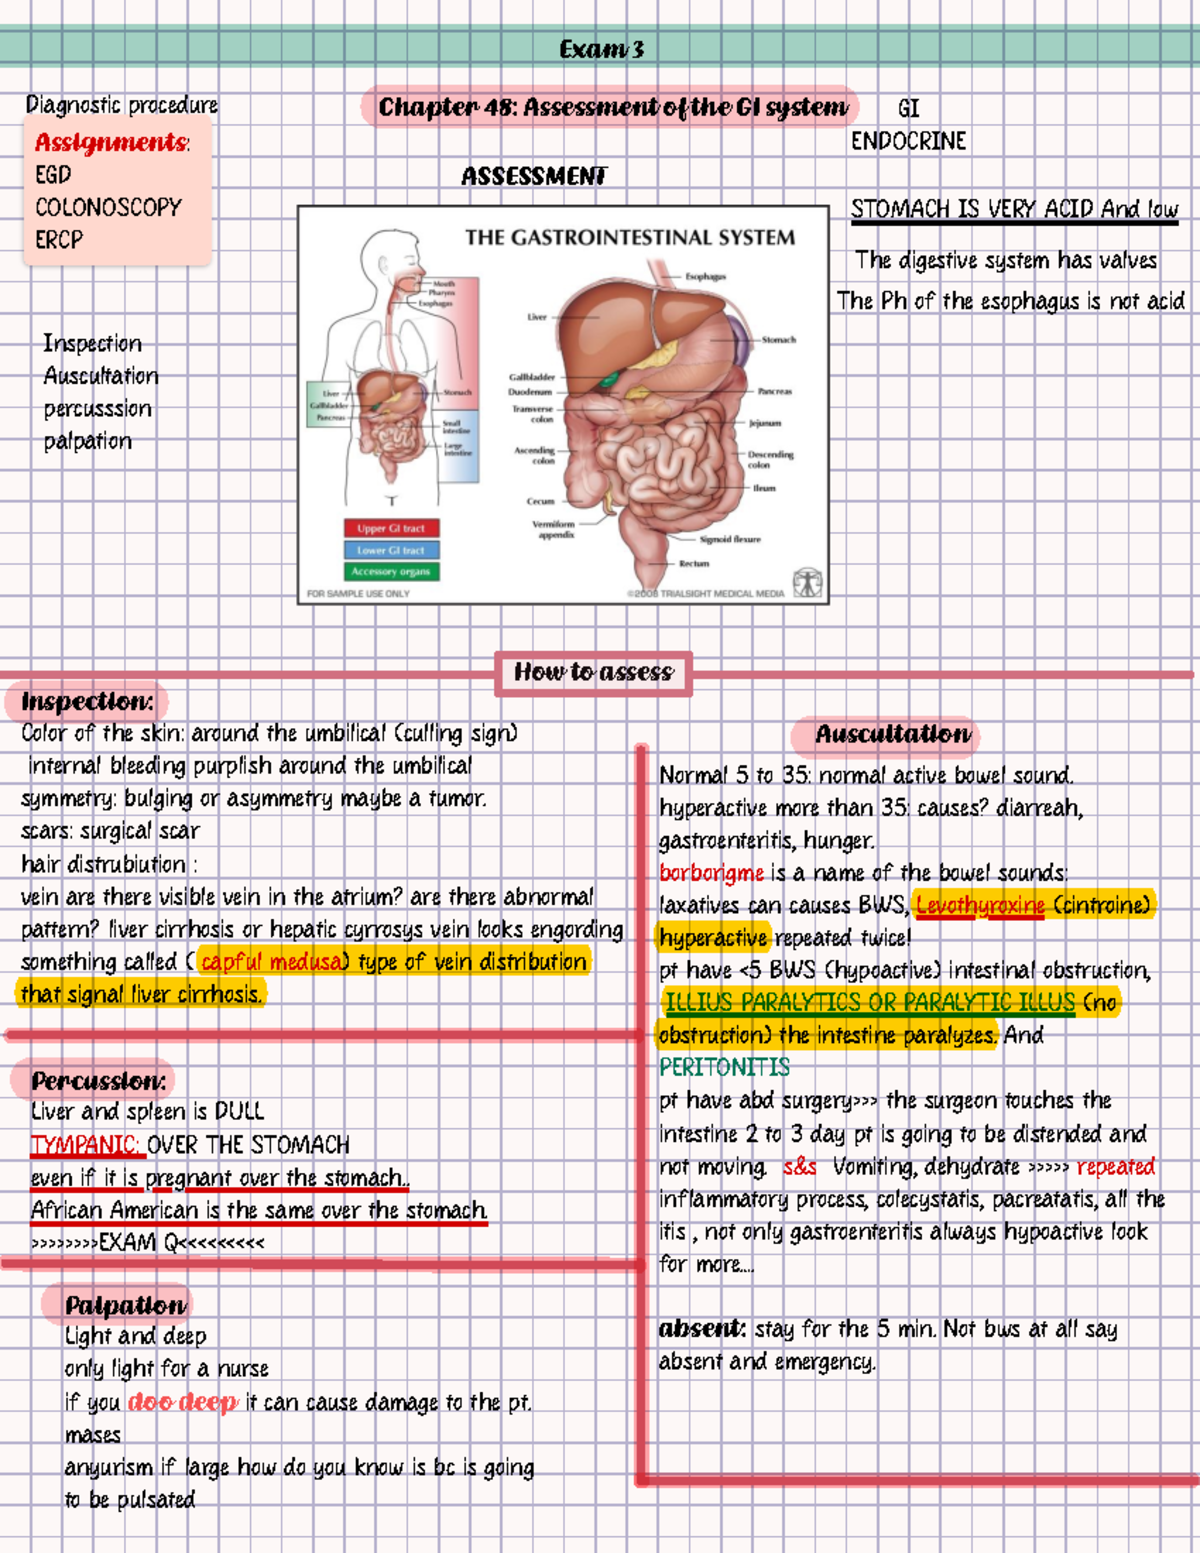
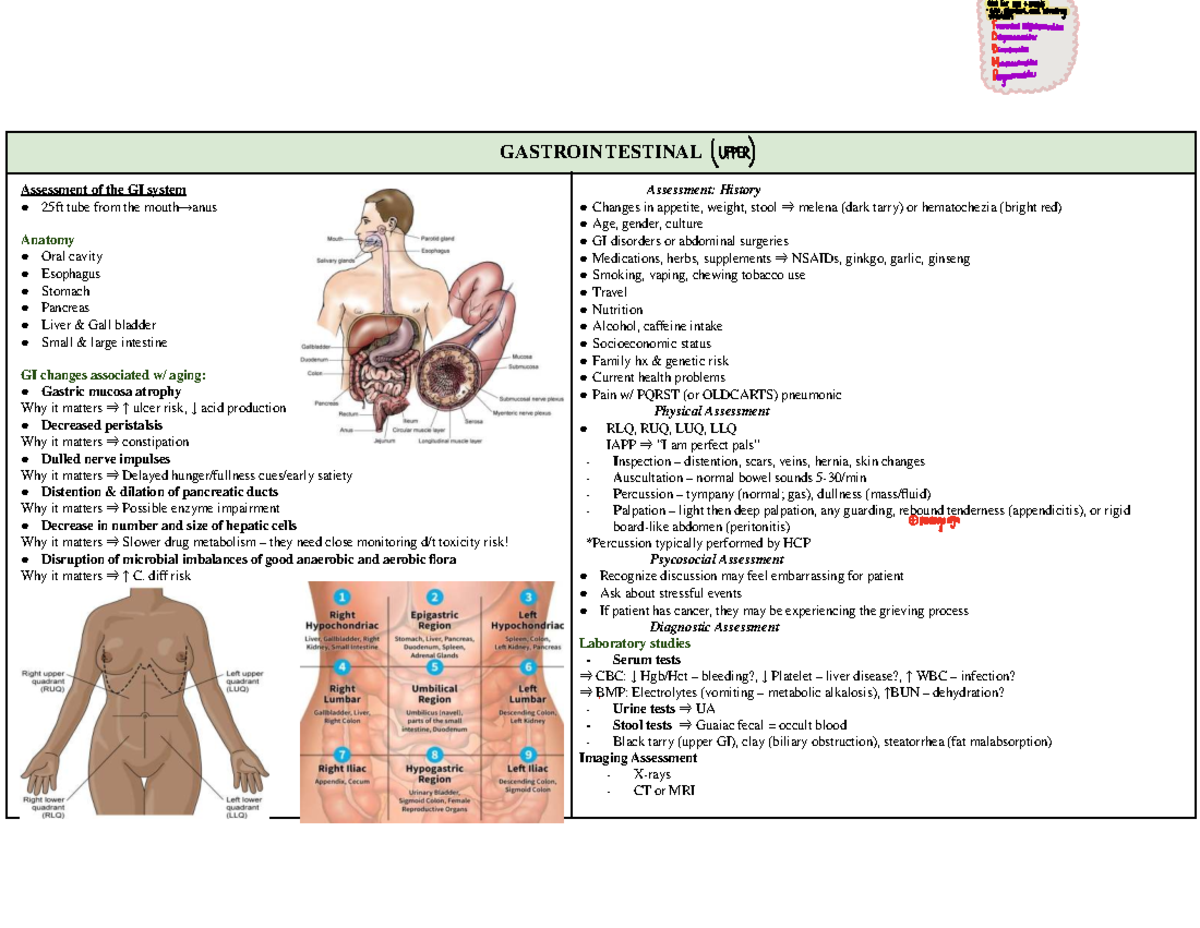
The GI system assessment is one of those skills that looks straightforward until you're actually standing over a patient with a distended abdomen and realizing you fumbled the sequence. I've been doing physical exams long enough to know that the difference between a good abdominal assessment and a wasted ten minutes usually comes down to one thing: order. Start with inspection. The patient should be supine with their head slightly elevated and their arms at their sides. Expose the abdomen fully from the xiphoid process to the pubic symphysis, but keep them draped otherwise. Watch for symmetry, scars, visible peristalsis, hernias, pulsations, and skin changes. A single trained eye can catch hepatomegaly just by noticing a bulge in the right upper quadrant or a prominent epigastric pulse. Don't skip the flanks — look for Cullen's sign or Grey Turner's sign if trauma or pancreatitis is in the differential. Then auscultate before you touch anything else. This is the most common mistake people make. Palpating the abdomen first can stimulate bowel sounds artificially, which makes it impossible to distinguish hyperactive from normal from absent sounds. Place your stethoscope diaphragm gently against each of the four quadrants and listen for at least thirty seconds before concluding bowel sounds are absent. Normoactive sounds occur every five to fifteen seconds. Hyperactive sounds are gurgling and frequent — think early obstruction or gastroenteritis. Hypoactive sounds are slow and sparse. Absolute silence needs a full two-minute confirmation across all quadrants before you call it absent.
Percussion comes next. Start from an area of known normal resonance and move toward areas of suspected abnormality. Tympany over most of the abdomen is normal because of gas-filled bowel. Dullness over the liver span in the right midclavicular line is expected. Dullness in other areas — particularly in the flanks when the patient is supine — suggests ascites. That said, you need at least one to one point five liters of free fluid before flank dullness becomes detectable by percussion alone. Shifting dullness and the fluid wave test add sensitivity but require practice. Palpation is where most assessments fall apart. Light palpation first, then deep palpation. Use the palmar surface of your fingers, not the fingertips. Ask the patient to breathe slowly through their mouth. Start away from any area of reported tenderness and work your way in. Document the location, size, consistency, mobility, and tenderness of any masses you feel. For liver and spleen palpation, approach from the patient's right side and use bimanual technique. The liver edge is normally palpable one to two centimeters below the costal margin in thin individuals. If it's firm, nodular, or tender, that's a different conversation entirely. I ran into a problem once with a patient whose CT later showed a retroperitoneal mass. Every standard maneuver during the abdominal exam came back negative. The mass was posterior and deep enough that neither light nor deep palpation could reach it, and percussion didn't suggest anything either. What finally gave it away was watching the abdominal wall move asymmetrically when the patient coughed — a subtle shift near the right flank that I caught only because I was standing still and looking rather than actively touching. Stand back and observe. It costs nothing and catches things palpation misses.
Rebound tenderness and the psoas and obturator signs are useful when appendicitis is on the table, but they have limitations. Rebound tenderness has a poor positive predictive value for surgical pathology according to multiple meta-analyses. A positive psoas sign suggests a retrocecal appendix, and a positive obturator sign points toward a pelvic appendix, but neither test alone changes management significantly. Use them as part of a clinical picture, not as standalone diagnostics. Gallbladder assessment follows its own logic. Inspect the right upper quadrant. Palpate deeply under the right costal margin while the patient takes a slow breath. If the gallbladder is enlarged and inflamed, you'll feel it descend and then stop abruptly as the patient catches their breath due to pain — that's a positive Murphy's sign. Keep your fingers in place while they inhale. If they can't complete a full inhalation because of pain, the test is positive. The issue is that Murphy's sign is specific but not sensitive. A normal gallbladder with cholecystitis may not be palpable at all, and obese patients are nearly impossible to assess this way. Bowel sounds remain one of the most misunderstood parts of the exam. Here's the thing most people get wrong: the presence or absence of bowel sounds doesn't reliably distinguish between paralytic ileus and mechanical obstruction. Both can present with high-pitched, tinkling sounds early on. The clinical context matters more than the sound itself. A patient who hasn't passed flatus, is vomiting, and has a distended abdomen needs imaging regardless of what you hear. Listening for bowel sounds before deciding whether to order a CT is a waste of time.
Get the Full Details
When documenting findings, be specific. "Bowel sounds present in all quadrants" tells the next clinician nothing useful. Write "normoactive bowel sounds heard in all four quadrants, no vascular bruits appreciated." "Abdomen soft, non-tender, non-distended" is better than "benign abdominal exam." The difference between adequate documentation and inadequate documentation is often whether the reader can tell what you actually did. The Hepatojugular reflux test belongs in the GI assessment when there's suspicion of right heart failure contributing to hepatic congestion. Apply firm pressure to the right upper quadrant for thirty to sixty seconds while watching the jugular venous angle. A sustained rise in JVP of more than three centimeters indicates positive reflux. It's a quick maneuver that connects cardiac and hepatic pathology in one step. Don't forget the hernia orifices. Inspect and palpate the inguinal regions with the patient standing. Ask them to cough or bear down. Check for reducibility. Femoral hernias present below and lateral to the pubic tubercle, which distinguishes them from inguinal hernias that present above and medial to it. A non-reducible hernia that's tender and accompanied by vomiting is a surgical emergency until proven otherwise. Time matters here more than any scoring system.
A few tools help but none replace hands-on examination. Ultrasound is far more sensitive than percussion for detecting ascites, picking up as little as one hundred milliliters in the hepatorenal recess. Point-of-care ultrasound is becoming standard in many emergency departments, and it's worth learning basic views even if you're not the one performing the scan. A quick subcostal view showing fluid around the liver changes the pre-test probability dramatically. The limitations of this assessment are worth stating plainly. Body habitus matters enormously. In obese patients, deep palpation is nearly impossible and organomegaly is routinely missed. Muscle guarding from anxiety or pain can simulate rigidity, making peritonitis impossible to confirm clinically. Geriatric patients frequently present with minimal findings despite significant intra-abdominal pathology. A ruptured AAA in an elderly patient may have barely any tenderness on exam but will show up on every lab value and every deterioration over the next few hours. Clinical assessment is a screening tool, not a definitive one, and treating it as anything more dangerous than that is how bad outcomes happen. If you're learning this for the first time, practice on yourself before you practice on patients. Palpate your own liver edge by lying supine and taking slow deep breaths while pressing just below the right costal margin. Find your cecal water hammer in the left lower quadrant. Locate your aorta just to the left of the midline and note whether its pulsation is within normal limits. Knowing what normal feels like on your own body makes it infinitely easier to recognize abnormal when someone else is the subject.
The sequence stays the same every time: inspect, auscultate, percuss, palpate. Everything else — the maneuvers, the special tests, the interpretation — depends on what you find. There's no shortcut through the basic four. Anyone who tells you otherwise is either oversimplifying or skipping steps they themselves haven't mastered.