Assessment Of Pain: The Practical Reality
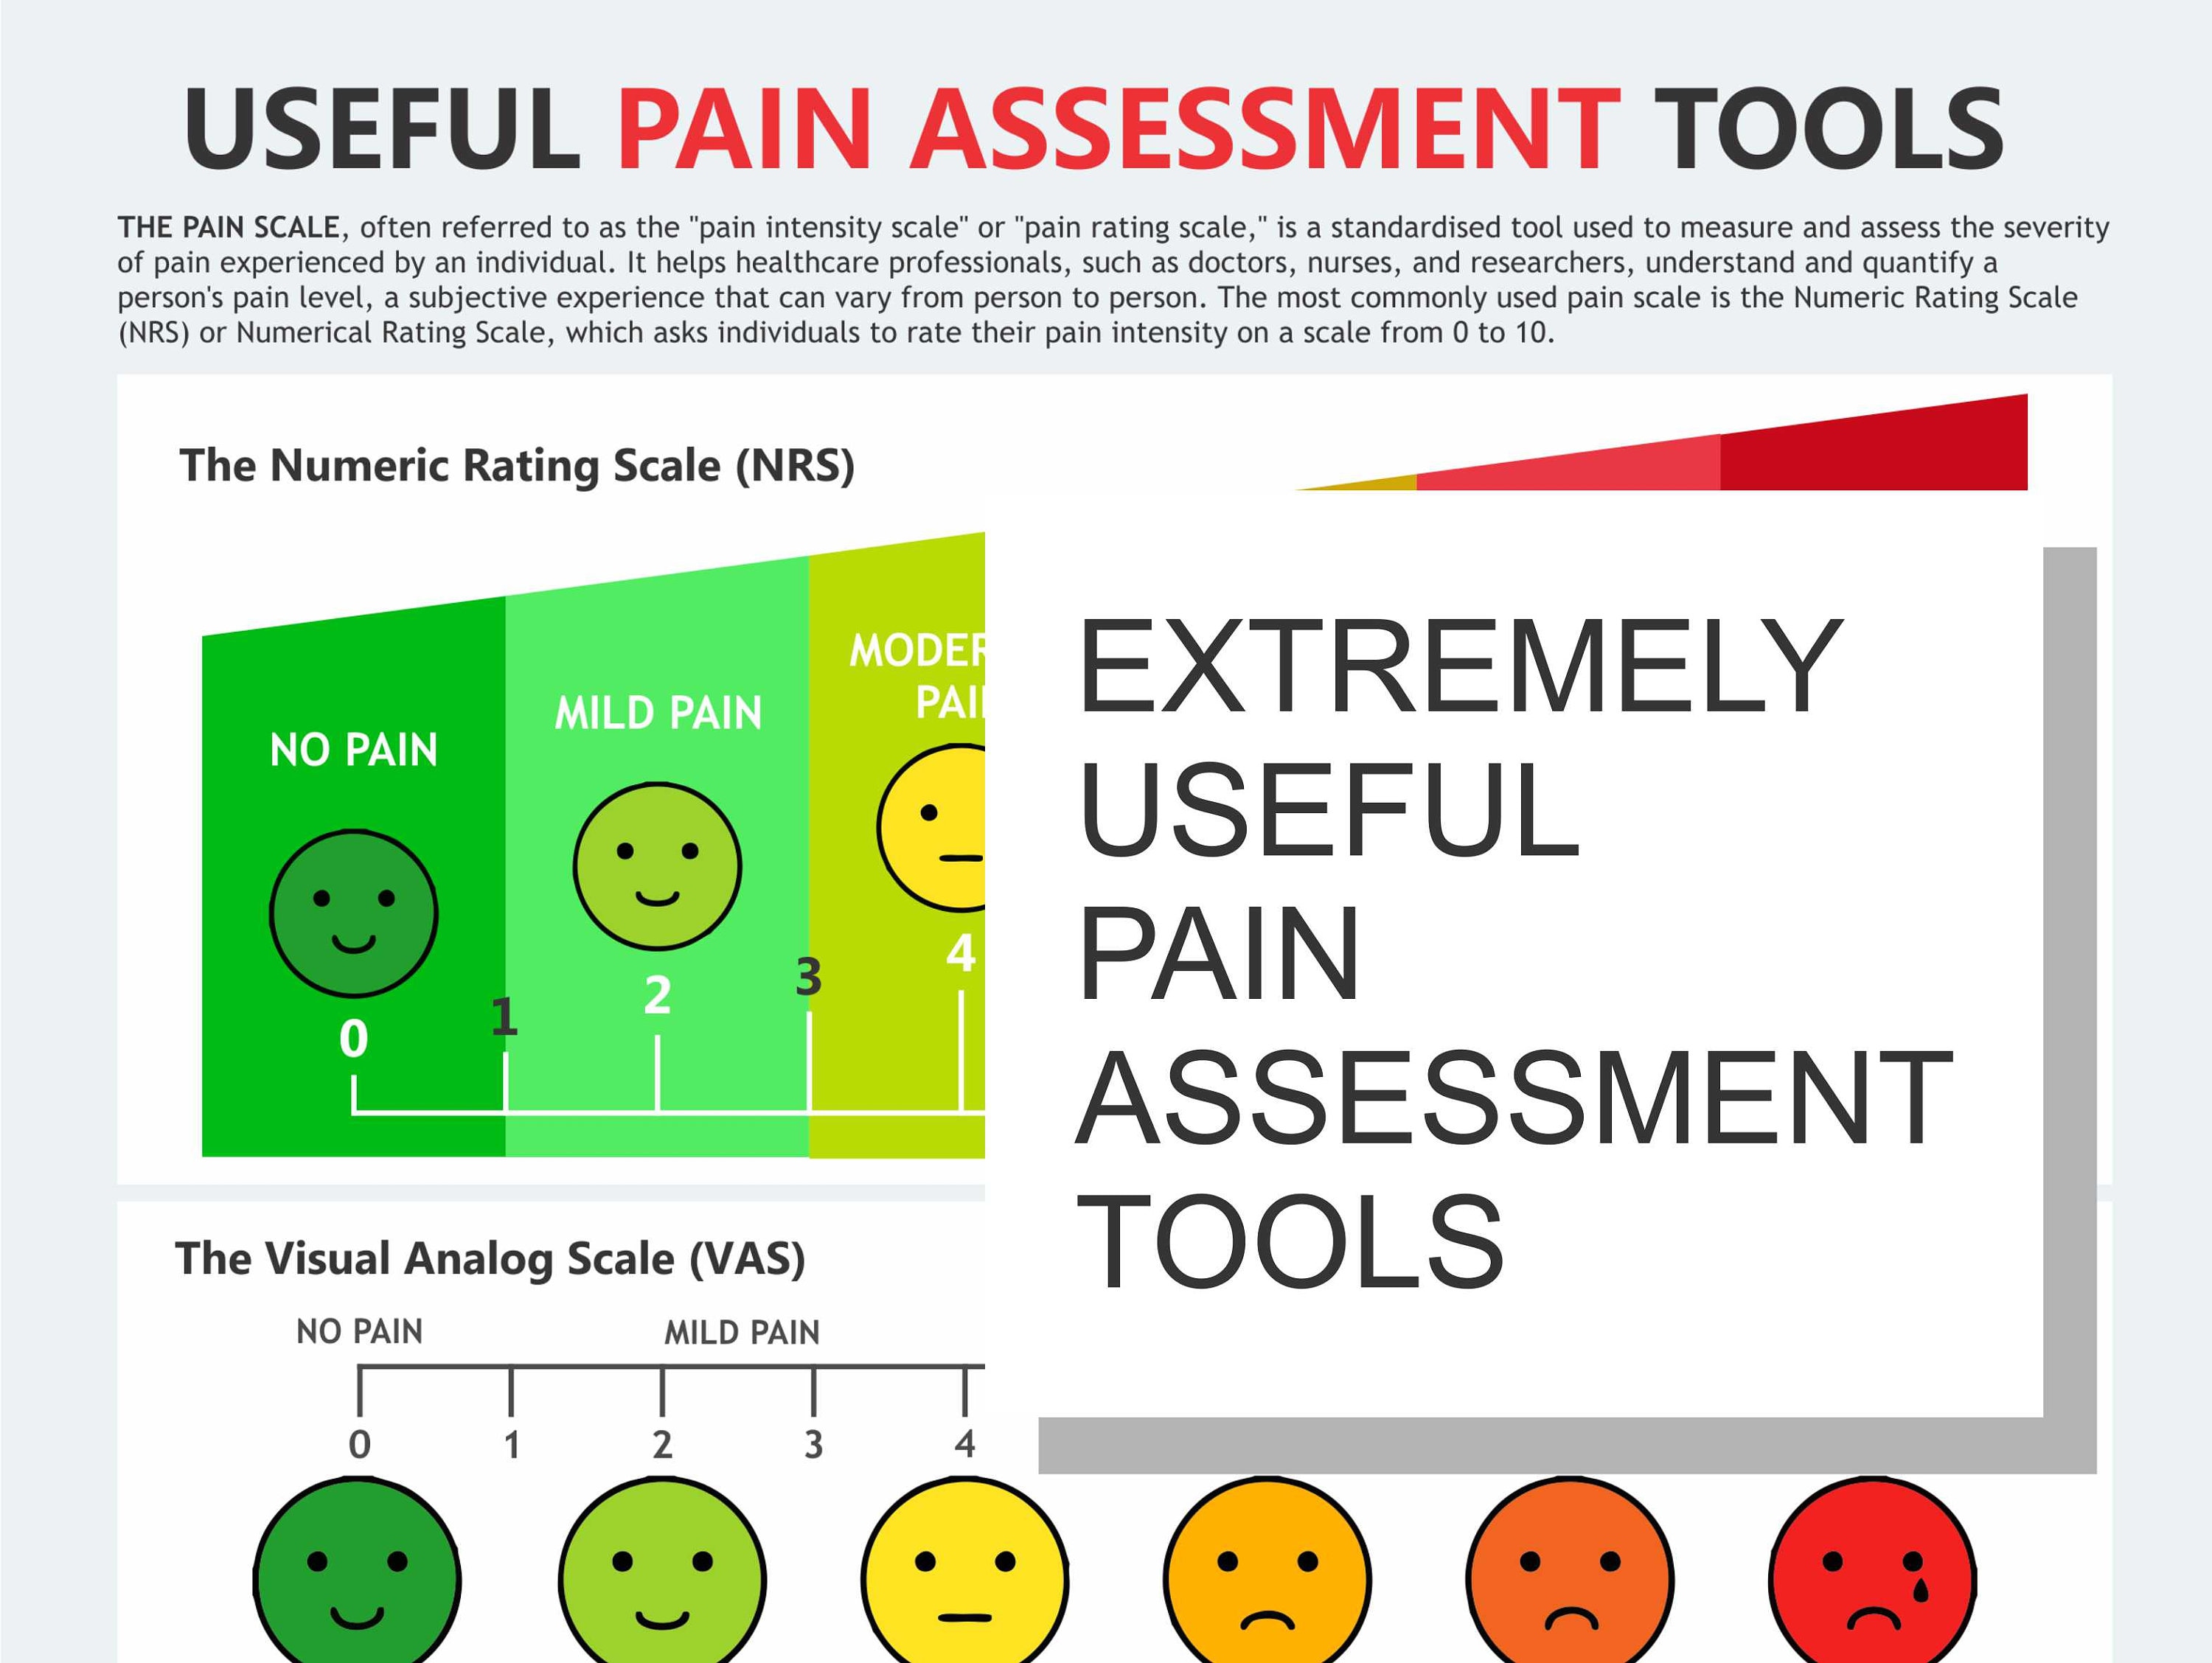
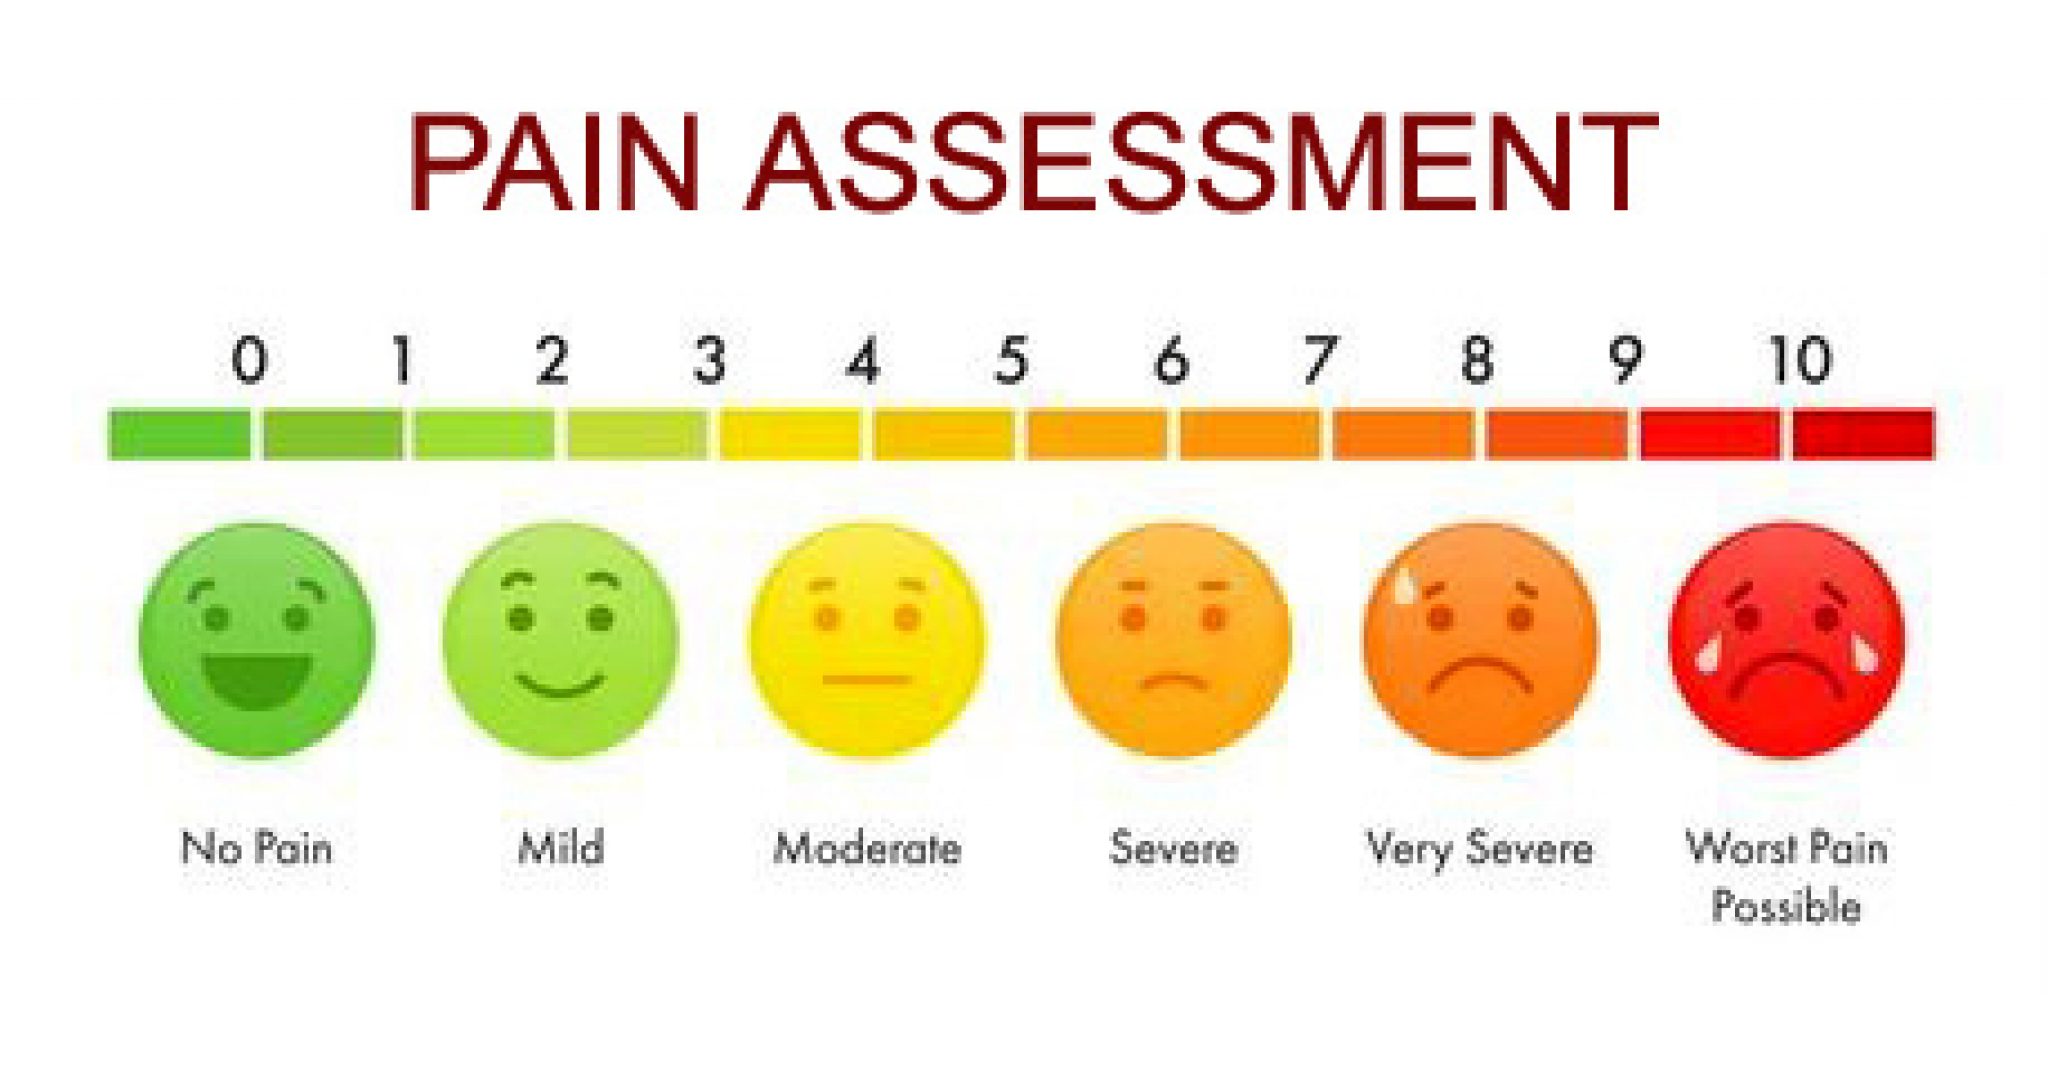
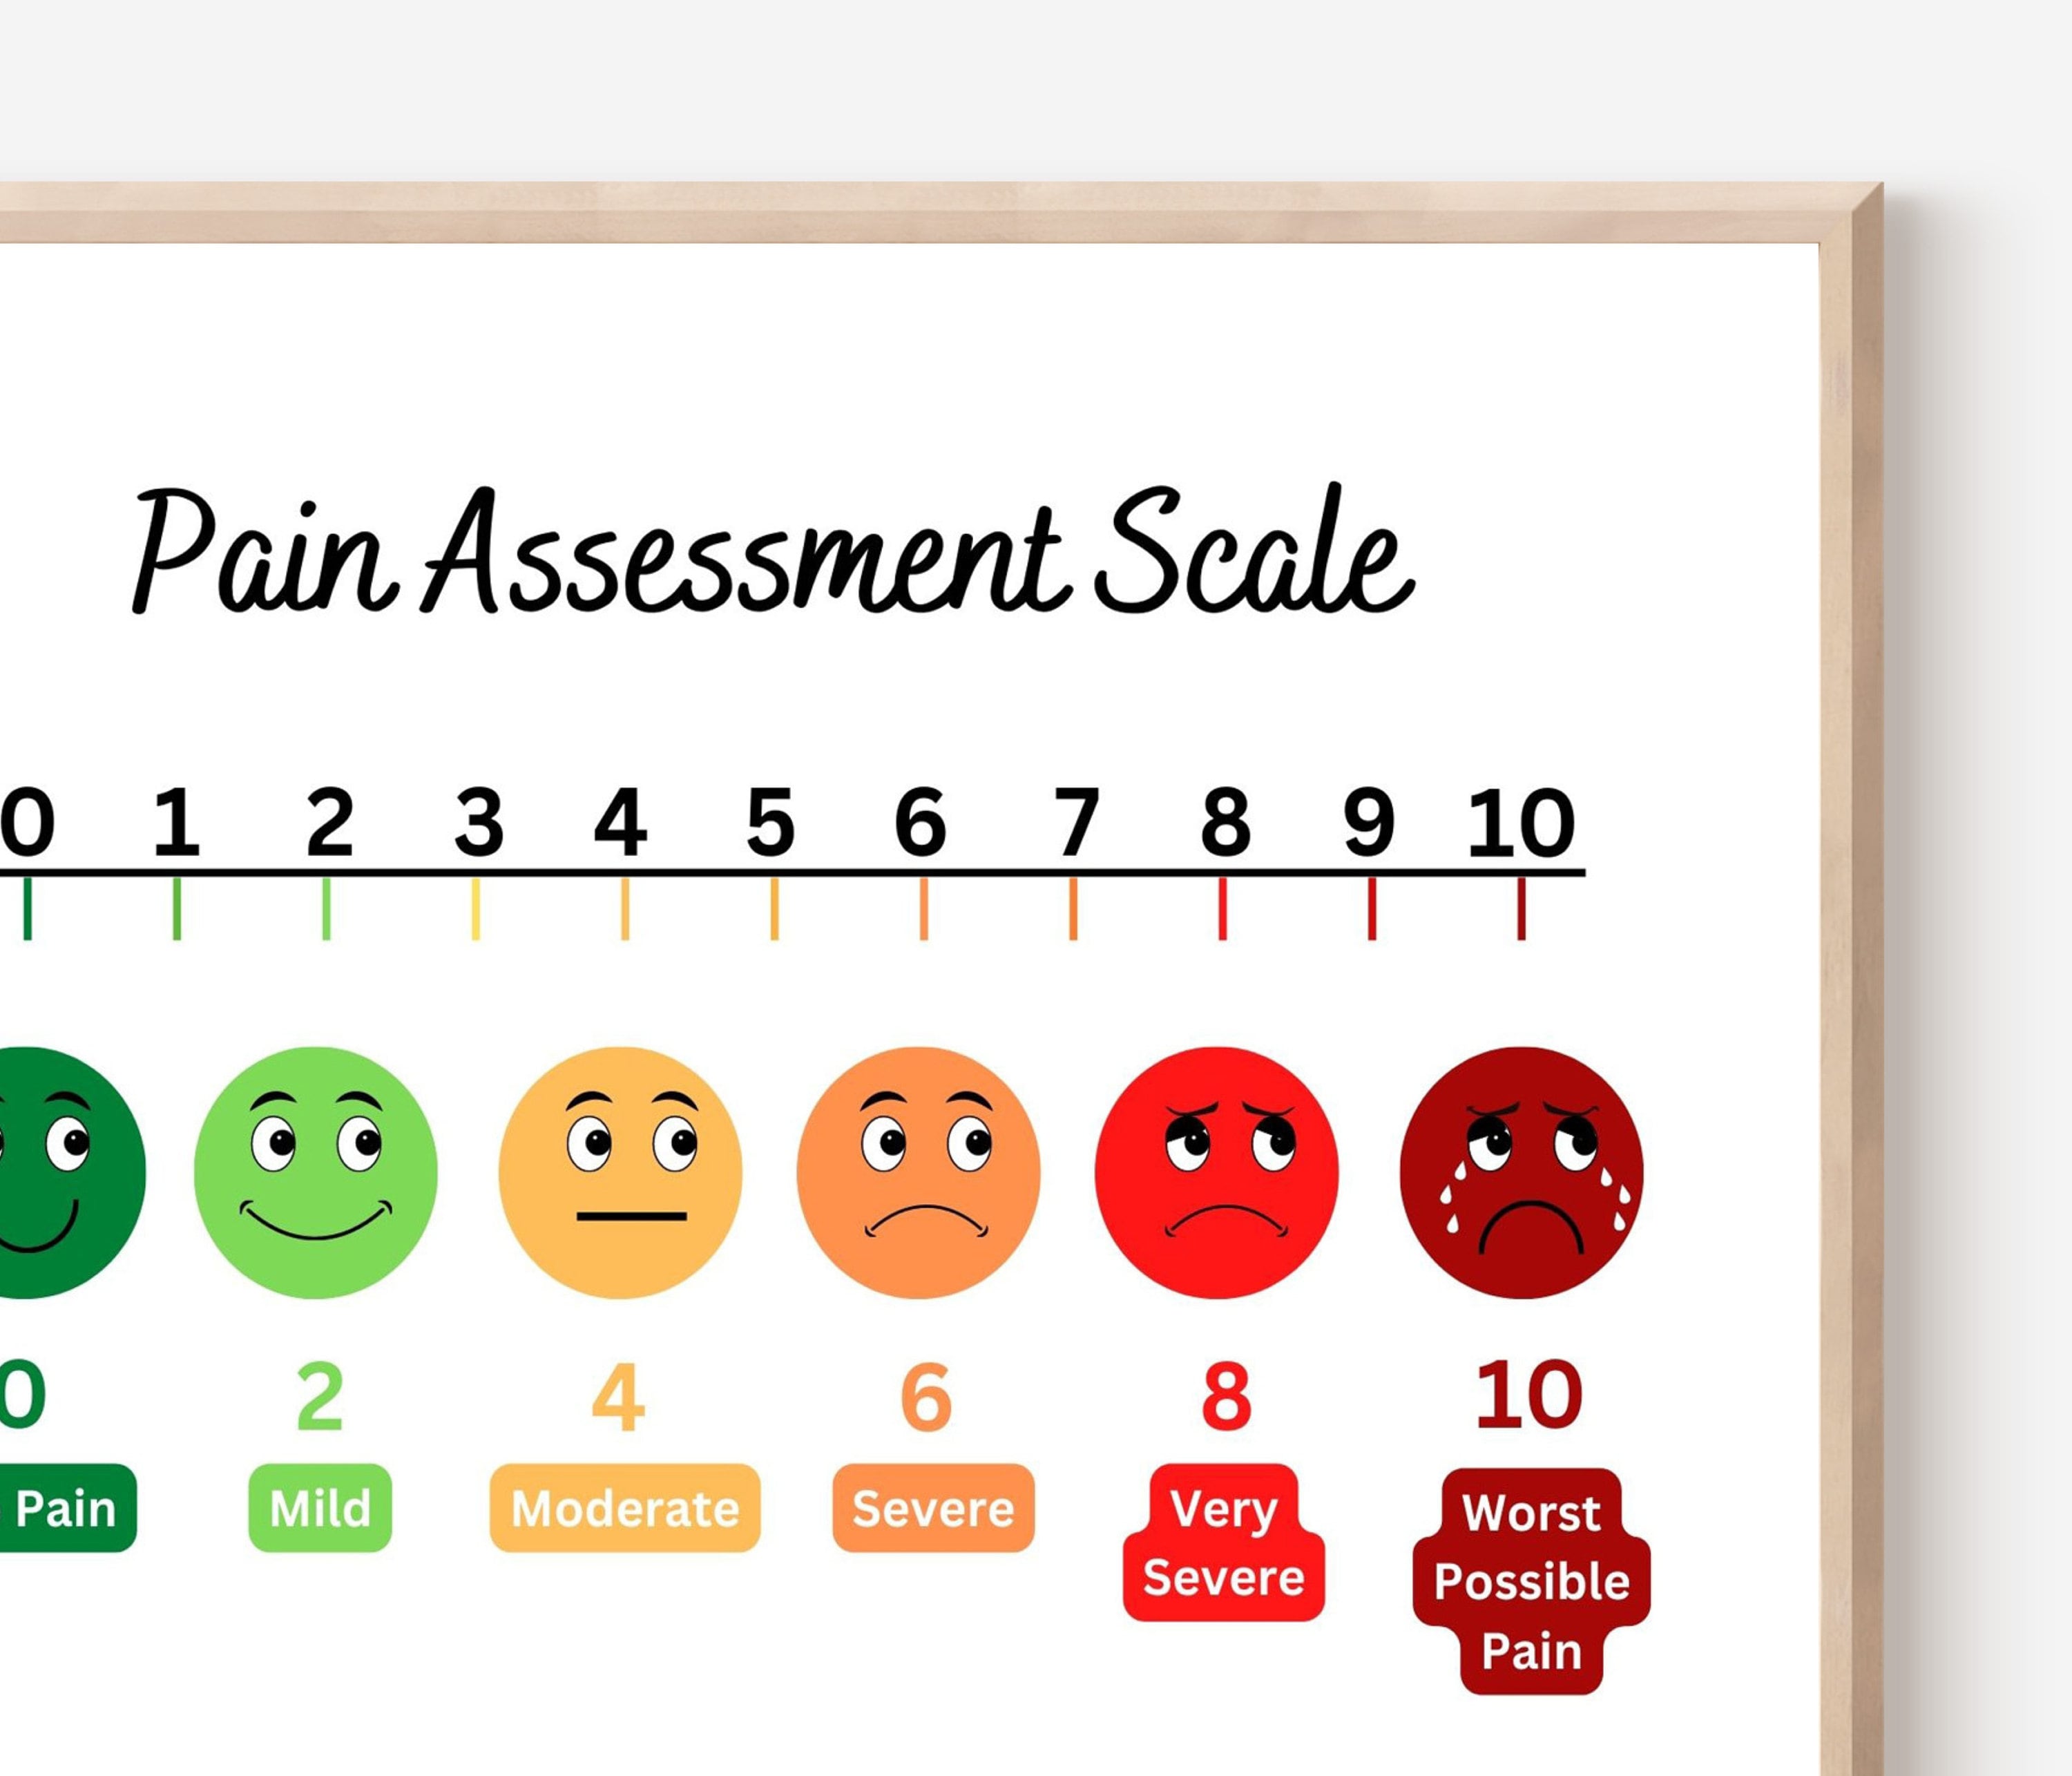
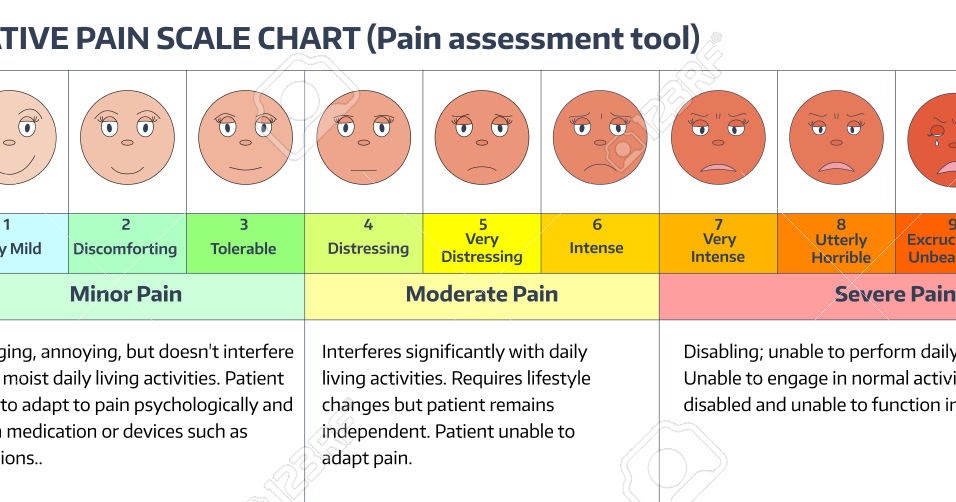
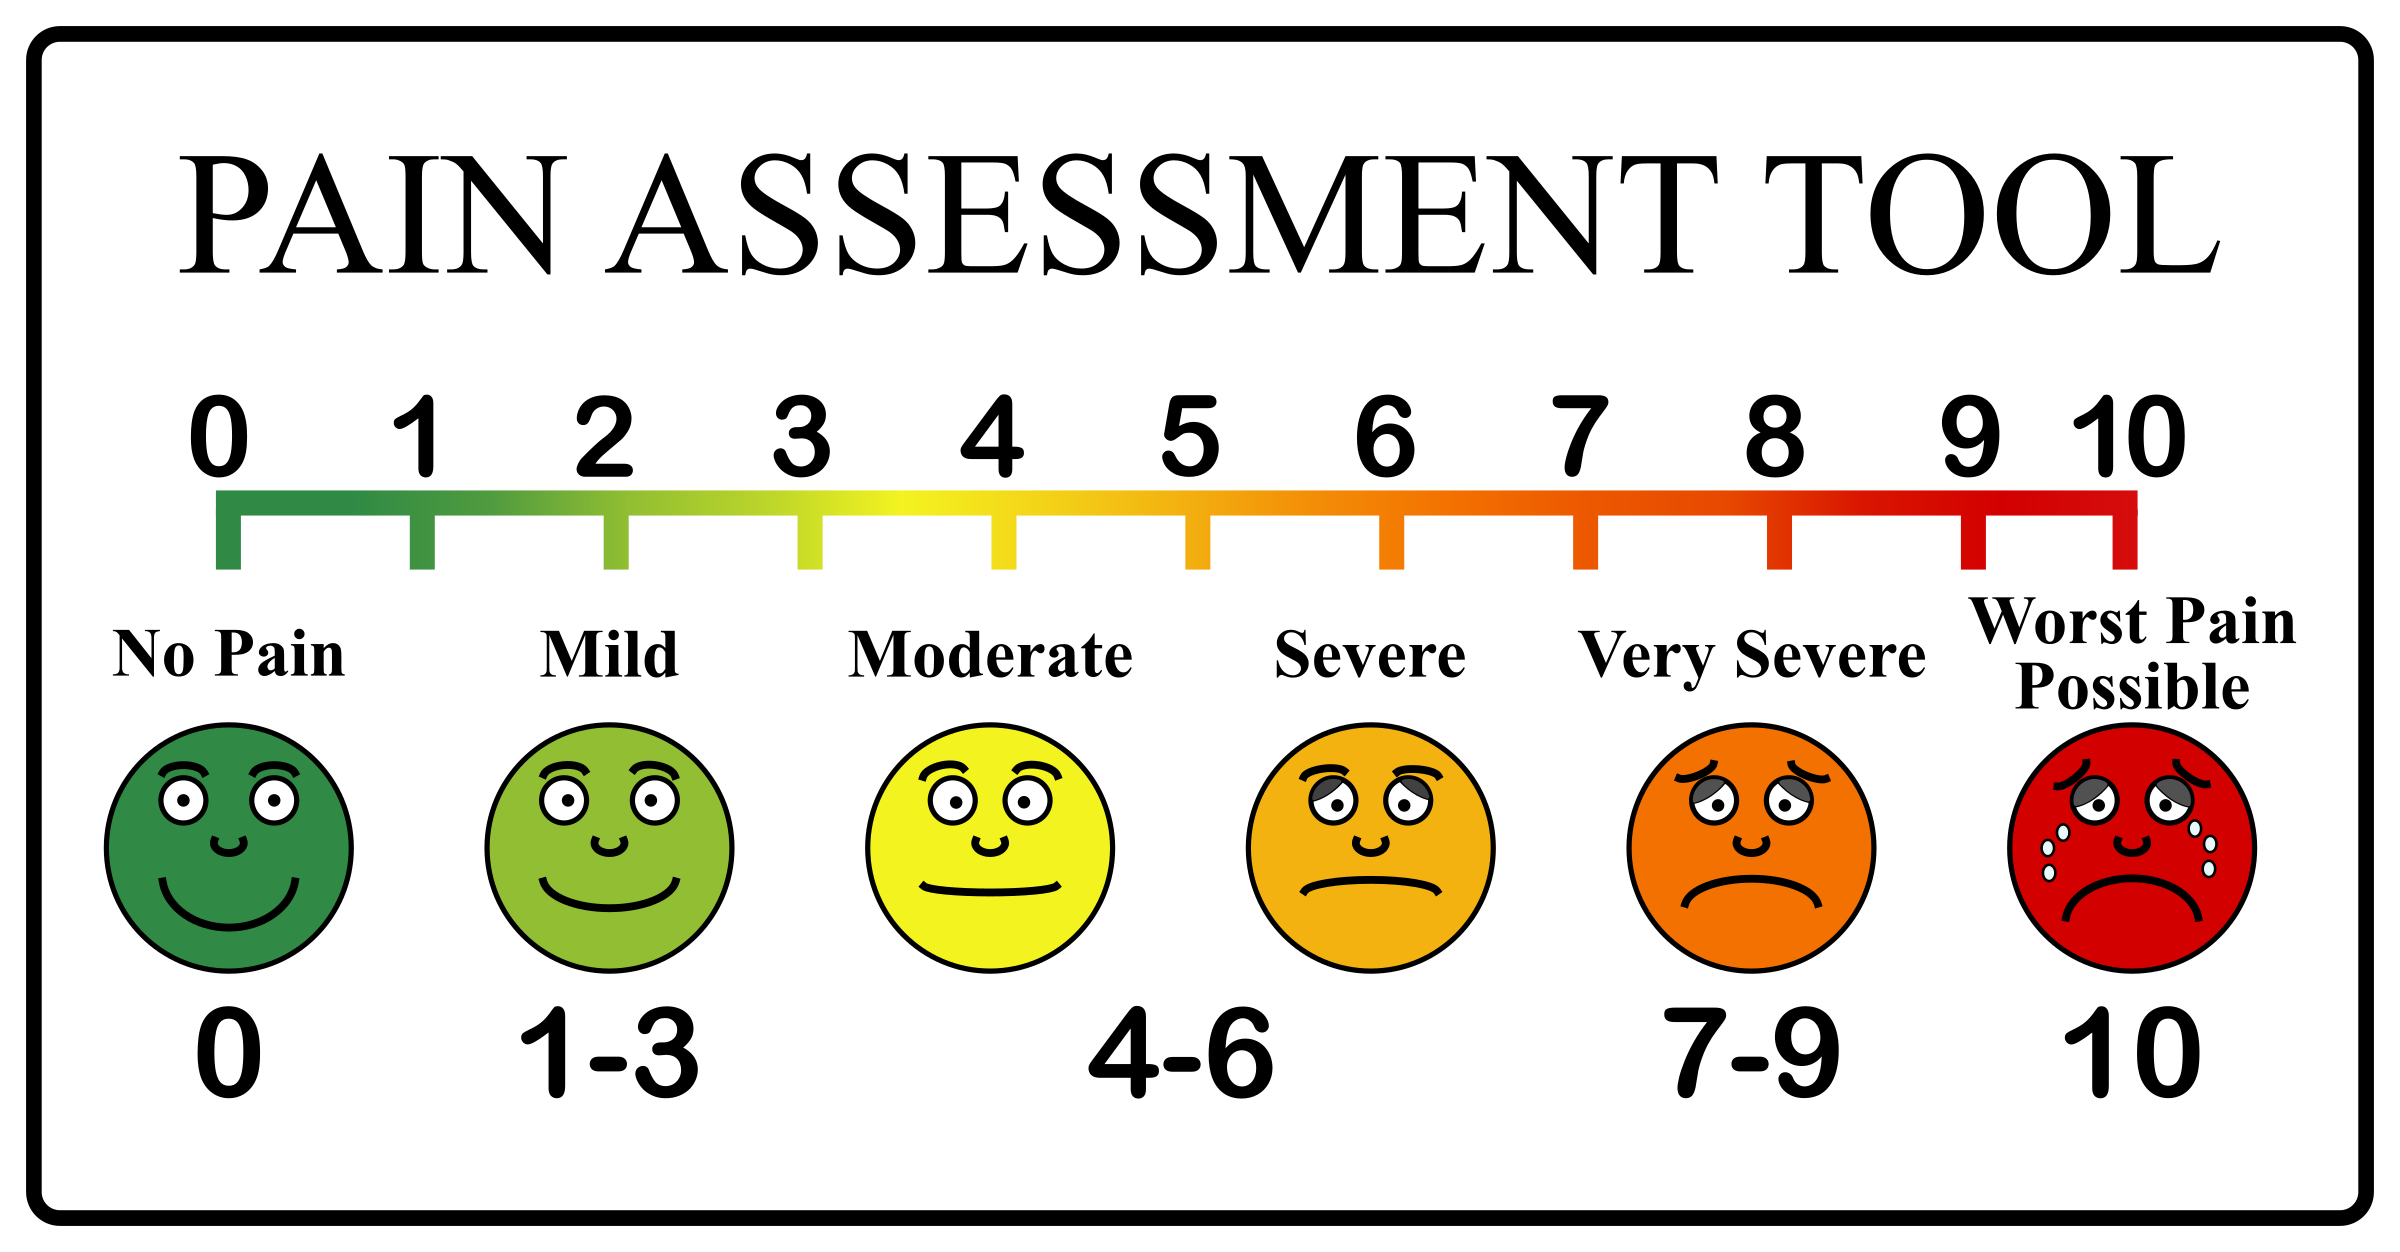
Pain is subjective by definition, which makes its assessment a constant negotiation between patient report and clinical interpretation. The tools exist, but they rarely capture the full picture on their own. What matters more is how you use them together, and when you decide they're not giving you useful information. The Numeric Rating Scale (NRS) runs from 0 to 10. It's the most commonly used tool in clinical settings because it's fast and requires no equipment. A patient says "seven" and you document it. The problem is that "seven" means different things depending on who you're talking to. A chronic pain patient who's lived with severe discomfort for years will often rate a flare-up at a 6 or 7. Someone who's never dealt with significant pain might call a broken rib an 8 or 9. The number itself is meaningless without context about that individual's baseline.
Assessment Of Pain: Beyond The Numbers
The McGill Pain Questionnaire is more thorough but also more time-consuming. It asks patients to select words from lists describing sensory, affective, and evaluative dimensions of their pain. "Throbbing," "shooting," "suffocating," "frightening" — each category maps to different neurological pathways and clinical implications. A patient describing burning and tingling points toward neuropathic pain. Someone reporting aching and heaviness is more likely dealing with nociceptive pain. This distinction changes treatment entirely, which is why the questionnaire exists despite taking 10 to 15 minutes to complete properly. I ran into a situation a few years back where a patient's self-reported pain scores didn't match their functional status at all. They were consistently rating their pain as a 3 out of 10, which would suggest mild discomfort. But they couldn't walk more than fifty feet without stopping, and they were avoiding any movement that involved their affected joint. The standard questionnaires were all coming back as low-severity. What I should have been looking at was the Disability Index component of the Brief Pain Inventory, which I'd been skipping because it took extra time. When I actually filled it out, it showed moderate to severe functional interference. The pain rating of 3 was technically accurate in the moment — they weren't in acute distress at the exact second they answered — but it was completely misrepresenting their actual condition. The workaround was to stop relying on the NRS alone and build the assessment around functional outcomes instead. Documented the discrepancy and adjusted the treatment plan accordingly. That patient ended up responding much better once we targeted the right issues. The Faces Pain Scale revised (FPS-R) uses seven facial expressions ranging from no pain to extreme pain. It's useful for populations that struggle with abstract numerical concepts, though it still doesn't solve the fundamental problem that everyone experiences and expresses pain differently.
What most beginners miss is that consistent serial assessment matters far more than any single data point. One pain score tells you almost nothing. Five pain scores taken at the same time of day, under similar conditions, over the course of a week, will reveal patterns that a single assessment completely obscures. Morning stiffness that improves with movement tells a different story than pain that worsens throughout the day. I've seen people get misclassified because someone grabbed a score at the worst possible moment and treated that snapshot as representative. It isn't. There's also the issue of response shift. Patients recalibrate their internal scale over time based on new experiences. A woman who reports her labor pain as an 8 has a completely different frame of reference than a man reporting post-surgical pain as an 8, even though the number is identical. This isn't about fairness, it's about the reality of human perception. Your documentation should reflect that the number is a relative measure for that specific individual at that specific time, not an absolute quantity.
Get the Full Details
Practical Assessment Of Pain In Clinical Settings
The OPQRST mnemonic covers Onset, Provocation, Quality, Radiation, Severity, and Time. It's taught everywhere and used nowhere near enough in its complete form. Most clinicians hit three or four of the six elements and move on. The ones that take the extra thirty seconds to ask about radiation and provoking factors are usually the ones that catch things they otherwise would have missed. A patient with what seemed like straightforward musculoskeletal back pain who also reports radiation to the anterior chest and relief leaning forward — those details redirect the entire differential. Brief questions do work if you're systematic. The PQRST method is quick, takes about two minutes, and gives you structured data without requiring a formal questionnaire. Start with what provokes the pain, then quality, then region and severity, then timing and radiation. The order matters less than the fact that you're covering all the bases every time instead of winging it. The biggest limitation across every pain assessment tool is cultural and contextual variability. Some populations are conditioned to minimize pain expression. Others are conditioned to amplify it. Neither reflects the true intensity of the experience. In my experience, building rapport before deploying any tool does more for assessment accuracy than any questionnaire design improvement ever will. A patient who trusts you will give you a more honest score than one who suspects you're just ticking boxes for documentation purposes.
For pediatric assessment, the Wong-Baker FACES scale is widely used but has documented reliability issues in children under four. The FLACC scale — Face, Legs, Activity, Cry, Consolability — is better for non-verbal or pre-verbal patients, but it requires observation over time rather than a single snapshot. I've seen it misused as a one-time check, which defeats the purpose. The scoring is only meaningful when you're watching behavioral changes across an encounter, not recording an impression from the doorway. Cognitive impairment presents another hard boundary. Standard self-report tools become unreliable when a patient cannot reliably communicate. The Pain Assessment in Advanced Dementia (PAINAD) scale was built for this population, using breathing, negative vocalization, facial expression, body language, and consolability as indicators. It's imperfect but it's what we have. The caveat is that PAINAD scores can be elevated by agitation that isn't pain-related, so you always need to rule out other causes of behavioral change first. When all the tools fall apart and you're still uncertain about the severity or nature of a patient's pain, the honest answer is often just to document the uncertainty and reassess. There's no shame in that, and it's significantly more common than most people realize.