How NCLEX Scoring Actually Works
The NCLEX uses computerized adaptive testing, which means the exam adjusts in real time based on whether you answer correctly. This is different from a traditional fixed-form test where everyone gets the same questions. Your score isn't a percentage of correct answers. It's a logit value compared against a cutoff set by the National Council of State Boards of Nursing. The system starts you with mid-level difficulty questions. Get one right and the next item gets harder. Get one wrong and it eases up. The algorithm keeps track of where you sit on the ability scale relative to the passing standard. Once it has enough data to be 95% confident you're either clearly above or clearly below that line, it stops. That's the entire mechanism.
Understanding Assessment Score Nclex Results
Your official report shows a binary Pass or Fail. There's no numeric score given to candidates. But behind the scenes, the scoring engine produces a logit measurement. If your logit is above the passing threshold at the 95% confidence level, you pass. If it's below, you fail. The exact cutoff changes slightly over time because NCSBN recalibrates periodically, but it generally hovers around zero logits. For the RN exam, the minimum number of items is 75 and the maximum is 150. For the PN exam, it's 85 to 205. Hitting the maximum doesn't automatically mean you failed. Some people take all 150 items and still pass because the confidence interval only reaches the required threshold at that point. Others finish early and fail because the algorithm determined they were below passing well before the item limit. I ran into a situation a few years ago where a candidate called saying they'd taken exactly 150 questions and wanted to know if that was a failure signal. It wasn't. The real indicator is whether the upper or lower stop rule triggered. When the upper stop rule fires, you've demonstrated sufficient competency. When the lower stop rule fires, you haven't. Taking the full length just means the algorithm needed every available data point to make that determination. I had them check their results dashboard rather than speculate from the item count alone.
The Scoring Mechanics in Detail
The CAT algorithm uses item response theory, specifically the 2-parameter logistic model. Each question has a difficulty parameter and a discrimination parameter. The system selects the next question based on your estimated ability level. It maximizes information at your current estimate, which is why the adaptive path feels so different from a static exam. There are two main runout methods that determine when the exam ends. The first is the Minimum Length Method, or MLM. This applies when you finish between the minimum and maximum items and the confidence interval is already clear. The second is Runout of Length, or ROL. This triggers when you reach the maximum number of items and the algorithm still hasn't reached 95% confidence in either direction. In that case, the exam ends by default and the final ability estimate determines the outcome. Most examinees don't hit ROL. Roughly 85 to 90 percent of candidates end the exam through MLM or the standard stop rules. The remaining portion either clears early by demonstrating consistent high performance or gets pulled to the maximum by borderline performance across many items.
Get the Full Details
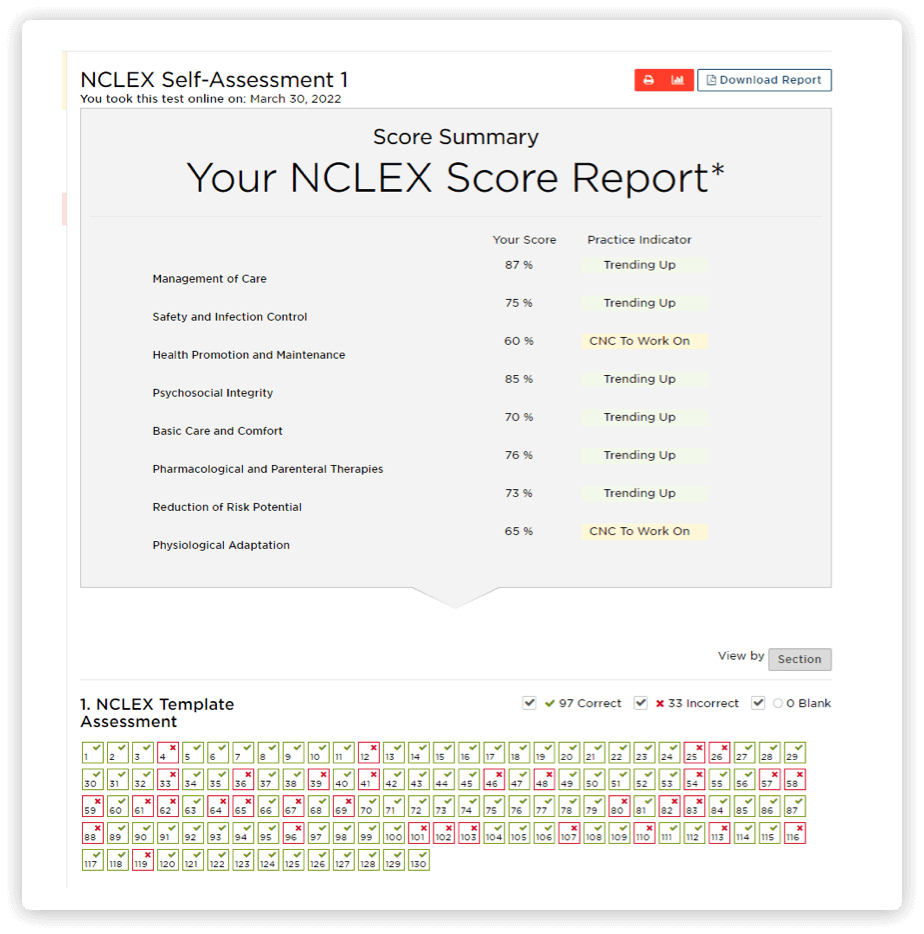
One thing most preparation materials get wrong is the idea that you can predict your result by counting easy versus hard questions. You can't. The adaptive algorithm doesn't reward or penalize you for the difficulty distribution of questions you saw. It only cares about whether your overall estimated ability crosses the threshold with sufficient confidence. Someone who answered mostly hard questions correctly might score the same as someone who got easy ones right and some hard ones wrong. The math collapses it all into one ability estimate. Another counter-intuitive point is that getting a long string of questions wrong at the end doesn't necessarily sink you. If your ability estimate early in the exam was solidly above the passing line, a few late misses won't drag you below it. The algorithm weights the entire test, not individual sections. The opposite is also true. A strong start followed by median performance will likely still produce a passing result. The New York State boards release an unofficial score report through their quick view system for some candidates. This shows a three-digit number where anything above 33 is generally considered passing. Other states may offer similar services through their board websites or third-party score evaluation vendors. The NCLEX.org candidate dashboard sometimes displays additional details depending on your jurisdiction's policies. But the official legal result always comes as Pass or Fail from your nursing regulatory body.
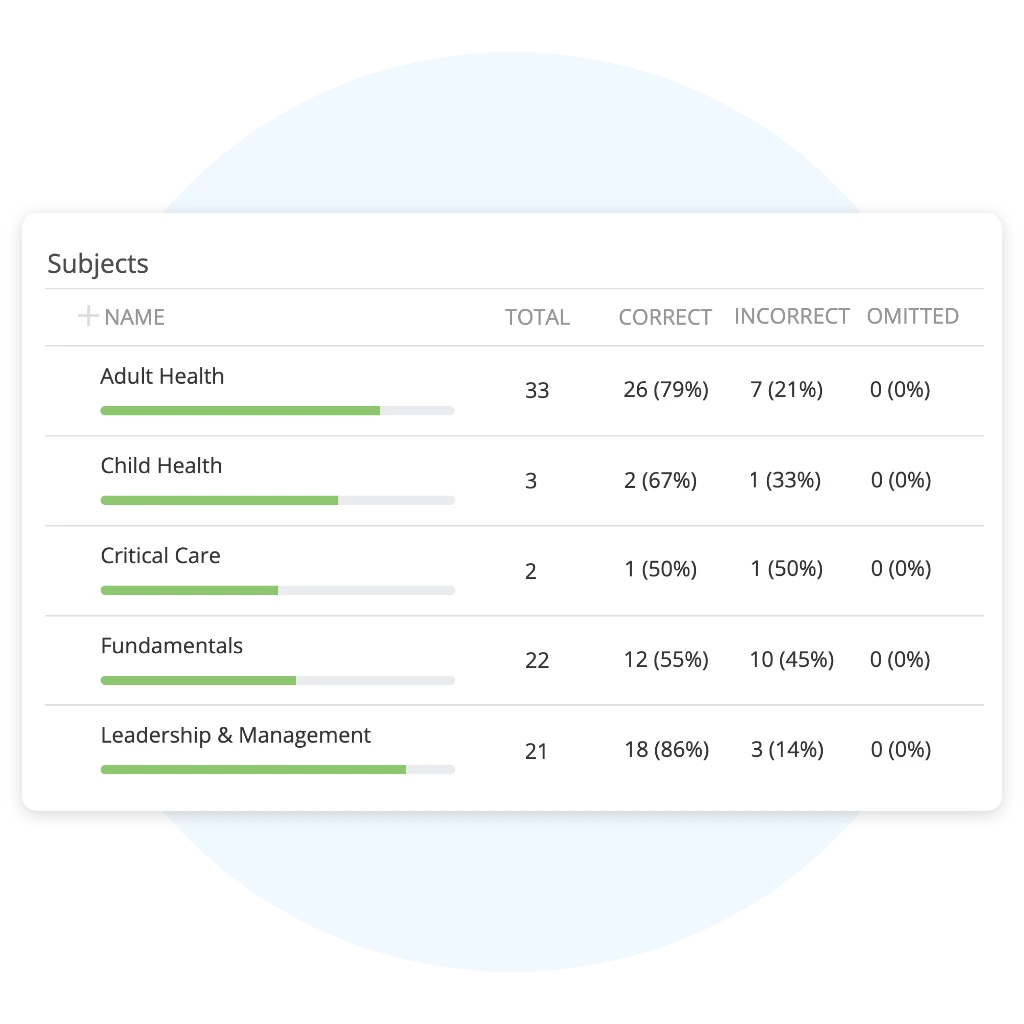
There are real limitations to the CAT scoring model that deserve acknowledgment. The system assumes items function the same way across all populations, which isn't always true. Cultural bias in certain question stems can skew ability estimates for non-native English speakers, though NCSBN does conduct differential item functioning analysis to catch and remove problematic items. The 95% confidence threshold means borderline candidates exist in a gray zone where a different random item sequence could theoretically produce a different outcome. This isn't a flaw in the practical sense, but it does mean the exam isn't perfectly precise at the cutoff edge. If you're analyzing your performance after the exam, focus on question patterns rather than raw counts. Note which content areas felt uncertain, especially pharmacology, prioritization frameworks like Maslow and ABC, and safety-related items. These tend to carry heavy weight in the logit estimation. Avoid obsessing over individual questions you remember vividly. Salient memories don't correlate with scoring outcomes. For anyone who didn't pass, the diagnostic report from your board will break down performance by functional areas. Use it to identify whether the gap is content knowledge or test strategy. Many candidates who narrowly miss the cutoff improve significantly on retake by focusing on question analysis rather than simply studying more material. The difference between failing and passing often comes down to recognizing how the NCLEX frames clinical judgment questions under the latest Next Generation NCLEX format.