Why Dental Charting Takes Longer Than It Should
Most dental assistants spend more time figuring out what codes to use than actually doing the charting. I have seen people pause a clean appointment for seven minutes just to remember which notation goes with a moderate carious lesion versus a suspicious one. The problem is not that charting is difficult. The problem is that there are too many notational systems and very few people consolidate them into something you can glance at during a procedure. This is where an Assisting Dental Charting Cheat Sheet becomes useful, assuming you pick one that is actually built for clinical speed rather than classroom theory.
Assisting Dental Charting Cheat Sheet
A cheat sheet for dental charting is a single-page reference that maps clinical findings to the notation system your office uses, lists the common codes for restorative work, periodontal status, and missing teeth, and gives you the quick rules for how to handle edge cases. The best ones are printed on a clipboard-size card or loaded onto a tablet you can leave open next to the operatory light. Anything larger gets ignored. Anything smaller requires reading glasses and slows you down during active procedures. You need it to answer questions fast. During a recall exam you are not thinking about the FDI numbering system. You are thinking about whether that proximal decay in tooth 14 gets marked as a suspected lesion or a confirmed one, and what code goes with it if you end up referring for an amalgam vs composite. A well-structured cheat sheet organizes this in a way that mirrors your workflow. The three systems you will encounter are Universal, Haderup, and FDI. Most general practices in the US use Universal. Pediatric and some specialty offices may use FDI. The cheat sheet should show you the conversion table on one panel. Keep it there. I do not care that you memorized it. You will still forget whether tooth 30 is U or L on a bad day, especially after a lunch break when you are juggling four recall charts in a row.
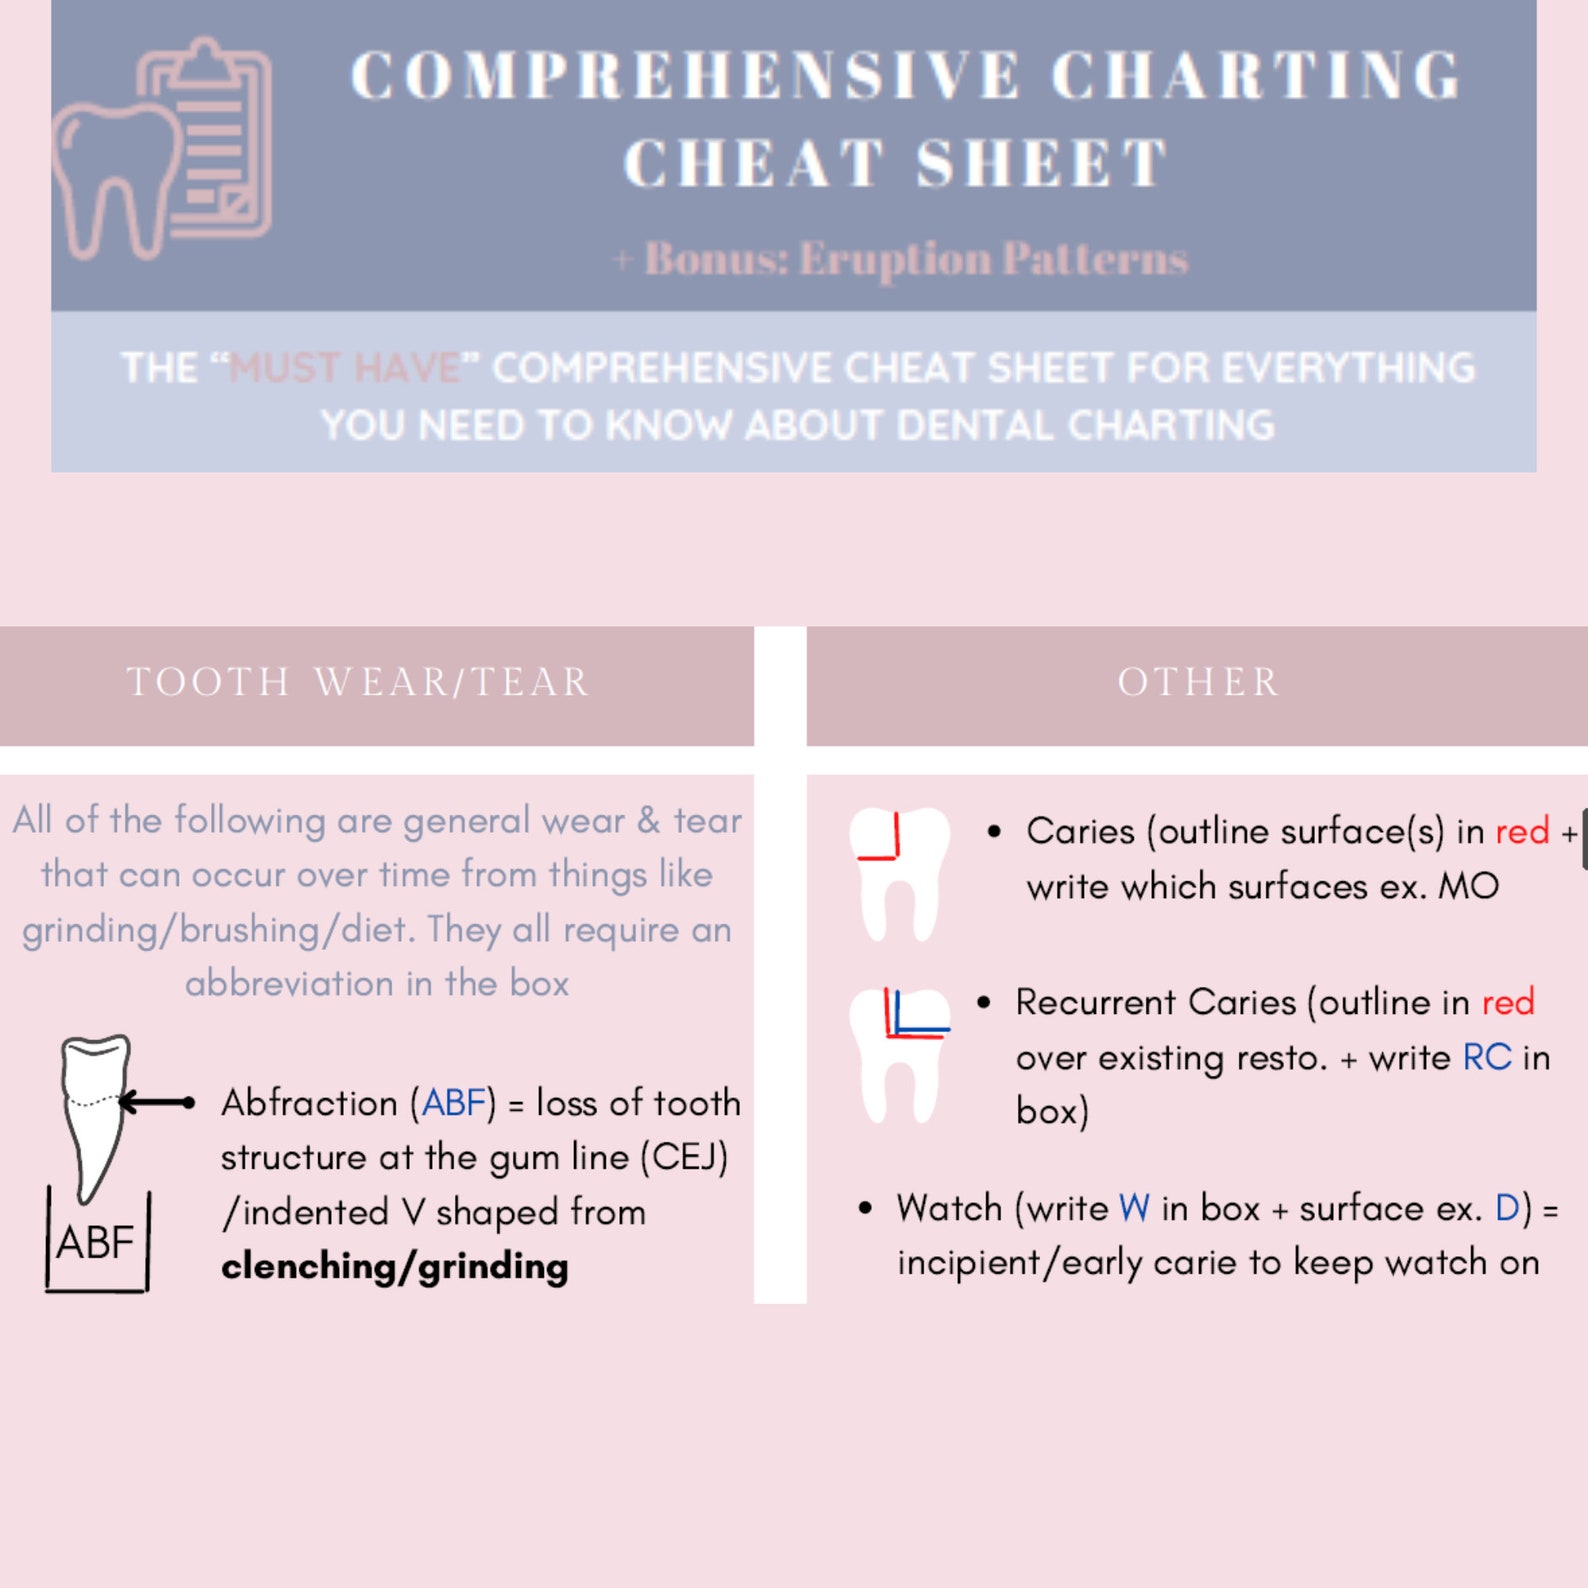
Your cheat sheet needs a quick-reference section for the most common findings, not every finding in the textbook. Build it around the data you actually chart. This usually means: If your office also charts bruxism attrition, clenching marks, or mucosal lesions, add those rows. Do not add rows for things you never document. A crowded cheat sheet is slower than a short one because your eye has to search longer. Start with whatever template your provider prefers. Most dentists use a standard form that already has checkboxes or boxes for sextant charts, bitewings, and restoration tracking. Copy that layout and fill in the blank areas with the codes and symbols you actually need. Then trim anything redundant.
Get the Full Details
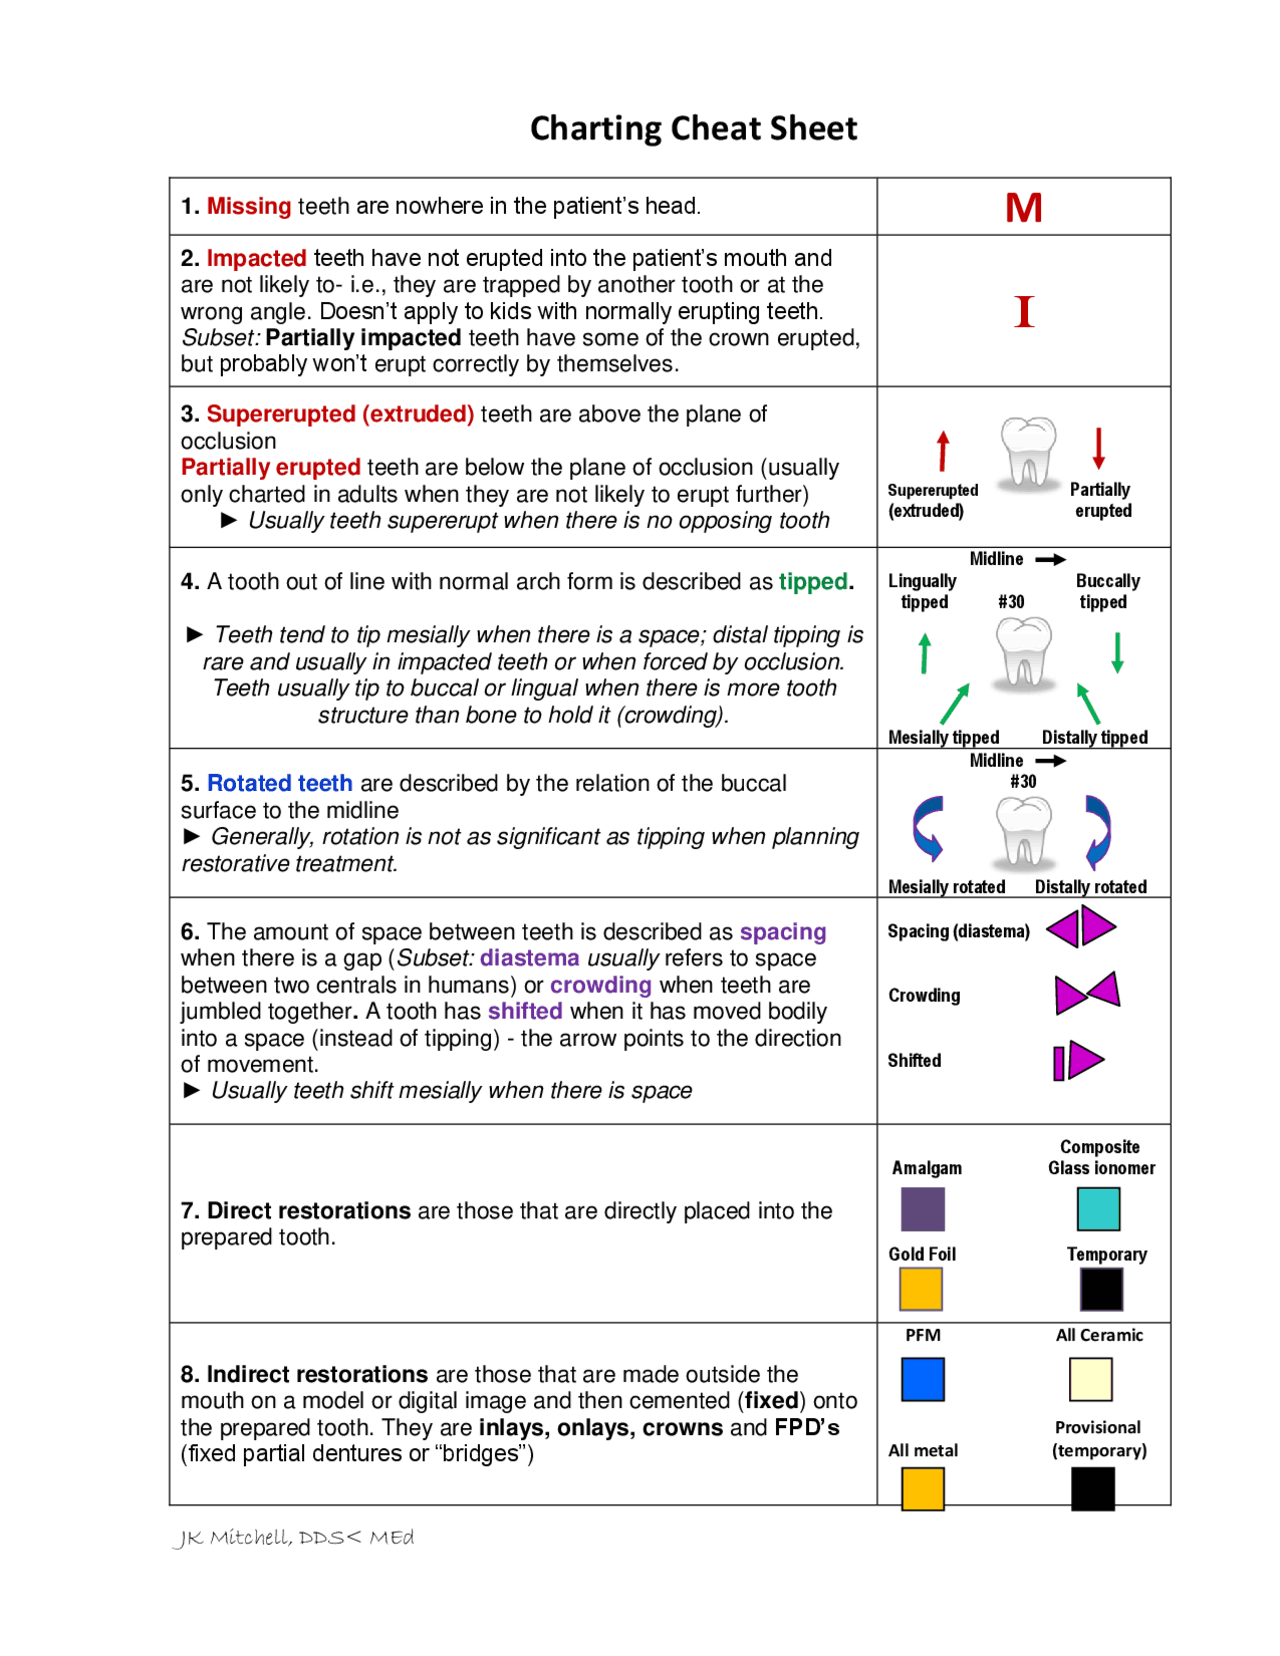
I keep mine laminated at the chairside. The version I use now is roughly three years old. It started as a Word doc, got converted to a two-column printable PDF, then moved to a tablet once our practice went fully electronic. The content barely changed. The format did. Here is a practical breakdown of what to include based on real operatory use:
Restoration Codes
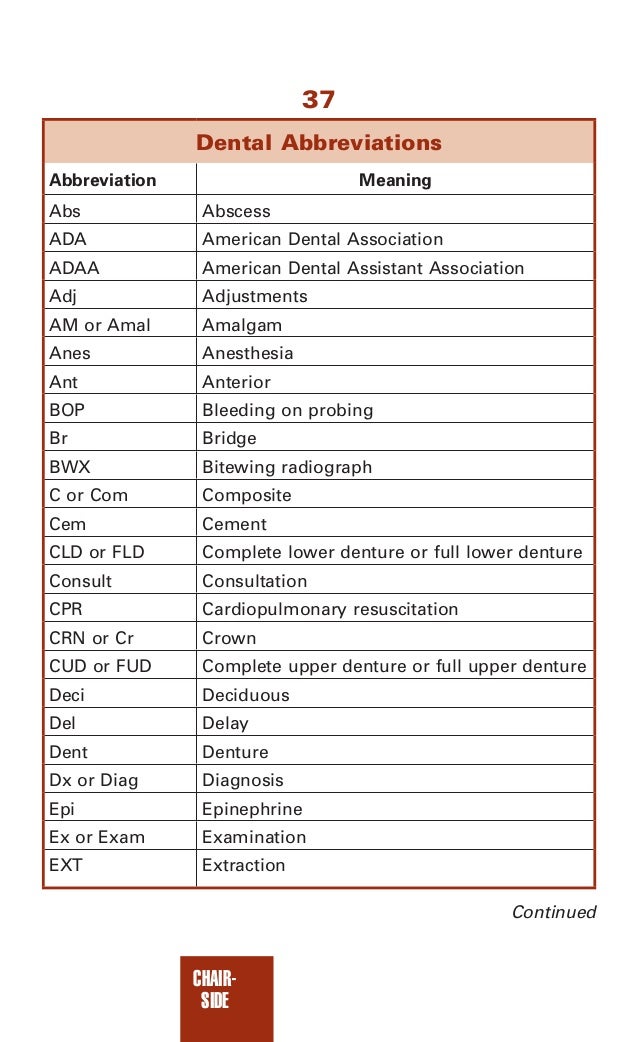
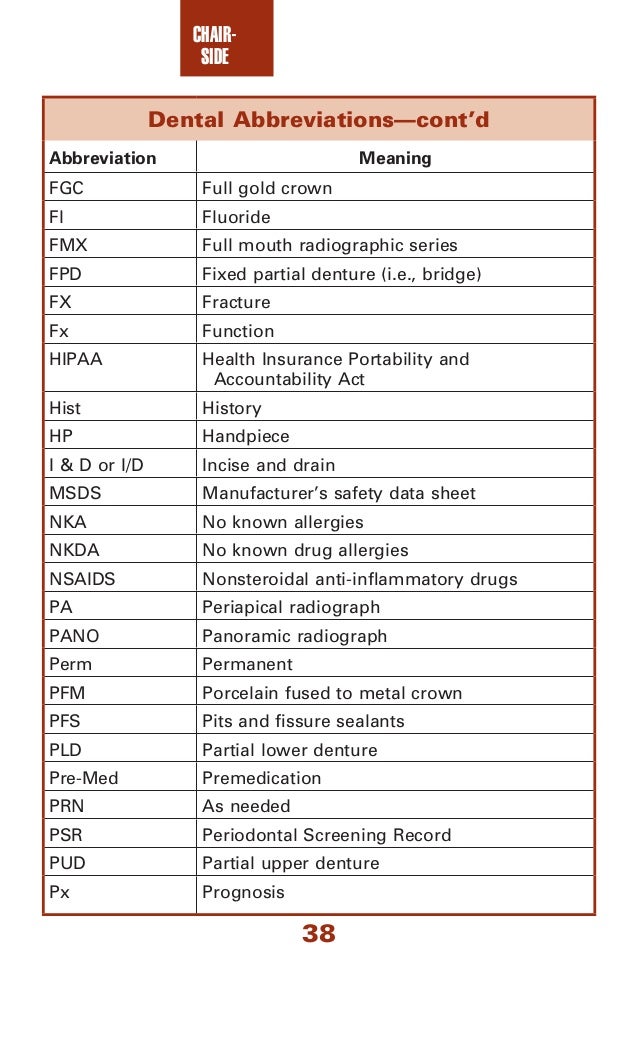
List the common abbreviations and what they mean in your notation system. FO, DO, MO, MOD, BO, AO. Add the material codes if your chart requires them, such as G for amalgam, C for composite, I for inlay, O for onlay, and E for ceramic. Include a quick note that some offices prefer letters like A for amalgam and R for resin. Match it to your software default so you stop second-guessing yourself mid-exam. Put the BPE or CPITN band thresholds on the page. Band 1 is under 3.5 millimeters. Band 2 is 3.6 to 5.5 millimeters with possible calculus. Band 3 is 5.6 to 8.5 millimeters. Band 4 is over 8.5 millimeters. If your practice uses six-point pocket charts, add a row that flags when a site crosses into surgical referral territory. Most people skip this part and then get confused when a periodontist asks why a 9-millimeter pocket was not flagged on the initial chart. Add a small section for implant numbers, bridge abutments, and removable partial denture clasps. Implant notation is inconsistent across EHR platforms, which is why this section exists. Write down how your practice numbers implants. If your system uses a separate implant chart, note that on the sheet so you stop trying to force an implant code into the tooth column.
About two years ago I ran into a situation with a patient who had a #3 amalgam and a #1 composite on the same tooth, plus a fractured cusp that needed evaluation. The chart made it look like the tooth had three different restorative statuses at once. My original cheat sheet had no section for combined restoration types, so I spent three minutes trying to remember whether I should list the primary restoration or the secondary one, then missed noting the fracture entirely until the hygienist called it out later. That cost us a whole extra minute of chair time and annoyed the dentist because the recall note looked incomplete. My workaround was simple. I added a combined restoration row that used a slash notation, like 3/1 for amalgam over composite, and reserved a separate symbol for fractures. I also added a rule that any cusp involvement gets its own abbreviation so it does not get buried under the restoration code. Now I write #3/1C in the restoration box and put a small triangle symbol in the adjacent fracture field. It takes two seconds to fill out and reads clearly on the EHR screen.
Common Pitfalls That Make Cheat Sheets Useless
Most of the ones I see in break rooms are useless because they are copied from a textbook or a vendor website and printed without adjustment. A few patterns repeat constantly. First, people include every possible code instead of the ones they actually use. I once found a laminated card in a clinic that had 40 codes for root canal therapies alone. Nobody in that office ever treated endodontics. The card was 8 inches wide and took up half the instrument tray. The assistant never used it. Second, people do not match the cheat sheet to their EHR screen layout. If your software asks for an arch, a quadrant, and a tooth number, but the cheat sheet organizes by tooth surface, you will lose time flipping back and forth. Build the layout to match the data entry flow, not the textbook.
Third, people ignore updates. Code sets change. ADA adds new surface modifiers. Your software vendor patches the charting module twice a year. If your cheat sheet was printed before those changes, it becomes a liability. I update mine every time the practice switches EHR versions. It takes about ten minutes.
Advanced Nuances Beginners Miss
Here is something that does not show up in the beginner manuals. Charting is not just about recording the current state. It is about creating a timeline that a provider can read later without reconstructing the whole chart from scratch. A good cheat sheet includes shorthand for historical comparison, such as how to mark a tooth as stable, improved, or deteriorated since the last visit. Most assistants skip this because it feels optional. It is not optional. When you are charting a moderate reduction in pocket depth from 5 to 4 millimeters at tooth 19, the notation tells the provider whether the previous 5 was documented and whether the site was previously flagged for SRP. Without that context the progress looks random. Another thing people get wrong is the relationship between bitewing findings and clinical charting. Bitewings often reveal interproximal caries that the visual exam misses. A complete cheat sheet shows you how to cross-reference a bitewing diagnosis into the clinical notation. I usually add a small note next to each tooth that indicates whether the finding came from the bitewing or the explorer. This matters during insurance audits because the payer expects the radiographic evidence to match the chart notation.
Where This Approach Fails
I should be honest about the limitations. A single-page cheat sheet does not replace knowledge. It speeds up recall, but it cannot teach you periodontal staging, occlusal analysis, or the clinical decision-making that determines whether a finding is suspicious versus confirmed. If you rely on the sheet alone and skip the actual assessment steps, you will miss pathology. I have seen assistants who treat the cheat sheet like a crutch and stop checking the lingual surfaces or failing to record free attachment levels because the sheet says they only need to note the pocket depth. That is a documentation error and a clinical risk. It also breaks down in complex cases. Full-mouth rehabilitation patients, orthognathic cases, and medically complex patients often need customized charting workflows that no generic sheet can cover. In those situations you need a provider-created checklist or a custom EHR template. A cheat sheet is a shortcut for routine exams and recalls. It is not a substitute for case-specific documentation protocols.
What to Do Instead When a Cheat Sheet Is Not Enough
If your practice handles a high volume of complex restorative work, consider building a role-specific quick guide instead of a general cheat sheet. Split the reference into hygiene-focused, restorative-focused, and emergency-focused panels. Each panel covers the notation rules most relevant to that procedure type. This keeps the card lean and lets you hand the appropriate panel to the right team member. Another option is to integrate the cheat sheet into the EHR as a tooltip or a collapsible sidebar. Some platforms support this. If yours does, you get the reference without removing your eyes from the screen. It reduces the physical handling time by about thirty seconds per chart, which adds up over a busy afternoon.
Download and Setup Guidance
I do not host files directly, but the files I reference here are available through the Sapiens AI portal under the clinical resources section. The downloadable version is formatted for letter-size printing and comes in two variants: a clipboard-friendly single-page version and a foldable card version. Both are editable so you can adjust codes to match your software. To set it up quickly, print the single-page version on cardstock and laminate it. Place it on a magnet strip attached to the operatory light arm or on a clipboard mounted near the computer station. Replace it whenever the EHR updates the code set. Expect about five minutes of maintenance every six months. If you want the foldable card, cut along the dashed lines and fold it into a quadrants size that fits in a pocket. It survives glove use better than a clipboard card because it does not catch on instruments.

Final Practical Notes
Keep the cheat sheet visible but out of the patient's direct line of sight. Students and new assistants often hold it up too prominently and make the patient self-conscious about the codes. A subtle placement on the instrument tray works better. Train the front desk to know where it lives so they can point you at it during handoffs without disrupting the flow. Use it during the first month of any new hire orientation. Pair it with live charting examples from real patients. Watching someone fill out a chart while referencing the sheet builds muscle memory faster than reading the sheet alone. I typically run a mock exam where the assistant charts a simulated patient using only the reference card. It takes about twelve minutes and reveals which sections are confusing before the person sees their first live recall. The cheat sheet is a tool, not a strategy. It works when you treat it as an operational aid and ignore it when the case demands deeper documentation. That balance matters more than the content on the page.

