How Automated Neuropsychological Assessment Metrics Actually Work in Clinical Practice
I've spent more years than I care to count working with cognitive assessment tools, and there's a gap between how these systems are presented in papers and how they perform when you're actually administering them. The phrase "automated neuropsychological assessment metrics" gets thrown around a lot, but the reality is messier. Let me walk you through what I've learned the hard way.Understanding Automated Neuropsychological Assessment Metrics Anam Systems
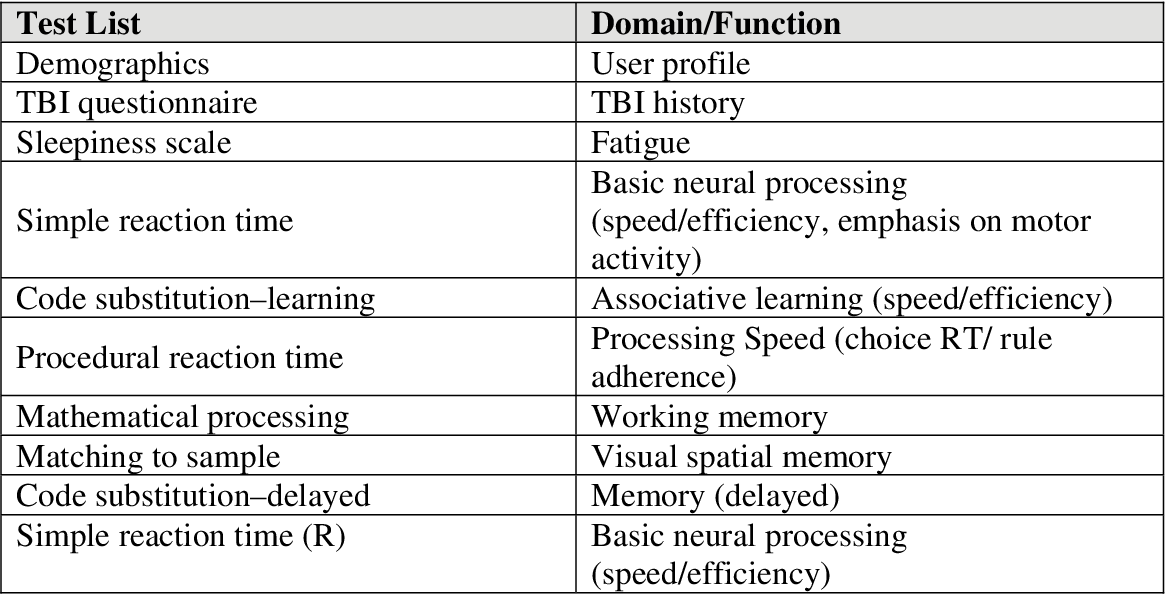
ANAM stands for Automated Neuropsychological Assessment Metrics. It's a family of computerized cognitive tests originally developed for military use, designed to measure things like reaction time, memory, attention, and problem-solving under standardized conditions. The promise was always clean: remove human scorer bias, get reliable data faster, track changes over time. In practice, it's more nuanced. The core system includes tests like the Digit Vigilance test (how long you can maintain focus on a visual target), Coding (processing speed), Memory Comparison (working memory), Response Velocity (how fast you respond to changing rules), and Reasoning (problem-solving). Each produces a score, and those scores can be compared against normative data. That part works fine. Here's what the manuals don't always emphasize: normative data for these tests tends to be skewed toward younger, healthier populations. If you're using ANAM to assess someone older than the reference group, or someone with different educational backgrounds, your metric interpretations might be off by quite a bit. I learned this the hard way when a client's "decreased" scores were actually normal for their demographic but flagged because the norms didn't account for age-related changes in processing speed.One practical tip: always check what normative sample your particular ANAM version uses. Some versions have updated norms from 2003, others from 2015, and the differences matter when you're tracking decline over time. A 10-point drop on one version might mean something entirely different on another.
The Real Workflow: From Administration to Interpretation
Setting up ANAM isn't as simple as installing software and starting a test. I've seen people waste hours because they didn't account for keyboard latency, monitor refresh rates, or environmental factors that silently degrade data quality. Let me walk through the process. First, you need a proper testing environment. The room should be quiet, with consistent lighting. The chair and desk setup matters more than you'd think—if the keyboard is too far or the mouse requires an awkward grip, you're measuring physical discomfort rather than cognitive ability. I once spent two days troubleshooting what I thought was deteriorating cognitive function, only to discover the testing station had been moved to a desk with a wobbly keyboard tray. That subtle instability added about 50 milliseconds to every response, enough to skew the results significantly. When you run the tests, pay attention to the practice trials. Some versions give you three practice trials before the actual test starts. Don't skip them, even if the participant seems to understand the instructions immediately. Those practice runs establish a baseline reaction time and help identify any motor or comprehension issues that would contaminate the scored trials. The data output is typically a set of raw scores, T-scores, and percentile ranks. T-scores below 40 or above 60 usually warrant further investigation, but don't jump to conclusions based on a single test session. I've seen people with temporarily elevated stress levels produce scores that looked pathological on first pass but normalized within a week. The metric itself doesn't tell the whole story.Here's a counter-intuitive insight: sometimes the most useful ANAM metric isn't the overall score but the variability between trials. A person might average "normal" scores across all tests, but show huge swings from Trial 1 to Trial 3 on the same task. That inconsistency can be more informative than a low average, especially for conditions like ADHD or mild traumatic brain injury where attentional control fluctuates.
Common Pitfalls and When to Use Alternatives
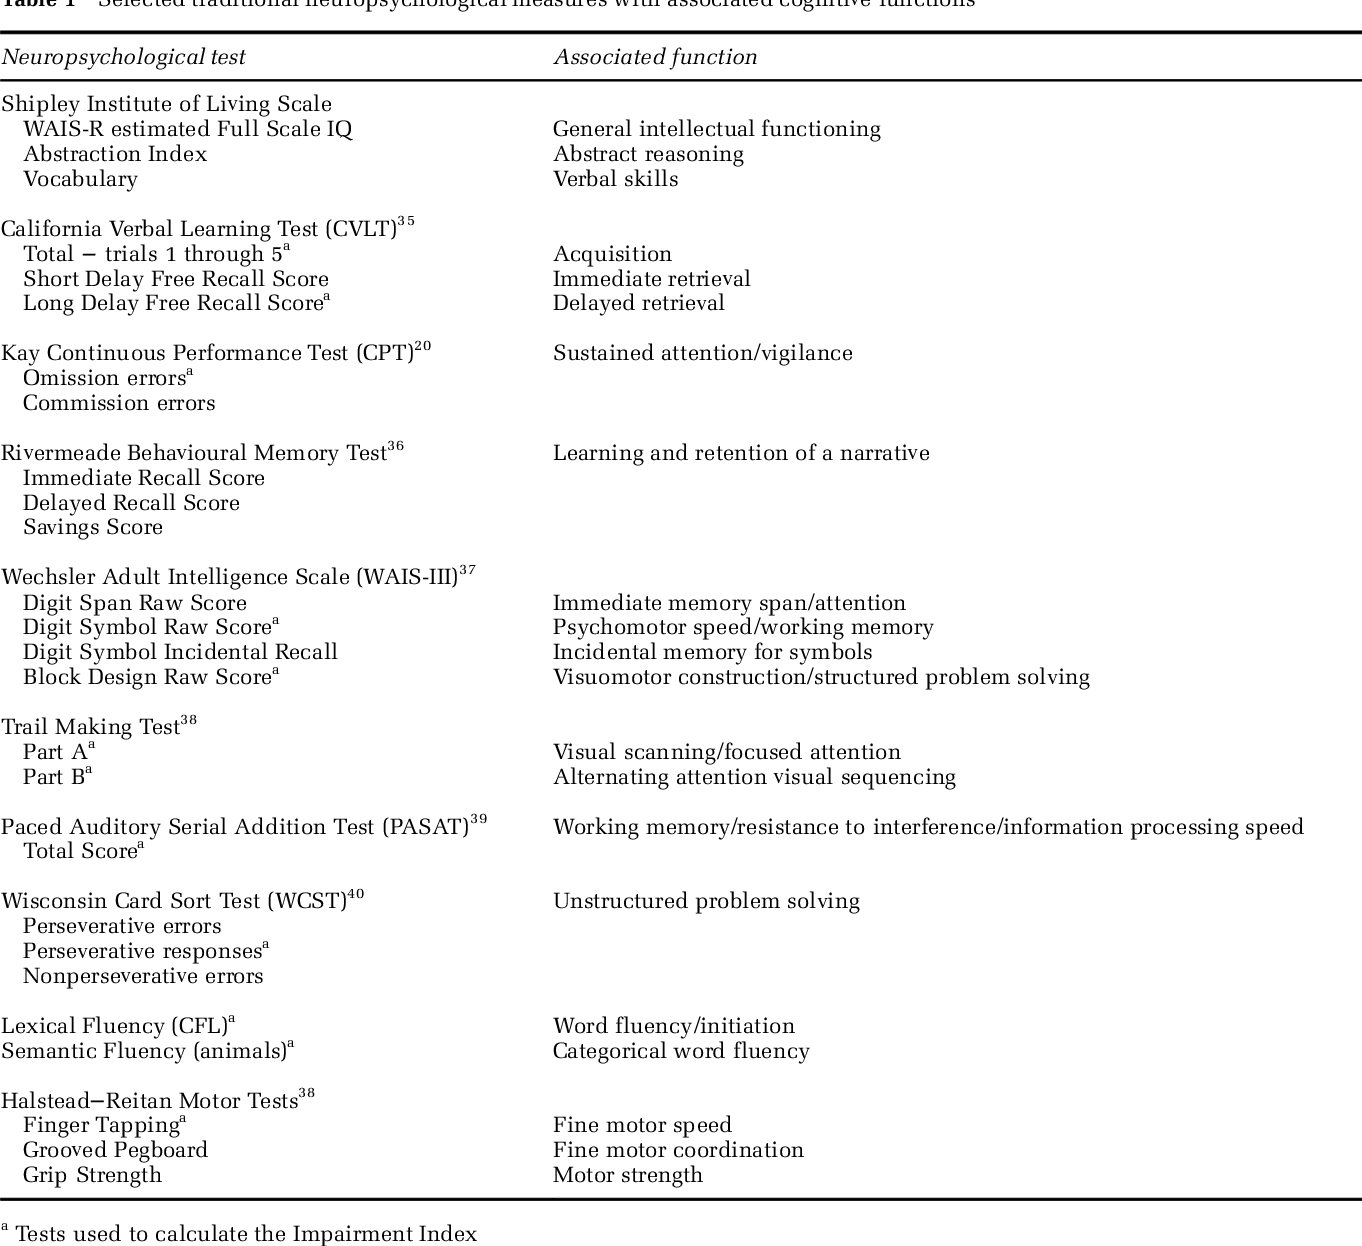
ANAM has limitations that become obvious only after you've used it for a while. The tests are sensitive to practice effects, meaning someone who takes the battery multiple times will improve simply from familiarity, not from actual cognitive change. I've seen this inflate treatment outcomes by 15-20 percent in rehabilitation studies when participants weren't counterbalanced properly. The system also struggles with certain populations. Motor impairments, visual deficits, or language barriers can all contaminate the scores in ways that aren't immediately obvious. If you're working with someone who has a tremor or limited hand function, the Reaction Velocity test becomes a measure of motor control rather than cognitive processing. I had to switch to a paper-based alternative for one client and spent extra time documenting why the ANAM data wasn't valid for their case. Another issue: ANAM isn't designed for comprehensive neuropsychological evaluation. It covers some cognitive domains well but leaves gaps. There's no equivalent for language assessment, visuospatial skills, or executive functioning beyond the basic Reasoning test. If you need a full picture, you'll still need traditional paper-and-pencil tests alongside it.My recommendation: use ANAM for what it does well—serial cognitive monitoring, especially in military, sports, or occupational settings where tracking change over time matters more than a single diagnostic snapshot. Don't expect it to replace a full neuropsychological battery or serve as a standalone diagnostic tool. The metrics are useful, but they're one piece of the puzzle, not the whole picture.
Get the Full Details