What the Axial Appendicular Skeletal System Actually Is
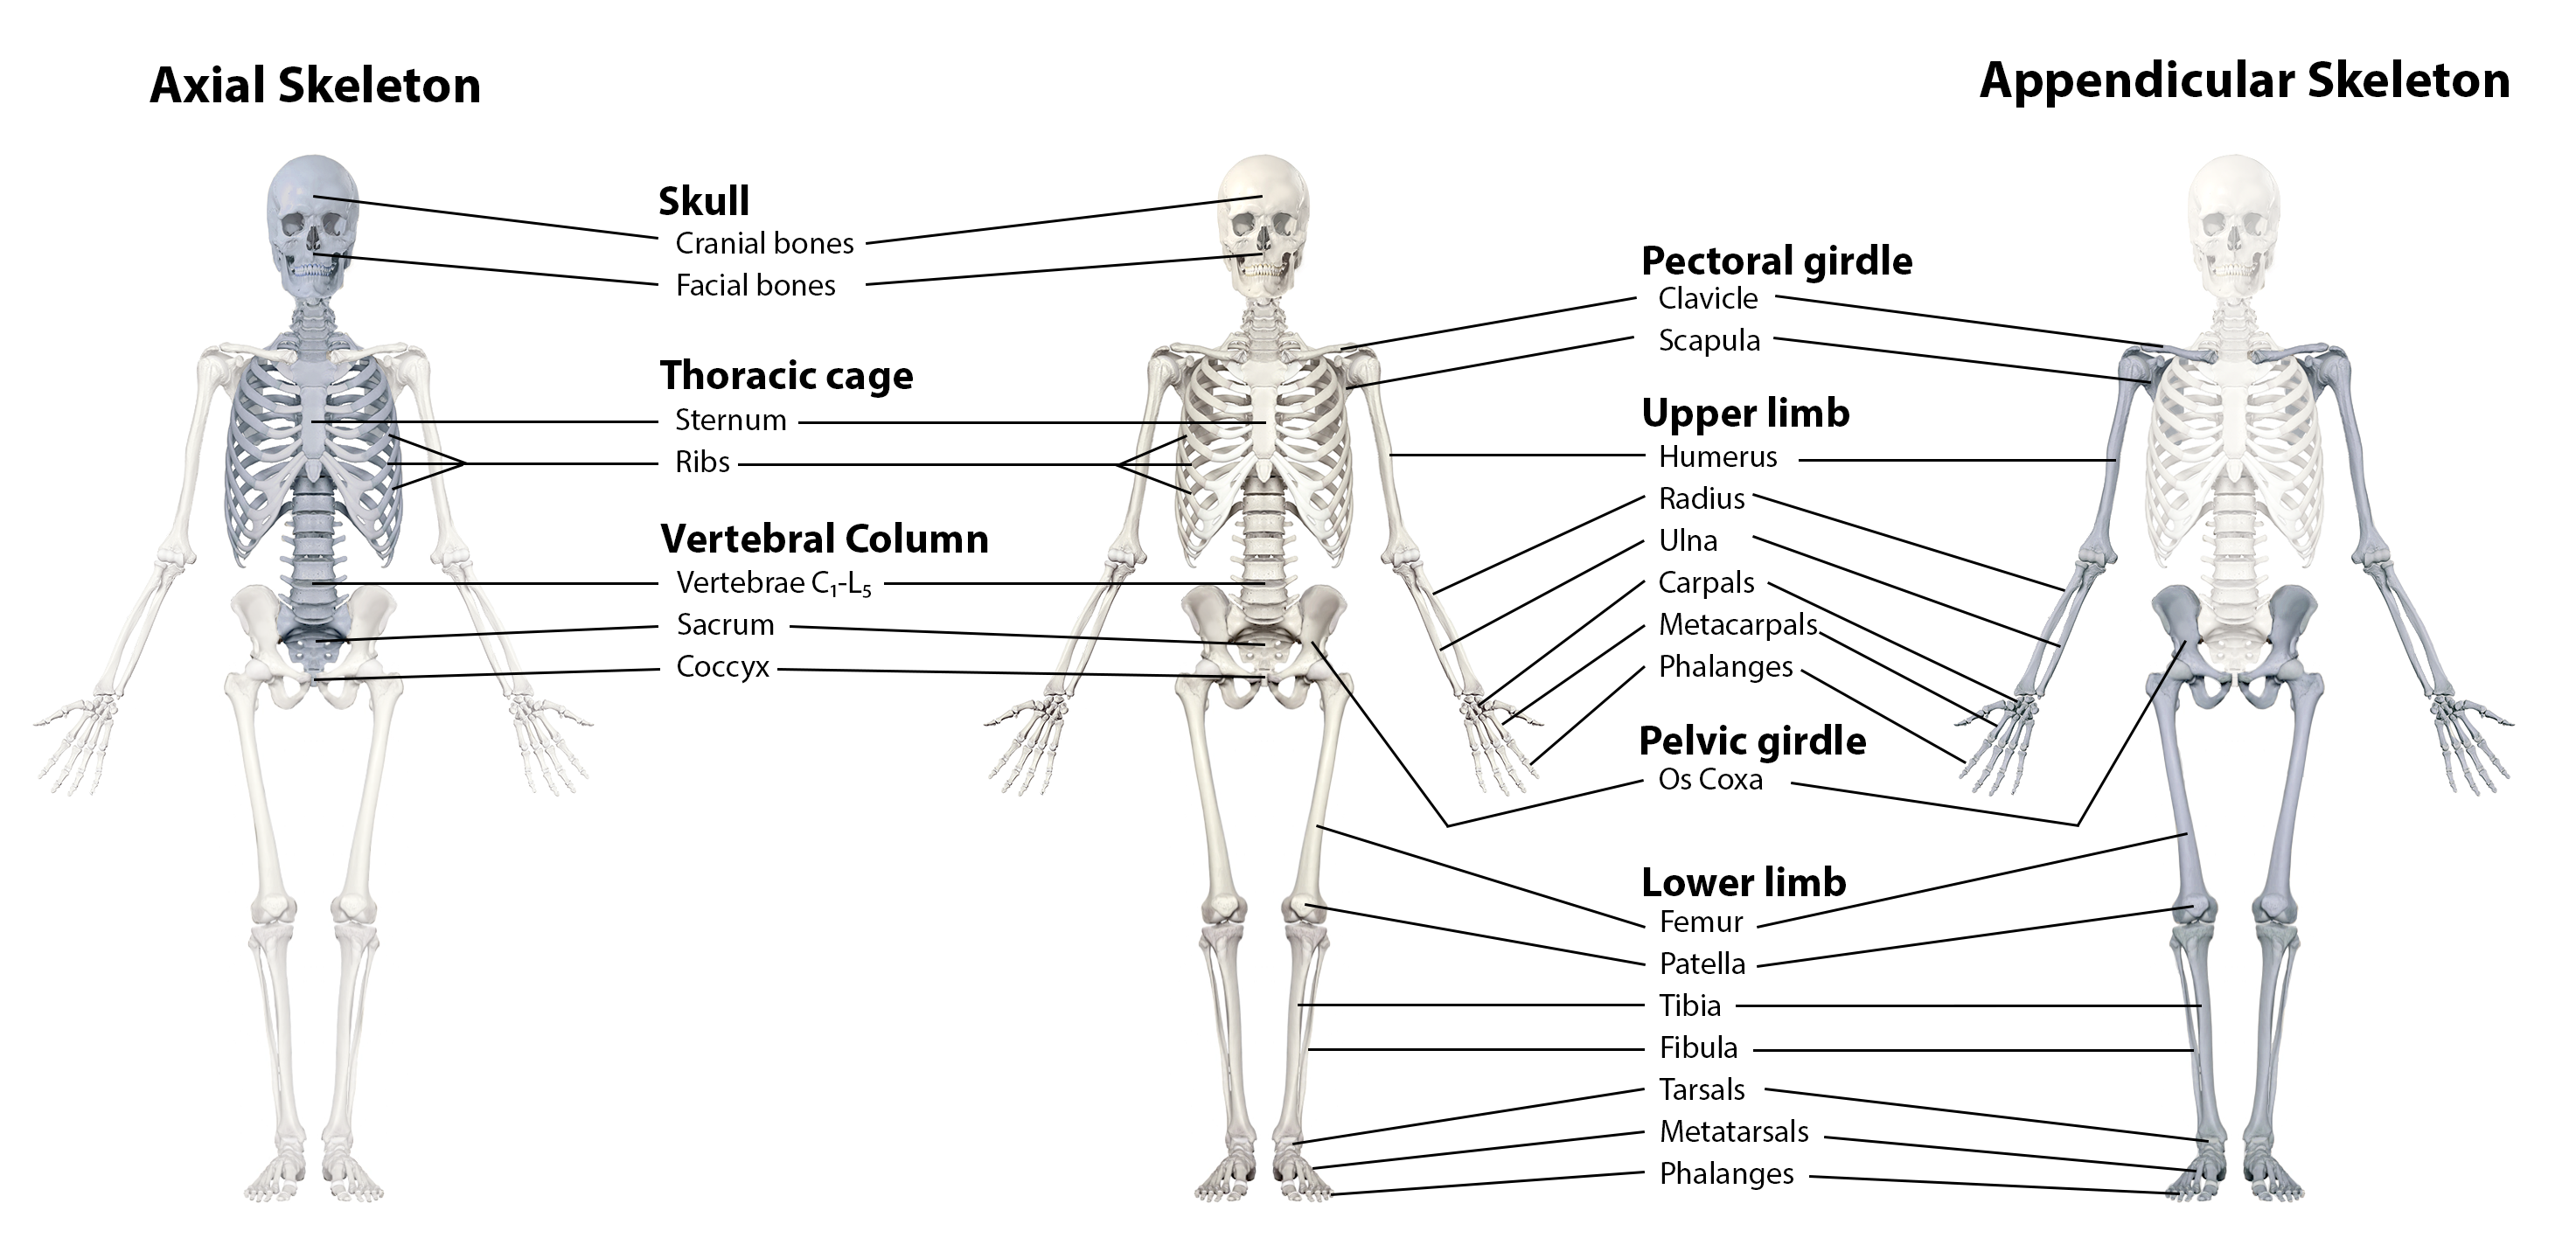
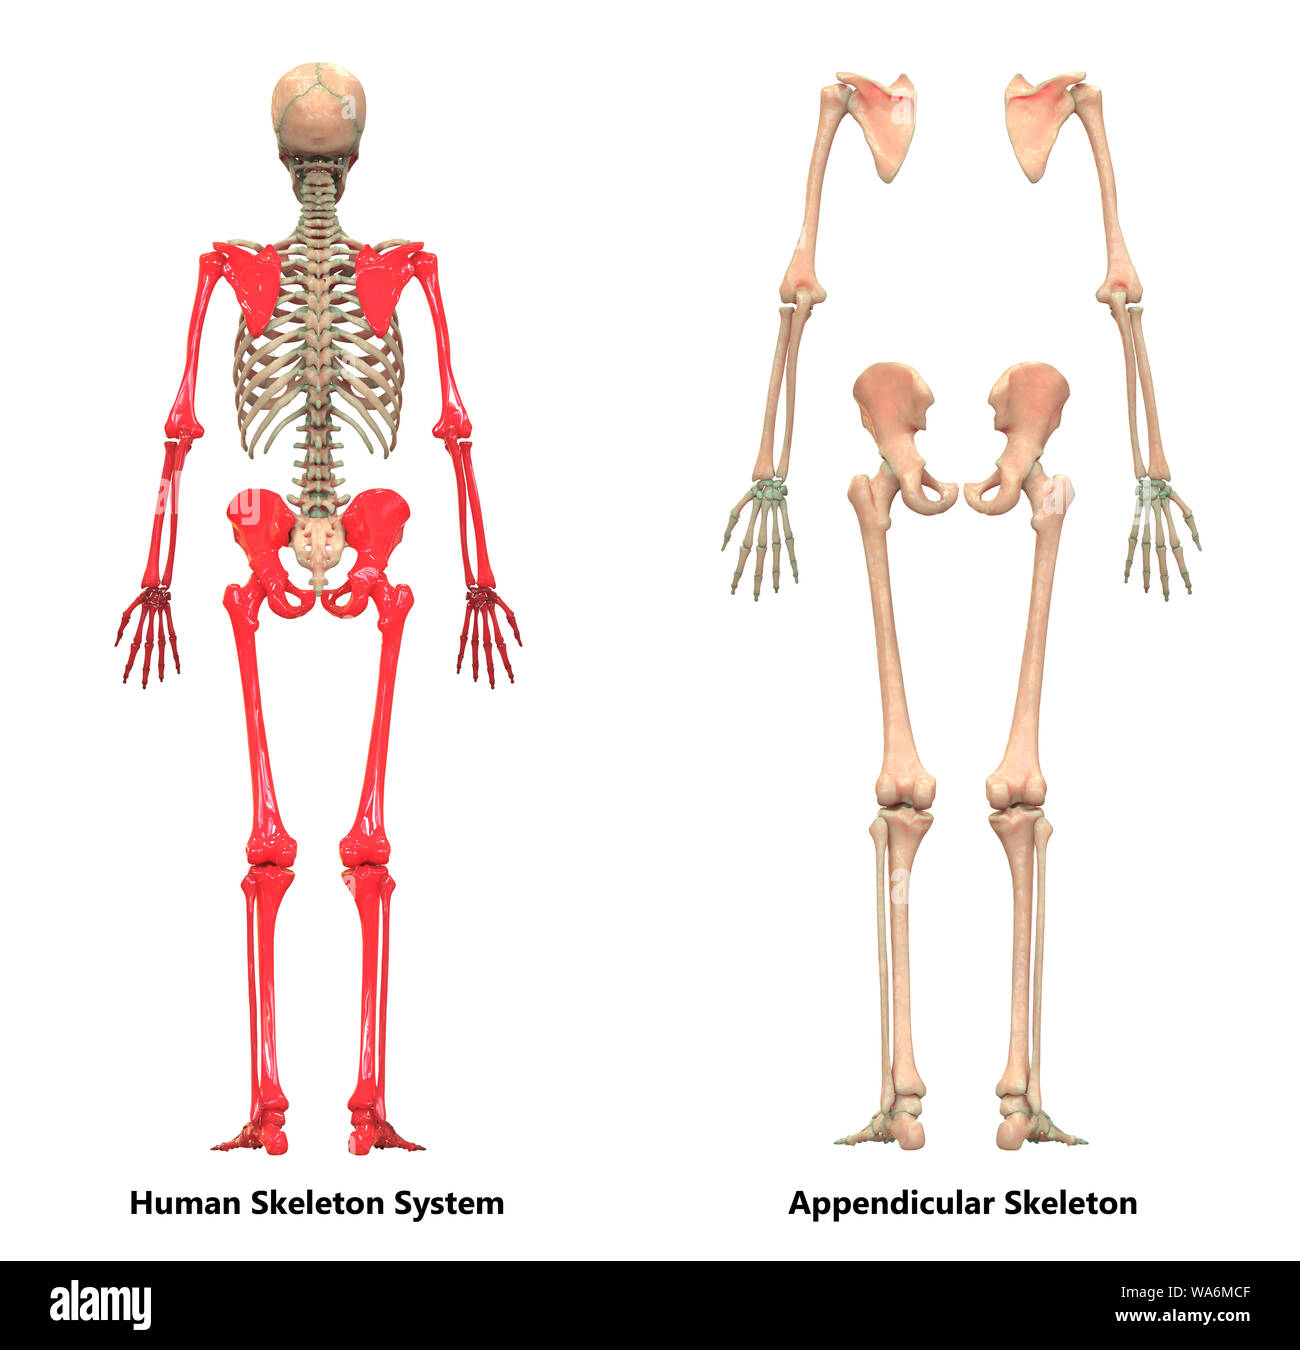
The skeletal system splits into two main divisions: the axial skeleton and the appendicular skeleton. The axial skeleton runs down the center of your body and includes the skull, vertebral column, rib cage, and hyoid bone. That is twenty-six individual vertebrae, eight cranial bones, fourteen facial bones, and twenty-four ribs plus the sternum. The appendicular skeleton makes up everything else — the shoulder girdles, pelvic girdle, and all the bones in the arms and legs. That is another one hundred and twenty-six bones for a typical adult. Together, that is two hundred and six bones, roughly fourteen percent of total body weight in an average adult. The numbers shift slightly between individuals and across the lifespan. Babies are born with around two hundred seventy bones, many of which fuse over time. By adulthood, the count settles into that standard range.
Understanding the Axial Appendicular Skeletal System in Practice
I spent years working in radiology, reading x-rays and MRIs day after day. The textbook definitions are fine, but the real challenge comes when you are actually looking at a scan and trying to map structures fast enough to catch something wrong. The axial and appendicular divisions are not just academic categories. They tell you where to look when a patient presents with specific symptoms. A lower back complaint usually points to the lumbar vertebrae in the axial skeleton. Shoulder impingement involves the clavicle and scapula of the appendicular skeleton. One thing beginners consistently miss is that the pectoral and pelvic girdles sit right on the border between the two systems. The clavicle and scapula anchor the upper limbs to the axial skeleton through the sternum. The pelvis does the same for the lower limbs. These transition zones are where most clinically significant injuries show up because they bear mechanical stress from both directions. When you are studying, do not treat the girdles as an afterthought. They are structurally critical. I ran into a case where a patient had persistent neck pain that traced through to the shoulder. Standard cervical imaging showed mild degenerative changes, nothing dramatic. But the pain pattern did not match the imaging findings. I traced it further and found a small fracture in the C7 transverse process that had been missed on the initial read. The axial skeleton can hide problems like this, especially in the lower cervical and upper thoracic junction where the ribs start to add visual clutter on plain films. CT with sagittal and coronal reconstructions cleared it up in about five minutes of scanning time.
Functional Differences Between the Two Divisions
The axial skeleton has three primary jobs: protection, support, and resonance. The skull protects the brain. The vertebral column protects the spinal cord. The rib cage shields the heart and lungs. The hyoid bone anchors the tongue and supports the floor of the mouth. It also handles phonation to some degree, which is why fractures there are clinically notable beyond just structural concerns. The appendicular skeleton is primarily built for movement. The long bones in the limbs act as levers. The joints between them provide the range of motion needed for manipulation of the environment. The girdles serve as the attachment points that transfer force between the limbs and the central axis. This division is also where you see the most variation between individuals in terms of size, proportion, and even bone count. Supernumerary ribs, extra lumbar vertebrae, and variations in the carpal and tarsal bones are all common enough that you should expect them in clinical practice. A counter-intuitive point worth noting: the axial skeleton is not as rigid as people assume. The sacroiliac joints, the symphysis pubis, and the intervertebral discs all have built-in micro-mobility. That flexibility is what allows the spine to absorb shock and the pelvis to expand during childbirth. When someone tells you the axial skeleton is just a static frame, they are oversimplifying. It is a dynamic structure, and that dynamism is why axial issues can refer pain to unexpected areas. A compressed nerve in the lumbar region can cause pain all the way down the leg because the skeletal components are connected through fascia and neural pathways, not just by direct bone-to-bone contact.
Get the Full Details

Common Issues and What to Watch For
Osteoporosis tends to hit the axial skeleton first and hardest. Vertebral compression fractures are the classic presentation, and they often go undiagnosed because people assume the resulting height loss and mild back ache are normal aging. DEXA scans are the standard diagnostic tool, and the T-score interpretation is straightforward once you know the thresholds: above negative one is normal, between negative one and negative two point five indicates osteopenia, and below negative two point five is osteoporosis. The appendicular skeleton has its own set of frequent problems. Stress fractures in the tibia and metatarsals are common in runners. Rotator cuff injuries dominate upper extremity complaints. Knee ligament tears are ubiquitous in sports medicine. These are not surprising statistics, but the overlap can be misleading. Someone with chronic knee pain might actually have a referred issue from a lumbar disc problem. The sciatic nerve runs from the lower spine through the hip and down the leg, and irritation at the source can present as joint pain distal to the actual problem. I have seen this mistake happen in both directions. Young patients get sent for lumbar imaging when the issue is purely orthopedic, and older patients get dismissed as having age-related joint wear when the real problem is a spinal issue. The axial appendicular skeletal system framework is useful here because it reminds you to consider both divisions when evaluating musculoskeletal complaints. If the localized exam findings do not fully explain the symptom pattern, look at the other system.
Study and Reference Approaches That Actually Work
Flashcards work for memorizing bone names and locations. They do not work well for understanding relationships between structures. A better approach is to study by functional regions. Learn the skull as a unit with its sutures and foramina. Learn the vertebral column segment by segment, noting how each region differs. Learn the upper and lower extremities as complete chains rather than isolated bones. When I was training, we used a method called regional systemic correlation. You pick a region and list every structure in it — bone, muscle, nerve, blood vessel, organ. Then you connect them. For example, the thoracic cavity includes the ribs, sternum, thoracic vertebrae, the heart, lungs, major vessels, and the brachial plexus roots. Linking them together makes recall faster and more reliable than rote memorization, especially under time pressure. For practical reference, I recommend the Netter atlas for visual learners and the Grant's Atlas of Anatomy for those who need more detail. Online resources like TeachMeAnatomy and Radiopaedia are useful for quick lookups, particularly when you need to correlate skeletal structure with imaging findings. Anatomical variation atlases are worth having on hand if you work in clinical settings because they save time when a standard reference does not match what you are seeing on a scan.
The axial and appendicular skeletal system is a foundational topic that shows up in nearly every medical and health science context. Understanding it thoroughly saves time later when you encounter complex cases. The divisions are simple to define but nuanced in application, and that is where the real learning happens.