Reading Axial Brain Mri Anatomy on a Daily Basis
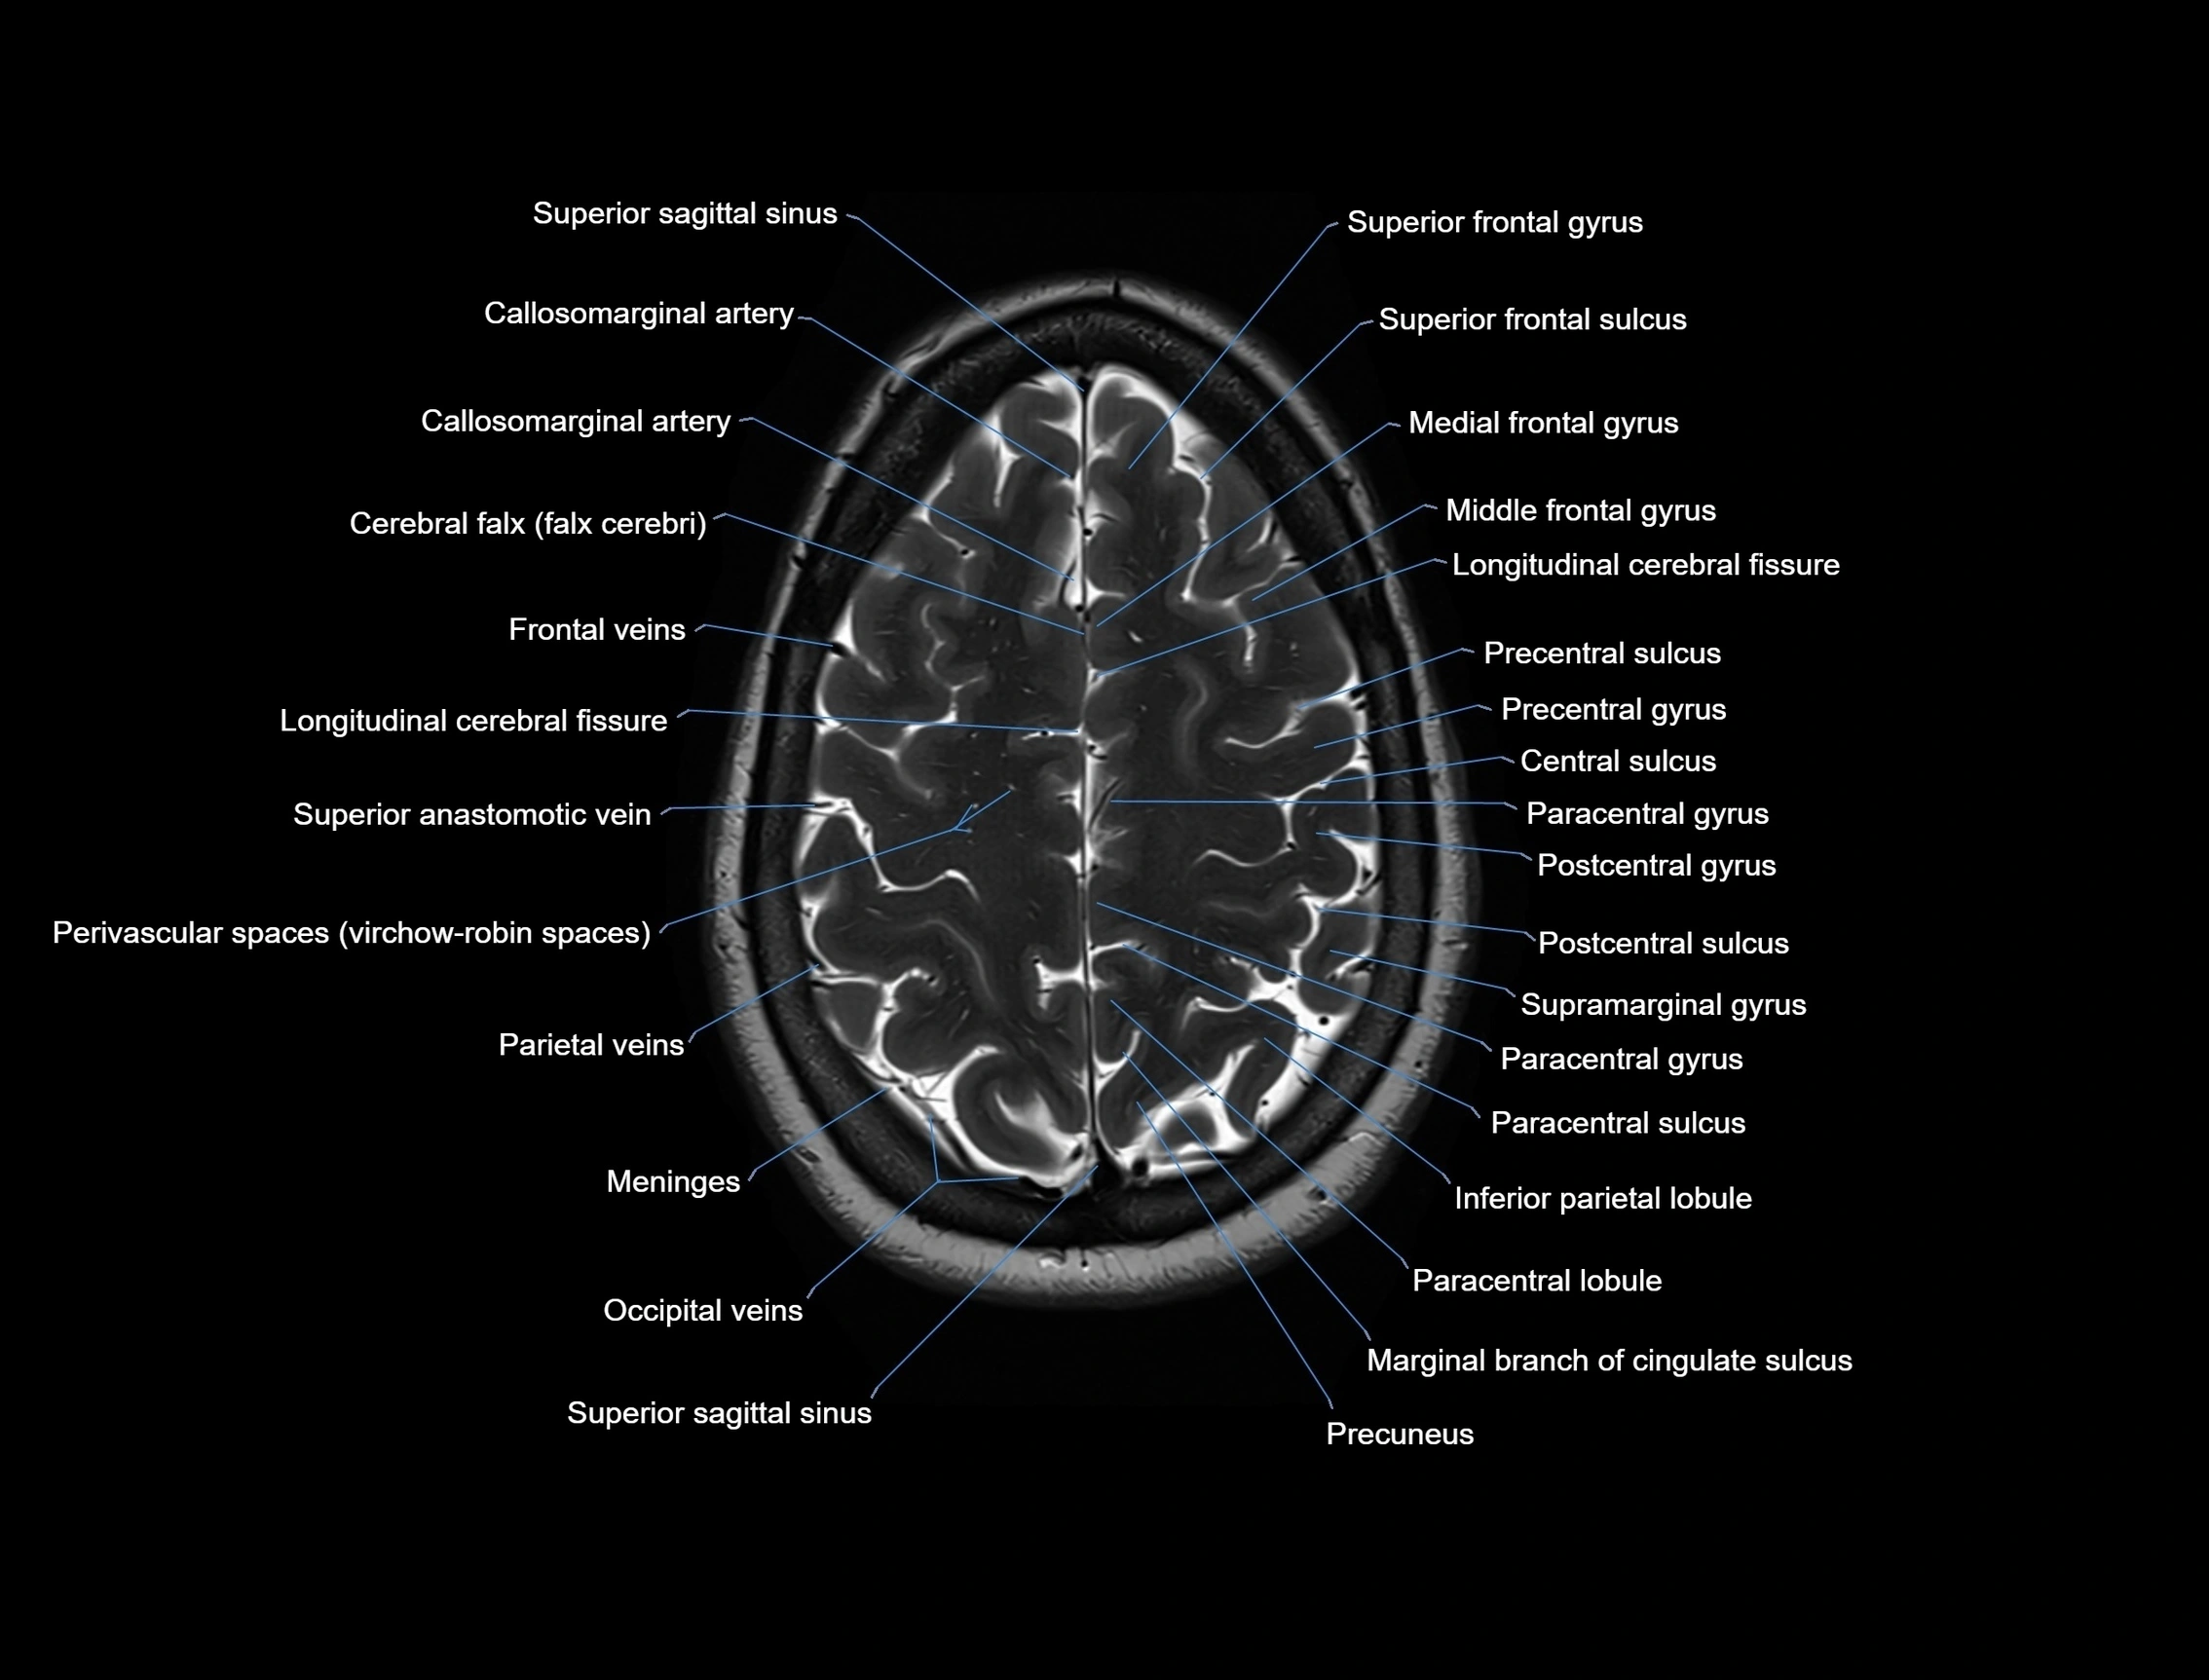
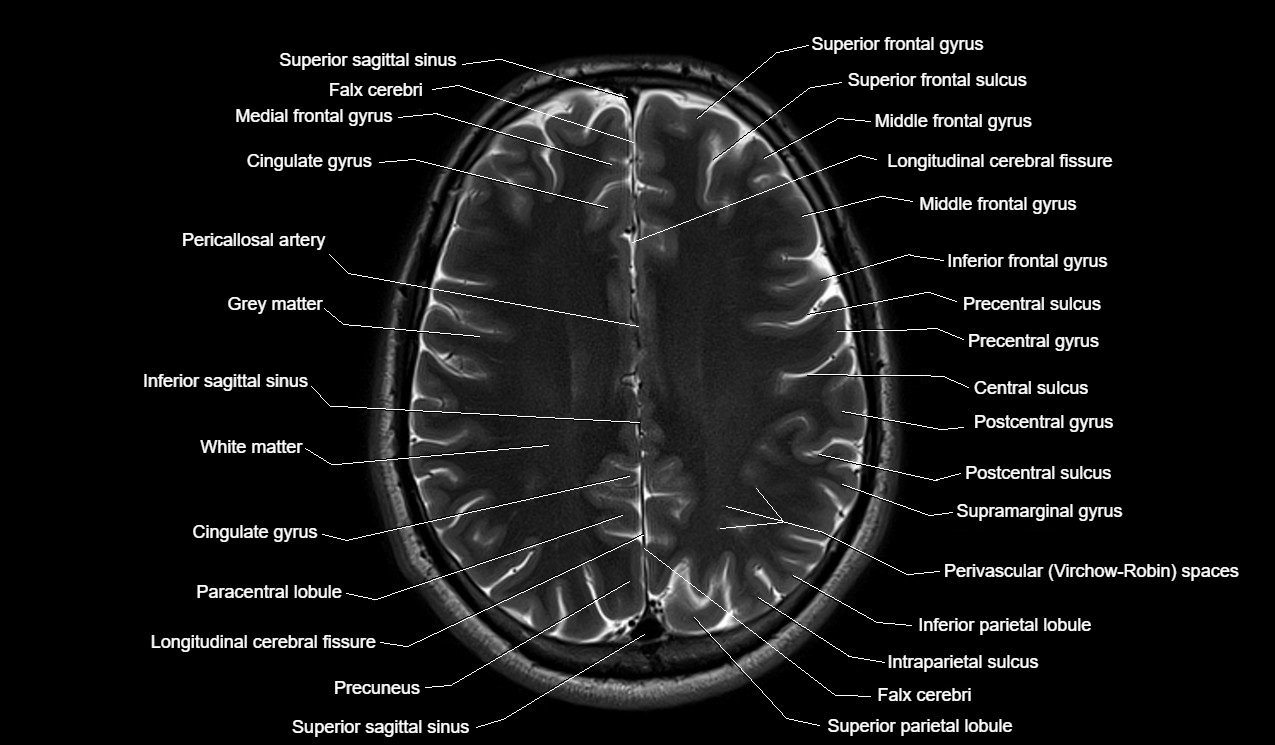
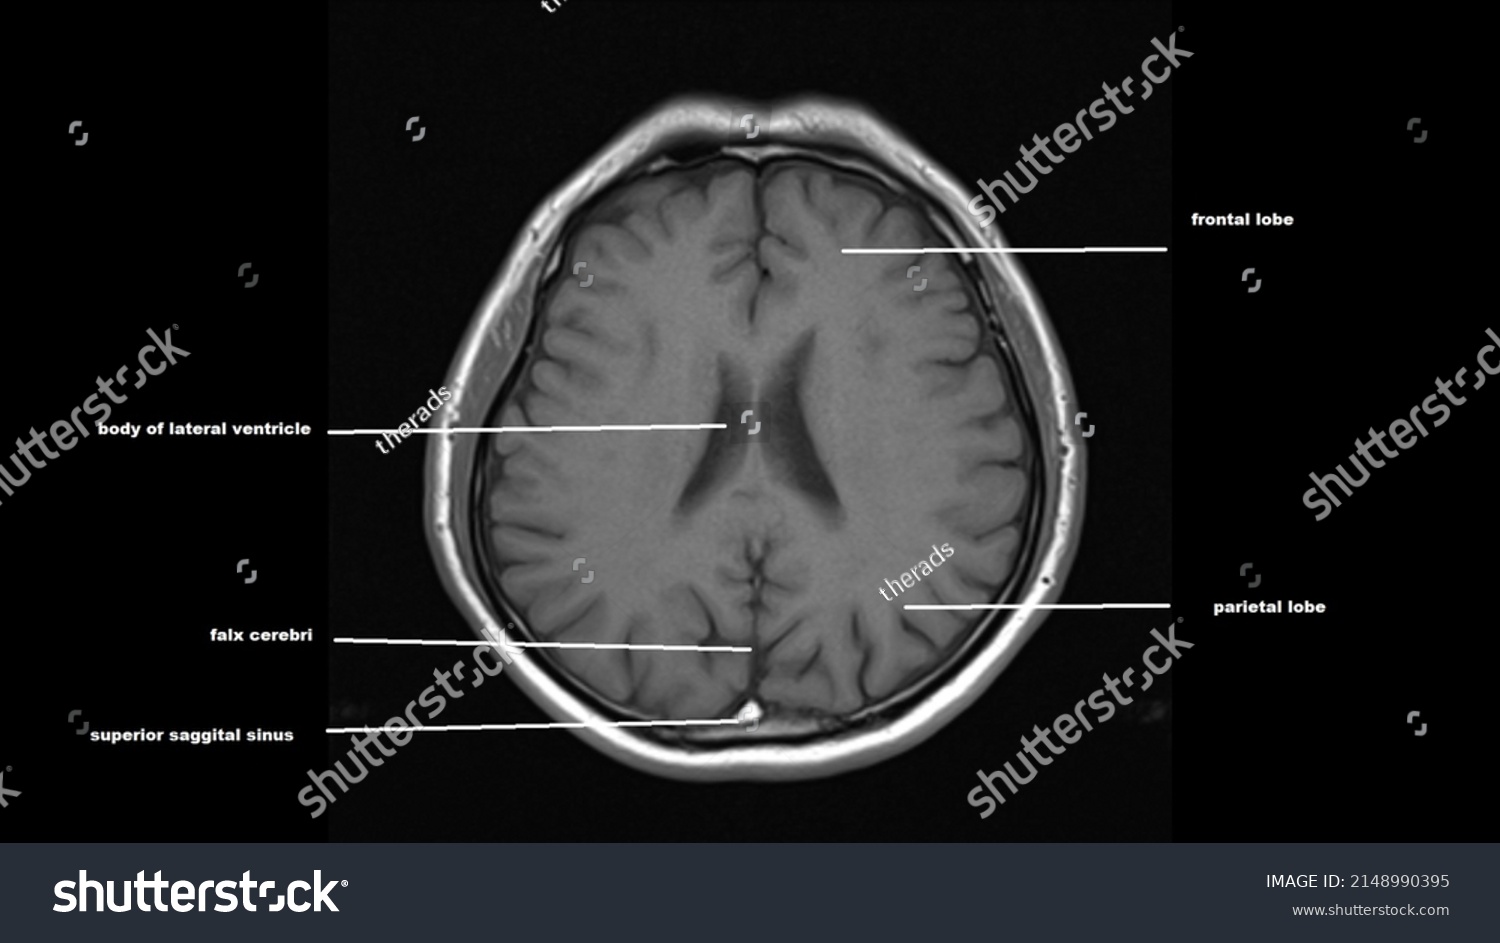
Most people learning this stuff start at the wrong level. They try to memorize every sulcus and gyrus before they understand how the slices actually relate to what's going on clinically. I spent years doing this backwards and it made everything slower than it needed to be. The brain in axial plane is fundamentally a series of horizontal cross-sections from the vertex down to the skull base, and the key is knowing what each level shows without getting lost in anatomical trivia that rarely matters for a reading radiologist or a practicing neurologist. The axial plane cuts the brain horizontally, dividing it into superior and inferior portions. On a standard clinical MRI, you're looking at T1-weighted, T2-weighted, FLAIR, and often DWI sequences at each level. The difference between sequences matters more than most beginners realize. T1 shows anatomy clearly with gray matter appearing darker than white matter. T2 flips that — white matter is dark, gray matter is bright, and CSF is brilliantly white. FLAIR suppresses the CSF signal so you can see periventricular lesions that would otherwise blend into the bright ventricles on a regular T2. DWI highlights acute ischemia within minutes of onset, which is why it's non-negotiable in stroke protocols. Starting from the top and working down, the first visible structures are the superior frontal gyri and the high convexity where the motor and sensory strips begin to appear around the level of the central sulcus. The falx cerebri is the thin midline structure you'll see throughout most of the scan, separating the two hemispheres. It's easy to mistake a prominent interhemispheric fissure for pathology if you're not paying attention. A small subdural collection can also track along the falx and get missed entirely if you're only looking at individual slices rather than scrolling through the series.
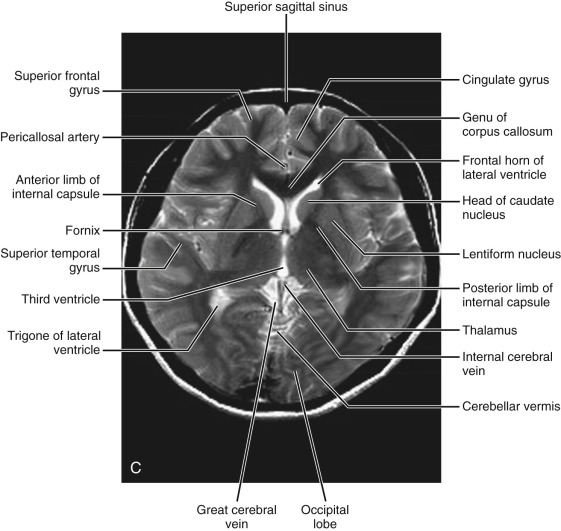
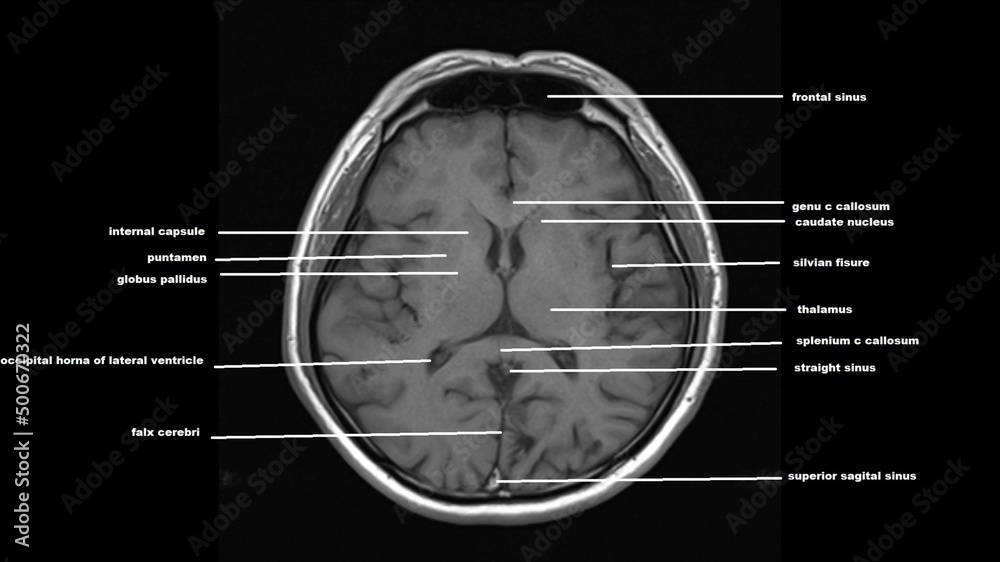
At the level of the lateral ventricles, you're typically seeing the frontal horns anteriorly, the bodies in the middle, and the occipital horns posteriorly. The caudate nucleus flanks the frontal horn laterally — its head is what creates the lateral bulge you see on each side. Between the caudate and the thalamus sits the internal capsule, a critical white matter pathway. Lesions here, even small ones, can produce significant motor deficits because all the corticospinal fibers are funneled through that narrow space. I had a case last year where a tiny lacunar infarct in the posterior limb of the internal capsule was almost invisible on T1 but stood out clearly on DWI. The patient presented with pure motor weakness on one side and the diagnosis wasn't obvious until I compared the DWI to the ADC map to confirm true restricted diffusion rather than T2 shine-through. The third ventricle appears as a midline slit between the two thalami. The thalami themselves are large ovoid structures on either side. Above them you can sometimes see the lateral geniculate bodies posteriorly and the medial geniculate bodies just behind them. The pineal gland sits posterior and slightly superior to the third ventricle — it's commonly calcified in adults and that calcification is normal, not a reason to order a CT. I've seen too many residents flag a calcified pineal gland as an incidental finding that triggers unnecessary follow-up imaging. It's a landmark, not a lesion. Below the thalami is the midbrain, which has that characteristic mule-ear appearance on axial slice. The cerebral peduncles form the anterior part and the tegmentum sits posterior to them. The substantia nigra is visible as a slight hypointensity within the midbrain on T2-weighted images due to its melanin and iron content. This is also where the cerebral aqueduct runs — a tiny channel connecting the third and fourth ventricles. Aqueductal stenosis is a common cause of obstructive hydrocephalus and it's easily missed if you're not specifically looking at this level.
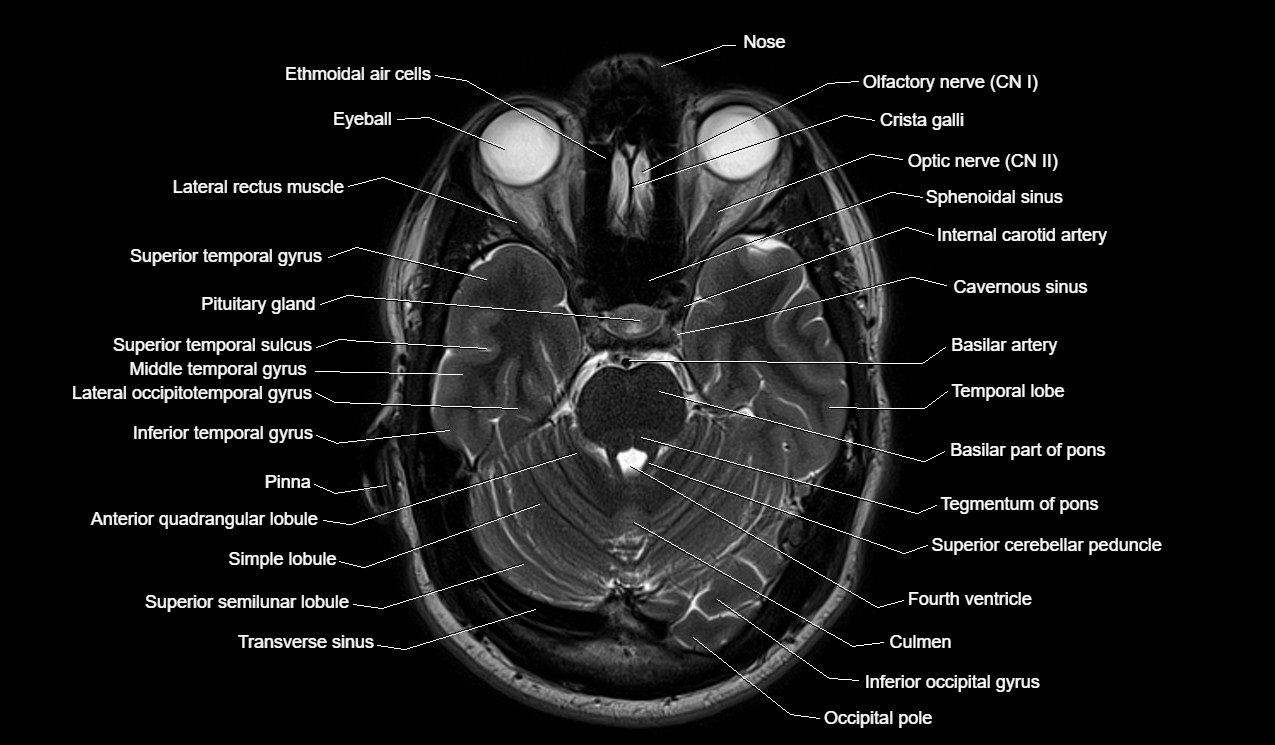
The pons and medulla come next as you move inferiorly. The pons is the large bulging structure anterior to the fourth ventricle. The fourth ventricle is diamond-shaped on axial view and sits between the pons anteriorly and the cerebellum posteriorly. The cerebellar hemispheres and the vermis make up the posterior fossa contents. The cerebellopontine angle spaces on either side of the pons are where vestibular schwannomas typically occur. An asymmetric CPA angle should always raise suspicion for a mass lesion, even a small one. The basal cisterns are another important landmark system. The suprasellar cistern at the level of the pituitary stalk contains the Circle of Willis vessels. The interpeduncular cistern sits between the cerebral peduncles. Subarachnoid hemorrhage tends to collect in these cisterns first, which is why a non-contrast CT is the initial test of choice for suspected SAH — though MRI with FLAIR and SWI sequences is remarkably sensitive for detecting blood in the cisterns as well.
Get the Full Details
Common Pitfalls and What Beginners Miss
One of the most consistent mistakes I see is confusing normal variants with pathology. The arachnoid granulations along the parasagittal region can look like mass lesions on T1 and FLAIR if you're not accustomed to their appearance. They follow CSF signal on all sequences and often have a teardrop shape pointing inward from the dura. Another frequent error is calling the velum interpositum a third ventricle extension or a cyst. It's a normal dural reflection that sits between the thalami and the corpus callosum and contains the internal cerebral veins. Sagittal sinus flow voids are another source of confusion. On gradient echo and susceptibility-weighted images, the superior sagittal sinus can show heterogeneous signal due to complex flow patterns. This is normal. Calling it a thrombus based on a single sequence is a mistake I've seen on reading room QC reports far too often. You need to correlate with phase-contrast MR venography or at minimum check multiple sequences before diagnosing dural sinus thrombosis. The symmetry argument is both useful and dangerously overused. Most brains are roughly symmetrical, but they're never perfectly symmetrical. Asymmetry of the temporal horns, slight differences in the size of the hippocampi, minor variations in sulcal pattern — these are all normal. The problem is that when you're tired or rushing through a heavy workload, your brain will sometimes impose false symmetry and miss an actual abnormality because it doesn't match the other side. I keep a mental checklist for every scan: compare left and right at each level, but don't let the comparison make you complacent. A subtle effacement of the right insular ribbon on FLAIR can be the only early sign of an evolving MCA infarction, and it's easy to overlook if you're scanning too quickly.
Posterior fossa imaging has its own set of challenges. Volume averaging between the pons and the medulla can create artificial signal changes that look like pathology. Partial volume artifact is also a problem at the skull base where bone creates susceptibility artifacts, particularly on gradient echo sequences. These artifacts can obscure the internal auditory canals and make small vestibular schwannomas harder to detect. Thin-section imaging at 3mm or less through the posterior fossa helps significantly, and I always scroll through the cerebellopontine angles slowly with the window and level optimized for soft tissue rather than leaving it on the default brain preset. Another thing that isn't emphasized enough is the relationship between axial anatomy and surgical corridors. If you're going to interpret brain MRIs meaningfully, you need to understand what a neurosurgeon is doing when they approach a lesion. The transsylvian route, the translaminar approach through the superior frontal gyrus, the subtemporal corridor — each of these has specific anatomical structures that must be avoided. Knowing that the dominant hemisphere's arcuate fasciculus runs through the perisylvian region changes how you describe a tumor's relationship to functional cortex. It's the difference between saying "the mass abuts the language area" and actually understanding which white matter tract is at risk.
Practical Workflow for Axial Brain Mri Anatomy Review
I review scans in a consistent order that I've refined over thousands of cases. First pass is a rapid sweep through all sequences at a thick-slab display to catch gross abnormalities — midline shift, hydrocephalus, large masses, significant hemorrhage. Second pass is sequential single-slice review starting from the vertex and moving down, checking each structure at each level. Third pass is targeted — if I found something on the first two passes, I go back and measure it, characterize it across sequences, and look for associated findings like edema or mass effect. If nothing was found, I do a final focused review of the posterior fossa and the sellar region where small lesions are easiest to miss. Window and level settings make a real difference in detection rate. The default brain preset is adequate for most things but optimizing for gray-white matter differentiation usually means lowering the window width to around 80 and adjusting the level to around 40 on T1 images. For FLAIR, a narrower window helps highlight subtle hyperintensities in the white matter. I spend about 30 seconds per sequence per adjustment and it consistently picks up findings that would be invisible on the standard display. This typically adds maybe four to six minutes to a review that would otherwise take twelve to fifteen, but it catches things that would otherwise require a callback or a repeat scan. Modern PACS systems have been making this easier with intelligent preset switching and automated comparison with prior studies. The comparison feature alone has probably saved me from reporting more benign findings as new abnormalities than I can count. A stable enhancing nodule that's been there for three years isn't concerning regardless of how it looks on the current scan. But if you're not systematically comparing, you lose that context and you start chasing incidentalomas.
The limitation I want to be honest about is that axial imaging alone is insufficient for many pathologies. A lesion that appears isodense on axial T1 might be obvious on coronal or sagittal reconstructions. Gliomatosis cerebri, certain demyelinating diseases, and leptomeningeal carcinomatosis are all better appreciated in multiple planes. I don't rely on axial images exclusively anymore. Standard protocol now includes reconstructed coronal and sagittal views from the isotropic 3D T1 and 3D FLAIR sequences that most modern scanners produce. The additional five minutes it takes to scroll through the reformats is worth it for the increase in diagnostic confidence. There's also the question of field strength. At 3T, the anatomical detail is noticeably better than at 1.5T, particularly in the posterior fossa where susceptibility artifacts are more pronounced but so is the signal-to-noise ratio. The higher field strength also improves the sensitivity of DWI and perfusion imaging. But 3T isn't universally better — it's more susceptible to motion artifact, and patients with certain types of implants may not be candidates. The tradeoff is real and it matters when you're deciding between protocols. Ultimately, axial brain MRI anatomy is about pattern recognition built on a foundation of systematic knowledge. The structures don't change — what changes is how quickly and accurately you can identify them and relate them to clinical findings. The shortcuts only work if you've put in the foundational work first. And even after decades of doing this, I still double-check the posterior fossa on every single scan because that's where the misses happen.