Three ways to slice a 3D volume
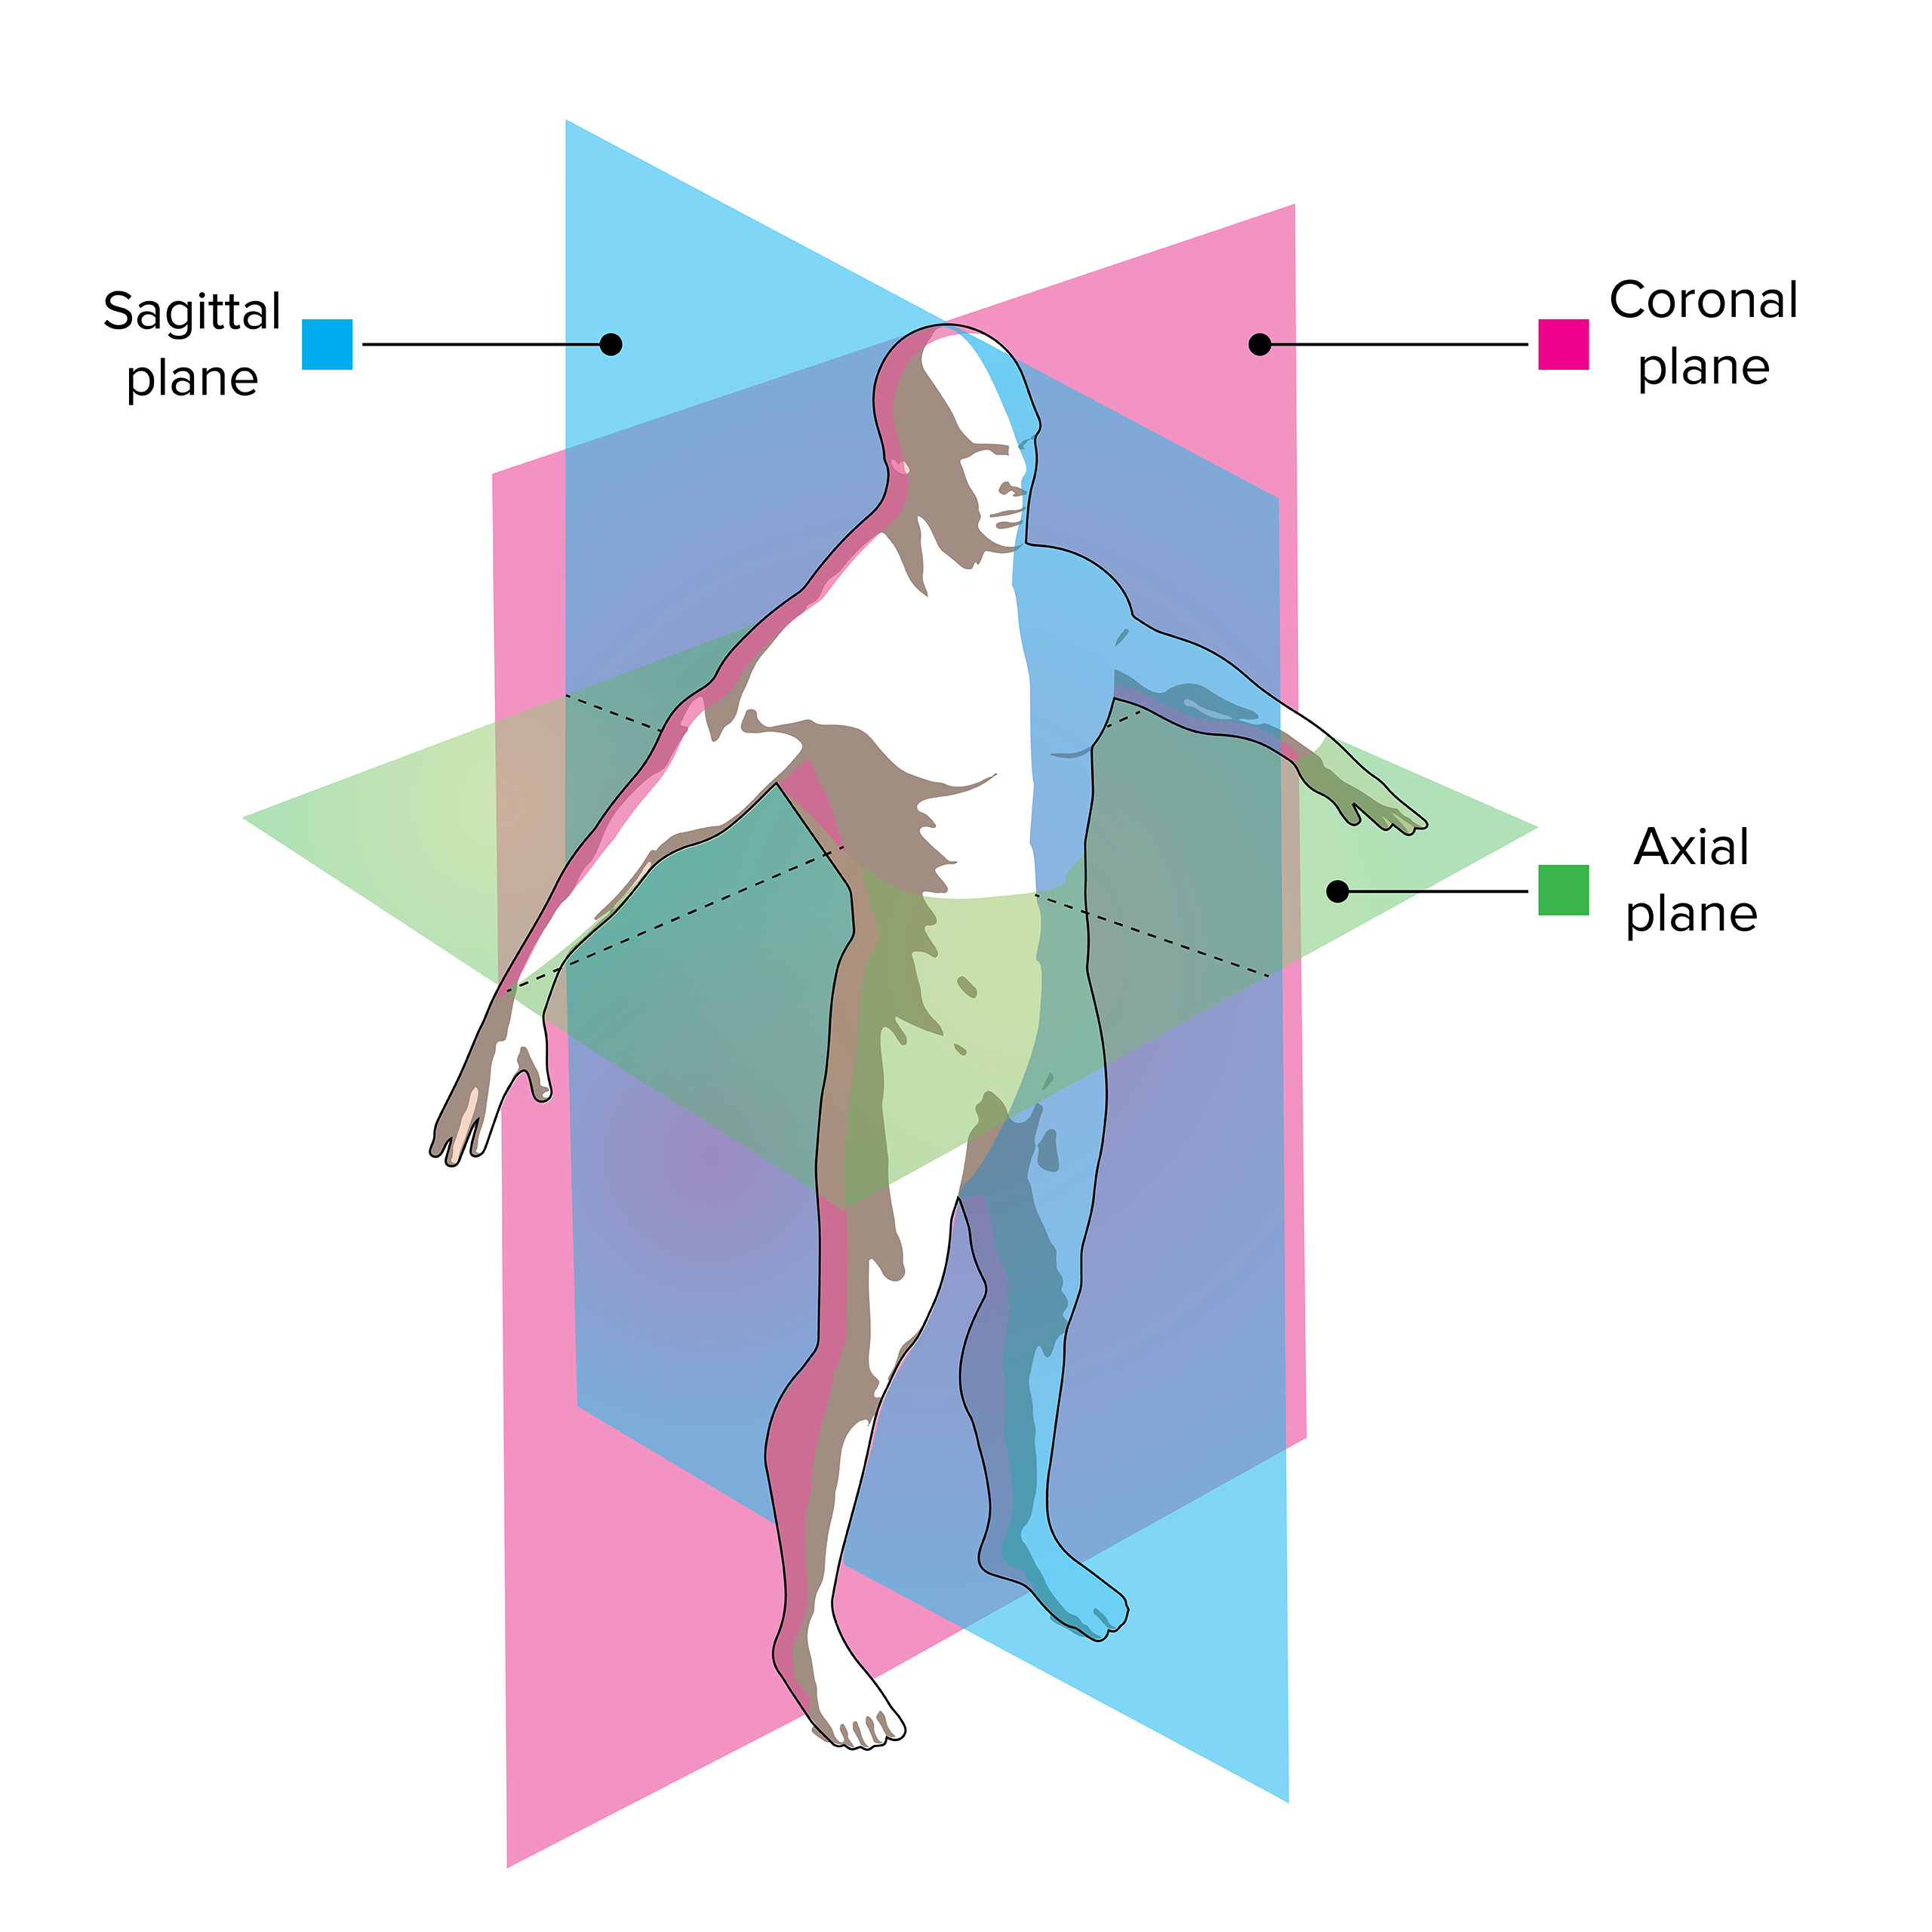
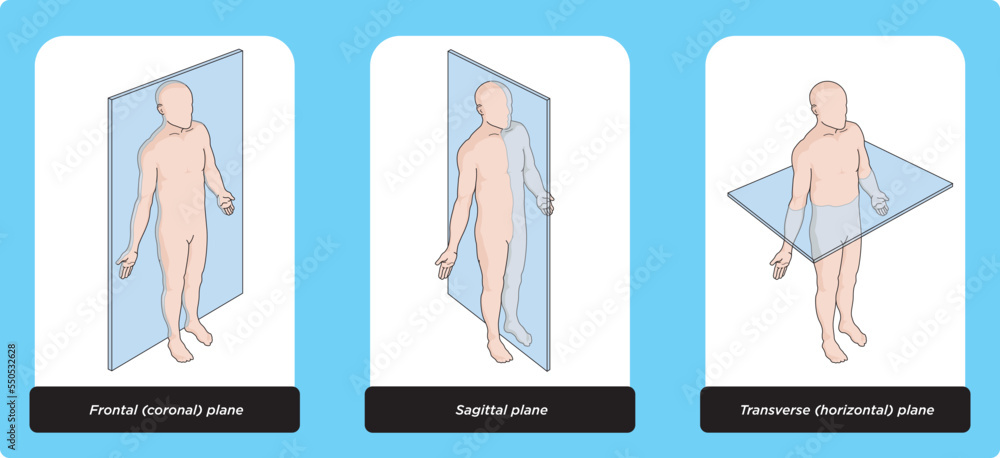
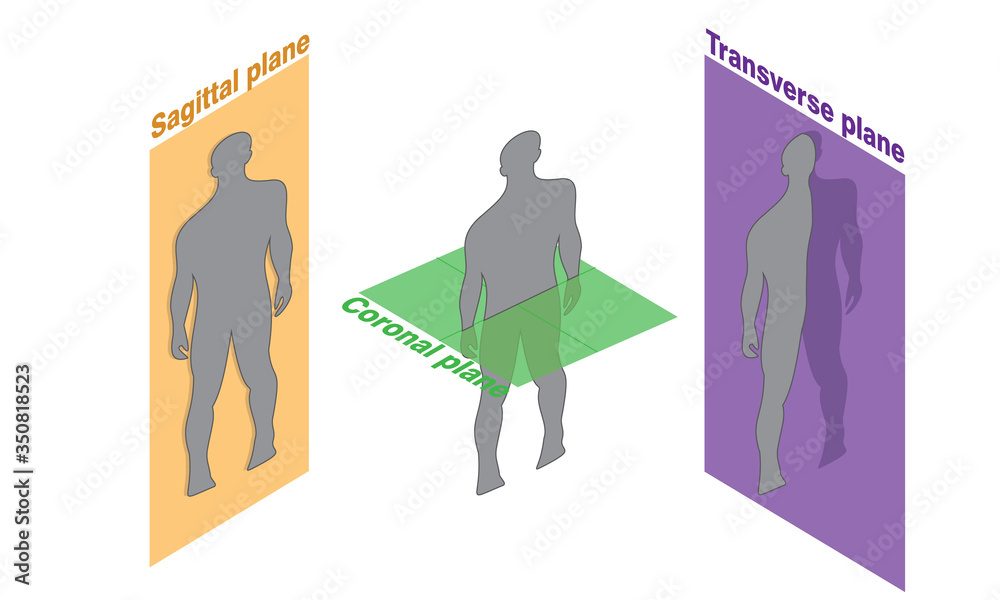
When you work with volumetric data — MRI, CT, ultrasound — you are almost always looking at a stack of 2D slices that represent a 3D space. The axial coronal sagittal planes are just the three standard orthogonal orientations you use to navigate that space. That is it. Nothing more mysterious than that, but people overcomplicate it because the terminology comes from anatomy rather than imaging physics. The axial plane cuts horizontally through the body, dividing top from bottom. The coronal plane cuts vertically front to back, separating anterior from posterior. The sagittal plane cuts vertically left to right, separating left from right. A mid-sagittal cut goes right down the middle; anything off-center is parasagittal. These definitions haven't changed in decades and they are consistent across almost every imaging modality.
Axial Coronal Sagittal Planes — why reformatting breaks things
Here is the part nobody warns you about: when you reformat a volume from its native acquisition plane into a different one, you are doing interpolation, not magic. Most scanners acquire axial slices with a certain in-plane resolution and a certain slice thickness. If your axial slices are 5mm apart and you try to reformatted a coronal view at that same spacing, the result will look smooth but the data is interpolated. It isn't new information. It looks fine for gross anatomy, but if you are measuring something small — a lesion under a centimeter, a thin ligament — those reformatted planes can smear the edges and give you inaccurate dimensions. I ran into this on a spinal MRI case where the original acquisition was axial 3mm slices with a 1mm gap. I needed coronal views to assess disc protrusion laterality. The vendor's built-in reformat looked decent at first glance, but when I measured the lateral extent of the protrusion against the original axial slices, I was off by about 4mm. The workaround was to go back to the DICOM and use a multi-planar reconstruction tool that lets you set the output slice thickness independently. I set it to 1.5mm with a 0.75mm interval, which gave me enough overlap to cross-reference properly. It took about ten extra minutes but saved me from reporting an incorrect measurement. If you are working in a PACS system, look for an option called isotropic reformat or volume rendering rather than simple slab projection. The real issue is that most radiologists and technologists accept the default reformat settings without questioning them. The default is usually fast and visually acceptable, which is exactly when it causes problems. Fast reconstructions use linear interpolation, which smooths edges. For diagnostic purposes near tissue boundaries, cubic convolution interpolation gives sharper results but takes longer. I always use cubic when I am doing measurements, linear only for quick orientation.
How to actually use these planes in practice
Start with the axial plane. It is usually the acquisition plane, so it has the highest native resolution. orient yourself there first. Then switch to the coronal and sagittal views as localizers — they are derived from the same dataset, so they should match. If they don't match, check for patient rotation or mislabeling of the DICOM headers. That happens more often than you would think, especially with portable ultrasounds and CT scans done in trauma bays where positioning is rushed. One thing beginners miss is that the sagittal and coronal views in your viewer are not independent. They are linked to the axial through a set of crosshair cursors. Moving the cursor on one plane moves it on all three. This is useful but also dangerous because it is easy to lose track of which plane you are actually adjusting. I keep one view locked to a reference slice and only move the crosshairs when I am intentionally navigating. Otherwise I get myself turned around, especially with oblique reconstructions where the standard orientation doesn't apply. For CT angiography and contrast studies, the axial plane during the arterial phase is where you do your primary read. The coronal and sagittal reformats are secondary aids. Don't let the reformatted images distract you from the source data. I have seen residents call a stenosis on a coronal MIP that wasn't there when they went back to the axial source images. The maximum intensity projection merges everything along a ray path, which can create false continuity between vessels and make artifacts look like pathology.
Get the Full Details

There is a useful trick for checking whether your reformatted planes are aligned correctly: look at the spine or the ribs. In a properly oriented coronal reformat, the vertebral bodies should stack symmetrically and the rib heads should appear at consistent levels. If one side looks higher or the vertebrae are tilted, your volume is rotated and every measurement you take from that reformat is going to be slightly wrong. You can usually fix this in the viewer with a reorientation function, but some older systems don't have it. In those cases you are better off reslicing from the raw data if it is still available. The other common mistake is assuming the plane names mean the same thing across modalities. In ultrasound, "axial" can refer to the depth axis of the beam, not the anatomical transverse plane. In MRI sequences like FLAIR or DWI, the acquisition might be oblique to the AC-PC line, which means your axial slices are tilted relative to the standard anatomical axial plane. You need to be aware of what the scanner actually acquired, not just what the labels say. The DICOM tag ImageOrientationPatient tells you the exact tilt. Reading it takes five seconds and prevents a lot of confusion. When you are learning this, don't memorize the definitions in isolation. Load a dataset and actually rotate through the planes. Click through slices. See where the anatomy appears and disappears. The spatial relationships click faster when you see them move than when you read about them. Start with a normal brain CT, then move to a chest CT, then a spine MRI. Each body region emphasizes different aspects of the three planes and you will notice patterns quickly.
Axial Coronal Sagittal Planes are not complicated, but they are easy to mess up if you treat the reformatted views as primary rather than as navigational tools. The source data is always the ground truth. The planes are just different ways of looking at the same information, and knowing which one gives you the most reliable answer for a given clinical question is what separates a careful reader from a careless one.