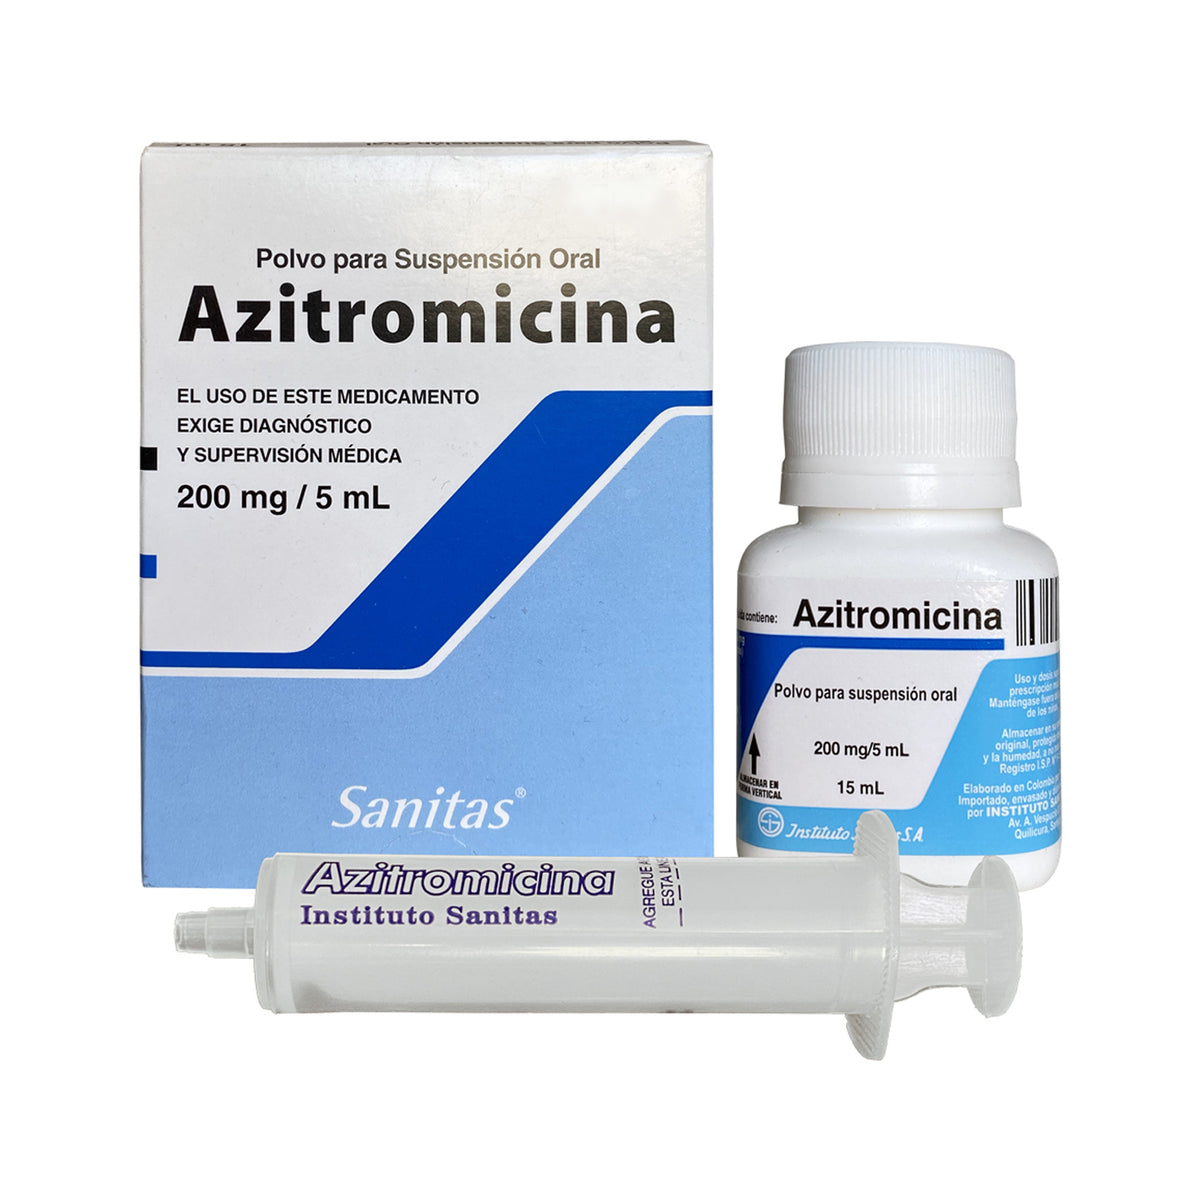
How to Work with Azithromycin Oral Suspension in Real Practice
Azitromicina Solucion Oral is a macrolide antibiotic delivered as a compounded powder that you reconstitute with water. It comes in different concentrations depending on the manufacturer—usually 100 mg per 5 mL or 200 mg per 5 mL after mixing. The powder sits at the bottom of the bottle, and until you add the correct volume of water and shake it properly, nothing is dissolved yet. I have seen more prescribing errors from people skipping the reconstitution step than from any other issue with this medication. The dosing schedule for azithromycin is unlike almost every other antibiotic. It has a half-life of roughly 68 hours, which means it stays in your system much longer than standard broad-spectrum antibiotics. For most respiratory infections in adults, the protocol is 500 mg on day one, then 250 mg daily for days two through five. Pediatric dosing uses a different calculation entirely—typically 10 mg/kg on day one, then 5 mg/kg daily for four days. You need to weigh the patient properly because weight-based dosing mistakes here are easy to make when you are guessing. I once had a situation where a parent was measuring the dose with a regular kitchen teaspoon instead of an oral syringe or calibrated cup. The variability in that approach can be 20 to 30 percent off. I switched them to a 5 mL oral syringe immediately and told them to check the measurement at eye level against the calibration line. The difference between a 2.5 mL and a 3 mL error becomes significant when you are dosing a small child at 5 mg/kg.
For respiratory tract infections, the typical 5-day course is standard. But there are scenarios where the dosing changes completely. For community-acquired pneumonia, some clinicians use 500 mg once daily for 3 days instead of the standard extended course. The drug accumulates in tissue at concentrations that are 10 to 100 times higher than serum levels, which is why the short course still works. This is counter-intuitive for people used to thinking about antibiotics like penicillin, which need consistent blood levels maintained through frequent dosing.
Reconstitution and Storage Details That Matter
When you add water to the powder, you are not dissolving it. You are creating a suspension. The particles need to be evenly distributed, which is why the label tells you to shake well before each use. If you do not shake it, the concentration at the top of the bottle will be lower than at the bottom. This is not a minor issue. I have seen actual therapeutic failures where the early doses were subtherapeutic because the suspension was not remixed properly. After reconstitution, the suspension typically needs refrigeration at 2 to 8 degrees Celsius. Some brands allow storage at room temperature for up to 10 days, but you need to read the specific package insert for the product you have. The stability data varies by manufacturer. A suspension stored beyond the labeled window can lose potency, and there is no easy way to tell by looking at it whether it has degraded. I ran into a problem once with a patient who left their bottle in the car over a hot day. The suspension looked fine, smelled fine, and the particles were evenly distributed. It had likely lost somewhere between 10 and 20 percent of its potency. I told them to discard it and restart with a new bottle. Azithromycin is cheap enough that the risk of undertreating an infection is not worth saving a few dollars.
Get the Full Details

Drug Interactions and Clinical Limitations
Azithromycin has fewer drug interactions than other macrolides like erythromycin because it does not significantly inhibit CYP3A4. That is one of the reasons it got popular. But it still carries a black box warning for QT prolongation. If the patient is on other medications that affect the QT interval—certain antiarrhythmics, antipsychotics, or fluoroquinolones—the combination can be dangerous. The risk is higher in elderly patients and those with electrolyte abnormalities, particularly hypokalemia or hypomagnesemia. Antacids that contain aluminum or magnesium can reduce the absorption of azithromycin by about 30 to 40 percent. If a patient is taking both, you should separate the doses by at least two hours. I have noticed many patients do not make this adjustment because they are not given clear instructions, and the reduced absorption means lower tissue concentrations at a critical time. There are also resistance concerns that are often understated. Azithromycin resistance in Streptococcus pneumoniae has been increasing steadily. In some regions, resistance rates exceed 30 percent. This means that for certain respiratory infections, azithromycin may simply not work as a first-line option anymore. If you are treating a bacterial infection and the patient shows no improvement after 48 to 72 hours, consider that resistance might be the cause rather than assuming the dose is wrong or the diagnosis is uncertain.
Common Formulation Problems and Practical Solutions
The taste of azithromycin oral suspension is bad. This is not subjective—most formulations use flavorings that mask the bitterness only partially. Children often spit it out, which leads to incomplete dosing. I have found that giving the dose right before a meal can help, but food can also affect absorption slightly depending on the formulation. The most reliable workaround I have used is mixing the measured dose with a small amount of acidic juice like apple or orange juice. The acidity helps mask the taste without interfering with absorption in any clinically meaningful way. Do not mix it into a full glass or bottle of liquid because if the child does not finish it, you do not know how much medication they actually received. Another practical issue is the measuring device. Many bottles come with a plastic dosing spoon that is inaccurate by design. These spoons are molded, not calibrated. The actual volume can vary by several milliliters. I always recommend using a calibrated oral syringe instead, which gives you accuracy to within 0.5 mL or better. The cost of a syringe is negligible compared to the cost of a treatment failure caused by an inaccurate dose. For neonates and infants, the standard suspension concentrations may be difficult to dose accurately. The volumes required are so small that even a well-calibrated syringe has limits. In these cases, some compounding pharmacies can prepare a lower-concentration suspension that allows for larger, more measurable volumes. I have used this approach when dosing preterm infants where the calculated volume was less than 1 mL. The accuracy improvement was significant, and it eliminated the need to administer multiple sub-milliliter doses.
What This Medication Does Not Treat
Azithromycin has no activity against methicillin-resistant Staphylococcus aureus. It is also unreliable against many Gram-negative organisms due to efflux pump resistance mechanisms. You should not use it for urinary tract infections because tissue penetration in the urinary tract is poor and resistance is common. I see this mistake occasionally—prescribing azithromycin for a UTI because it is a familiar antibiotic. It is the wrong tool for the job, and using it delays proper treatment. For viral upper respiratory infections, azithromycin provides no benefit. The antibiotic has no antiviral activity. Using it in these cases contributes to resistance and exposes the patient to side effects without any therapeutic gain. Gastrointestinal side effects occur in roughly 10 to 15 percent of patients and include diarrhea, nausea, and abdominal pain. These are usually mild but can be severe enough to cause discontinuation. The medication also carries a risk of Clostridioides difficile infection, as with any antibiotic that disrupts normal gut flora. The risk is lower than with broad-spectrum agents like clindamycin or fluoroquinolones, but it is not zero. Patients who develop persistent watery diarrhea during or after treatment should be evaluated for C. diff regardless of how mild the symptoms initially appear.

Where to Obtain the Medication
Azitromicina Solucion Oral is available by prescription in most countries. The brand name Zithromax is one option, but generic versions from various manufacturers are widely available and equally effective. Some regions also carry it under names like Azax, Azicip, or Azee depending on the local pharmaceutical market. The specific suspension strengths and excipients will vary by brand, so always verify the concentration on the label before dispensing. If you need to locate a pharmacy that stocks the suspension, call ahead and confirm they have the specific concentration your prescription requires. Many community pharmacies keep the tablets in stock but may need to order the oral suspension, which can take 24 to 48 hours. This delay is usually not clinically significant for most infections, but it is worth planning around if the patient is a young child who cannot take tablet formulations. For compounding pharmacies, the process is different. They mix the suspension from pure azithromycin base according to a specific formula. The shelf life of a compounded suspension is typically shorter than the commercial product—often 14 days when refrigerated. The concentration accuracy depends on the compounding pharmacy's equipment and technique. If you are using a compounded version, verify that the pharmacy uses calibrated balances and volumetric equipment, and ask about their quality control procedures. A poorly compounded suspension can have significant concentration variability between the top and bottom of the bottle even with proper shaking.
Online sources for azithromycin without a prescription exist, but the quality is unpredictable. Counterfeit products have been identified in various markets, and some contain incorrect amounts of the active ingredient or harmful contaminants. The risk is not theoretical. I have seen patients present with subtherapeutic response because they purchased the medication from an unregulated source. The few dollars saved are not worth the uncertainty.