Practical Notes on Comet Tail Artifacts at the Lung Interface
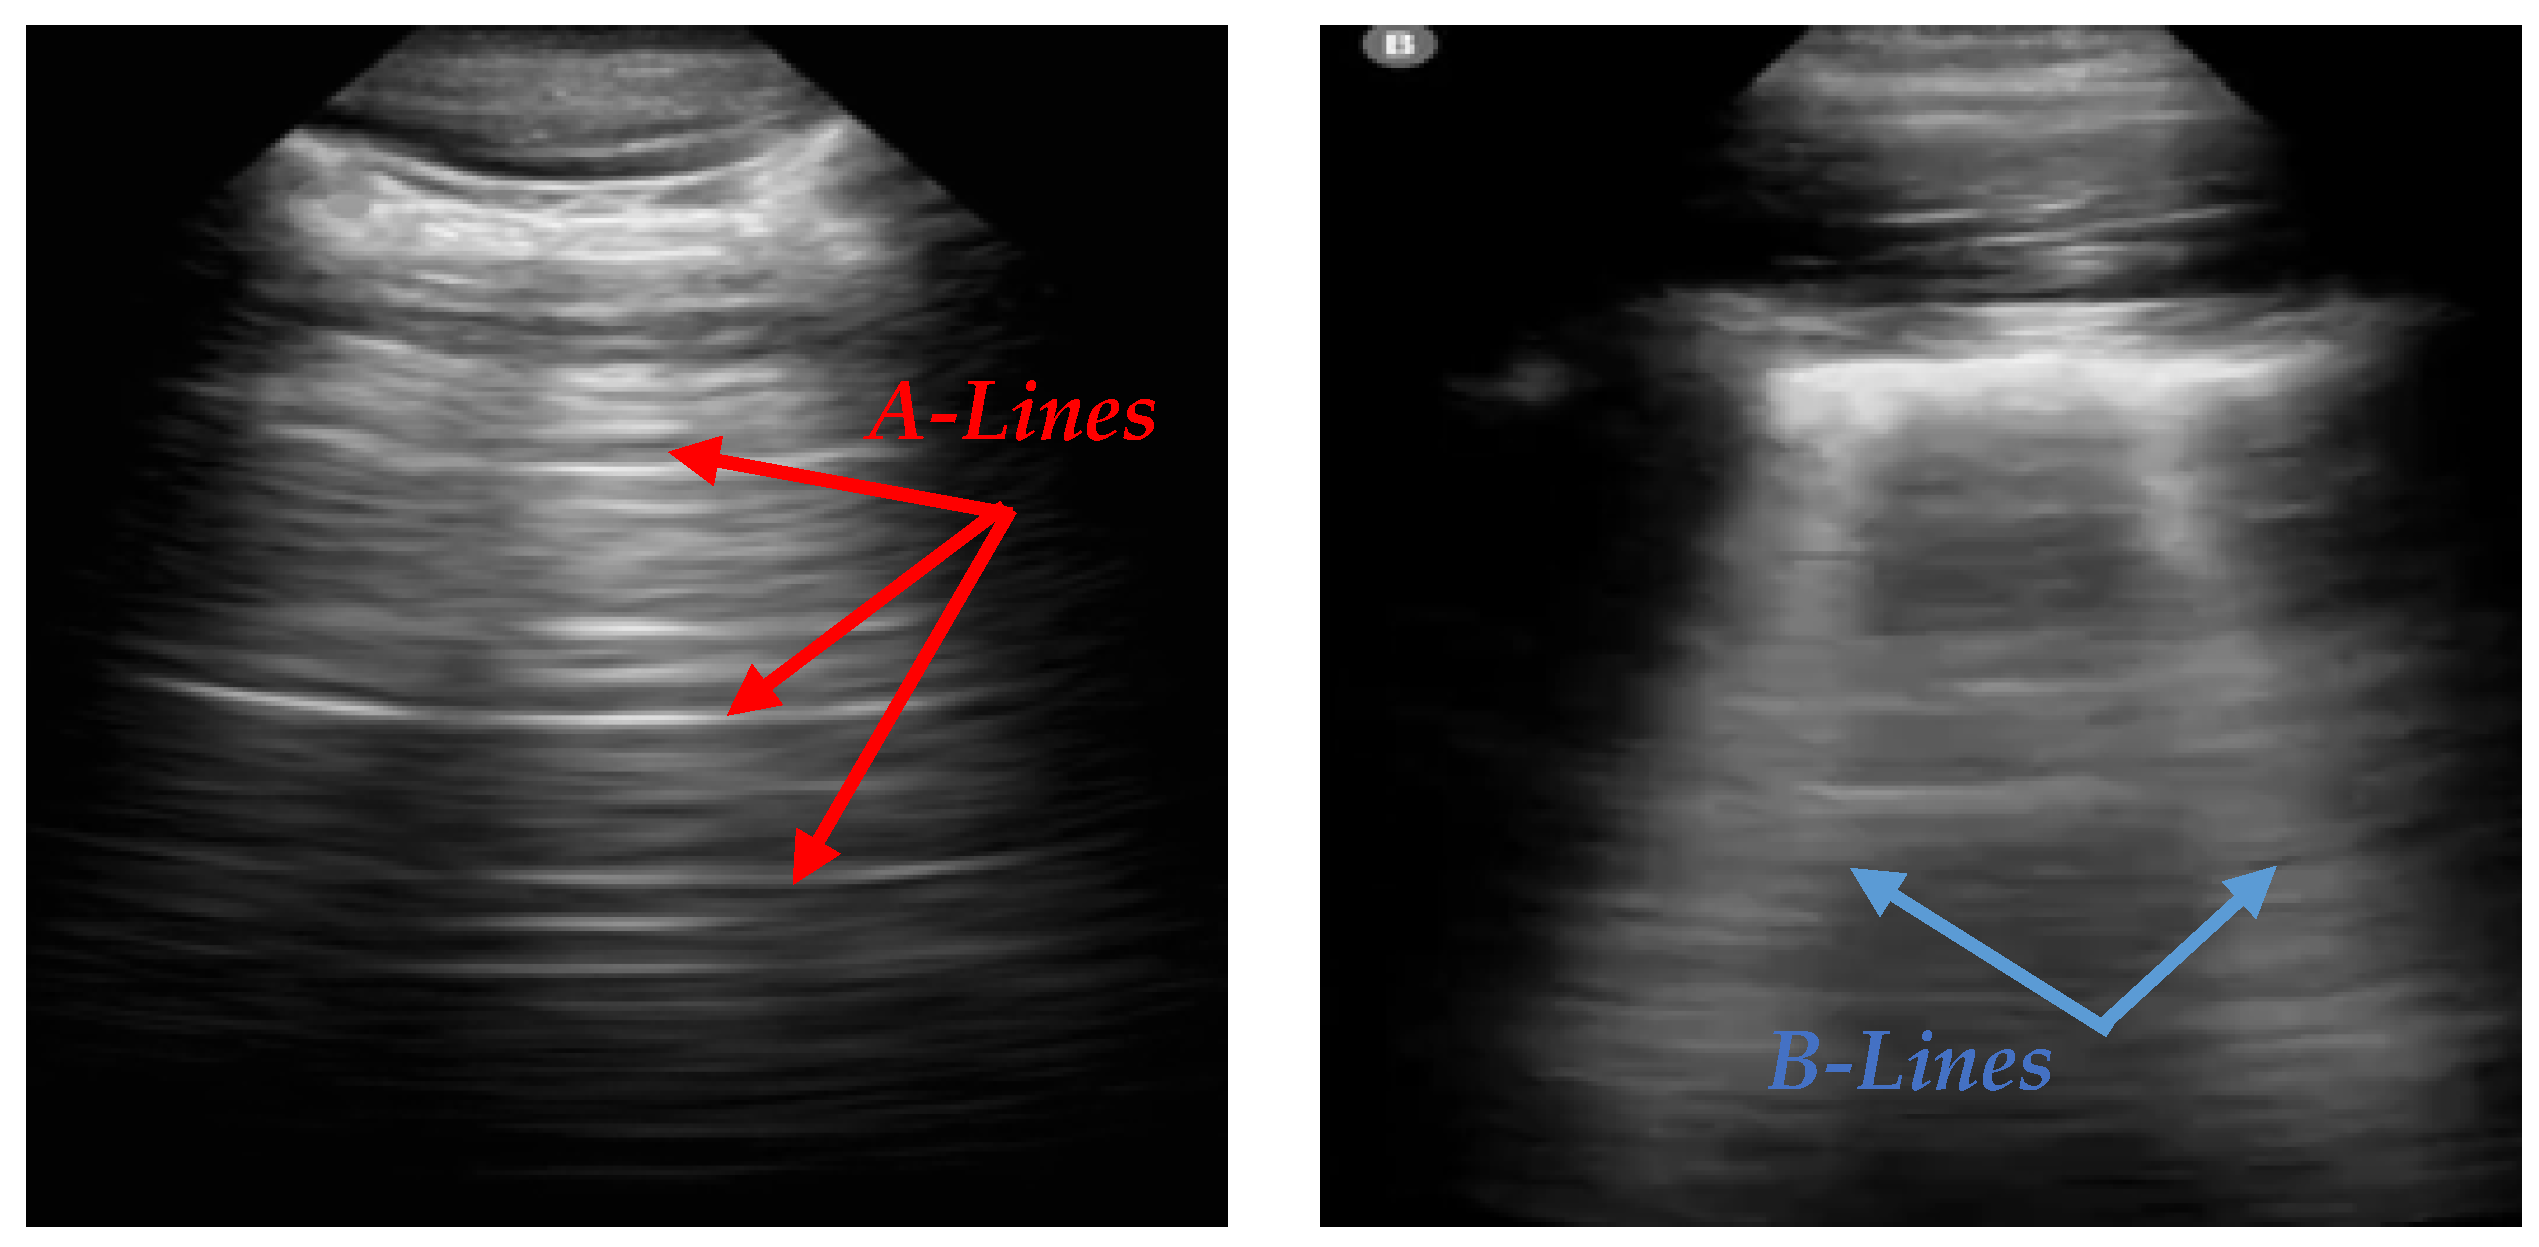
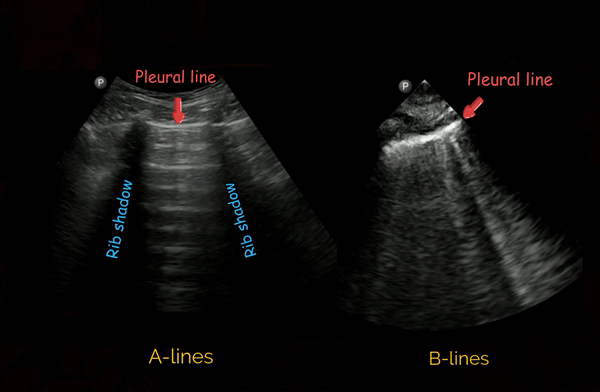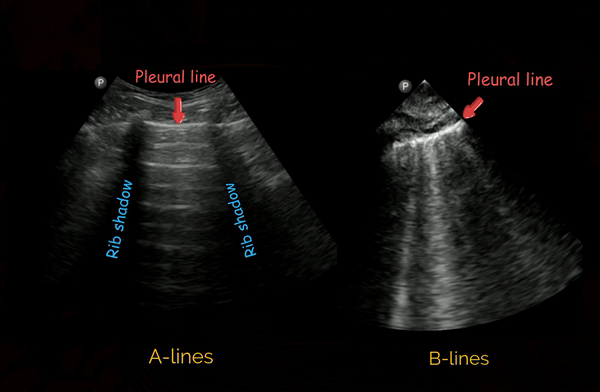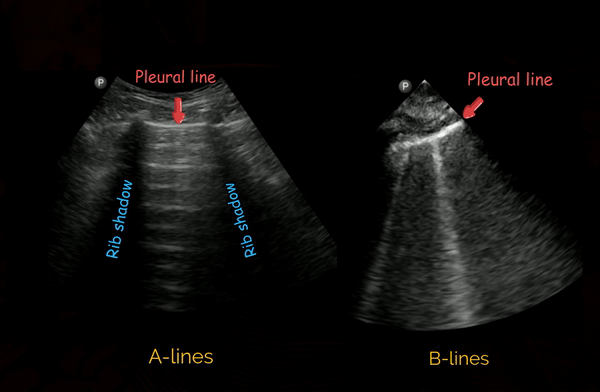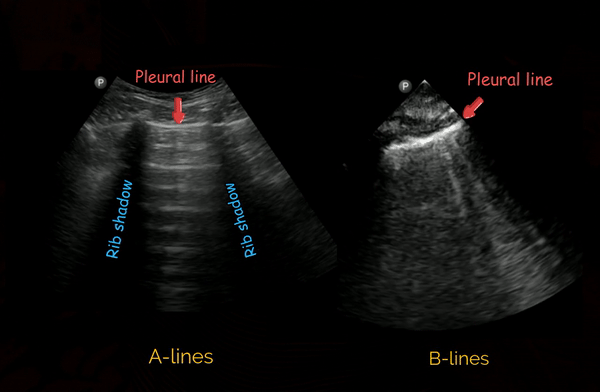
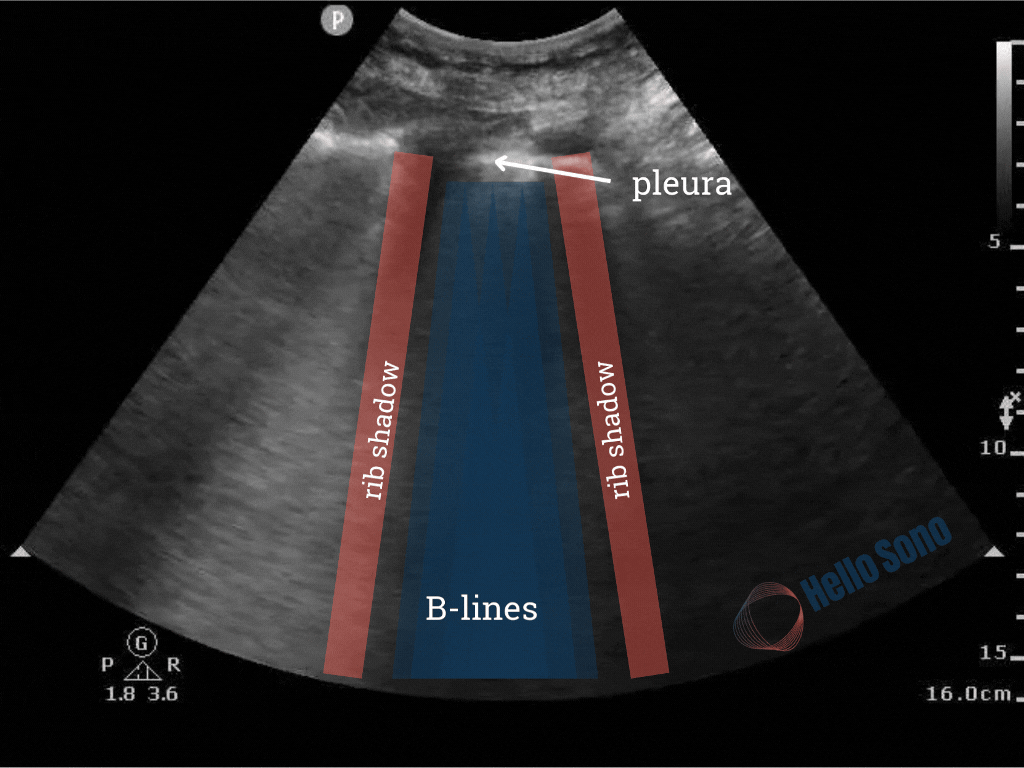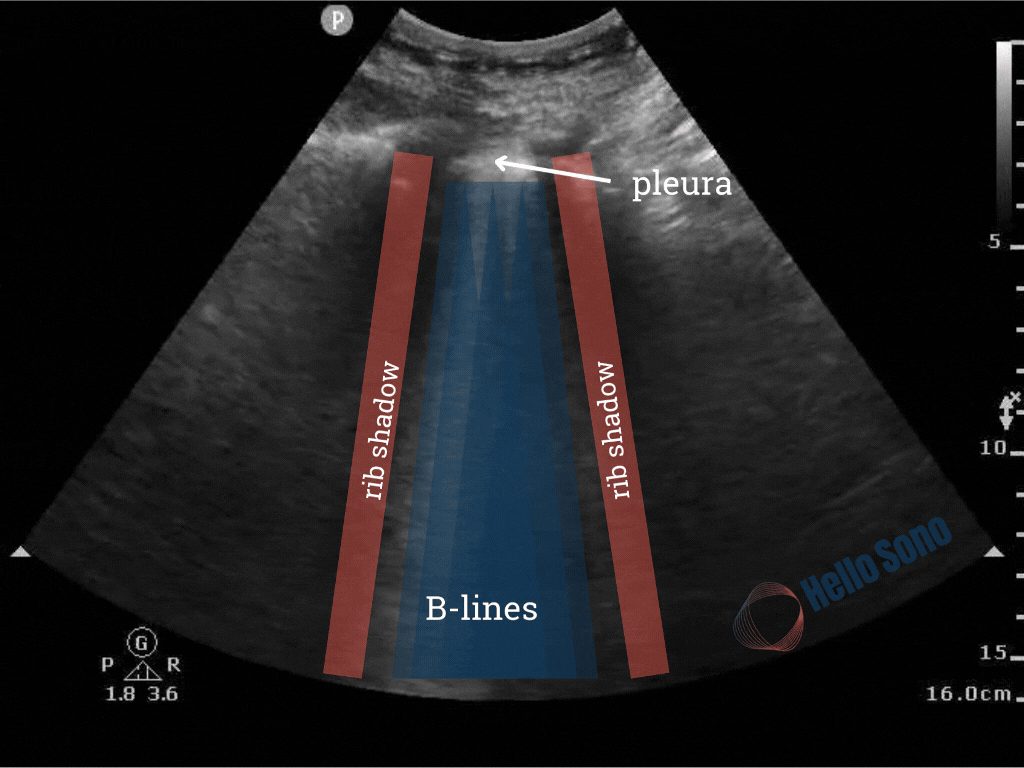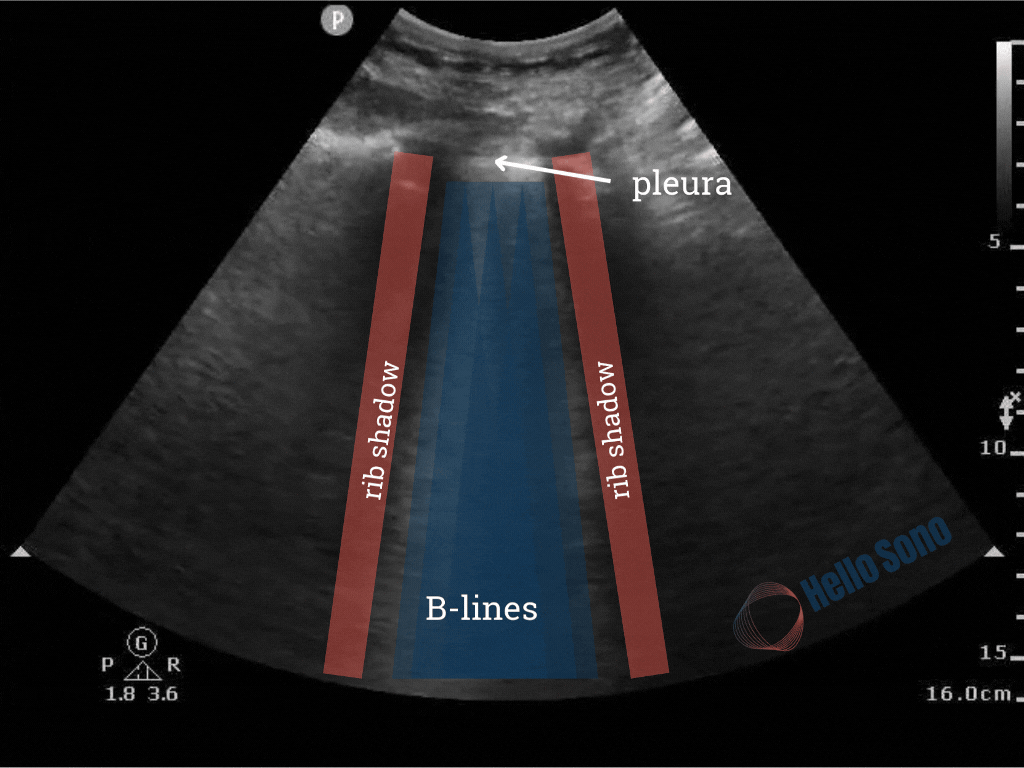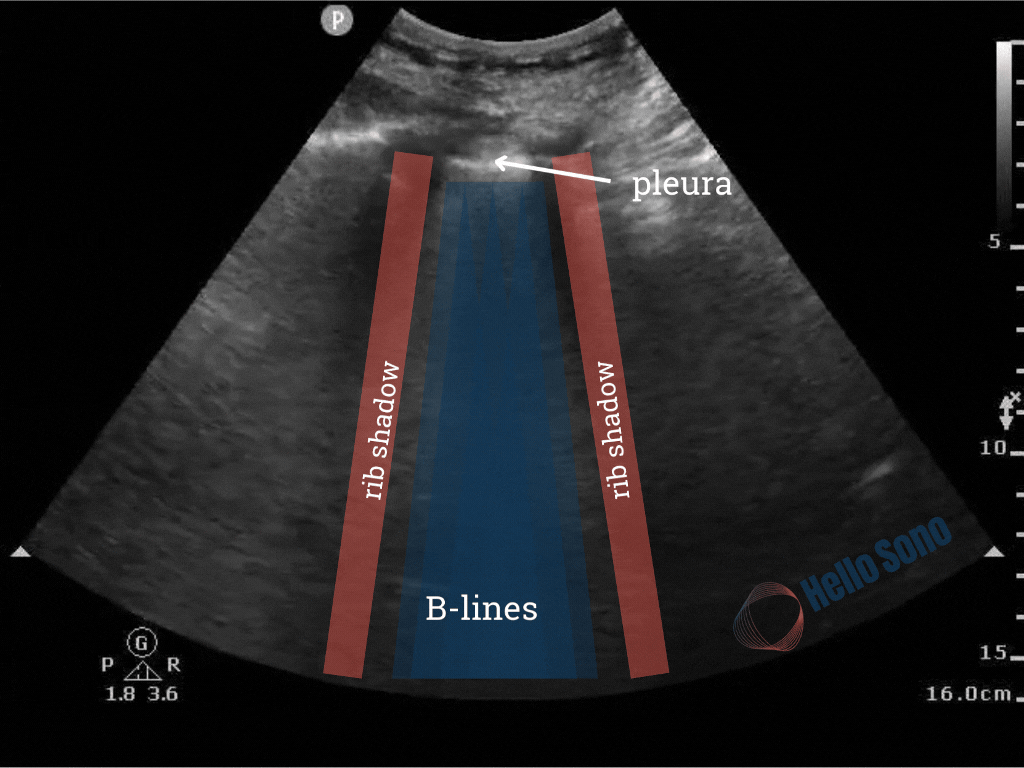
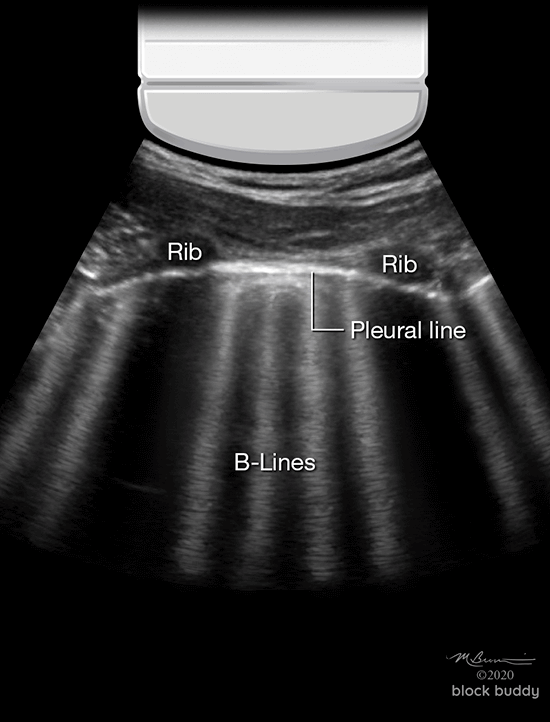
Most sonographers learn about these artifacts in their first month of pulmonary scanning. They show up as bright, vertical bands shooting down from the pleural line, erasing the normal horizontal reverberation echoes. You see them constantly in lung ultrasound and you will probably overcall them a few times before your pattern recognition settles in. I have been doing emergency and critical care imaging for over a decade and I still catch myself second-guessing a bright artifact every now and then. The mechanism is straightforward. When the ultrasound beam hits the pleural line, part of the energy reflects back and forth between the transducer and the tissue interface. In a normal lung you get A lines, which are horizontal reverberations spaced at regular intervals. But when there is fluid, thickening, or other changes in the subpleural interstitium, the reflections get redirected into vertical columns that look like comets tails or laser beams depending on which textbook you read. These are the B lines. They originate at the pleura and extend to the far field without fading, which is the key visual cue that separates them from other bright artifacts.
Understanding B Lines On Ultrasound
There is a practical way to check whether what you are seeing is a true B line or something else that happens to be bright and vertical. Roll the probe gently. True B lines move with the transducer. They maintain their attachment point along the pleural line throughout the entire sweep. If the vertical artifact stays anchored to one spot on the pleura and moves rigidly with the probe, it is a B line. If it seems to float independently or detach when you change angle, it is something else and you should stop calling it a B line. Here is a specific problem I ran into repeatedly early in my practice. I was scanning a patient with known pulmonary embolism who had a small anterior pneumothorax on the right side. At one intercostal space I saw a bright vertical artifact that I initially dismissed as a B line. It was only when I swept more laterally and the artifact suddenly vanished that I realized this was a pseudo-B-line caused by the edge of the pneumothorax creating a strong reflector at an oblique angle. The artifact looked identical to a true B line on that single sweep plane. The workaround I use now is simple but requires discipline. Once I see a solitary vertical artifact, I systematically scan two adjacent intercostal spaces on either side before committing to a diagnosis. A true B line will appear in multiple adjacent ribs because the pathology causing it is distributed through the interstitium. An isolated artifact that appears only in one specific window is almost never a real B line. The number of B lines matters clinically. Two or more per view in any given intercostal space, when present bilaterally outside the lung bases, meets the standard threshold for interstitial syndrome. This is not a suggestion. Papers from the European Society of Emergency Medicine and other groups established this cutoff through validation studies comparing ultrasound findings against CT and clinical outcomes. When I report interstitial syndrome I am saying that the patient has excessive fluid or inflammation in the lung interstitium, and the differential diagnosis includes pulmonary edema, pneumonia, interstitial lung disease, and ARDS. B lines alone do not tell you which one it is.
One thing most beginners miss is that B lines can be present in normal lungs under certain conditions. A single B line per intercostal space is common in older patients simply because the pleura becomes slightly irregular with age. I have seen healthy volunteers in their seventies with three or four B lines in the anterior zones and nothing abnormal on chest imaging. If you start panicking at every vertical artifact you see you will generate unnecessary workups. The bilateral symmetric distribution and the count matter more than any single artifact. Also, B lines disappear quickly when the patient sits up or is positioned to allow gravitational redistribution of fluid. I routinely re-scan patients after adjusting their position to confirm that the artifacts are truly fixed and not just dependent fluid shifting around. There is another nuance that does not get enough attention. B lines are highly operator-dependent and they are affected by probe pressure. When you press the transducer firmly against the skin you can actually compress the subcutaneous tissue enough to create artificial vertical reverberations that mimic B lines. This is more common in thin patients where there is minimal soft tissue between the probe and the chest wall. The fix is to use minimal contact pressure and let the gel do the work. I usually start with a light sweep and only increase pressure if I need better resolution, then I verify that the artifacts do not appear or disappear as I modulate that pressure.
Get the Full Details

What B Lines Cannot Tell You
The biggest limitation of B lines is that they are nonspecific. You cannot distinguish cardiogenic pulmonary edema from non-cardiogenic edema using B lines alone. A patient with sepsis induced ARDS can have exactly the same number and distribution of B lines as a patient with congestive heart failure. The clinical context and additional findings like IVC collapsibility, cardiac function, and response to diuretics determine the actual etiology. If you rely solely on B line counting you will misclassify patients and make the wrong treatment decisions. B lines also fail in several specific anatomical scenarios. They are unreliable in patients with severe subcutaneous emphysema because the air in the soft tissues creates overwhelming reverberation artifacts that obscure everything underneath. They are less useful in obese patients with thick chest walls because the signal attenuation prevents the vertical columns from reaching the far field where you need to see them to count them. In those cases, I supplement with clinical assessment and sometimes proceed directly to CT if the patient is stable enough to transport. The ultrasound is still worth doing because it takes thirty seconds but I do not let a negative or incomplete exam reassure me when the clinical picture suggests otherwise. Lung ultrasound is also limited by the presence of large consolidations or tumors that distort the pleural line. When the anatomy is destroyed, B line counting becomes impossible and you are left with whatever structural information you can extract from the abnormal area. This is not a failure of the technique, it is just the boundary of what it can do. B lines were never designed to replace CT. They are a rapid screening and monitoring tool that gives you information about the interstitial compartment faster than any other bedside method. Used appropriately they save time and reduce radiation exposure. Used blindly they create false certainty.