Why Parents Keep Misreading Growth Percentiles
I've been helping families interpret pediatric growth data for over a decade now, and the same mistakes keep coming up. The biggest one isn't even technical—it's assuming a single data point tells you anything meaningful about a baby's health. A one-off reading at the 30th percentile means almost nothing on its own. What matters is the trajectory over time, and most people don't realize that until they've seen a few cases go sideways because someone panicked at the wrong visit. The tools on the market for this vary wildly in accuracy. Some are fine for rough estimates. Others are built on outdated reference data or contain calculation errors that compound quickly. I stopped trusting random web calculators years ago after finding one that gave a result two full percentiles off from the CDC's own tables for the same input. That kind of drift doesn't seem like much until you're explaining to a parent why their pediatrician's reading doesn't match what some app told them online.
How a Baby Growth Chart Calculator Actually Works
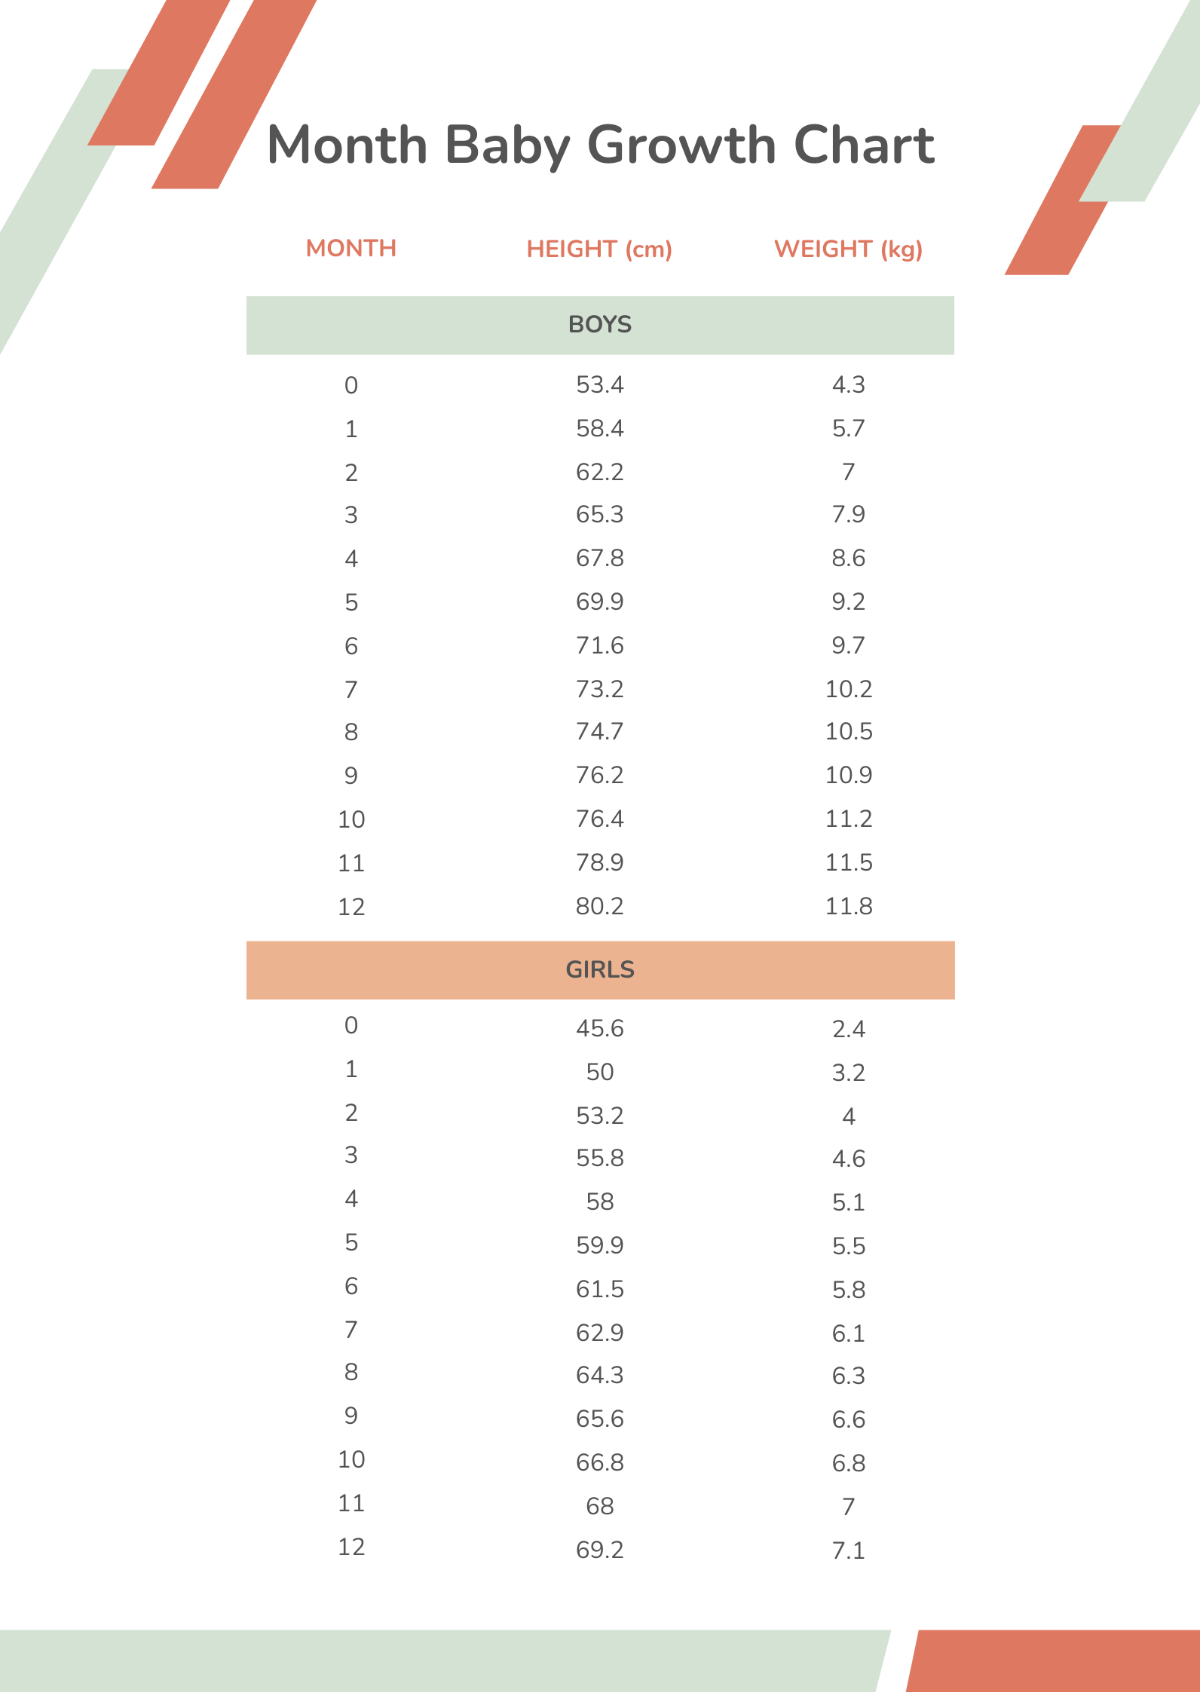
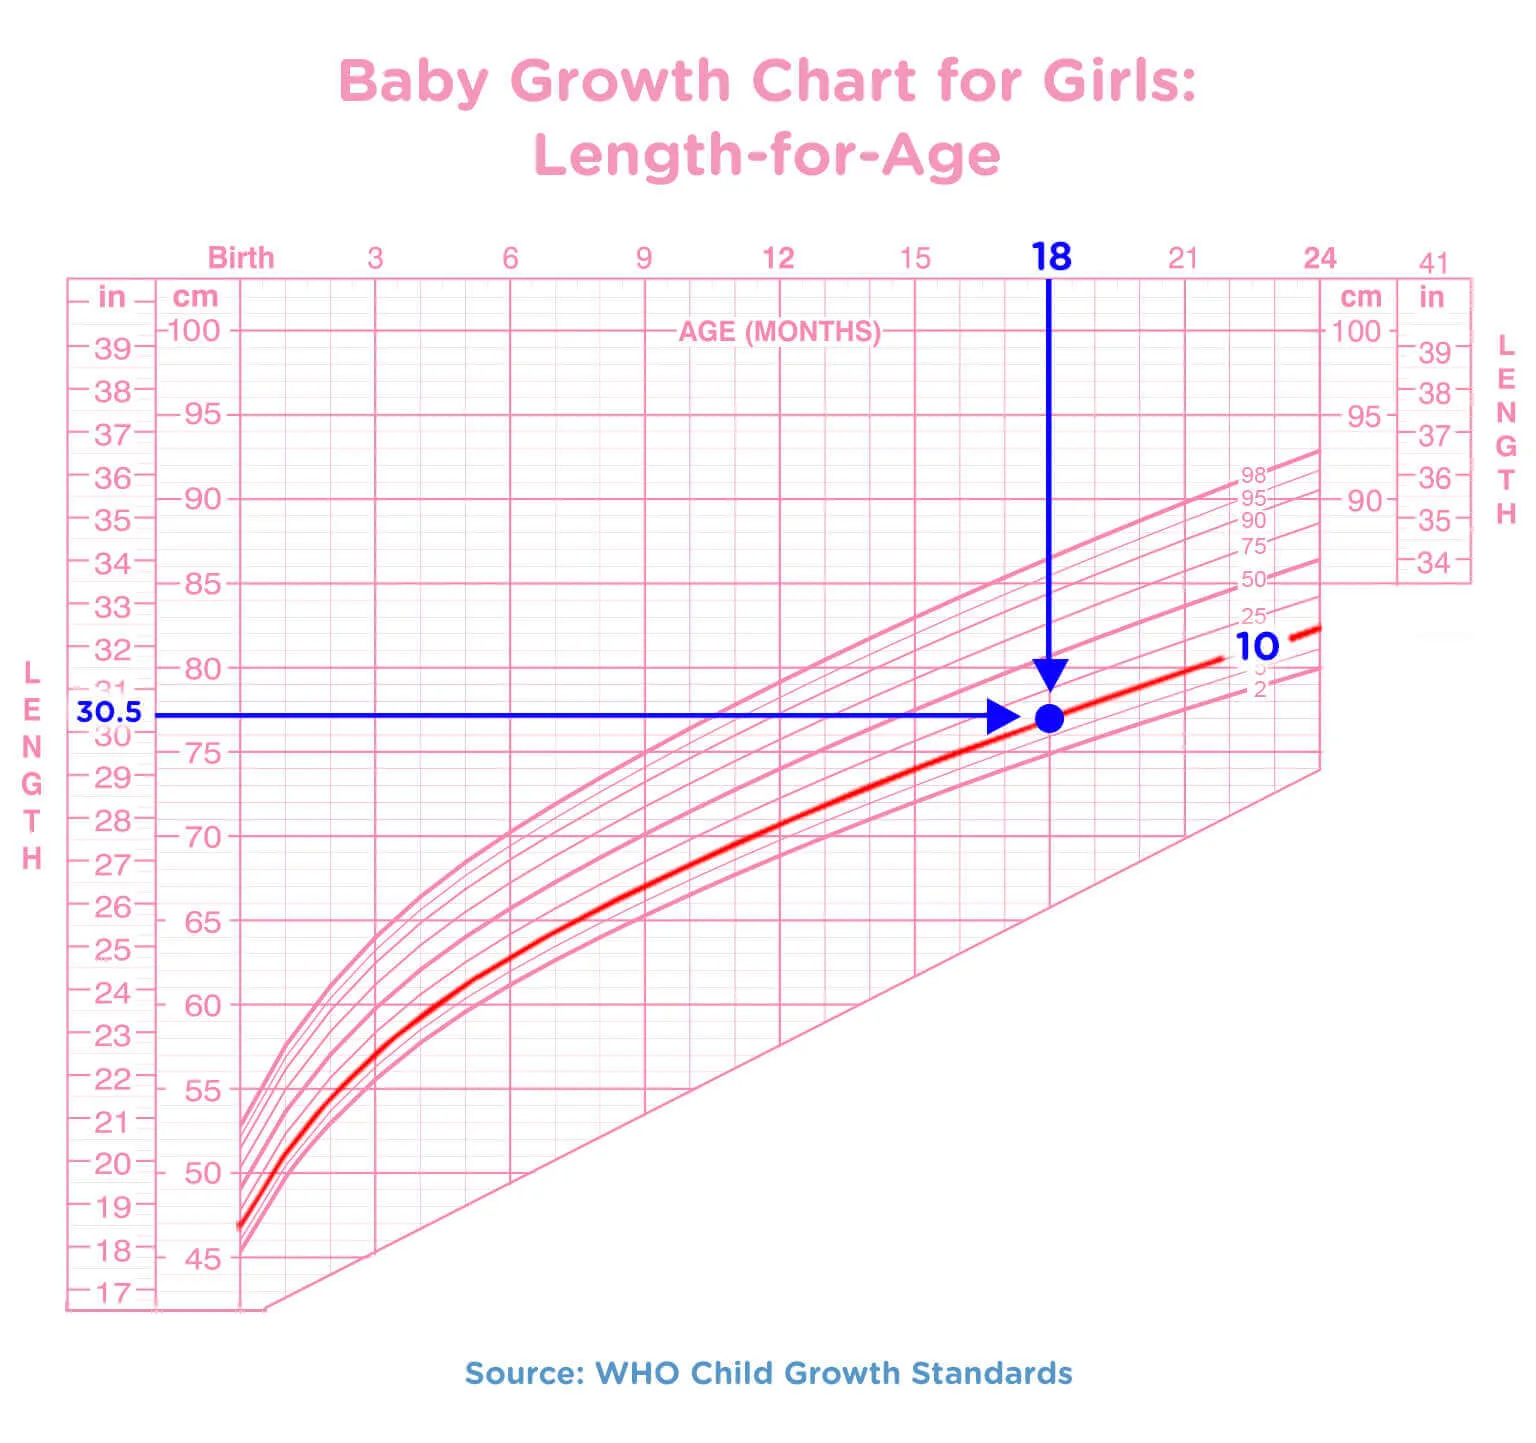
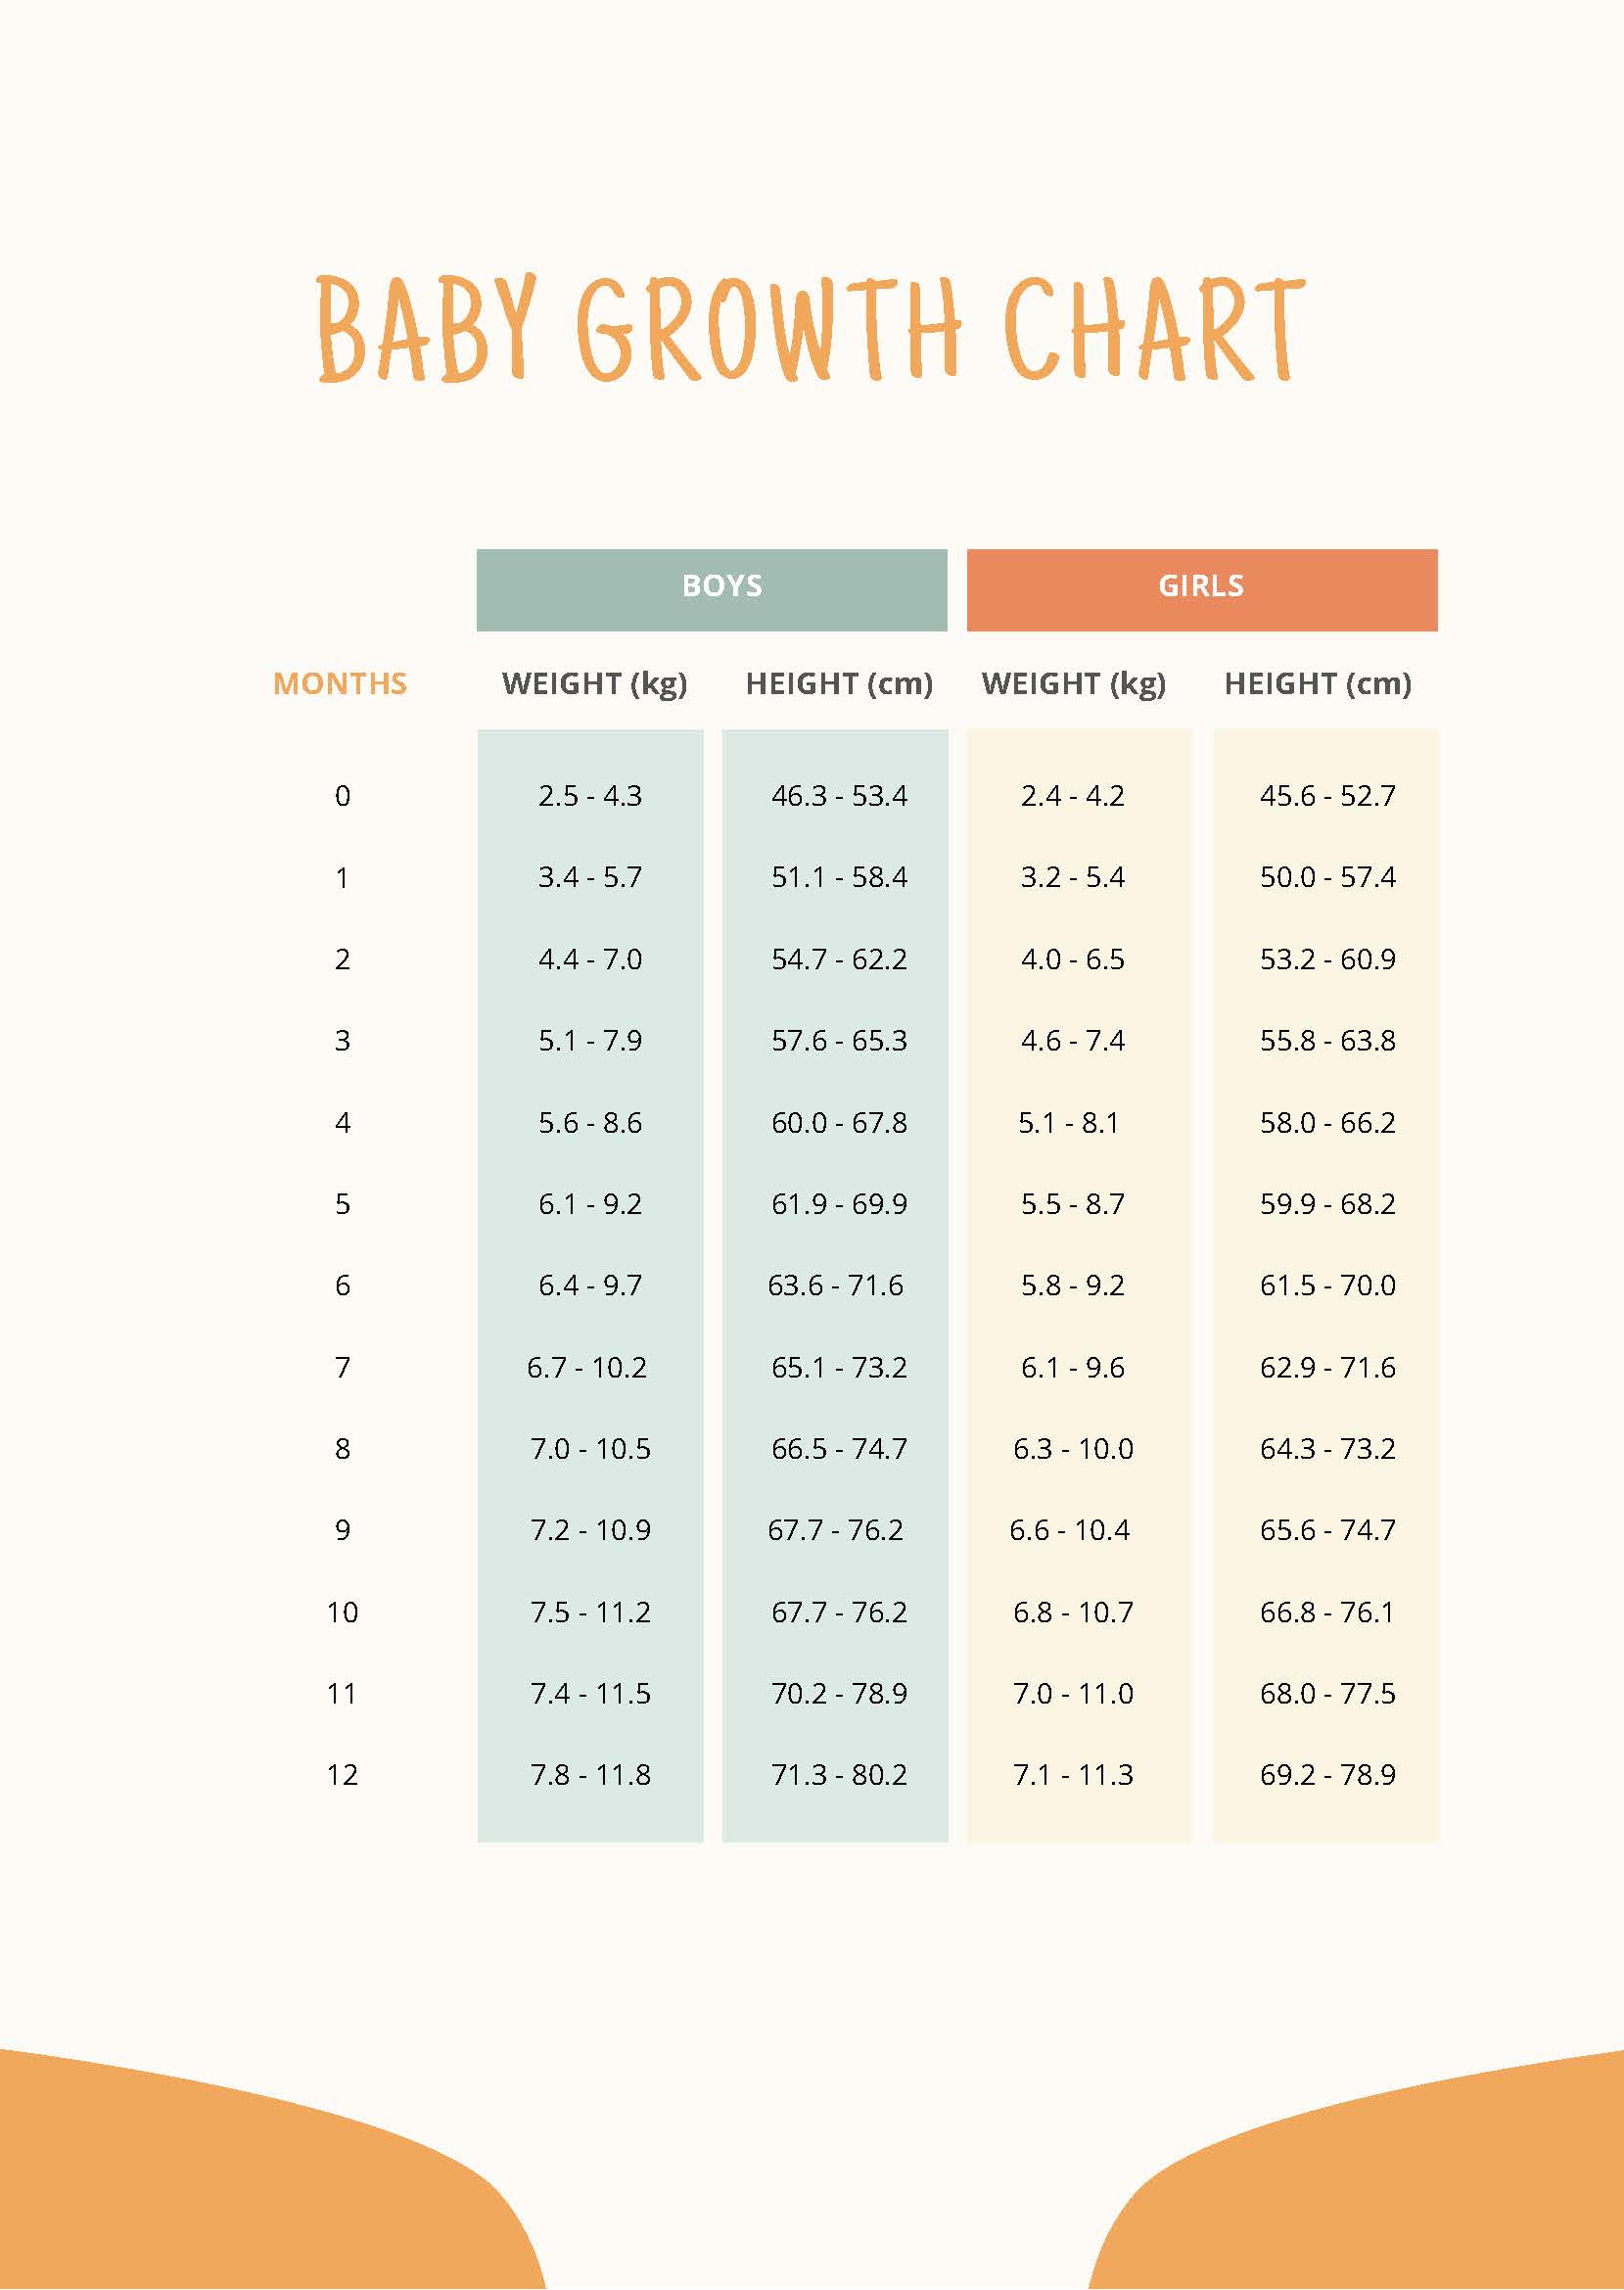
At the core, these calculators take three inputs: the child's sex, birth date, and either length/height plus weight. From there, they cross-reference against established growth standards—typically the WHO standards for children under two years old and the CDC growth charts for ages two through twenty. The output is a set of percentile rankings that place the child's measurements relative to a reference population. The WHO standards were developed differently than the older CDC charts. They track breastfed infants raised in optimal conditions across multiple countries, which produces slightly different curves, especially in the first six months. The CDC charts are based on mostly formula-fed, predominantly white American populations from the 1960s through 1980s. So which reference a calculator uses matters, and not every tool makes that clear. Here's the part most people miss: percentile ranking alone isn't a diagnosis tool. It's a descriptive one. A child consistently tracking at the 5th percentile for weight who is otherwise healthy, meeting milestones, and feeding well is usually fine. A child who drops from the 50th percentile to the 10th between two visits is a different story entirely, and that crossover is what clinicians actually flag.
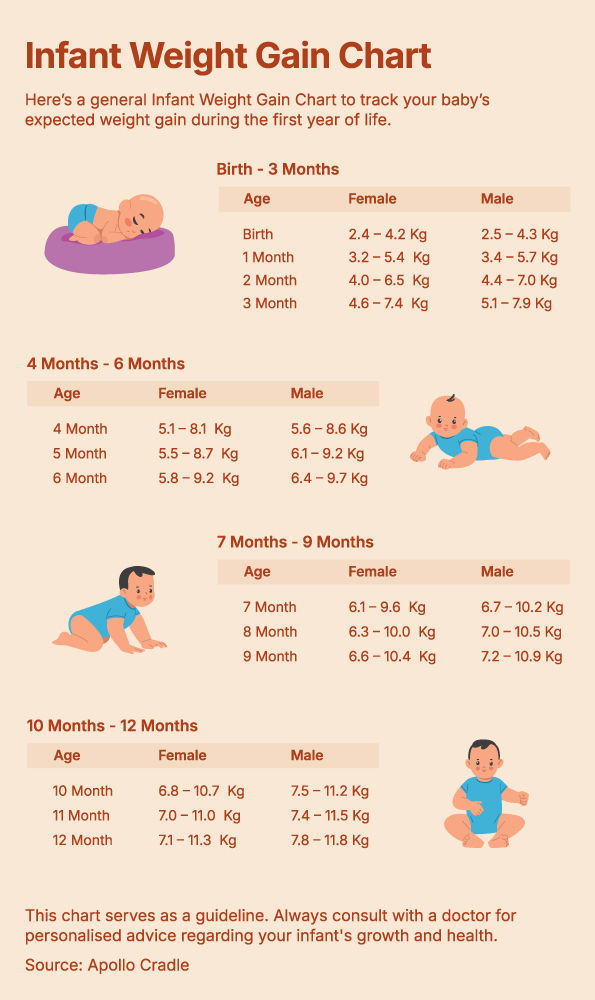
I remember one specific case that made me rethink how I'd been using these tools. A mother brought her six-month-old in because a calculator she found online flagged her baby's weight at the 2nd percentile, which triggered a panic about failure to thrive. I recalculated using the actual WHO growth standards with the same numbers, and the baby was right around the 10th percentile. The online tool was using CDC charts on a six-month-old, which compresses the lower end and pushes values downward artificially. That's a real problem—mixing reference populations without accounting for it creates false alarms, and I've seen it happen repeatedly with people running calculators that don't specify which standard they're applying.
Get the Full Details
What to Check Before You Trust Any Calculator
The first thing I look at is whether the tool clearly states which reference population it uses. WHO for under two, CDC for over two—that's the standard clinical approach in the United States. If a calculator uses one or the other across all ages, it's wrong somewhere. I also check whether it accepts gestational age for premature babies. A term-based calculation on a baby born at thirty-two weeks will look catastrophically low on a standard chart, and the correction should account for gestational age until about two years corrected age. Some calculators only handle weight-for-age. The clinically useful ones do weight-for-length too, which is actually the better marker for acute malnutrition or overweight status in infants under two. Body mass index calculations don't really enter the picture until after the first birthday, and even then they're less reliable than weight-for-length during the infant period. A tool that skips weight-for-length is giving you an incomplete picture. Accuracy testing is another thing worth doing. Take any reliable calculator you're considering, punch in a known example, and compare it to printed growth charts from the CDC or WHO websites. If the results diverge by more than half a percentile step, you've found a rounding issue or a data error. These things add up, especially for borderline cases where a child sits right near a percentile boundary like the 3rd or 97th.
Common Pitfalls That Waste Everyone's Time
The most annoying problem I deal with repeatedly is parents measuring their baby at home and plugging those numbers into an online calculator, then showing up at the clinic already stressed. Home measurements are harder to get right than people realize. A toddler who won't stand still adds half an inch to height. A scale that hasn't been calibrated runs several ounces off. Those small errors shift percentiles in ways that matter more at the tails of the distribution curve, where the spacing between percentile lines is tighter. Another issue is interpolation. Most calculators give you a clean percentile number, but the real growth charts are continuous curves, and the exact percentile depends on how smoothly the underlying mathematical model handles values between published data points. Different calculators use different interpolation methods—some linear, some cubic spline—and that can produce slightly different results at the edges of the reference range. It's a subtle thing, but in borderline clinical situations, those fractions of a percentile matter. There's also the problem of rapid catch-up or catch-down growth, especially in adopted children or those coming out of foster care. A child who arrives at eighteen months severely underweight may surge upward through the percentiles over the next year as nutrition improves. That's normal and expected, but parents and even some clinicians read it as abnormal if they're not expecting it. The calculator will plot the numbers correctly, but it won't tell you whether the pattern is physiologically appropriate without context about the child's history.
When Growth Chart Calculators Fall Apart Completely
These tools are useless for babies with certain medical conditions that affect growth independently of the standard references. Children with Down syndrome, Turner syndrome, achondroplasia, chronic kidney disease, or severe congenital heart disease have their own growth patterns that don't fit the general population curves. There are specialized growth charts for some of these conditions, but a generic Baby Growth Chart Calculator won't account for any of them, and using standard percentiles on a child with a diagnosed condition can produce misleading results that actually delay appropriate evaluation. They also don't handle asymmetrical growth well. A child whose head circumference is tracking normally but whose weight is dropping, or vice versa, needs more than a percentile number to understand what's happening. The calculator gives you four separate data points—weight, length, head circumference, and weight-for-length—but it doesn't synthesize them into a clinical picture. That synthesis requires a person who knows the child's full history, family context, feeding patterns, and developmental trajectory. Preterm infants are another edge case where standard calculators struggle. Even when a tool asks for gestational age, the math for adjusting preemie growth curves isn't standardized the way you'd hope. Some clinicians use corrected age, others use postmenstrual age, and the difference shifts the plotted position on the chart. The discrepancy between methods can be several percentile points during the first year, which is enough to change a watchful waiting recommendation into a referral if you're sitting near a clinical threshold.

What Actually Happens When You Use One Correctly
If you're a parent trying to make sense of your pediatrician's growth charts, the most practical use of a calculator is as a study aid rather than a diagnostic tool. Look up the numbers yourself before the appointment, understand what percentile the clinic is plotting, and prepare questions about the trend rather than fixating on a single number. This approach actually changes the dynamic of the visit because you're asking informed questions instead of reacting emotionally to a percentile you don't fully understand. Clinicians use these tools differently. We're not looking for exact percentiles—we're looking for trajectories. Two consecutive visits that show a child maintaining their percentile band, even if that band is at the low end, is generally reassuring. Two visits showing a consistent drift across percentile lines, even within the same broad category, is what triggers further investigation. The calculator gives you the numbers, but interpreting the pattern is where clinical judgment comes in, and no algorithm can replace that for individual children. The best calculators I've found in practice also generate printable charts or allow you to import multiple data points and see a plotted curve. A single percentile number is informational at best. A trend line spanning six months or more of data is what actually helps someone understand whether a child is growing appropriately. I recommend ignoring any tool that doesn't let you plot serial measurements, because it's giving you less than half the relevant information.