Why Your Lower Back Hurts After A Pap Smear And What To Actually Do About It
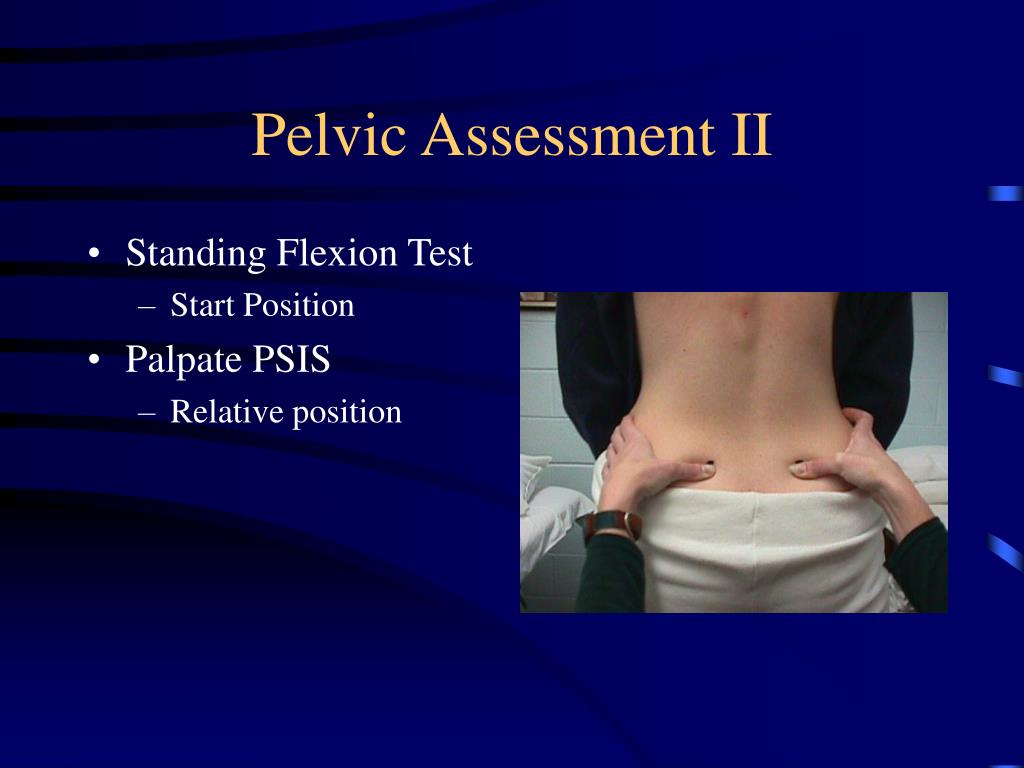
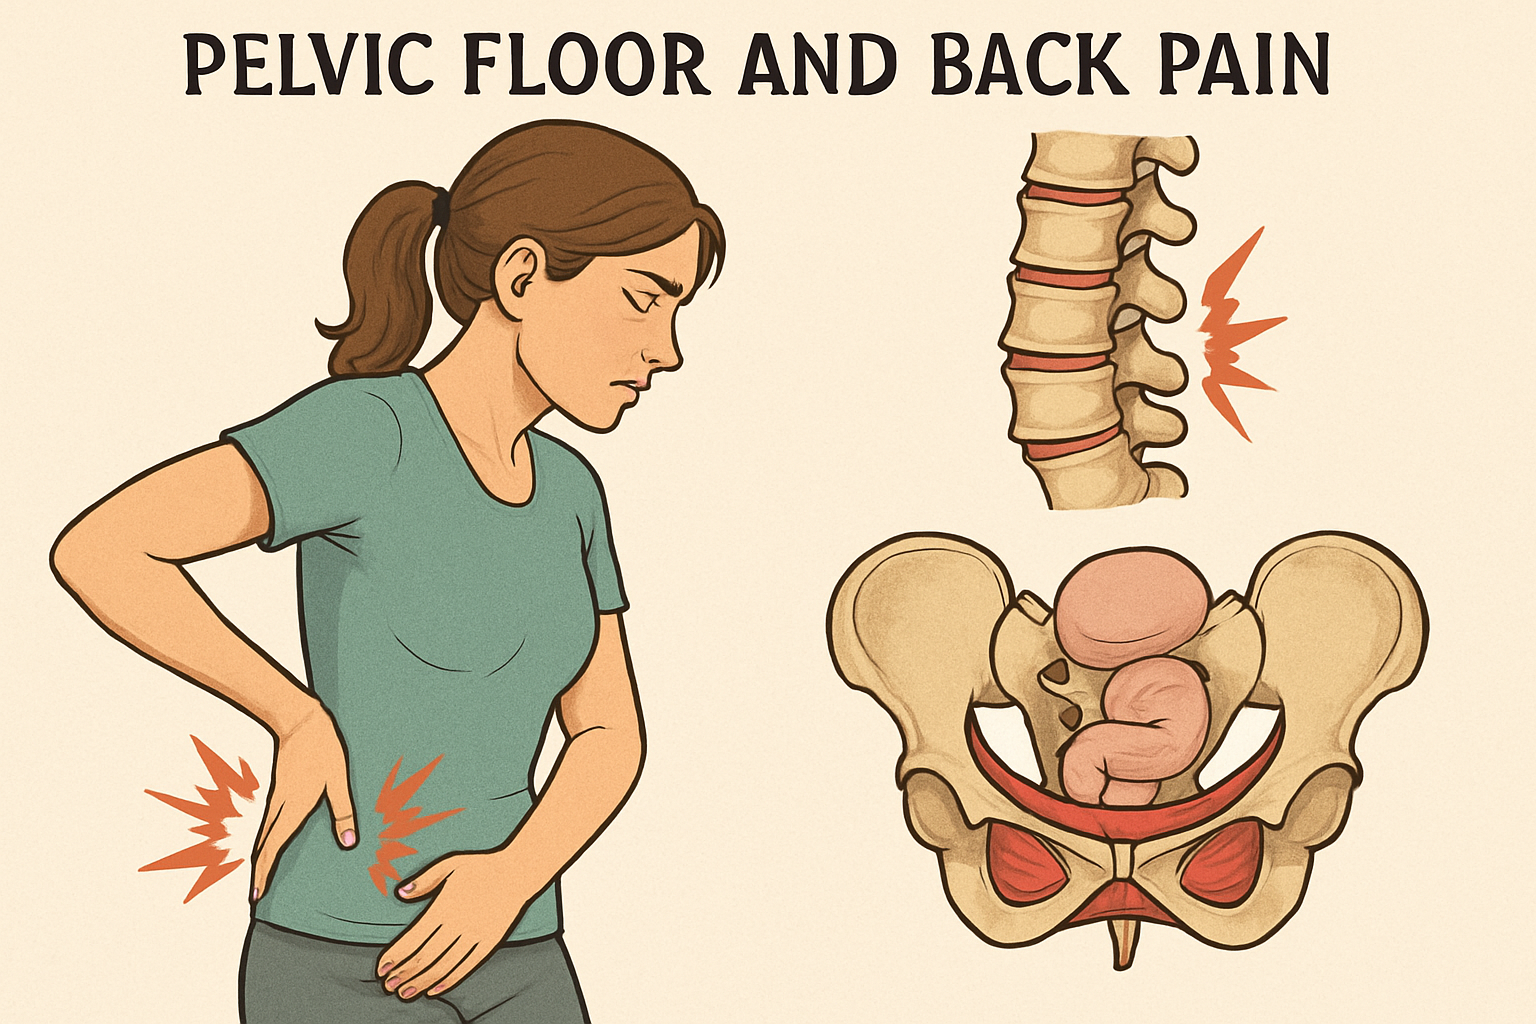
It is not normal to feel fine right after and then wake up the next morning with a stiff, aching lower back. I have seen this come up repeatedly in urogynecology follow-up clinics and on patient forums where people are genuinely confused because they did nothing out of the ordinary during the exam itself. The speculum insertion is straightforward, the cervical sweep is quick, and then two days later your sacroiliac joint feels like someone jammed a wrench into it. The mechanism is mechanical rather than mysterious. When you lie in the lithotomy position with your legs in stirrups for an extended period, your hips are externally rotated and your lumbar spine is either hyperlordosed or flattened depending on how your pelvis sits in the stirrups. For most patients the iliopsoas and piriformis are already tight from sitting at desks or driving all week. The exam pushes them further into a shortened or overstretched state, and that tension refers pain directly into the lumbar paraspinals and sacroiliac region. You are not damaging anything structural. You are aggravating a muscle group that was already loaded. There is also a cervical component that people overlook. The speculum retracts the vaginal walls, which pulls on the uterosacral ligaments, which attach to the sacrum. If your uterus is retroverted or if you have any degree of pelvic organ prolapse, that traction can create a dull, deep ache that radiates straight through to the low back. I had a patient once who developed sharp left-sided back pain specifically two days after a cervical biopsy, and we spent twenty minutes ruling out renal issues before I realized the biopsy site was on the left posterior cervix and the referral pattern was completely consistent with uterosacral ligament irritation. She felt better after three days of heat and naproxen. No intervention beyond that was needed.
The second major contributor is pelvic floor hypertonicity. A lot of patients go into the exam room already braced because they are anxious or because they have a history of painful exams. The examiner pushes the speculum in and the pelvic floor muscles clamp down reflexively. That acute spasm can persist for hours or even days after the visit. The pain sits deep in the buttock and tracks into the lower lumbar region. It is easy to mistake this for a disc problem when it is purely myofascial.
What Actually Helps and What Does Not
Heat is the single most reliable intervention I have seen work consistently. A heating pad on the low back for twenty to thirty minutes twice a day starting the evening of the exam will reduce the referred pain in the vast majority of cases. Nonsteroidal anti-inflammatories like ibuprofen or naproxen taken at the first sign of discomfort are also effective because they blunt the inflammatory cascade in the ligaments and musculature. I usually tell patients to take the first dose before they even leave the clinic if they know they are prone to this. Gentle hip flexor stretching helps too, but not the aggressive kind you see on social media. A half-kneeling psoas stretch held for forty-five seconds on each side, performed slowly without bouncing, is enough. Anything more intense will just irritate the already inflamed tissue further. A warm bath with Epsom salts can provide additional relief, though the magnesium absorption through the skin is minimal and the benefit is mostly from the heat and buoyancy. What does not help is staying in bed all day. Movement is actually necessary to prevent the muscles from seizing up further. A short walk of ten to fifteen minutes, gentle cat-cow stretches on the floor, and avoiding heavy lifting for forty-eight hours is the realistic approach. Deep tissue massage of the lower back immediately after the exam will make things worse because the tissues are already in a protective spasm state and need calming, not forceful manipulation.
Get the Full Details

When To Actually Be Concerned
Most post-exam back pain resolves within forty-eight to seventy-two hours. If it lasts longer than that, or if you develop fever, unusual vaginal discharge, heavy bleeding that soaks a pad in an hour, or pain that radiates down your leg past the knee, you need to contact your provider. Those are not normal sequelae of a routine pelvic exam. Fever and discharge could indicate an ascending infection, especially if a biopsy was performed. Leg radiation past the knee suggests nerve root involvement that is unrelated to the mechanical strain of the exam position. One edge case that rarely gets discussed is post-procedural vasovagal response. A significant number of patients experience a drop in blood pressure and heart rate during or immediately after the exam, particularly if cervical manipulation was involved. This can leave you dehydrated and fatigued for the rest of the day, and dehydration amplifies muscle tightness and back pain. Drinking two extra glasses of water after the exam and sitting for a few minutes before standing up can prevent this downstream effect entirely. I learned this the hard way when a patient came back two weeks later furious because she had the same back pain after every exam, and it turned out she was never being told to hydrate beforehand or rest afterward.
Prevention For Future Exams
If you know you are prone to back pain after pelvic exams, there are a few practical steps you can take. Request a smaller speculum if you have ever had a painful one before. Ask the examiner to support your lower back with a rolled towel when you are in the stirrups. Breathe out slowly as the speculum is inserted rather than holding your breath, which tenses your core and pelvic floor unnecessarily. And do not skip the post-exam rest period in the clinic. Sitting for five minutes before getting dressed and walking out reduces the likelihood of a vasovagal episode and gives your muscles time to reset. The bottom line is that back pain after a pelvic exam is almost always a transient musculoskeletal issue caused by positioning, muscle tension, and ligament traction. It is uncomfortable and it is real, but it is not indicative of a serious problem in the vast majority of cases. Heat, gentle movement, and time are the standard treatment. Persistent or worsening symptoms should always be evaluated by your provider, but an overnight stiff back is about as dramatic as it typically gets.