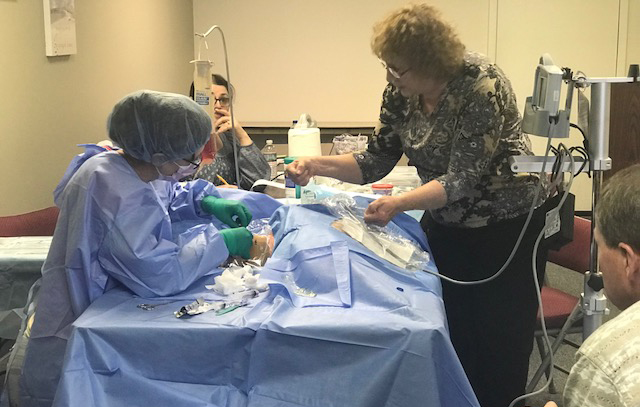
PICC Line Insertion: What Actually Happens in the Room
Most training programs walk you through the steps in a clean, linear order, and that is fine for a textbook. The real job is messier. You are inserting a thin flexible catheter through a peripheral vein and threading it until the tip sits in the superior vena cava. That sounds simple enough. It is only simple when the anatomy cooperates and you have time. Both things are rare.
I have been doing this for over a decade now, and I still get a small knot in my stomach the first time I see a patient whose vein looks like a coil spring on ultrasound. The training teaches you a perfect path. The body rarely agrees.
What Bard Picc Line Insertion Training Actually Covers
The Bard curriculum is built around their specific kit: the preloaded catheter, the peel-away sheath, the insertion needle, and the stylet. Their system uses a soft tip design that is meant to glide through tight venous angles without catching. The training module walks you through the percutaneous technique, usually via the basilic, brachial, or cephalic vein, and shows you how to advance using guidewire-assisted insertion when necessary.
Most programs also cover post-insertion verification. That means checking the external catheter length against the radiograph or using intracavitary ECG lead placement to confirm tip position before flushing. Skipping the tip check is the easiest way to send a patient home with a malpositioned line and explain it later.
Here is a practical version of how I approach it, stripped down to what matters in a busy unit.
Step one: Locate the vein with ultrasound. Choose the entry point at least two centimeters above the antecubital fossa. Avoid the bifurcation. You want a straight segment where the vessel walls are parallel and the path is clear. Step two: Prep the arm and drape. Apply chlorhexidine and let it dry completely. If you do not wait, the solution tracks under the drape and the site contamination risk jumps significantly. Step three: Anesthetize the entry site. Lidocaine 1% works. I usually inject a small wheal and then a shallow tunnel along the planned tract. Do not rush this step. A twitching patient makes the next phase much harder.
Step four: Insert the needle under direct ultrasound visualization. You want to see the needle tip advance through the anterior wall into the lumen. A quick flash of blood in the hub is confirmation, but do not advance the needle further once you see it. You are past the point of no return. Step five: Pass the guidewire through the needle. Advance it smoothly. Never force it. If you feel resistance, stop and reassess. The wire should track easily into the subclavian and then the SVC. If it coils in the axilla, you have hit a venous angle or a branch. Withdraw the wire slightly, redirect the needle, and try again. Step six: Peel away the sheath over the catheter and advance the catheter itself. Maintain control of the guidewire at all times. Losing the wire inside the patient is not a training failure, it is a bad day. Keep your fingers on it.
Step seven: Confirm tip position. Portable chest X-ray is standard. If you have intracavitary ECG capability, use it as a real-time check before sending for imaging. It cuts down on repeat procedures.
Get the Full Details
BARD Insertion and Removal Skills Training Checklist
I want to talk about something most videos leave out. The first time I encountered a heavily calcified basilic vein during a routine insert, the needle kept slipping off the anterior wall. The plaque was hard and irregular. Standard Seldinger technique was not working. I switched to a transverse approach, visualized the vein from the side, and used a shorter, finer gauge needle to enter just past the calcified segment. The catheter then advanced through a normal section of the vessel without resistance. That workaround saved the procedure. The alternative was referring the patient out and rescheduling, which does not always happen.
There are a few things about Bard systems that people do not expect.
The preloaded design is convenient, but it limits your ability to adjust catheter length before insertion. If you anticipate a long path, measure carefully and mark the catheter before you start. Measuring from the insertion site to the right atrium using surface landmarks is standard, but ultrasound measurement of the vein from entry point to the carina is more accurate. The difference between a properly placed tip and a misplaced one can be two or three centimeters.
Another counter-intuitive point: the peel-away sheath is both a benefit and a liability. It stabilizes the initial insertion and protects the tract. However, the sheath itself can kink if you advance the catheter at an extreme angle. I keep the sheath aligned with the vein axis rather than pulling it back prematurely. Once the catheter is halfway through, then I peel and continue. Doing it the other way around often causes the catheter to buckle inside the sheath.
Let me also address what Bard Picc Line Insertion Training does not solve. Calcified veins are one limitation. Another is severe venous tortuosity, which happens frequently in older patients or those with long-term IV access history. In those cases, the guidewire may track fine but the catheter refuses to follow. Using a J-tipped guidewire and a soft introducer needle can help, but sometimes the only solution is a different entry site. I have switched from basilic to cephalic successfully in cases where the basilic was unusable due to scarring.
There are also contraindications that matter more than the training suggests. Known superior vena cava occlusion, active infection at the insertion site, or ipsilateral mastectomy with lymph node dissection are hard stops. I have seen residents attempt an insert through a previously irradiated field because the protocol said the vein looked adequate on ultrasound. It did not stay patent. The line thrombosed within forty-eight hours.
Cost is another factor worth mentioning. Bard kits are among the more expensive PICC systems on the market. The convenience of the preloaded design is real, but if your facility performs a high volume of inserts, the per-unit cost adds up. Some departments choose to buy standard percutaneous kits and use ultrasound-guided microconvex probes instead, which reduces expense and gives better visualization. Neither approach is universally better. It depends on your patient population and your staff's comfort level with each technique.
If you are just starting out, do not treat the training modules as a substitute for supervised practice. Watching a video of a smooth insertion and performing your first five on real patients are two different experiences. The vein collapses differently when you are the one holding the needle. The patient moves. The ultrasound image is not as clear as the instructor made it look.
Measure carefully. Advance slowly. Confirm the tip. And do not be afraid to change your approach mid-procedure. The training gives you a baseline. Your hands decide whether it works.
Gallery Bard Picc Line Insertion Training
PICC line (Peripherally Inserted Central Catheter) Training
Visual illistration of a BARD PICC line inside the body. | Radiology tech, Nurse, Vascular
Picc Line Insertion Education - Education Supplies
Bard Picc Line Certification - prntbl.concejomunicipaldechinu.gov.co