What You Need to Know About Using a Bard Power Port
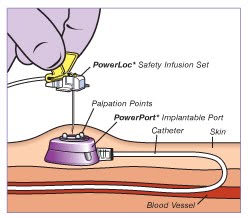
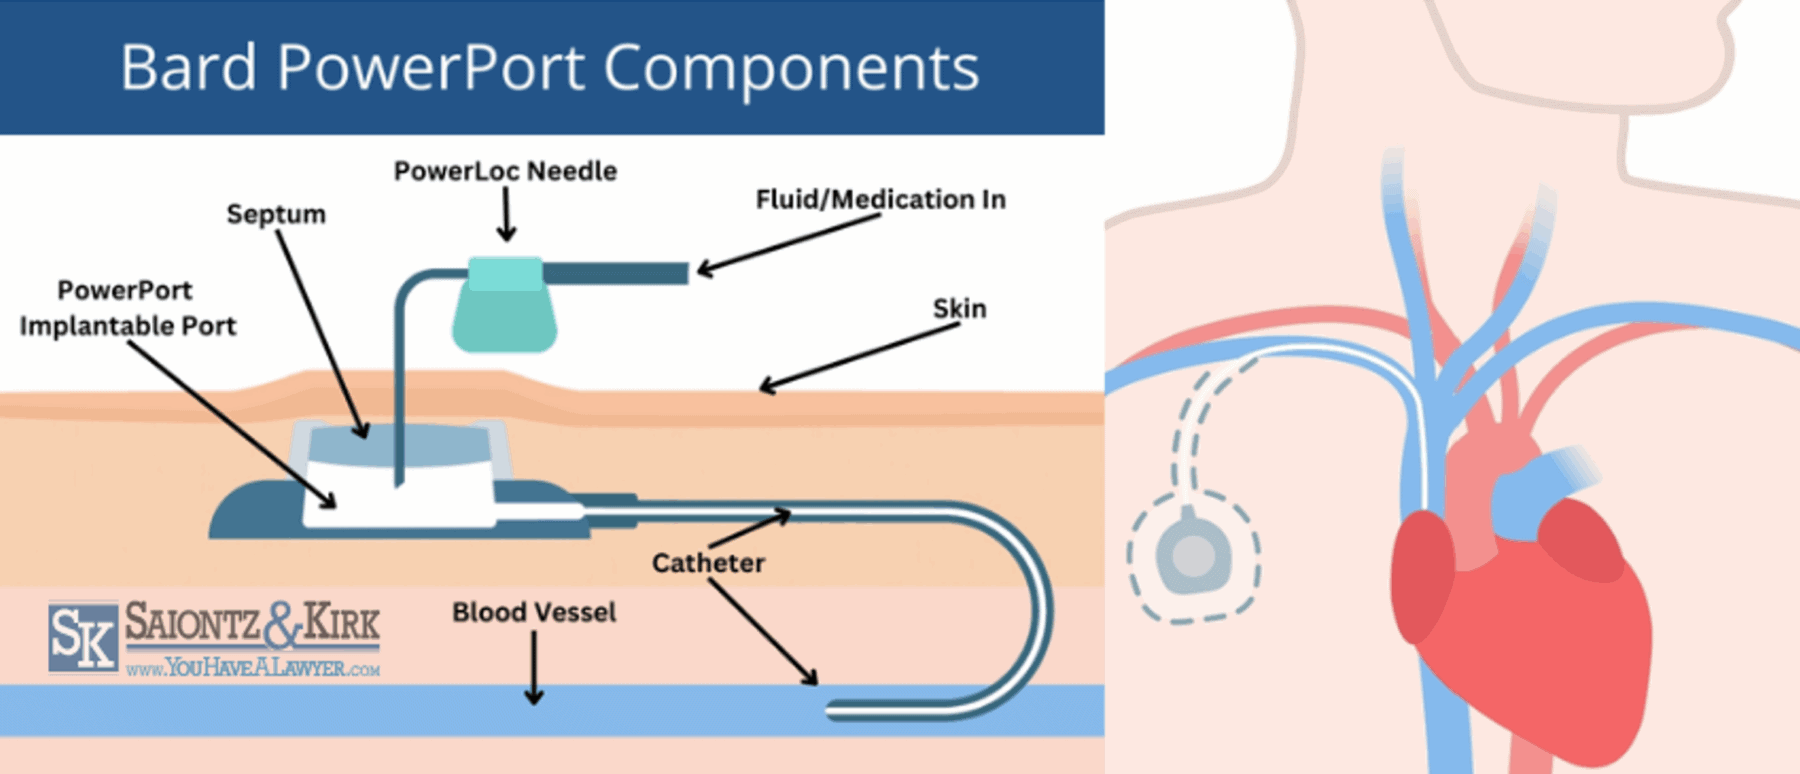
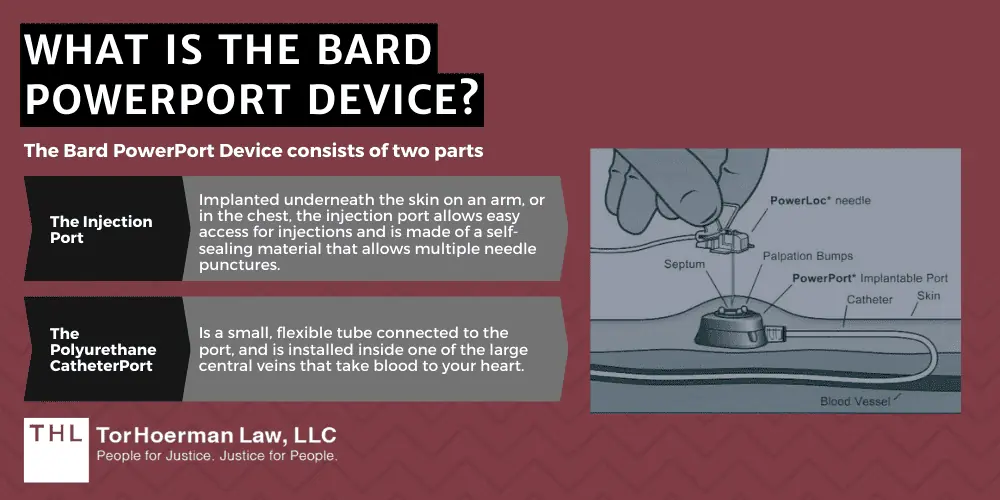
A Bard Power Port is an implanted venous access device. It sits under the skin, usually in the upper chest, and gives you a reliable way to get chemotherapy, antibiotics, or nutrition directly into your central veins without needing repeated needle sticks in your arms. The company, Bard (now C. R. Bard, a Becton Dickinson company), has been making these things since the mid-1990s. They are standard-issue in oncology and long-term IV therapy clinics across the US and Europe. The system is straightforward in theory. You have a silicone or polyurethane catheter threaded into a large vein like the subclavian or internal jugular. The catheter connects to a port body, which is a small reservoir with a self-sealing silicone septum. A non-coring needle goes through the skin and into that septum whenever someone needs to use it. That's it. The mechanics are simple. The complications are what people don't talk about enough.
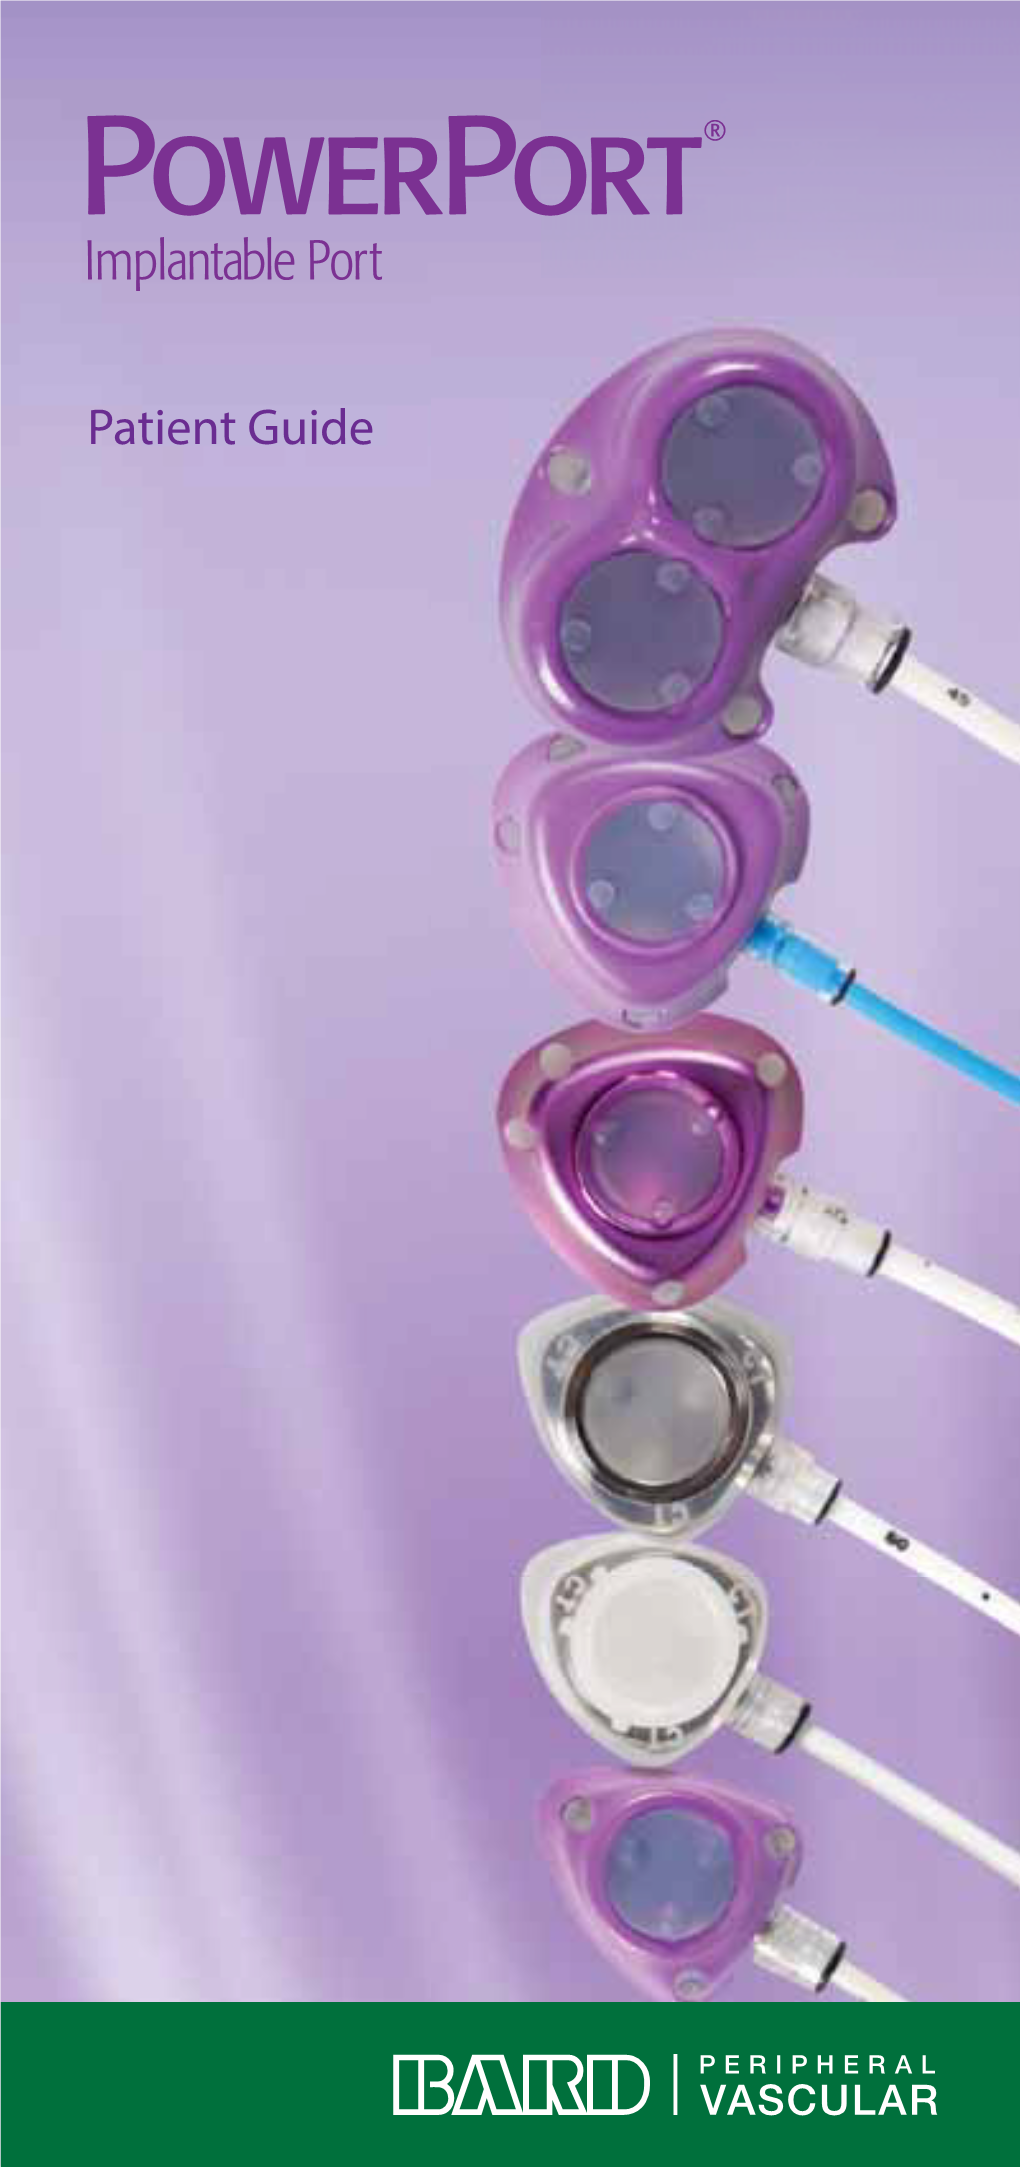
Bard Power Port Patient Guide
I have dealt with these ports through years of clinical support and nurse education, and the most common mistake I see is people assuming the patient guide is just a pamphlet you hand out and forget about. The real guide is the documentation your clinic keeps with your port info — model number, catheter length, insertion date, and any imaging records. When something goes wrong, which it eventually does with every single port, having that paper trail is what determines whether you fix it quickly or spend three weeks chasing records from a different hospital system. I once spent four days tracking down a port model because a patient had been transferred between two facilities and neither one updated the card. The workaround was calling the surgical nurse coordinator at the original insertion site and getting them to fax the operative report. Took an hour, but it saved a lot of back-and-forth. The actual patient orientation from Bard covers basic care: flush the port after every use with saline and heparin if you're not actively receiving treatment, watch for signs of infection around the site, and avoid heavy lifting with the arm on the same side as the port for the first week or two after insertion. Most of this is standard. What they don't emphasize much is that the needle insertion site needs to be rotated if you're getting long-term treatment, and that a port that isn't being used regularly still needs to be flushed every four to six weeks to keep it from clotting off. I've seen too many ports lost because the patient thought they were done with treatment and let the maintenance schedule slip.
Common Problems and What Actually Works
Port clots are the most frequent issue. The catheter tip can get a fibrin sheath or a small thrombus that makes flushing feel resistant. The first thing to check is whether the needle is properly seated. Sometimes a needle that is slightly won't aspirate back even when the port is open. If you confirm placement and it still won't flush, a low-dose tissue plasminogen activator (tPA) dwell is the standard intervention. Bard and other manufacturers publish specific protocols for this. The typical approach is 2 mg of alteplase in 2 mL, left in the port for up to 120 minutes, then aspirated. It resolves the majority of non-infected occlusions. If it doesn't, that's when you order a plain X-ray or CT to check for catheter malposition or a larger thrombus. Infection is less common but more serious. The redness, fever, and pain around a port site usually show up within the first few weeks after insertion, but late-onset infections from skin flora migrating along the catheter tract do happen months later. Blood cultures drawn from the port and a peripheral vein simultaneously are the right move here. If the port culture turns positive and the peripheral one doesn't, the port is likely the source. Removal is often necessary. No amount of antibiotics inside the port will reliably clear a biofilm. I've seen attempts to salvage ports with antibiotic locks fail repeatedly, and the patient ends up with a worse systemic infection because of the delay. It's better to pull it early and place a new one on the other side. Another thing nobody warns patients about: MRI compatibility. Most modern Bard ports are labeled MRI conditional, but the conditions matter. The field strength, the SAR limits, and the scan duration all factor in. A standard 1.5T scan is fine. A 3T scan with high SAR can heat the port site. Always verify the exact model number against the MRI safety table before scheduling. I had a patient who scheduled a 3T MRI for her knee and nearly got a second-degree burn on her chest because the technologist didn't check her port's MRI status. The port itself didn't move — it's not magnetic — but the radiofrequency energy can cause localized heating at the electrode-skin interface.
Get the Full Details
Practical Maintenance Tips
Keep your port card on you at all times. Not just your main address, but the port model number and the insertion date. If you end up in an ER in another state, that card is what lets the treating physician act fast instead of spending hours figuring out what device you have. The card usually comes from the insertion clinic. If you haven't gotten one, call your oncologist or interventional radiologist and ask for a duplicate. When you get a new port placed, take a picture of the X-ray before you leave the suite. Port tips can migrate. A catheter that looks fine on the initial film can be sitting against the vessel wall, which increases the risk of tip erosion or occlusion. Having that baseline image means you can compare it later if something feels off. I tell my patients to save it on their phone and bring it to every follow-up appointment. It's free insurance against misdiagnosis. If you notice the port feels hard or you can't palpate the reservoir anymore, that could be a contraction or fibrosis around it, which sometimes happens after radiation therapy to the chest wall. It doesn't always mean the port is failing, but it does make needle access harder. Interventional radiology can use ultrasound guidance in those cases. Don't wait until the next scheduled chemo cycle to report it. Call your clinic sooner so they can assess whether the port is still functional.
There is no download link for an official Bard Power Port Patient Guide because Bard distributes these through hospital discharge protocols and patient education portals, not as a standalone public document. If your clinic hasn't given you the materials, ask for them by name. The patient education handouts from Bard's website or your insurer's portal will have the model-specific information. Anything found on third-party sites is usually outdated or incomplete. The safest source is your own clinical team's paperwork. Ports work well when they're maintained properly. They are not fail-proof. Clots form. Infections happen. Needles slip. The trick is knowing what to watch for and when to escalate. Most problems are solvable if you catch them early. The ones that aren't are the ones people ignored for weeks because nothing seemed urgent at the time.