Getting Through the Psych Eval Without Losing Your Mind
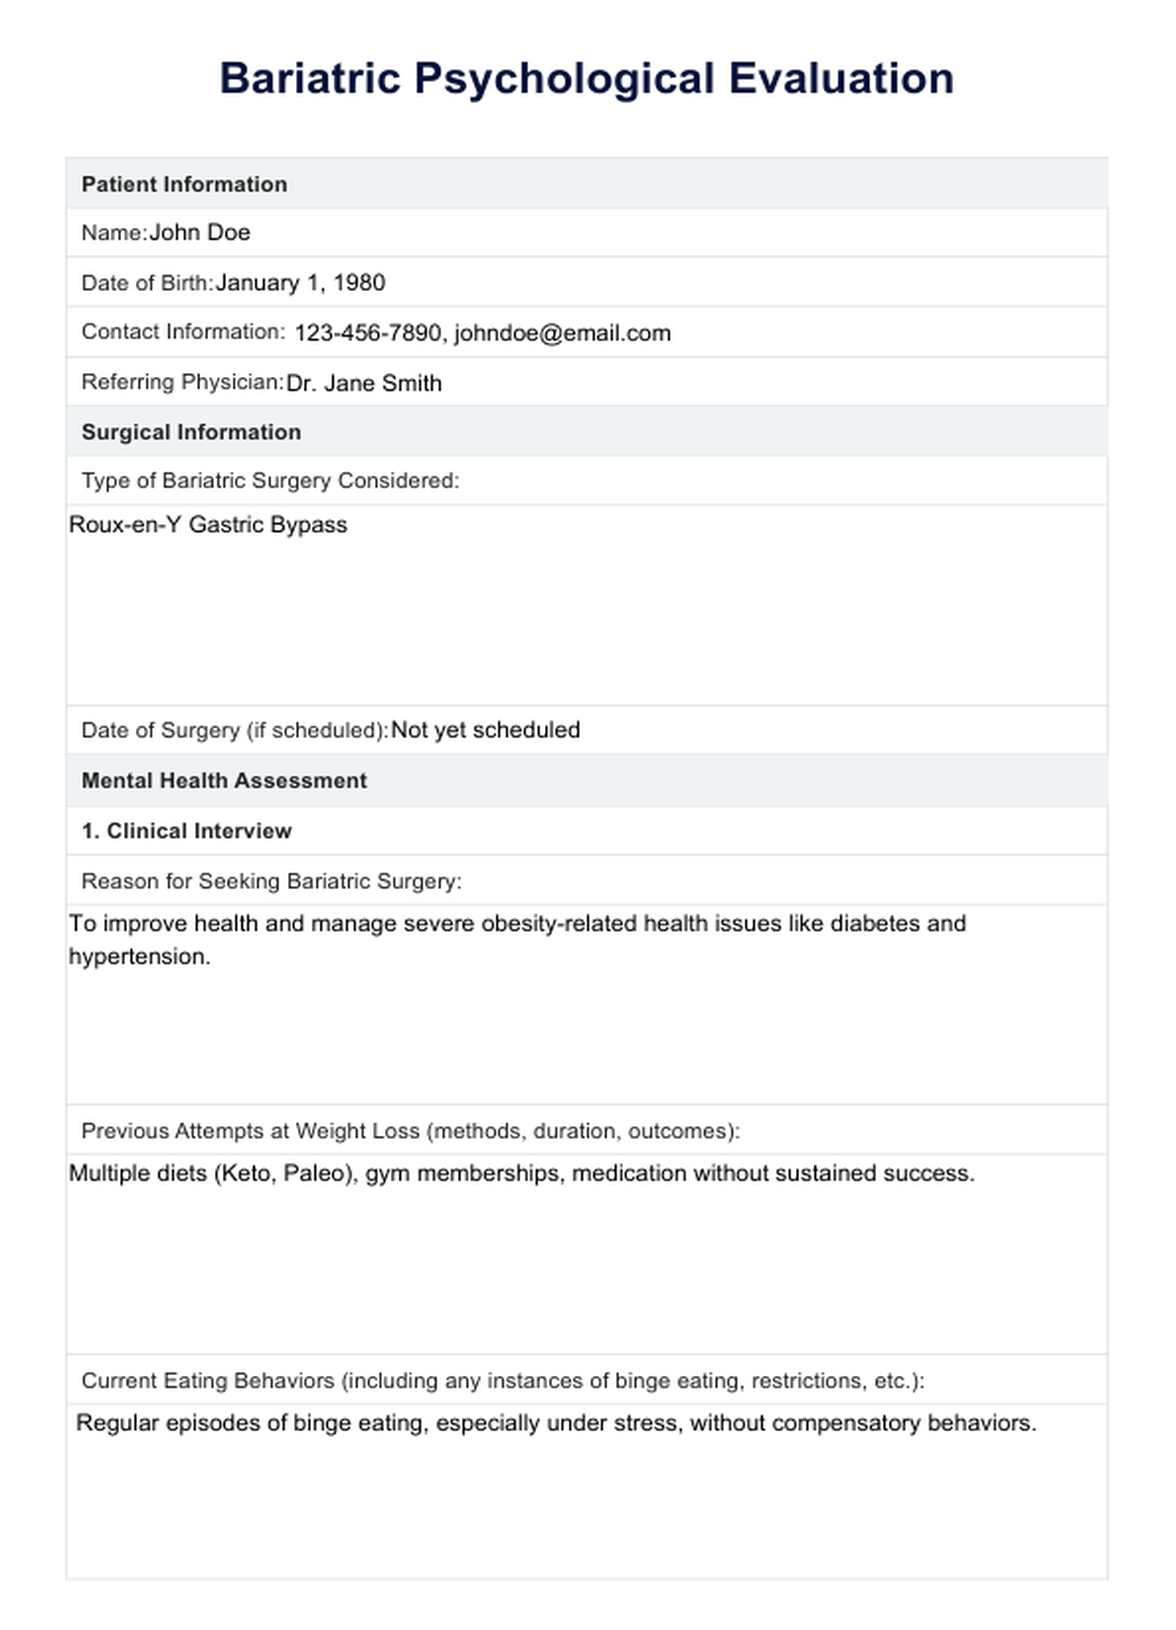
The bariatric surgery psychological evaluation isn't as complicated as some surgeons make it sound, but it's also not something you can breezely knock out in twenty minutes unless you've done this before. I've been reviewing these with patients and referring providers for years now, and the process still surprises me in the same predictable ways. Most people walk into it thinking they'll be judged. They are, technically, but the judgment is almost entirely procedural. You're being screened for factors that affect surgical outcomes, not being assessed for moral character. The actual questions fall into clusters, and knowing the clusters helps you prepare without sounding rehearsed. Here's what typically shows up on the forms and in the interview portion. Motivation and expectation questions come first. Why are you pursuing this surgery? What do you expect will change after? These are straightforward but people overcomplicate the answers. The evaluator wants to hear realistic expectations. Saying you expect to lose eighty pounds and your marriage will be fixed will raise flags. Saying you expect to lose weight with significant lifestyle changes and that your relationship dynamics may shift is the honest answer they're looking for.
Then there are the historical mental health questions. Have you ever been diagnosed with a psychiatric condition? Are you currently taking medications? Have you been hospitalized for mental health reasons? This is where people get tripped up because they assume a history of depression or anxiety automatically disqualifies them. It doesn't. Controlled, stable mental health conditions with documented treatment compliance are routinely cleared. Untreated or poorly managed conditions are what get flagged. Bring your treatment records if you have them. Having a therapist or psychiatrist's note on file showing stability for at least six months cuts down the back-and-forth significantly. The eating behavior questions are where most evaluations get interesting. Do you binge eat? Do you graze throughout the day? How would you describe your relationship with food? These matter more than the depression screening. Undiagnosed binge eating disorder or grazing patterns are the biggest predictors of post-surgical complications and weight regain. If you struggle with this, say so. I've seen patients hide binge eating for fear of being denied surgery, then present with severe nutritional deficiencies and emotional distress within a year of the procedure. The evaluator can usually tell when someone is deflecting anyway, and deflection looks worse than honesty on paper. Social support is another major category. Who lives with you? Do you have someone who can help you after surgery? What does your family think about this procedure? Bariatric surgery requires significant lifestyle adaptation in the first three months. Patients without any social support sometimes clear the evaluation and still struggle enormously afterward because nobody's checking in on them or helping with meals. That's not a failure of the patient. It's a gap the evaluation is supposed to catch early so resources can be arranged beforehand.
Substance use gets asked about directly. Do you drink alcohol? Do you use tobacco or other substances? Alcohol tolerance changes dramatically after surgery, and the relationship between alcohol and weight gain is complex enough that evaluators need to establish a baseline. Tobacco use is often a hard stop depending on the surgeon's protocol. Being honest here saves everyone time. Understanding of the procedure is tested too, though not always in an obvious way. What will you be able to eat after surgery? What are the risks? How will your life be different? People who can articulate the lifelong dietary progression and the permanent anatomical changes tend to score well. Not because the evaluator cares about trivia, but because comprehension correlates with adherence.
Get the Full Details

What Actually Happens in the Room
The evaluation itself usually takes forty-five to sixty minutes. Some programs use a standardized instrument like the Bariatric Surgery Screening Instrument or the MMPI-2-RF with bariatric norms, while others rely on a clinical interview structured around the question clusters I described. The instrument-based approach is faster but less flexible. The interview approach gives the evaluator room to probe specific concerns, which is where things get nuanced. I remember a patient a few years back who had an excellent profile on paper. Stable employment, no hospitalizations, normal BMI trajectory toward the surgical range, supportive partner. TheMMPI-2-RF came back clean. During the interview, she mentioned casually that she was going to take her two children with her to the recovery area for the first week. She said it out loud like it was completely normal, with no awareness that this would be a boundary issue or that post-op pain management and medical equipment make that impractical at best and unsafe at worst. She wasn't answering the question poorly. She was revealing a gap in her understanding of the post-operative environment that wasn't visible on any form. We adjusted the plan and connected her with a counselor who helped her process separation anxiety related to the surgery. She went on to have a successful procedure. But that detail only came out because I asked about her support system more specifically rather than just checking the box. That's the thing about these evaluations that never gets mentioned in the patient literature. The forms miss things. The clinical interaction catches what the forms don't. And a skilled evaluator is watching for incongruence between what someone writes on paper and how they describe their situation verbally.
Pitfalls That Derail Clearances
Certain mistakes show up repeatedly and they're almost entirely preventable. The first is minimization. Downplaying binge episodes, underreporting alcohol intake, saying everything is fine when it clearly isn't. This tends to backfire because evaluators have heard every variation of this. A patient who admits to weekly grazing with full awareness of the problem and a concrete plan to address it reads more credible than one who insists food has never been an issue. Another common issue is weaponizing a disability. I've had patients present documentation for chronic pain or thyroid disorders as though these automatically entitled them to surgical clearance. They don't. Chronic conditions complicate the picture but aren't disqualifying by themselves. The question is always whether the condition is managed and whether it would interfere with post-operative compliance. A patient with well-controlled hypothyroidism who takes their medication daily isn't a concern. A patient who mentions their thyroid diagnosis in passing and hasn't had labs checked in eighteen months needs to get that sorted before rescheduling. Then there's the performance problem. Some patients treat the evaluation like a job interview and give them the answers they think will get a yes. That approach usually fails because the questions are designed to detect inconsistency. Ask someone how they handle stress five different ways throughout a single session and eventually the stories diverge. Authenticity is underrated in this context. The evaluator would rather hear a careful, honest account than a polished one.
When the Evaluation Fails You
Not getting cleared is more common than people expect, and it's rarely permanent. The most frequent reasons for referral or delayed clearance are uncontrolled depression, active substance use, untreated eating disorders, and insufficient social support. Each of these has a standard pathway to resolution that the evaluating clinician can outline. Uncontrolled depression usually means adjusting medication or increasing therapy frequency for a set period before re-evaluation. Active substance use requires a documented period of abstinence, typically ninety days with verification through screening. Untreated eating disorders need a specialized referral and evidence of engagement with treatment. Insufficient social support might mean connecting with a bariatric support group or arranging home health resources. Some programs will clear a patient with partial conditions and attach requirements. Others require full resolution before proceeding. The protocol depends entirely on the surgical program's risk tolerance and the referring physician's assessment. There's no universal standard here, and that inconsistency is one of the real frustrations patients face. You can be cleared at one center and asked to come back at another with the same clinical picture. The evaluation also has genuine blind spots. It captures a snapshot in time, usually one session, and cannot reliably predict how someone will handle the physiological and psychological stress of surgery weeks or months later. Post-operative depression and anxiety are well-documented even in patients who clear the evaluation cleanly. The tool isn't designed to predict that. It's designed to identify pre-existing conditions that would compound surgical risk. Those are different objectives.

Practical Steps Before Your Appointment
Gather your documentation beforehand. Medication lists with dosages. Previous mental health records if you have accessible copies. Names and contact information for any treating providers. Having this ready means the evaluator can verify details during the session rather than asking you to follow up later, which adds weeks to the timeline. Reflect honestly on your eating patterns before the appointment. Not to fabricate a narrative, but to have a clear picture yourself. If you've never really examined whether you binge, graze, or eat for emotional reasons, the questions will catch you off guard. A few days of candid food and mood logging before the evaluation gives you data to draw on and demonstrates engagement with the process. Bring a list of questions for the evaluator too. Understanding what happens after the evaluation, how long clearance is valid, what the next steps are if additional testing is recommended. This signals that you're taking the process seriously without performing compliance. There's a difference and evaluators notice it.
The Bariatric Surgery Psychological Evaluation Questions themselves are fairly standardized across programs, but the application varies enough that treating it as a bureaucratic hurdle is a mistake. It's a screening tool that, when done properly, protects patients from procedures they aren't psychologically prepared for and connects them with resources before surgery rather than after. That's the actual function of it, separate from whatever anxiety it generates in the moment.


