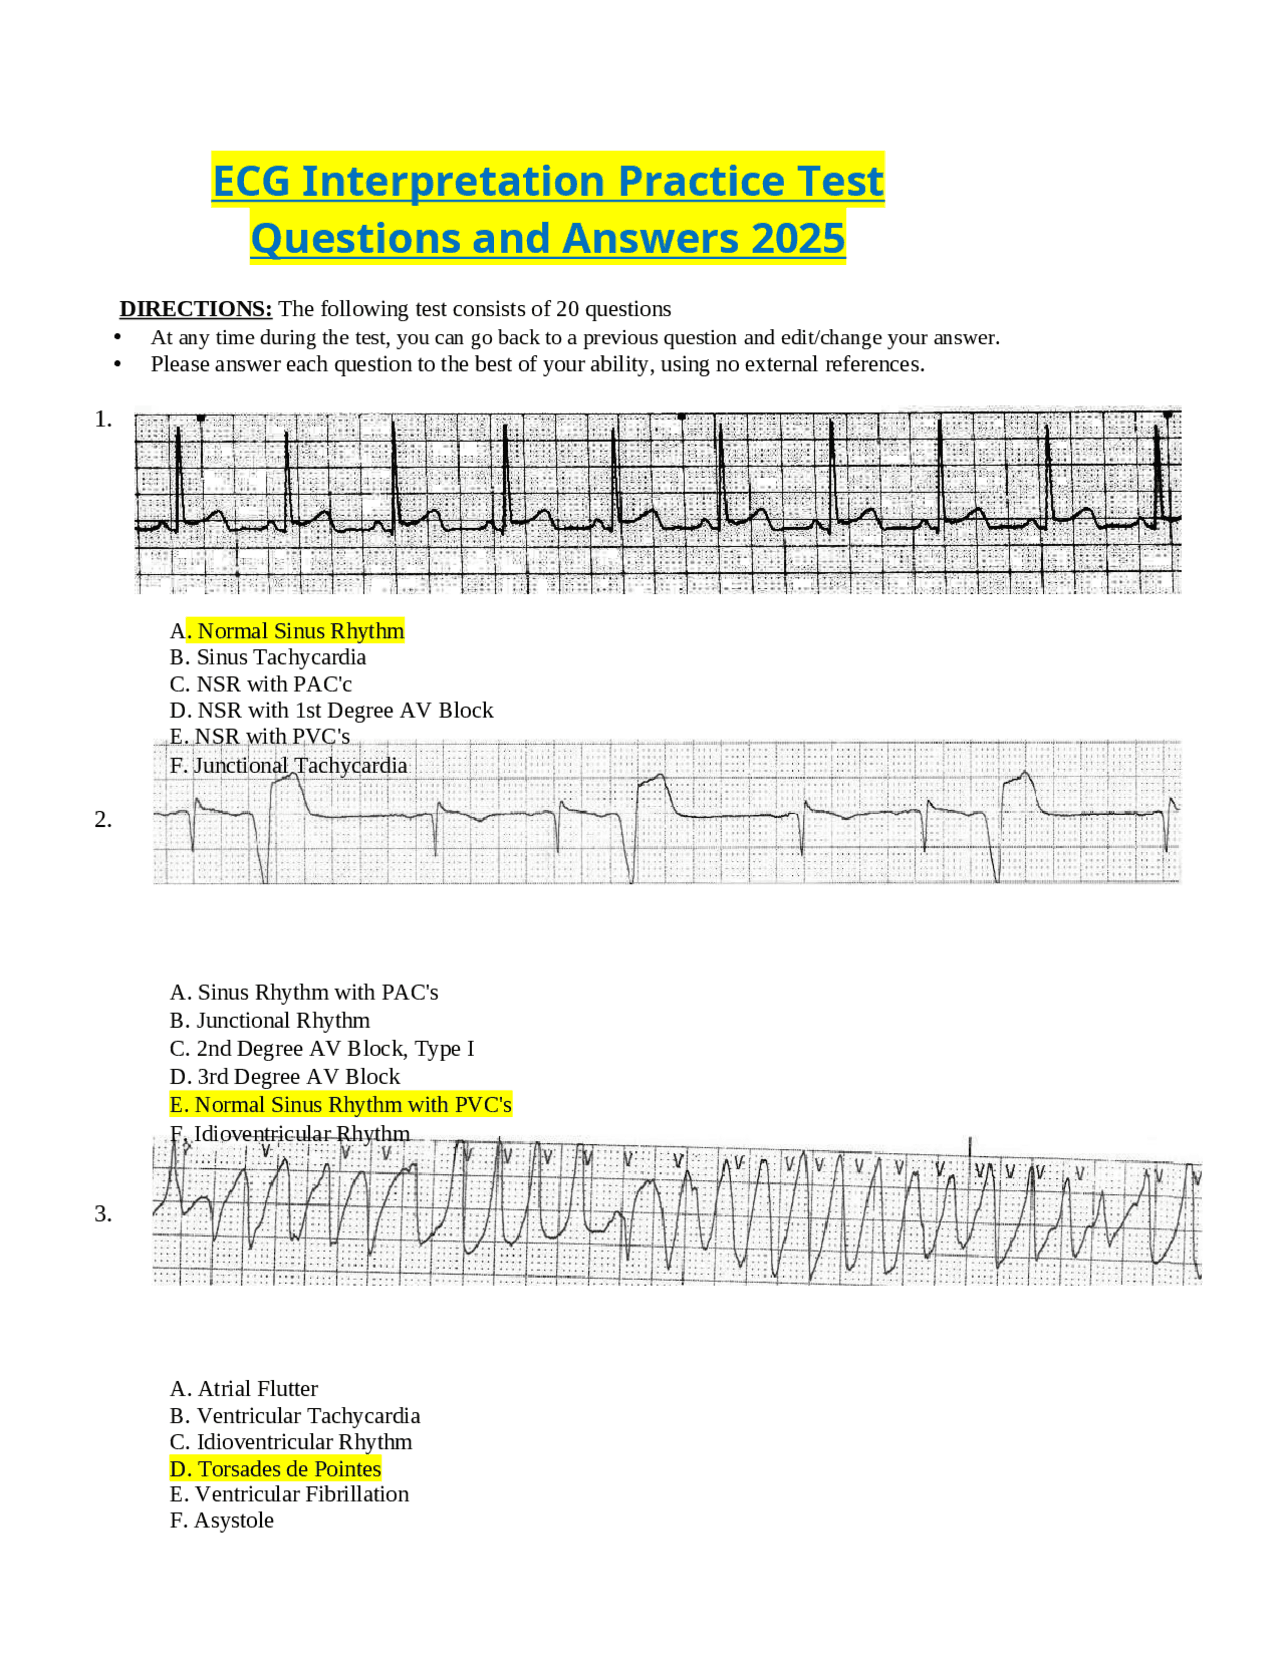
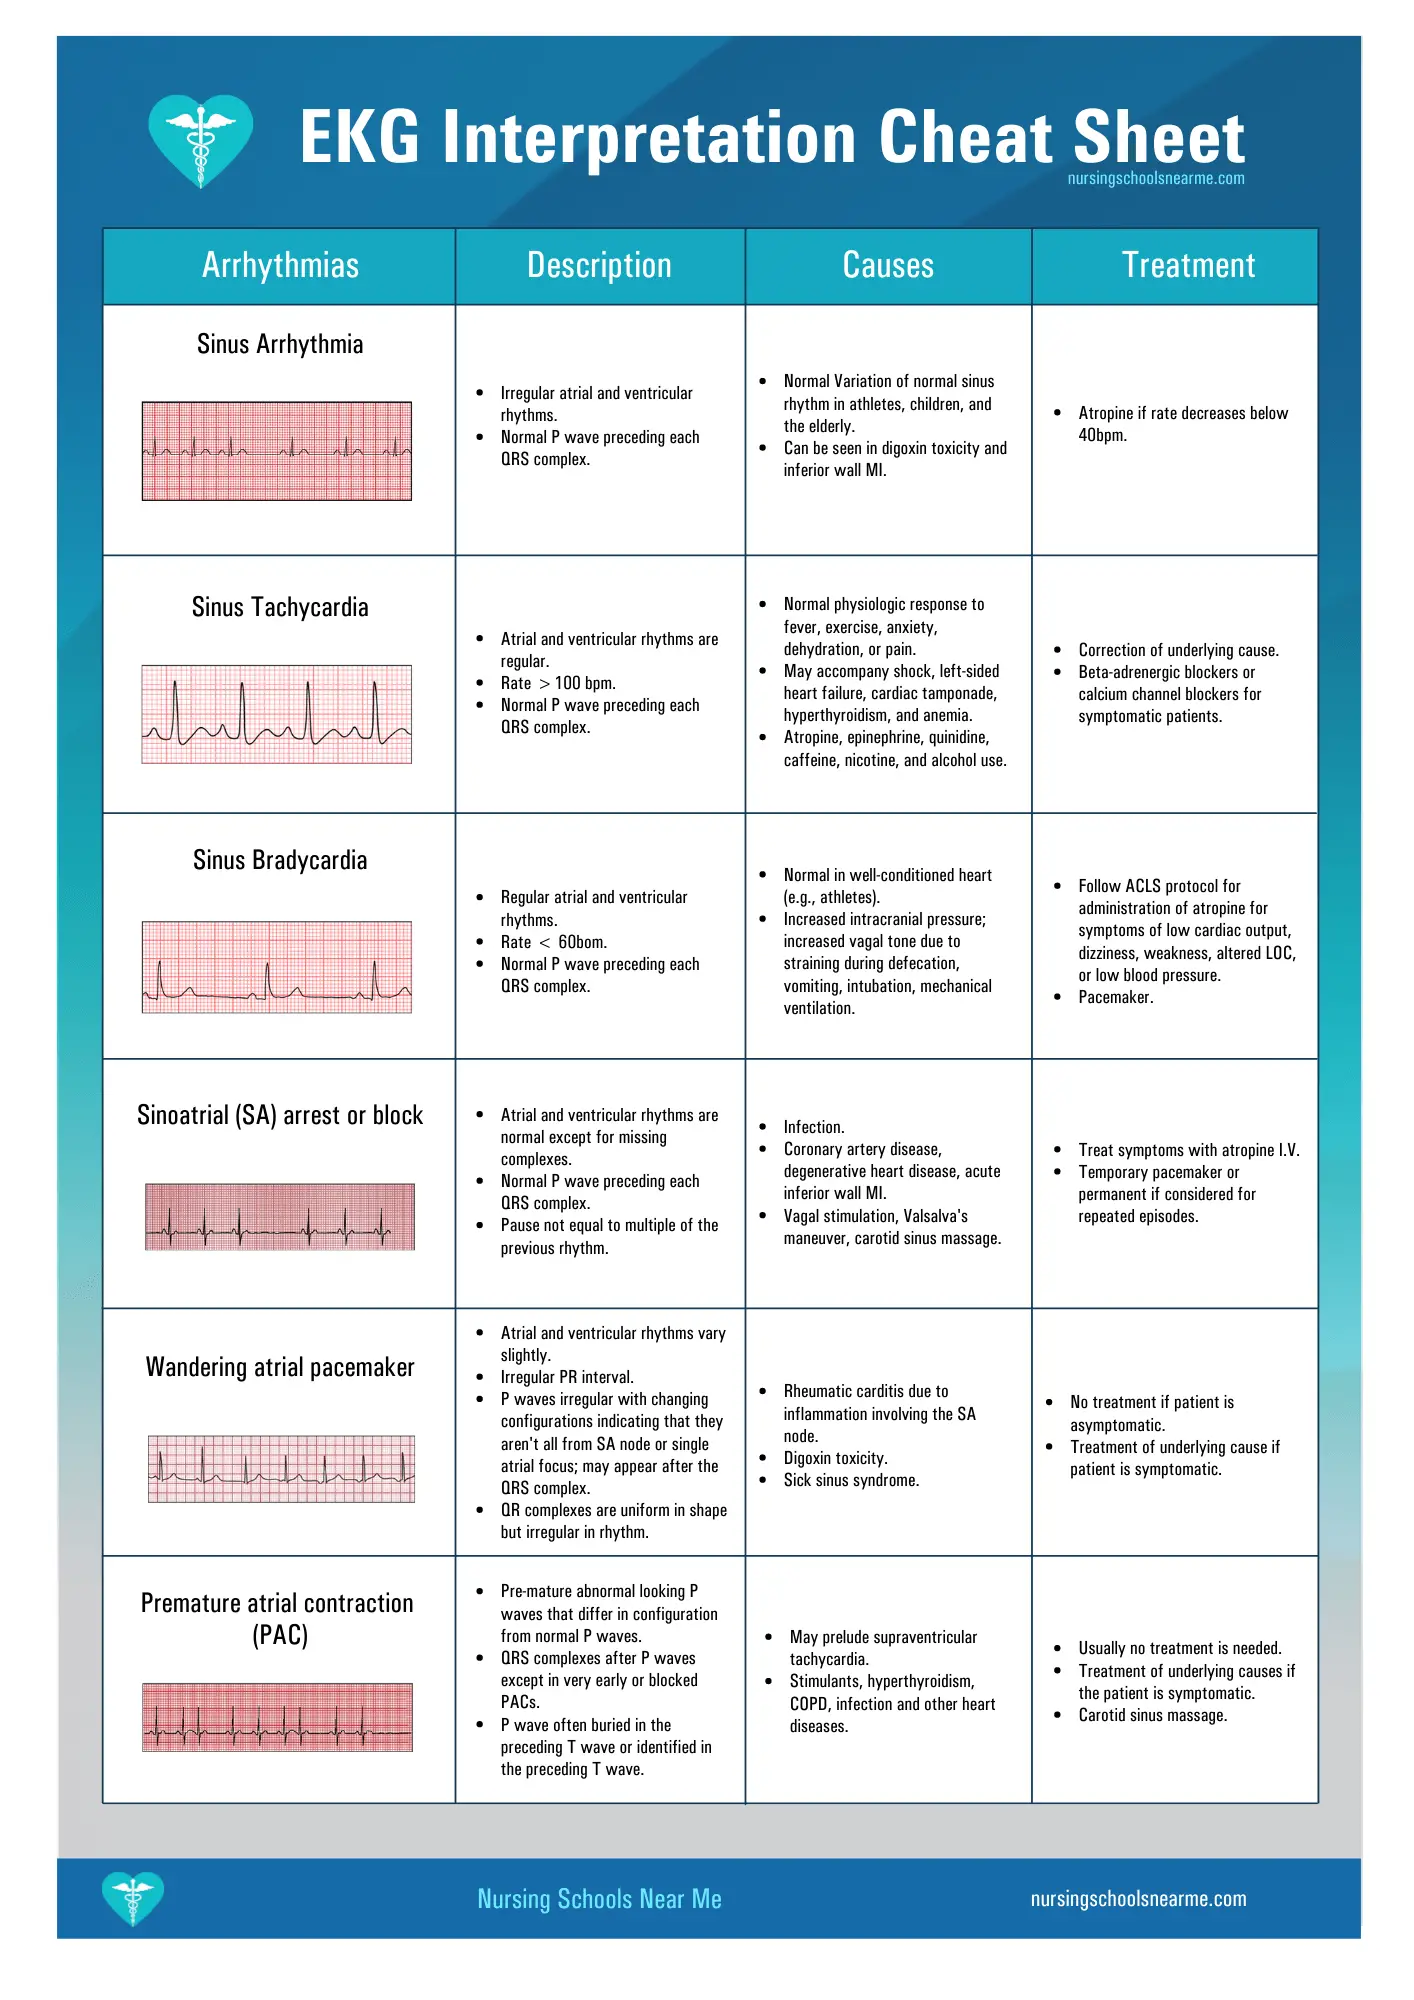
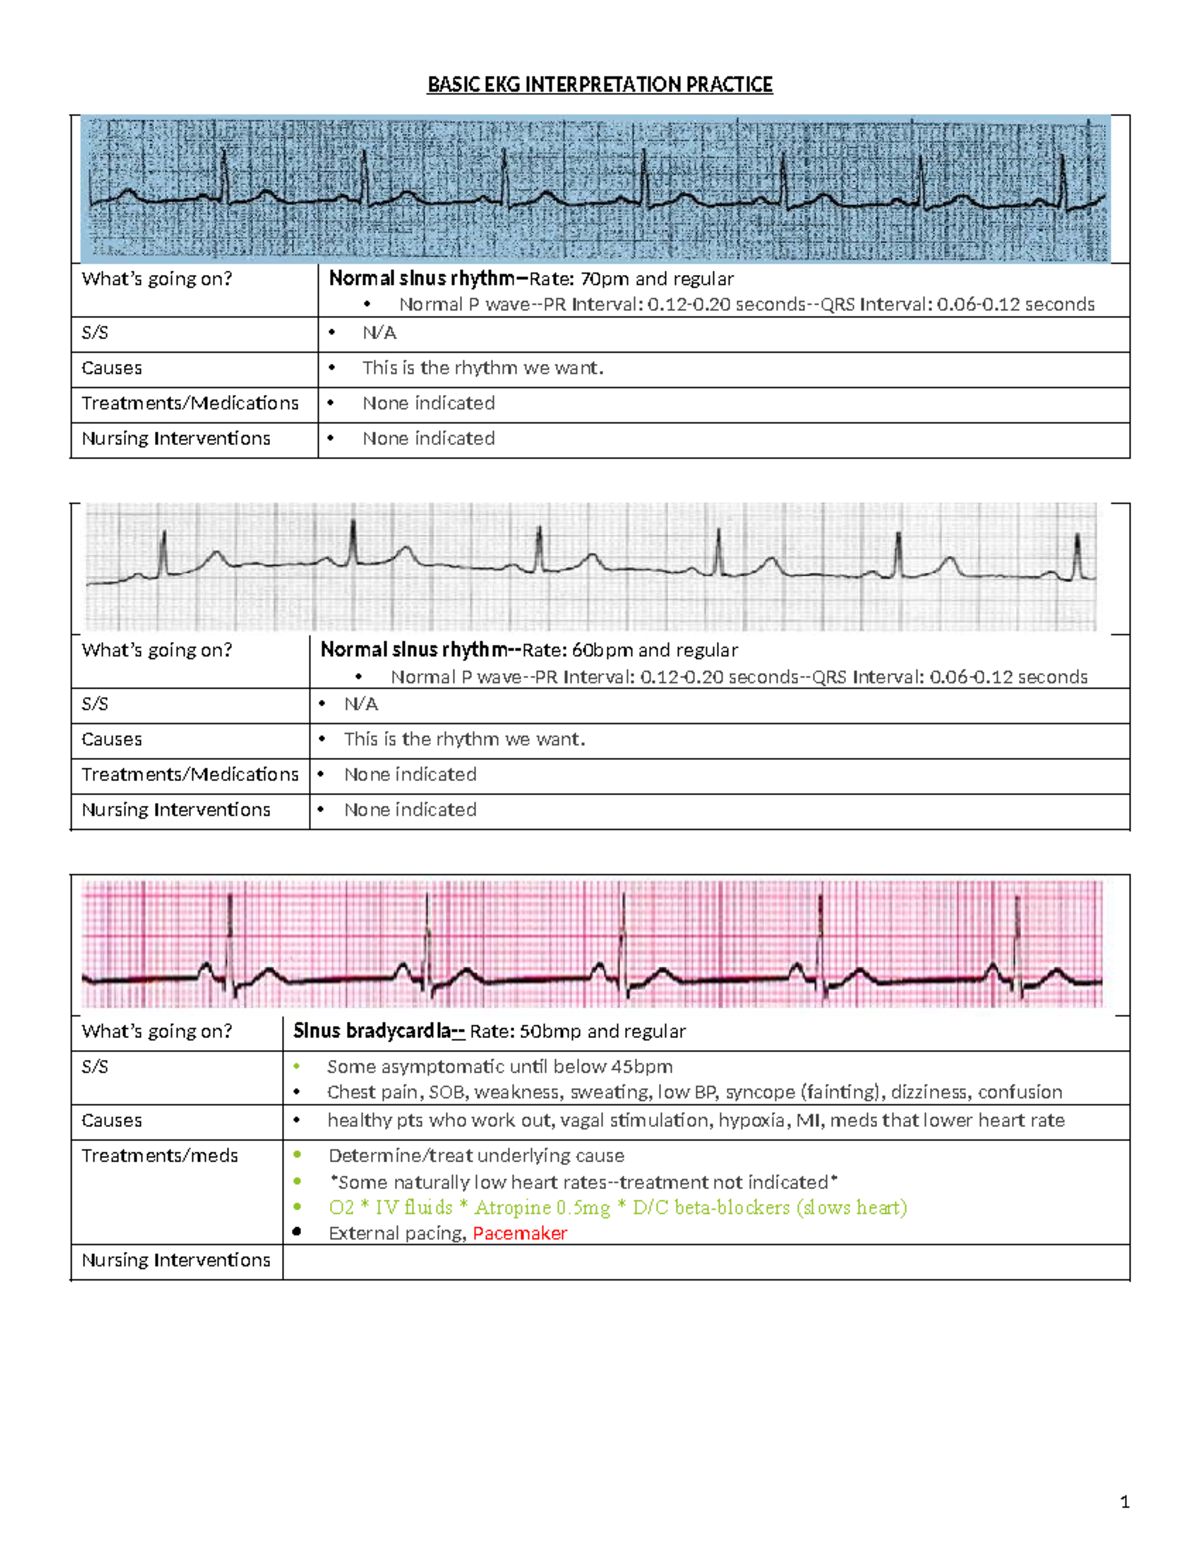
What actually happens when you practice ECG interpretation
Most people jump into ECG study guides and immediately get overwhelmed by arrhythmias that look dramatic but are either benign or rare. I spent years tutoring med students and nursing residents through this, and the single biggest problem is the same every time. They memorize criteria without developing pattern recognition. A Basic ECG Interpretation Practice Test won't help you if you're just checking answers without understanding why each line on the strip looks the way it does. Here is how I actually recommend approaching this. Pick a resource that gives you the raw tracing first and the answer only after you've committed to a read. The moment you peek at the solution before deciding, you short-circuit the learning process. You think you recognized the pattern, but you actually just got exposed to the answer.
How to use a Basic ECG Interpretation Practice Test effectively
Start with rhythm. Not rate, not axis, not intervals. Rhythm. Look at the R-R intervals across the entire strip and ask yourself whether they are regular or irregular. If they are irregular, determine whether the irregularity is regular (think atrial fibrillation versus wandering pacemaker) or irregularly irregular. This single distinction will rule out roughly 40 percent of common arrhythmias before you even measure a QT interval. After rhythm, check the rate. I used to tell students to count the big boxes between R waves and divide 300 by that number. That works fine for regular rhythms at normal rates, but it falls apart at extreme bradycardia or tachycardia. When the rate is below 40 or above 200, the 300 method introduces significant error. Instead, count the number of QRS complexes in a 10-second strip and multiply by six. Most standard ECG paper has 50 large boxes in a 10-second span at 25 mm per second speed, so this is straightforward if you know your paper speed. Then move to the axis. I draw a quick mental grid on the leads. Lead I positive and lead aVF positive means normal axis. Lead I negative and lead aVF positive means right axis deviation. Lead I positive and lead aVF negative means left axis deviation. Lead I negative and lead aVF negative means extreme axis deviation. This takes about 15 seconds and catches conduction abnormalities that would otherwise hide in plain sight.
Wave morphology comes after. P wave shape tells you the origin. Tall peaked P waves in lead II suggest right atrial enlargement. Notched P waves wider than two small boxes point to left atrial enlargement. If there are no P waves before every QRS, you are dealing with an atrial tachyarrhythmia or a junctional rhythm, and the QRS width determines whether there is aberrant conduction or a ventricular origin. ST segments and T waves are where most people make dangerous mistakes. They see any ST depression and immediately call ischemia. But early repolarization causes concave ST elevation, usually in the precordial leads, with J-point notching. Pericarditis causes diffuse concave ST elevation with PR depression. Hyperkalemia produces tall symmetric T waves before any QRS widening appears. One leads to unnecessary cardiac workups. The other prevents a missed life-threatening electrolyte abnormality. I once had a resident insist on a diagnosis of anteroseptal myocardial infarction because of ST depression in V2 and V3 on a routine preoperative ECG. The tracing showed deep symmetric T wave inversions in those same leads with normal Q waves and no reciprocal changes anywhere else. I had him pull the prior ECGs from the chart. The pattern had been identical for three years. This was a persistent juvenile T wave pattern, completely benign, present in young adults as a normal variant. If he had called that an MI, the patient would have gone to the cath lab for nothing. The workaround was simple: always compare to prior ECGs when available, and never diagnose acute changes without knowing the baseline.
Get the Full Details

Intervals matter more than most textbooks admit. The PR interval tells you about AV nodal conduction. A PR longer than five small boxes is first-degree AV block. But here is the nuance beginners miss: a short PR interval with a delta wave is WPW syndrome, and that changes everything about how you treat tachycardia. Giving AV nodal blocking agents like beta blockers or calcium channel blockers to someone with WPW and atrial fibrillation can be fatal because it promotes conduction down the accessory pathway. That is not a theoretical risk. I have seen it documented in case reports. The QT interval requires correction for heart rate. Using Bazett's formula can overcorrect at fast heart rates and undercorrect at slow ones. Fridericia's formula is more accurate across a wider range. A QTc above 470 milliseconds in men or 480 in women warrants investigation for prolonged repolarization, which increases torsades de pointes risk significantly. When you are building your practice routine, do not just do one set of 50 tracings and consider yourself done. Space your practice out over weeks. Retrieval strength decays if you cram. Do ten tracings a day for five days instead of fifty in one sitting. Your brain needs the consolidation period between sessions to actually internalize the patterns.
There are free resources online that are decent. Life in the Fast Lane has a solid ECG library with explanations. The EMCrit Project ECG book is available as a free PDF and covers critical care cases you will actually encounter. For structured practice tests, the American Heart Association offers assessment modules through their ACLS portal, though those require certification membership. Various medical education platforms sell question banks, but they tend to overemphasize dramatic cases and underrepresent the mundane tracings you will see 90 percent of the time. One significant limitation of most practice test resources is that they present clean, textbook-quality ECGs. Real clinical ECGs are messy. They have baseline wander, muscle artifact, lead misplacement, and poor electrode contact. A practice test that only shows perfect tracings will leave you unprepared for actual clinical work. I always supplement standard question banks with actual patient ECGs from my own archive, including the poorly acquired ones. Learning to extract diagnostic information from a noisy tracing is a separate skill from recognizing patterns on a clean strip. Another limitation is that most practice tests do not provide clinical context. An ECG does not exist in a vacuum. The same ST depression means something different in a 22-year-old asymptomatic athlete than in a 68-year-old with chest pain and diabetes. Without clinical correlation, you are practicing blind interpretation, which is only part of the actual skill set. Try to pair every practice tracing with a clinical scenario, even if you create the scenario yourself.
If you want a more hands-on approach, some programs offer virtual ECG simulators where you manipulate electrode placement and see the resulting changes on the tracing. This teaches you about lead vectors in a way that static images never will. It also reinforces why limb lead reversal is one of the most common errors in ECG acquisition and how easily it mimics pathology. The bottom line is that consistent deliberate practice beats any single resource. Pick a method, stick with it for at least six weeks, review your mistakes weekly, and always compare new tracings to old ones when possible. The pattern recognition that develops over time is what separates someone who can read an ECG from someone who can interpret one in a clinical context.