How Basic First Aid Training Actually Works in Practice
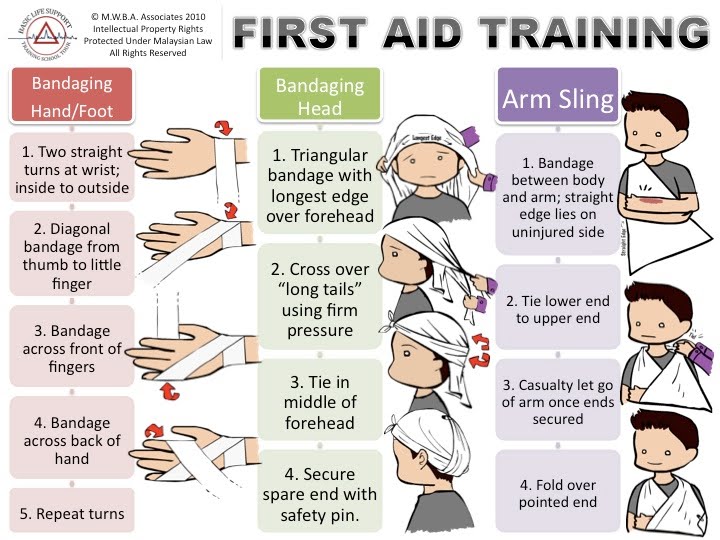
The biggest mistake people make when starting Basic First Aid Training is treating it like a checklist. You learn the steps, you pass the test, and then two years later you're standing over someone on the floor with no idea where to begin. That's not your fault. Most entry-level courses are designed to get you certified, not to make you competent. A properly structured course will get you through the material in about 8 hours and hand you a certificate that expires in three years. A good one will leave you actually able to function when adrenaline hits. Those are two different things. I went through this same problem a few years back when I was trying to train a small team at a warehouse. We had everyone complete the standard Red Cross module, and on paper we were all certified. Six months later, a forklift operator sprained his wrist badly enough that his hand was swelling within twenty minutes. Two of the five people who had "completed training" couldn't figure out how to properly immobilize it. One of them tried to put ice directly on the skin. This isn't a joke. This is what happens when you treat first aid as a compliance checkbox.
What Basic First Aid Training Covers That Nobody Warns You About
The standard curriculum is predictable: CPR, choking response, bleeding control, shock management, burns, fractures. You learn the algorithms. What the courses rarely drill into you is the sequencing problem. In a real emergency, you don't have the luxury of thinking through each decision. Your brain will default to whatever you've practiced most. If you've only memorized steps without repetition, you will freeze or skip ahead. Here's a counter-intuitive point that comes up constantly: the primary survey—the DRSABC sequence (Danger, Response, Send for help, Airway, Breathing, Circulation)—is actually less useful than most people think when you're alone with a single casualty. I ran into this specifically when I was working a shift and a colleague collapsed from what turned out to be a vasovagal episode. There was nobody else around. The textbook answer says call for help first, but there was no phone nearby and every second counted. I ended up going straight to airway and breathing assessment because the danger had already passed—I was the danger and I wasn't a threat. Skipping steps under pressure is sometimes the right call. The course won't tell you that. Another thing that basic programs gloss over is scene size-up. Before you touch a patient, you need to scan for electrical hazards, chemical exposure, traffic, aggression, or structural instability. I once watched a trained responder walk straight into a kitchen where someone had collapsed, only to realize too late that the person had been using an oxygen concentrator and there was an open flame nearby. The response was correct in theory. The situation was not covered in the training module.
How to Actually Retain What You Learn
The retention curve on first aid skills is brutal. Studies consistently show that without active recall practice, CPR compression technique degrades significantly within three months. Bleeding control decision-making follows a similar pattern. This is why the standard three-year renewal cycle is arguably insufficient for anyone who doesn't deal with emergencies regularly. What works is spaced repetition with physical practice. Not reading about it. Actually doing it. Buy a cheap CPR manikin—there are decent ones for under fifty dollars—and practice compressions twice a month for five minutes. Set your phone reminder. It takes longer to forget than you'd expect. For bleeding control, practice wrapping a tourniquet on yourself or a partner. Time yourself. The goal is sub-two-minute application under minimal stress. When the real thing happens, your time will double or triple. There's also the question of what to carry. Most first aid courses include a brief discussion of kits, and then move on. The reality is that a properly assembled kit matters more than the knowledge itself in the first few minutes. I keep a small trauma bundle alongside my standard kit: a combat application tourniquet, Israeli pressure bandage, nitrile gloves, and a CPR face shield. The total cost is roughly eighty dollars. It fits in a jacket pocket. The standard first aid kit from any hardware store will not address catastrophic hemorrhage adequately.
Get the Full Details

Limitations of Standard Basic First Aid Training
I need to be straightforward about where this training falls short. Basic First Aid Training does not prepare you for pediatric emergencies unless you specifically take a pediatric add-on module. It does not cover anaphylaxis administration in depth—you'll learn that EpiPens exist but may not learn when to use them versus when to wait for EMS. It rarely addresses medical emergencies like strokes, heart attacks, or diabetic crises beyond recognition, which means you can identify them but your response options are severely limited. The biggest gap is psychological. No eight-hour course teaches you how to manage a panicked bystander, how to maintain authority in a chaotic scene, or how to handle the aftermath yourself. I've spoken to people who completed full first aid certification and later admitted they felt sick for days after their first real call. That's normal. It's also something the training industry essentially ignores. If you're looking for a concrete starting point, the St John Ambulance and Red Cross both offer solid introductory courses at roughly the 8-hour mark. If you want something more practical and less exam-focused, look into community-based courses run by organizations like the Australian Resuscitation Council or the European Resuscitation Council, which tend to spend more time on hands-on repetition. The certification is equivalent. The skill retention is measurably better.
There's no shortcut around the physical repetition. You can read every manual ever written on the subject, but until you've physically practiced chest compressions on a manikin until your own ribs feel tender, you don't actually know how hard to press. Until you've wrapped a pressure bandage on a friend's arm three times without being told what to do next, you don't know the sequence by muscle memory. That's the difference between having taken a course and being ready.