The Practical Scoring Process for the Beck Depression Inventory
Most people don't realize the BDI is straightforward to score until they've done it a few times and then have to grade a stack of forms by hand at 11pm on a Sunday. The inventory itself is 21 items. Each item presents four statements that reflect increasing severity of a particular symptom, and you assign a score from 0 through 3. The highest statement in each item cluster gets 3 points, the next highest gets 2, and so on. You add them all up and get a total between 0 and 63. That's the basic mechanism. It's not complicated, but getting it right requires attention because the wording between adjacent options is subtle.
BDI scoring works because each of the 21 depression domains—sadness, pessimism, past failure, loss of pleasure, guilt, punishment feelings, self-dislike, self-criticism, suicidal thoughts, crying, agitation, loss of interest, indecisiveness, worthlessness, energy changes, sleep disturbance, irritability, social withdrawal, body image changes, and work difficulty—has those four gradations built into the actual instrument. The original BDI from 1961 was revised in 1996 as the BDI-1A to update wording around suicidality and some other items. There's also a BDI-II from 1996 that aligns with DSM-IV criteria. The scoring logic is essentially identical across versions, but the individual item text differs, so you need to make sure you're using the right answer key for the version you have in front of you. Mixing up BDI-1A and BDI-II keys is something I've seen happen, usually by someone who grabbed the wrong form off a shared drive.
Understanding Beck Depression Inventory Scoring in Practice
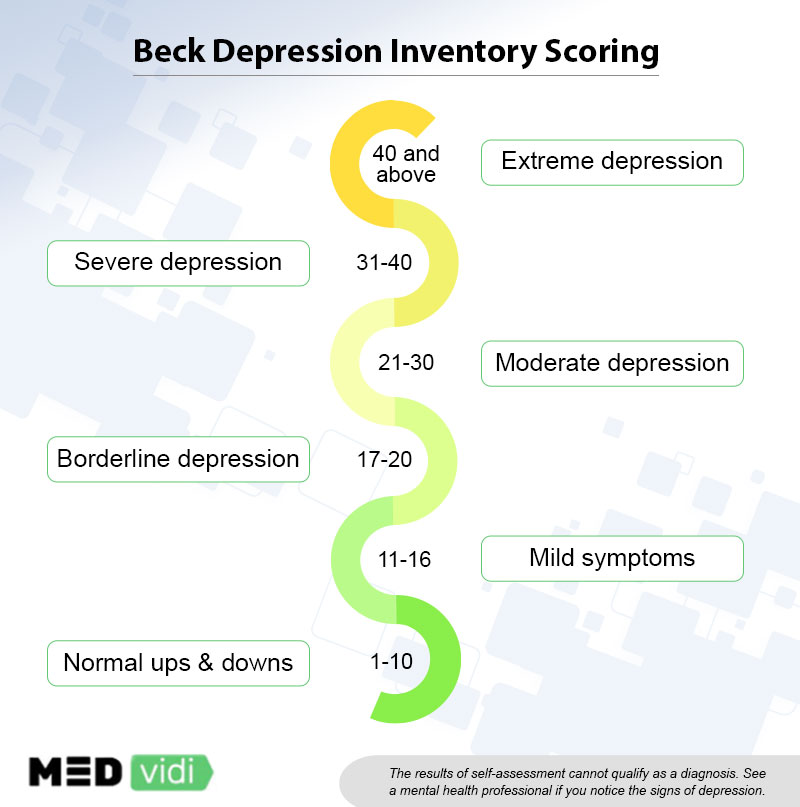
Here is how the actual scoring breakdown works. A total score from 0 to 13 is generally classified as minimal depression. Fourteen to 19 falls into the mild range. Twenty to 28 is moderate. Twenty-nine and above is severe. Those cutoffs come straight from Beck's original manual and are what almost every clinician and researcher uses. But the raw numbers only tell part of the story.
One thing most beginners miss is that item-level analysis often matters more than the total score. If someone scores a 22 overall but it's entirely driven by items about sleep disturbance and fatigue, that could point to a medical issue rather than primary depression. I learned this the hard way when I was reviewing data for a study and noticed a participant who scored in the severe range but had zero endorsement on the cognitive-emotional items—everything was concentrated in the somatic cluster. When we pulled their medical records, they had untreated hypothyroidism. The BDI picked up the symptoms but couldn't distinguish the cause. That's a genuine limitation of the instrument, and it's worth keeping in mind before you hand a score to a diagnostician and walk away.
Another edge case that trips people up involves reverse-scored thinking. The BDI doesn't use reverse-scored items, which is actually one of its design strengths compared to some other inventories. But what happens instead is more insidious. A client might select the highest severity option on several items in a row without reading carefully, a pattern called acquiescence bias or straight-lining. I encountered this once with a respondent who put "3" on literally every single item except one, where they accidentally wrote a "2." The total came out to 62, which is as high as it gets. When I went back and reviewed the responses with them, they'd essentially speed-read through the whole thing and clicked through without engaging with the content. The fix was straightforward—administer the test in a controlled setting with a brief instruction period that emphasizes taking time with each item, and flag any form where more than six consecutive identical responses show up. That pattern alone should trigger a retest or at least a clinical note.
For scoring efficiency, if you're processing large batches, an automated scoring sheet or a simple spreadsheet with conditional formatting saves a tremendous amount of time. I built a Google Sheets script that takes raw item responses and outputs both the total and the subscale breakdown in about three seconds per form. Doing it by hand, especially when you're working through 50 or 100 responses in a research context, takes considerably longer and introduces a real risk of arithmetic errors. A single transcription mistake—an "8" written instead of a "3" on one item—can shift a score from the moderate range into the severe range, which changes clinical interpretation. Double-checking at least 10 percent of manually scored forms against the originals is standard practice in most research labs, and it should be treated as non-negotiable.
The BDI has known limitations that anyone using it seriously needs to acknowledge. It overidentifies depression in medically ill populations because somatic symptoms overlap heavily with many physical conditions. It's less validated in older adults, where depression often presents differently. Cross-cultural applicability is restricted—certain items about guilt and self-dislike carry cultural weight that doesn't translate uniformly. And it's a self-report measure, which means it's subject to everything that goes with that: intentional underreporting by people who don't want to appear vulnerable, overreporting by people who feel their suffering should register as something more, and everything in between.
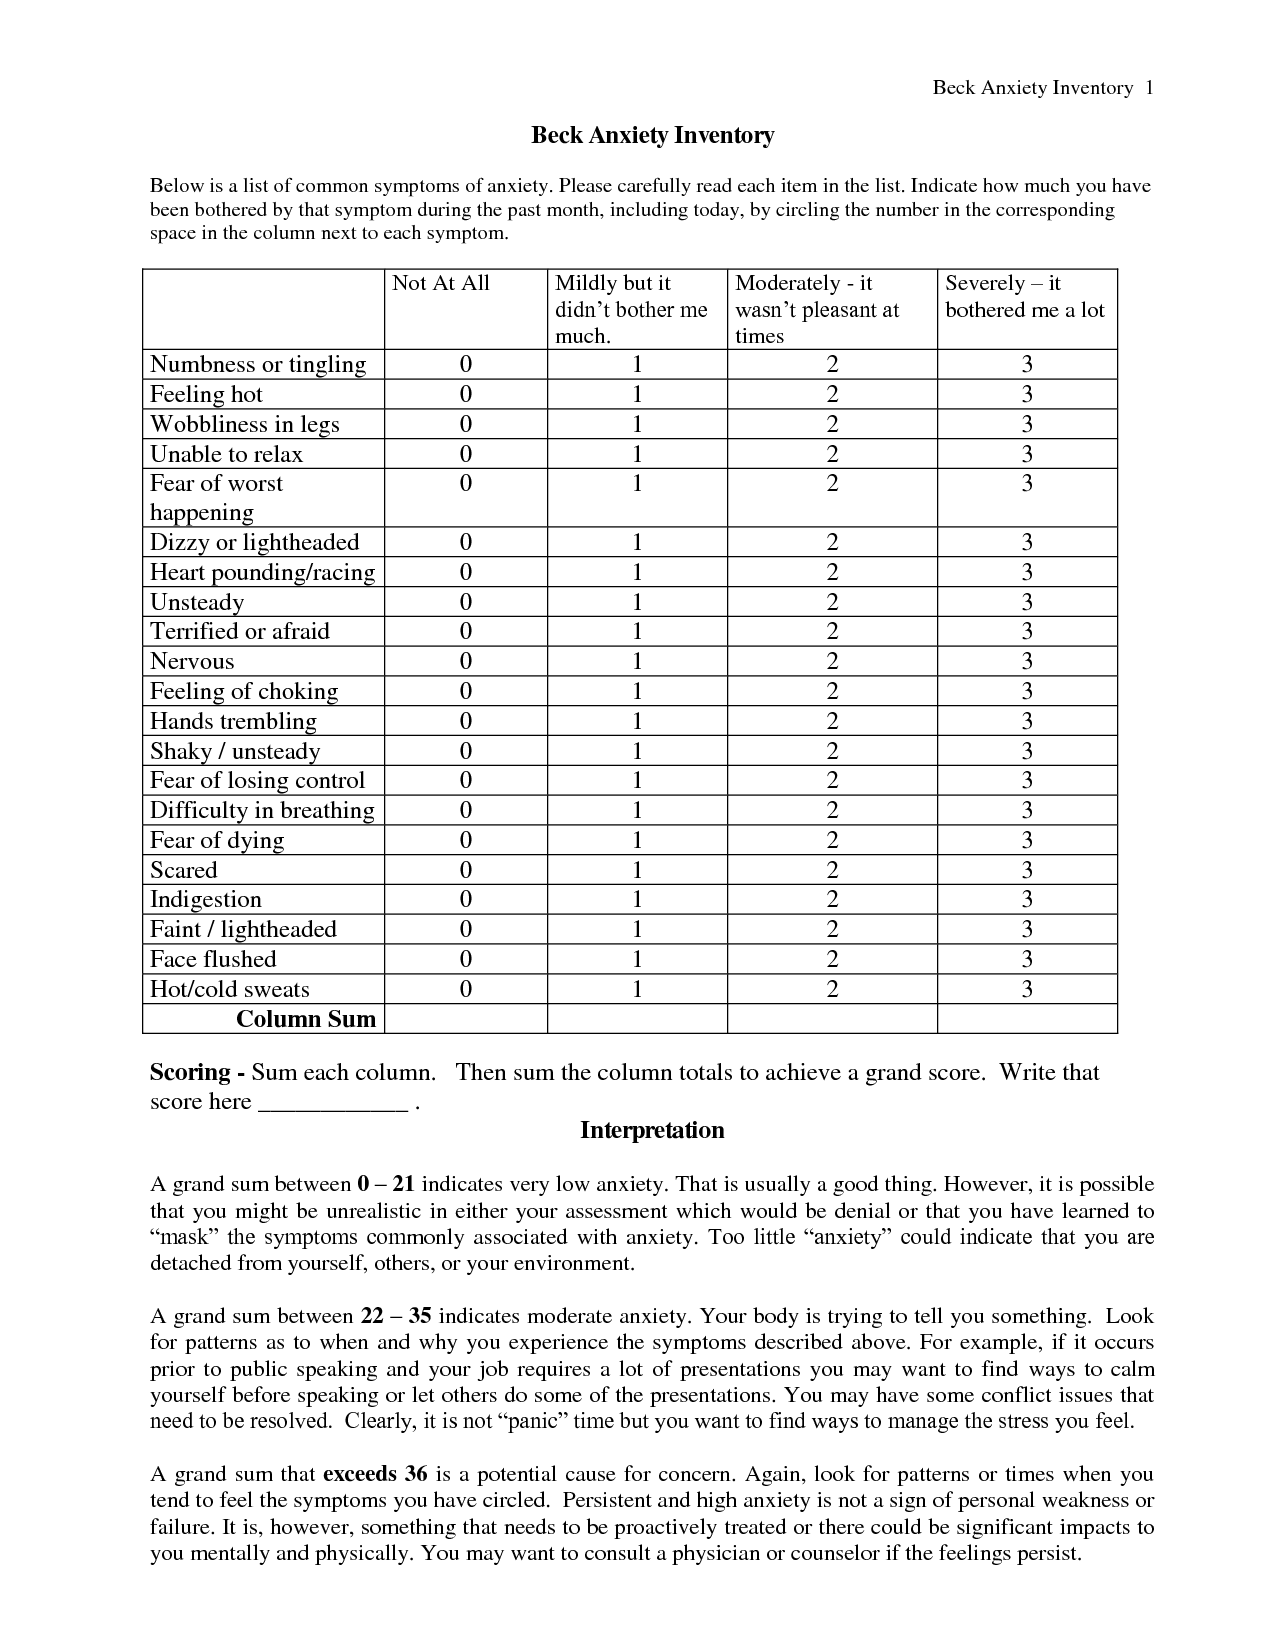
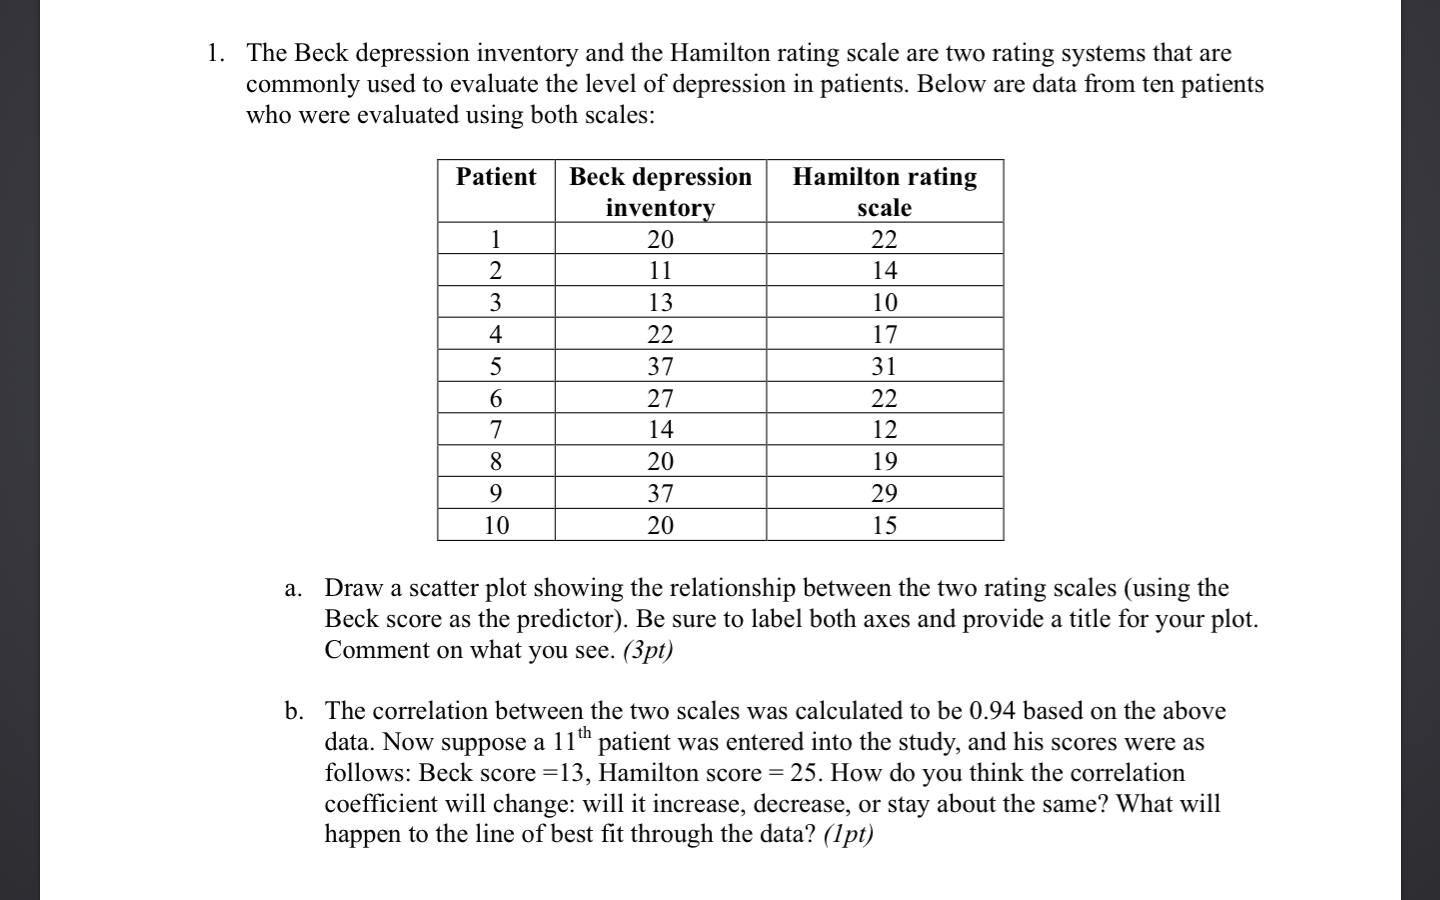
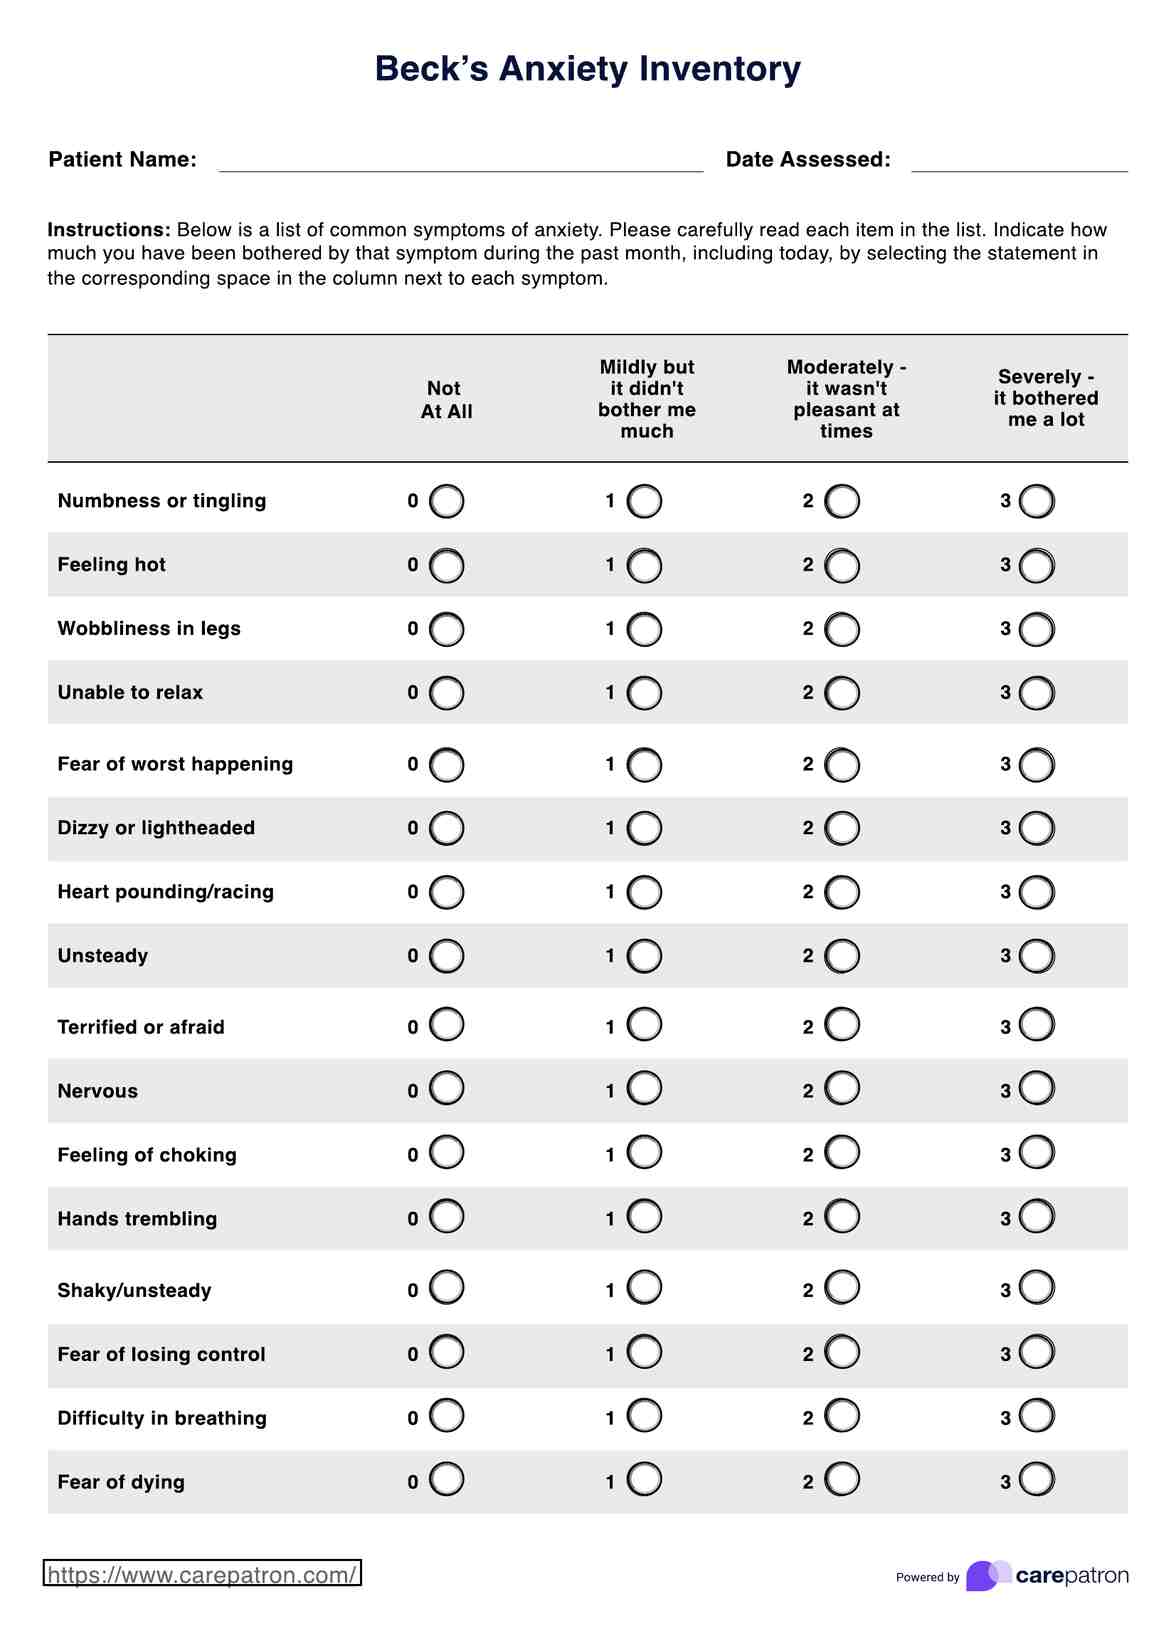
If you need something more comprehensive for differential diagnosis, the Beck Depression Inventory paired with the Beck Anxiety Inventory (BAI) gives you a clearer picture because anxiety and depression symptoms overlap substantially and each instrument captures different variance. For structural assessment, some researchers supplement with the Hamilton Depression Rating Scale, which is clinician-administered and tends to weigh somatic items differently. None of these alternatives are perfect either, but they each expose different blind spots.
Where to Access Scoring Materials
The BDI is a copyrighted instrument owned by Pearson. You can't legally distribute the full questionnaire or official scoring keys without a license. The scoring guide itself—the table that maps each item's four options to their point values—is typically included in the test manual that comes with a licensed copy of the instrument. If you're a student or researcher looking for practice, many university psychology departments keep copies available through their testing labs, and some professor's course websites post sample scoring sheets for educational use. For clinical or research purposes, you purchase the kit from Pearson or an authorized distributor, and it includes the full instructions, the items, the scoring sheet, and the normative data you'd need for interpretation.
The scoring process itself takes roughly 30 to 45 seconds per form once you're familiar with the layout, and about 8 to 12 minutes if you're scoring a new batch and cross-referencing the answer key. For a single administration, the client takes about 5 to 10 minutes to complete the inventory. That speed is one reason it remains widely used despite being nearly seven decades old—nobody wants to administer a 40-item battery when a 21-item one gives them clinically useful data in a tenth of the time.