What Actually Matters When You're Coding Behavioral Health Claims
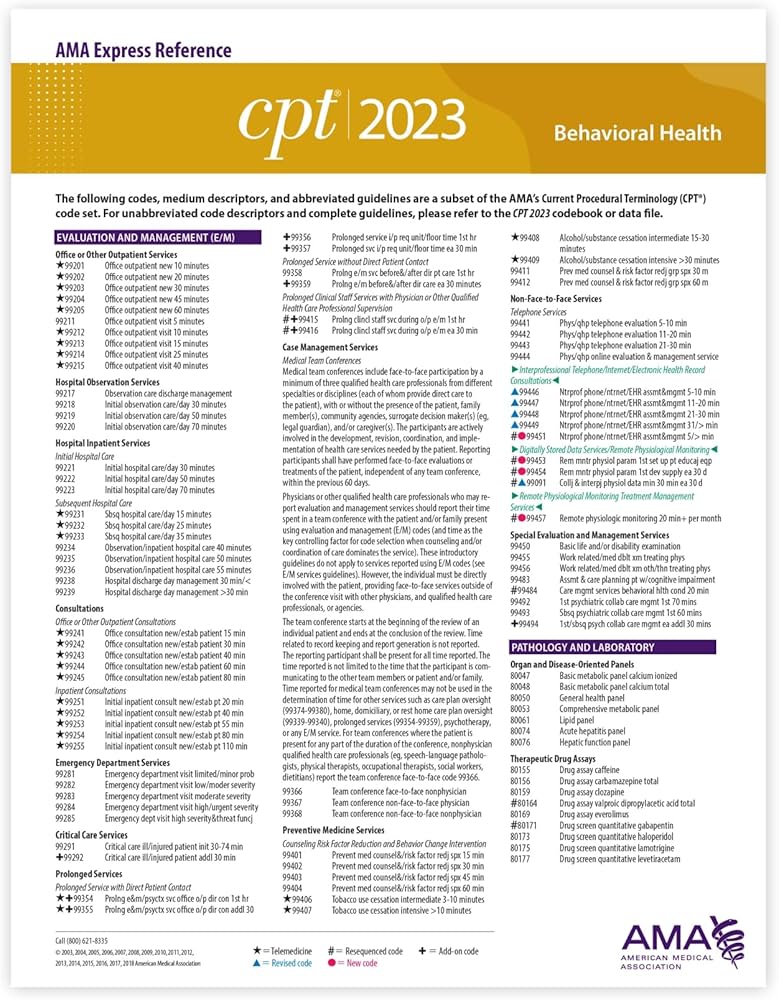
I spent three years in a private practice billing mental health claims before moving into auditing. The codes themselves aren't the hard part. What's hard is knowing which one to pick when the session ran long, when you switched modalities mid-visit, or when the payer insists on a different modifier than the one you've been using for two years. A good Behavioral Health Cpt Codes Cheat Sheet 2023 doesn't just list codes. It maps them to real scenarios you'll actually face. Most cheat sheets online are just tables copied from the CPT manual. Useless for day-to-day work. The useful ones show you the decision points. I'm going to walk through the codes I use every single week, the ones that trip people up, and the edge cases where a wrong code means a denial you won't catch until you're chasing the check.
Behavioral Health Cpt Codes Cheat Sheet 2023: The Core Assessment Codes
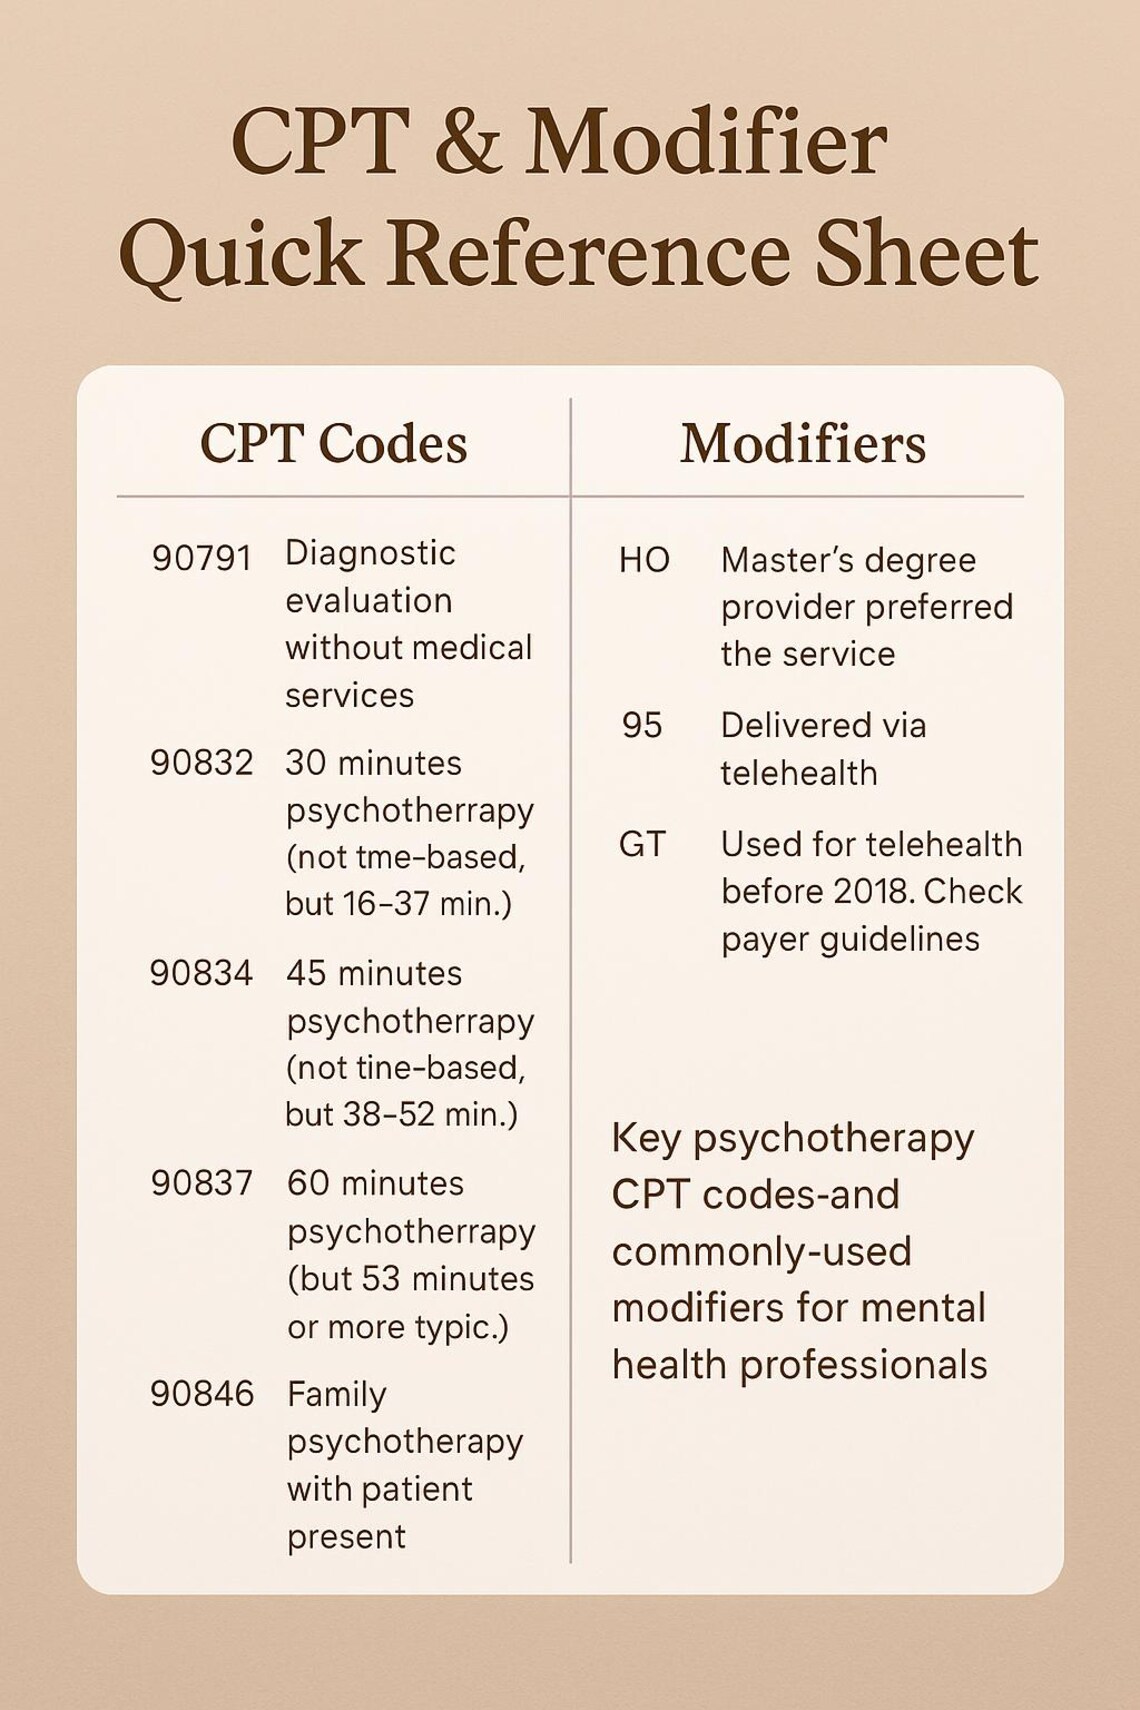
Psychiatric diagnostic evaluation (90791) and psychotherapy (90832 through 90838) are the backbone. Everything else branches off them. The diagnostic evaluation is a one-time intake-style assessment. No therapy happens during that encounter. If you even casually touch on treatment during a diagnostic eval, payers will flag it. I had a provider who billed 90791 alongside 90834 in the same session because the patient started processing trauma during the assessment. Denied on both. The fix is documentation discipline. If treatment begins, you bill psychotherapy from the start. Period. Now the psychotherapy codes. 90832 is 30 minutes, 90834 is 45 minutes, 90837 is 60 minutes. The time thresholds matter. CMS and most private payers follow the mid-point rule. For 45-minute billing, the service has to be at least 38 minutes. For 60-minute billing, it has to be at least 53 minutes. This isn't a suggestion. I audited a clinic that was routinely billing 90837 for 50-minute sessions because they "felt" it was close enough. Three denials in a row. They cleaned it up by adding a time-stamp column to their documentation template. There's also the psychotherapy-plus-diagnostic code 90838 and 90839. These are for when you're doing both a diagnostic evaluation and psychotherapy in the same session. That's rare in standard outpatient practice but common in inpatient and partial hospitalization settings. The time thresholds are different here because the diagnostic component is folded in. 90838 requires 45 to 75 minutes total. 90839 requires more than 75 minutes. Confusing these with the standalone therapy codes is the most common mistake I see.
The Drug and Alcohol Codes People Get Wrong
90832 through 90837 also exist in the substance use context, but there are separate codes under the 94xxx range and the 90xxx range that people miss. Alcohol and drug testing with interpretation is 80912 if you're ordering the test and 93042 for ETOH confirmation. These are lab codes, not psychotherapy codes. Billing them under a behavioral health NPI without the correct lab-facing CLIA waiver sometimes causes friction. The more important codes for substance use are the psychotherapy ones paired with addiction counseling. I've seen providers try to use 90837 for a group addiction session. That's not how it works. Group psychotherapy is 90846. You need at least two patients plus one or more therapists. Minimum time is 45 minutes. If you're running a 60-minute groups session with three patients and a co-therapist, that's 90846, not 90837. Mixing those up is an audit red flag. Family psychotherapy (90847) is another code that gets misplaced. It requires the therapist plus at least one family member who is involved in the patient's treatment. The patient doesn't have to be present for 90847, which surprises a lot of people. I worked with a clinician who refused to use it because she thought the patient had to be in the room. She was leaving money on the table for those sessions where parents were doing conjoint work with an adolescent but the teen was in the waiting area.
Get the Full Details

Behavioral Health Cpt Codes Cheat Sheet 2023: Time-Based Complexity
Let me tell you about a specific problem I ran into last year that most cheat sheets don't address. A provider was billing 90837 for a 62-minute session but the EHR flagged it as 58 minutes. Two patients argued about what the actual time was. One said the session ran long because the patient brought up a crisis. The other said they wrapped up early. The payer requested a recording. There wasn't one. The workaround was straightforward but painful. We implemented a policy where the therapist enters the start and end time directly into the note before closing the encounter. No retrospective edits allowed. If the session genuinely runs long past the planned time, you document the extension in real time and recalculate. That single change eliminated our time-discrepancy denials within 60 days. Another nuance that barely anyone talks about: the add-on code 90833 for EMDR therapy. It's billed alongside a primary psychotherapy code, not standalone. You pair it with 90834, 90837, or the appropriate base code. If you're doing EMDR for 45 minutes and billing only 90833, you'll get denied. It's an add-on, not a primary. I've seen this happen repeatedly with newer clinicians who read that EMDR has its own code and assumed it replaced the therapy code entirely.
The Telehealth Codes That Changed and What Stuck
Telehealth billing during COVID was chaos. Some of it settled. Some of it didn't. The key telehealth modifier is GT (or POS 02 depending on the payer). For behavioral health, the same psychotherapy codes apply whether in-person or remote. 90834 is 90834 whether you're in the same room or on a HIPAA-compliant video platform. The catch is that not all payers cover telehealth for all behavioral health services. Medicare expanded coverage significantly during the public health emergency and has kept a lot of it. Private payers vary. I had a case where a commercial plan denied a 90837 telehealth claim because the patient was in a state where that payer didn't have telehealth reciprocity. The patient had traveled for a family wedding and the provider hadn't verified cross-state coverage. Always check the payer's telehealth matrix before the first remote session. A quick call to the provider services number takes two minutes and prevents a $200 denial. Also worth noting: the audio-only telehealth codes. Most behavioral health services require visual interaction. Audio-only is generally not covered for psychotherapy CPT codes. There are exceptions for certain evaluation and management codes in primary care, but for 90832 through 90839, both parties need to see each other. Payers are enforcing this more strictly now that the emergency flexibilities are winding down.
Precertification and the E/M Override Situation
Here's something that will save you headaches. Many behavioral health services require precertification. The length-of-stay or number-of-session caps are real. I've lost count of the claims denied because a provider booked a 12-session course of treatment without checking if the authorization covered all 12. The auth came back for eight. The last four got denied as unauthorized. The workaround I recommend: build a precertification checklist into your intake workflow. Before the first session, verify the number of authorized sessions, the applicable CPT codes covered, the diagnosis requirements, and the expiration date. Write it down. Keep it in the chart. When the auth expires at session nine, you know by session seven that you need a renewal. There's also the crossover between E/M codes and psychotherapy codes. If you're seeing a patient in a hospital setting and doing both a psychiatric assessment and a brief intervention, you might be looking at 992xx E/M codes rather than 908xx psychotherapy codes. The distinction matters for reimbursement rates. E/M codes with prolonged service add-ons (99356, 99357) can sometimes be more lucrative than the flat-rate psychotherapy codes, but they require documentation that meets the E/M level-of-service criteria. Most outpatient mental health clinicians don't document to E/M standards. If you want to bill E/M, you need to meet the history, exam, and medical decision-making requirements. That's a different skill set.

Behavioral Health Cpt Codes Cheat Sheet 2023: Quick Reference
90791 - Psychiatric diagnostic evaluation, no medical components 90832 - Psychotherapy, 30 minutes 90834 - Psychotherapy, 45 minutes
90837 - Psychotherapy, 60 minutes 90838 - Psychotherapy with eval, 45-75 min total 90839 - Psychotherapy with eval, >75 min total
90846 - Group psychotherapy, 45+ minutes 90847 - Family psychotherapy 90833 - EMDR add-on code

90845 - Psychiatric consultation, 60 minutes 90845 is the consultation code. It's different from 90791 because a consultation is at the request of another provider. A diagnostic evaluation is initiated by the treating clinician. The distinction matters to payers who require a referral letter for consultation codes. I've had claims held because there was no consult request on file for a 90845. The fix is making sure the referring provider's request is documented in the chart before the encounter.
Where Cheat Sheets Fail You
A static document can't handle the reality of coding. The CPT manual changes every year. ICD-10 code sets change too. Payer policies change quarterly. A Behavioral Health Cpt Codes Cheat Sheet 2023 is useful as a starting reference, but it's not a substitute for checking current payer guidelines and the annual CPT updates. The 2023 edition won't help you with a 2024 claim denial. Keep your sources current. The biggest limitation of any cheat sheet is that it can't account for payer-specific variations. Medicare might cover telehealth psychotherapy in all 50 states. A regional PPO might only cover it in the state where the provider is licensed. Medicaid varies by state. Commercial plans vary by plan type. The codes are the same across all payers. The coverage is not. Always verify coverage before you render the service, not after you submit the claim.