Setting Up Behavioral Interventions in a Psych Ward
I spent four years on a locked acute psychiatry unit, and if there is one thing that separates staff who survive from staff who burn out in six months, it is understanding how to actually deliver behavioral therapy without turning it into a paperwork exercise. Most nursing programs give you a textbook definition and move on. The reality on the floor is different. When a patient with borderline personality disorder refuses to participate in group therapy because they believe everyone is staring at them, or a patient with schizophrenia keeps pacing the hallway at 2 AM because their thoughts feel too fast to sit still, you cannot just document "non-compliant" and walk away. You have to figure out what behavior is being reinforced, what trigger started it, and what you can realistically change in a 15-minute interaction between med passes. This is where the Behavioral Therapy Definition In Mental Health Nursing becomes something other than a term on an exam. It is the operational framework you use every shift to observe, measure, and modify behavior in patients who may not have the cognitive capacity or emotional regulation to do it themselves.
Behavioral Therapy Definition In Mental Health Nursing
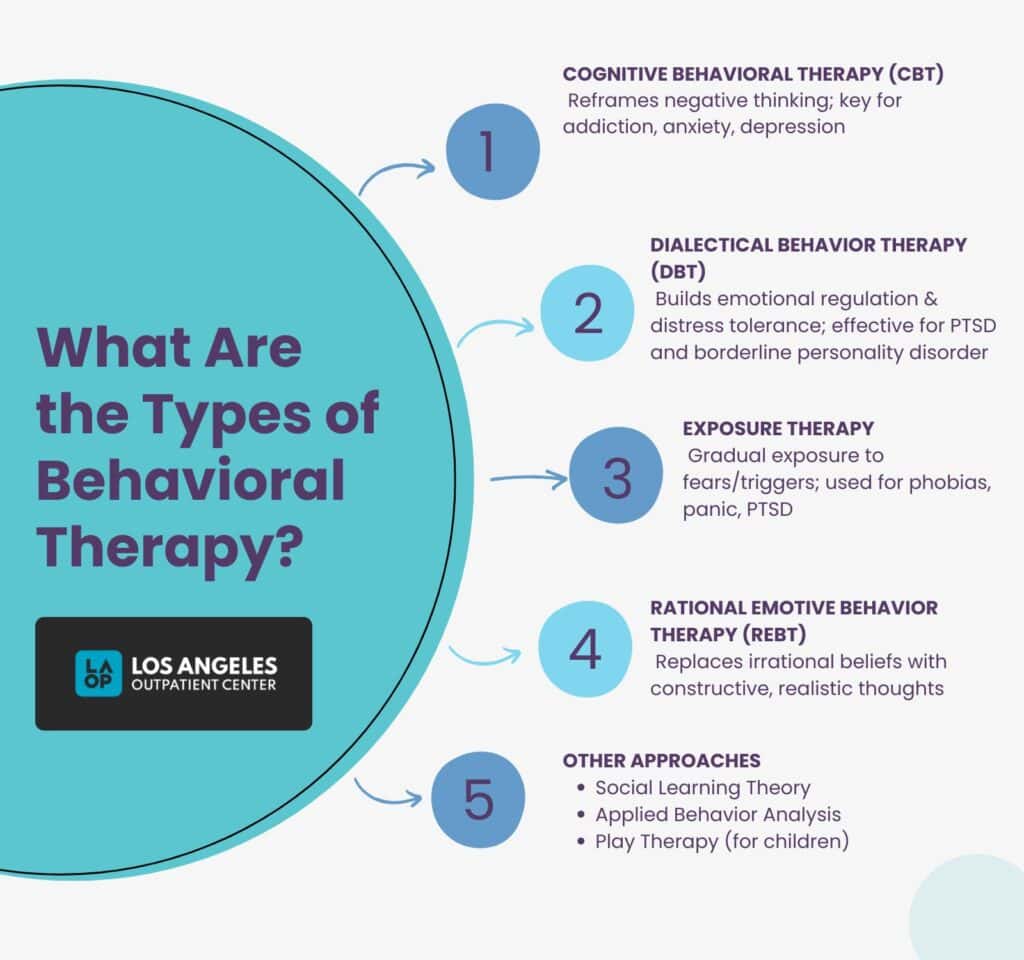
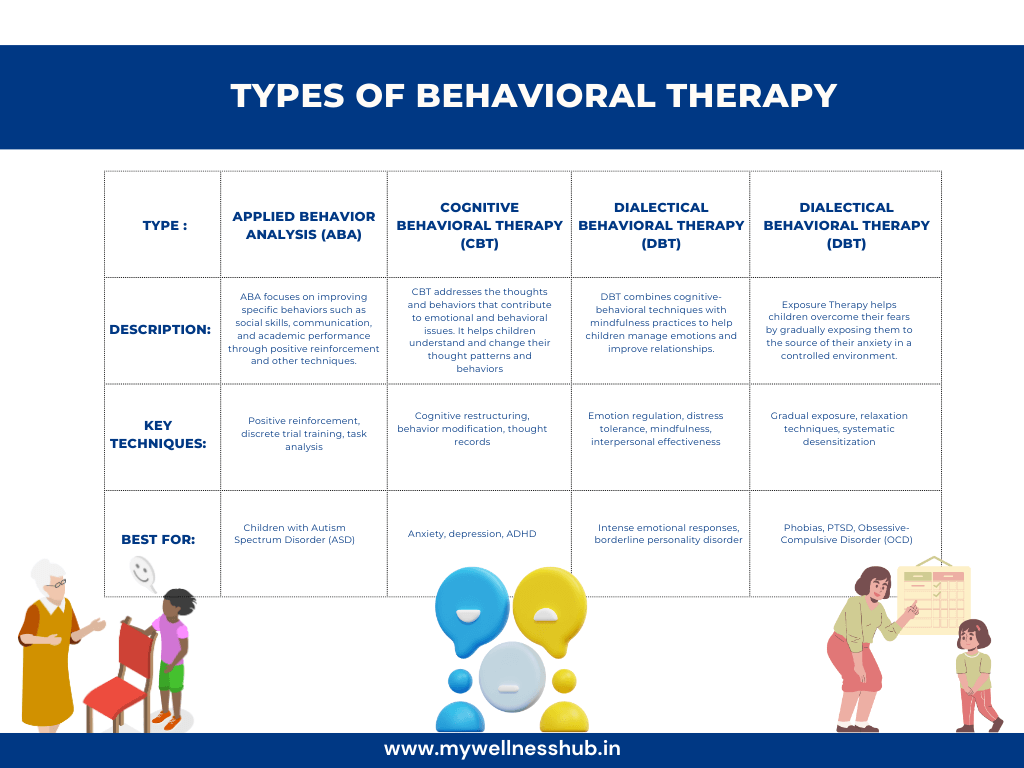
At its core, behavioral therapy in mental health nursing is the systematic application of learning theory principles to assess, intervene, and evaluate observable patient behaviors within a therapeutic context. It is not talk therapy. It is not insight-oriented exploration. It is grounded in classical conditioning, operant conditioning, and social learning theory, and it requires the nurse to act as both observer and active intervention agent. The definition sounds academic until you are standing in a day room watching a patient with OCD count every floor tile before crossing a threshold, and you need to decide whether to redirect them, enforce a unit rule, or document an escalation. The framework tells you which move to make and why. Here is how it works in practice. You start with a functional behavioral assessment. You identify the antecedent, the behavior itself, and the consequence. I once had a patient whose aggressive outbursts always happened after dinner during the shift change. The antecedent was not the food or the noise. It was the staff transition. Two nurses left, two new nurses arrived, and the patient who had developed a secure attachment to the departing staff experienced an acute abandonment response. The behavior was aggression. The consequence was usually that staff retreated and gave him space, which inadvertently reinforced the outburst by removing the demand for social interaction.
The workaround was simple but counter-intuitive. Instead of giving him space after the outburst, we maintained a calm, consistent presence and redirected him to a structured activity while the new staff introduced themselves during a low-arousal period before the shift change. We also scheduled his most demanding therapeutic interactions during the overlap hours when the familiar nurse was still present. The outbursts dropped by roughly 70 percent over three weeks. This is behavioral therapy in action. You are not analyzing childhood trauma. You are manipulating environmental variables to change behavioral outcomes. The nursing process integrates this through the ADPIE framework adapted for behavioral measurement. Assessment includes baseline behavioral data collection using tools like the Behavioral Observation Scale or simple frequency counts. Diagnosis translates into nursing diagnoses such as "ineffective coping related to inability to modulate impulsive behaviors." Planning establishes measurable behavioral targets with clear criteria for success. Implementation involves the actual interventions, which can range from contingency management and token economies to systematic desensitization and behavioral activation. Evaluation measures whether the target behavior changed against the predetermined criteria. One thing most beginners miss is that behavioral therapy in nursing is not limited to patients with behavioral disorders. It is equally critical for patients with dementia, severe depression, autism spectrum disorder, and acute psychosis. A patient with depression who has not left their bed in four days is a behavioral problem that requires behavioral intervention. The intervention might be behavioral activation, starting with a goal as small as sitting on the edge of the bed for five minutes, then gradually increasing duration and complexity. You do not wait for the patient to "feel motivated." Motivation follows action in behavioral models, not the other way around.
Get the Full Details

Another counter-intuitive point is that reinforcement is not the same as praise. Positive reinforcement in a clinical setting means delivering a meaningful consequence immediately after the target behavior occurs. Praise alone is often insufficient because it is abstract and delayed. A patient with severe antisocial traits may respond better to concrete privileges like extended visiting time or choice of meal timing than to verbal encouragement. The key is identifying what actually functions as reinforcement for that individual, which requires observation and trial rather than assumption. There are significant limitations to be aware of. Behavioral therapy is highly dependent on staff consistency, and on a busy unit with high turnover and float staff, maintaining that consistency is nearly impossible. If one nurse is using a token economy and another is inadvertently reinforcing the same problematic behavior through attention, the intervention collapses. Environmental factors like noise, overcrowding, and understaffing can also undermine behavioral protocols regardless of how well they are designed. Additionally, behavioral therapy has limited effectiveness for patients whose behaviors are driven by organic causes such as delirium, substance withdrawal, or neurological conditions. In those cases, the behavior is a symptom of physiological disturbance, and behavioral interventions alone will not resolve it. Medical stabilization must come first.
For patients with complex trauma histories, purely behavioral approaches can feel dismissive and may damage the therapeutic alliance. In those situations, behavioral therapy should be integrated with trauma-informed care principles, which means ensuring that interventions do not replicate dynamics of control or punishment that the patient has experienced previously. The documentation side is where most nurses struggle. Behavioral therapy requires precise, objective documentation. Writing "patient was agitated" is useless. Writing "patient paced hallway 12 times in 10 minutes, refused verbal redirection on two occasions, elevated heart rate to 110, and returned to baseline after administration of PRN lorazepam 0.5 mg" is measurable data that tracks behavioral change over time. This level of documentation is time-consuming, and I will not pretend otherwise. It adds roughly 10 to 15 minutes per patient per shift to your charting load. But it is also what makes your interventions defensible and your progress trackable. If you are entering mental health nursing and want to build competence quickly, focus on mastering the ABC model first. Antecedent-Behavior-Consequence. It is simple enough to apply in real time and powerful enough to reveal patterns that are otherwise invisible. Start by observing one patient for an entire shift and mapping their behavioral episodes onto an ABC chart without intervening. You will be surprised by how many behaviors have predictable triggers and predictable payoffs. Once you see the pattern, you can begin to disrupt it.
The skills you develop through behavioral therapy work translate across every setting in mental health nursing. Whether you end up in crisis intervention, outpatient clinics, correctional mental health, or community psychiatry, the ability to analyze behavior functionally and intervene systematically is one of the most reliable tools you will have. The theory is straightforward. The execution requires patience, consistency, and a willingness to treat every patient interaction as potential data.